Listening to S3 and S4 Heart Sounds Is Harder Than Textbooks Make It Sound
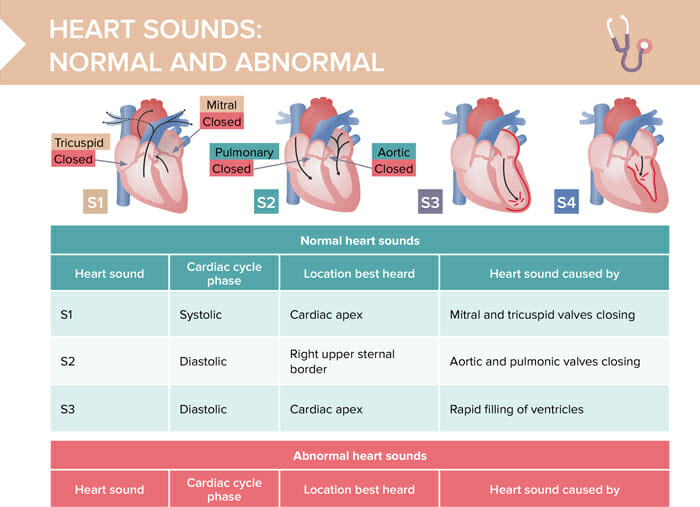
The heart makes two extra sounds that you can hear with a stethoscope if you know what you're looking for. S3 and S4 are low-frequency events that happen close together in the cardiac cycle, which is exactly why they get confused with each other all the time. Beginners will tell you one is early diastole and one is late diastole, but that's not helpful when you're actually standing at a patient's bedside trying to figure out which rumble you're hearing is which. S3 occurs during the rapid filling phase of diastole, right after S2. It's produced when blood slams into a ventricle that's already starting to fill. S4 happens just before S1, during atrial contraction, when the atrium pushes blood into a stiff ventricle. Both are vibrations that you feel more than hear at first. The frequency range matters here. Both sounds sit below 50 Hz, which means the bell of your stethoscope is the only tool that picks them up reliably. The diaphragm will filter most of that out and you'll be sitting there wondering why you can't hear anything. Light contact with the skin is essential. If you press the bell hard enough to stretch the skin, you're basically turning it into a diaphragm and those low frequencies disappear.
How to Actually Differentiate Them in Practice
Timing is everything, and timing is also the hardest thing to nail when you're still learning. S3 comes right after S2 with no gap worth noting. S4 comes right before S1. The trick is finding S1 and S2 first, which sounds obvious until you're dealing with a tachycardic patient where the intervals between everything compresses down to barely anything. I spent about six months regularly missing S4 because I kept mistaking it for an S3. The breakthrough came when I started focusing on the carotid pulse simultaneously. The carotid upstroke lines up with S1, and you can watch it happen while listening. When the low sound comes after the carotid peak, it's S4. When it comes well after the S2 point, it's S3. This visual-tactile feedback loop reduced my error rate significantly. There's another trick that isn't in any textbook. Have the patient roll onto their left side and bring the leg slightly up toward the chest. This position concentrates the apical impulse toward the chest wall and makes both S3 and S4 louder. I use this for every patient where I suspect either sound. It usually takes maybe 20 seconds and makes the difference between hearing nothing and clearly identifying the rhythm.
When These Sounds Appear and What They Mean
S3 is normal in children, adolescents, and pregnant women. It's also normal in well-trained athletes. In those populations, it's called a physiologic S3 and means nothing alarming. In adults over 40, an S3 is almost always pathologic and suggests volume overload or systolic dysfunction. Think congestive heart failure, dilated cardiomyopathy, severe mitral regurgitation. An S3 in a 65-year-old with dyspnea is basically a red flag you shouldn't ignore. S4 is almost never normal in adults. It indicates a stiff, non-compliant ventricle. Hypertension, hypertrophic cardiomyopathy, aortic stenosis, ischemic heart disease - these are the usual suspects. The ventricle has lost its compliance and the atrium has to push harder to get blood in. That push creates the S4. Atrial fibrillation eliminates S4 because there's no atrial contraction. If you hear an S4 in a patient with AFib, stop and reconsider your assessment. Both sounds can occur together, which is called a quadraphonic rhythm or gallop rhythm. When you hear four distinct sounds instead of the normal two, that's S1, S2, S3, and S4 all firing in sequence. This is clinically significant and warrants further workup regardless of which underlying condition is causing it.
Get the Full Details

Common Pitfalls That Make You Miss These Sounds
Room noise is a bigger problem than most people admit. I once spent ten minutes trying to identify an S4 in a busy emergency department hallway and couldn't hear a thing. Walking the patient to a quieter side room took about 30 seconds and made the sound immediately apparent. Don't skimp on the environment. Obese patients or those with thick chest walls present a real challenge. The low-frequency energy dissipates before it reaches the stethoscope. In these cases, position the bell directly over the point of maximal impulse and lean into it a bit more than usual, but not so much that you occlude the skin. Sometimes you need to ask the patient to take a deep breath and hold it on expiration. This pushes the heart closer to the chest wall and can make marginal sounds audible. Another issue that catches people off guard: S3 can sometimes sound like a tumor plop from a cardiac myxoma. The timing is similar but the clinical context is completely different. A myxoma plop usually changes with position, which is a useful distinguishing feature. If the sound moves or changes intensity when you reposition the patient, think about structural causes rather than just volume overload.
Electrocardiogram correlation helps a lot. If you have a concurrent ECG, the P wave preceding an S4 is a dead giveaway. The sound sits right after the P wave and right before the QRS complex. This removes all ambiguity about timing and makes identification nearly foolproof when the ECG is available.
Limits of Bedside Auscultation
Here's the honest part that nobody wants to hear: even experienced clinicians miss S3 and S4 a significant portion of the time. Studies show interobserver agreement for S3 detection hovers around 60 to 70 percent, and S4 is even worse. Your ears are useful but they're not infallible. If you're unsure, echocardiography will show you the ventricular function and compliance issues that produce these sounds directly. Don't let pride keep you from ordering the confirmatory test. Doppler echocardiography also lets you see the actual filling patterns. Early diastolic filling corresponds to S3, and late diastolic filling with atrial kick corresponds to S4. This visualization approach removes the guesswork entirely and gives you quantitative data about what the sound represents hemodynamically. The bottom line is that S3 and S4 are clinically important but technically difficult to detect consistently. Practice on as many patients as possible, use the left lateral decubitus position every time, correlate with the carotid pulse or ECG when available, and accept that sometimes you need imaging to be sure. The sounds themselves don't change, but your ability to hear them definitely does with experience.