What You Actually Need To Know About The Sagittal Plane
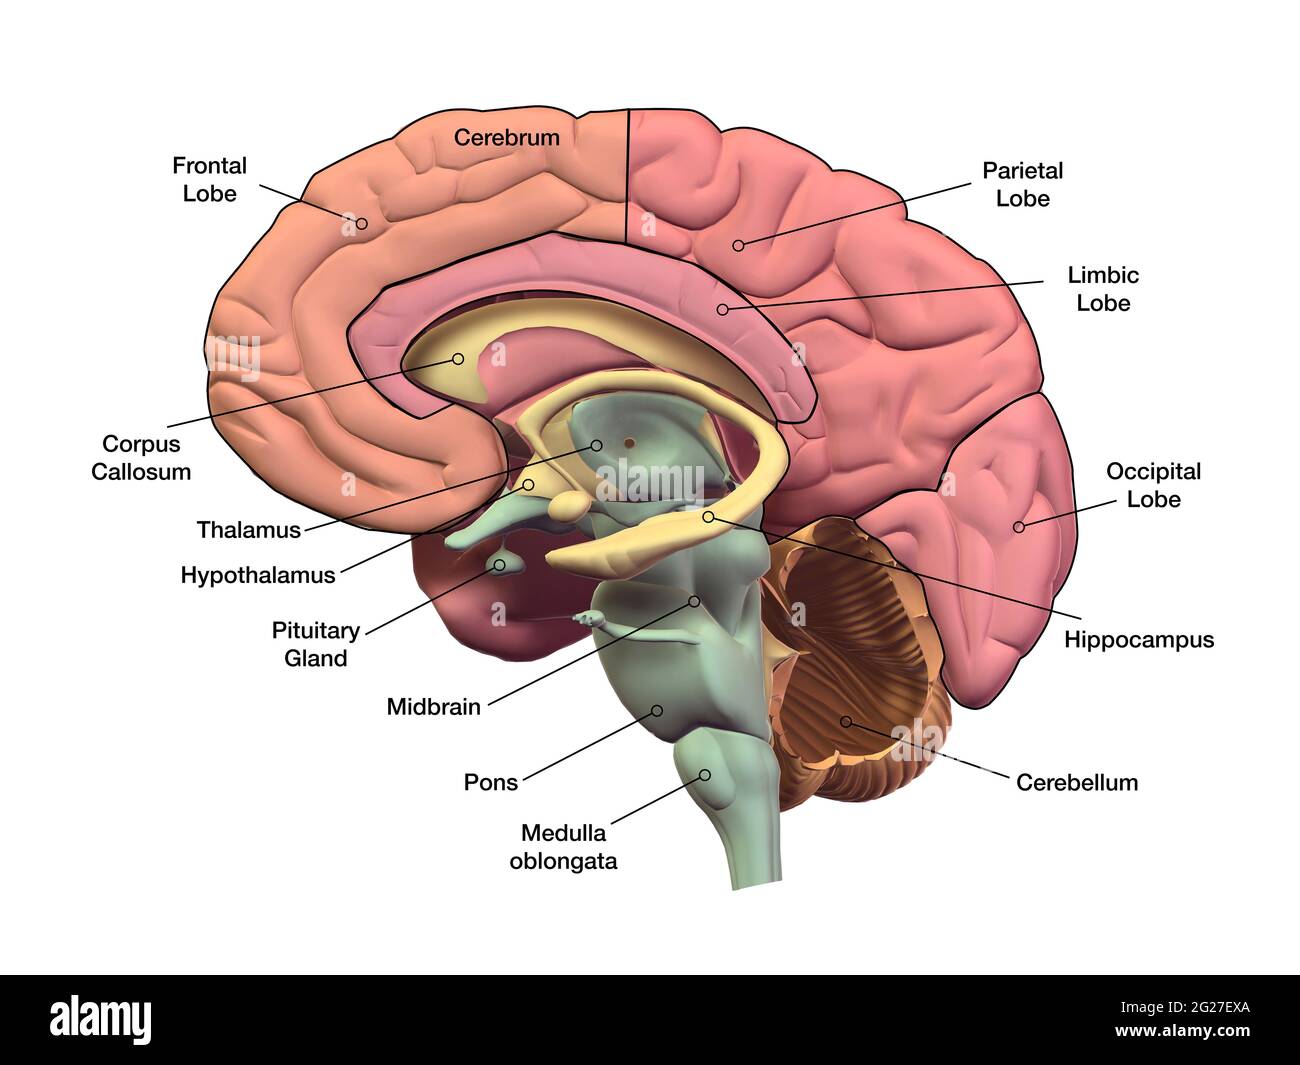
The sagittal plane is a vertical cut that divides the brain into left and right portions. It runs from front to back. A mid-sagittal cut goes right down the middle, splitting the hemispheres cleanly. Anything off-center but still parallel to that midline is just a parasagittal slice. Radiologists and anatomists use these planes constantly when reading MRI scans or looking at cadaver specimens. Most people learning neuroanatomy treat this like trivia for an exam. It isn't. If you are trying to localize a lesion on an imaging study or navigate surgical anatomy, understanding sagittal orientation is where things either click or fall apart completely. I have seen residents miss anterior communicating artery aneurysms because they could not mentally rotate the sagittal view fast enough during a scan review.
Sagittal Plane Of The Brain In Practice
When you look at a true mid-sagittal T1-weighted MRI, you should see the corpus callosum as a distinct C-shaped band arching over the ventricles. Below it sits the brainstem, and behind that the cerebellum. The pituitary gland rests in the sella turcica just beneath the hypothalamus. These landmarks exist in a specific spatial relationship, and disrupting that mental map causes errors. I spent years using these orientations to plan stereotactic biopsies, so I keep them very concrete in my head. The problem is that most textbook diagrams simplify the anatomy far too much. Real brains are asymmetric, and the sagittal plane does not always divide what you expect. The long axis of the lateral ventricle tilts slightly, and the septum pellucidum angles differently from patient to patient. This matters more than you would think when you are trying to correlate a sagittal image with axial and coronal slices. I ran into a specific issue about three years ago when I was reviewing diffusion tensor imaging tractography. The sagittal reconstruction showed what looked like a clean disruption of the cingulum bundle on one side. I initially read it as a traumatic injury. Then I re-oriented the volume using the true AC-PC line instead of relying on the scanner's default sagittal alignment, and the apparent discontinuity disappeared. The fiber tract was intact the entire time. The default scan alignment had been shifted by about two millimeters due to subtle head rotation during acquisition. That kind of error is invisible unless you actively check the midsagittal line against identifiable bony landmarks like the anterior and posterior commissures.
Another thing that tends to trip people up is assuming the falx cerebri defines the exact midline in every case. It usually does, but it can deviate significantly with mass effect, shrunken hemispheres from atrophy, or prior surgical intervention. If you are using the falx as your sole reference point for sagittal resection planning, you will occasionally end up a centimeter off from where you thought you were aiming. I always cross-reference the interhemispheric fissure with the nasal septum and the superior sagittal sinus position before committing to a trajectory. It takes about thirty seconds and prevents a class of errors that otherwise look plausible on a single plane. For anyone working with structural MRI data, the practical takeaway is straightforward. Acquire or request a high-resolution T1 sagittal series at isometric voxel size, ideally no thicker than one millimeter. Two millimeter slices work in a pinch, but you lose definition in smaller structures like the pituitary stalk and the dentate nucleus. Check the image quality yourself rather than trusting the technologist's preview screen, which often compresses the display to save time. Common pitfalls in sagittal interpretation
Get the Full Details

Slice thickness is the biggest source of partial volume error. When a one-millimeter slice happens to fall exactly between two gyri, the sulcal pattern looks deceptively simple. When it cuts through a gyrus, you get an artificially thick cortical ribbon. This is why radiologists always scroll through the entire sagittal stack rather than judging from a single midline image. Another issue is the assumption that every sagittal slice is symmetric between hemispheres. They are not. The right and left motor cortices differ in subtle ways, and the dominant hemisphere often shows slightly different perisylvian organization. If you are using sagittal images to infer contralateral anatomy, you are making an assumption that does not always hold. Sagittal imaging also has real limitations. It cannot reliably show lateralized pathology that does not distort the midline structures. Small meningiomas in the convexity may be completely invisible on a mid-sagittal view unless you examine the off-center parasagittal slices individually. Many people skip those peripheral slices because they assume the midline is representative. That assumption misses a significant number of lesions, particularly in the posterior parietal region where the sulcal anatomy is complex.
If you need a sagittal reformation from an existing volumetric dataset, most modern PACS workstations can generate it in under a minute. The standard approach is to take the axial T1 volume and reconstruct along the AC-PC plane. The accuracy depends entirely on how well the operator aligns the line between the anterior and posterior commissures. A two-degree angular error in that alignment introduces roughly four millimeters of positional drift at the level of the centrum semiovale. That drift is enough to misplace a target in radiosurgery planning. For research purposes or when you need precise quantitative measurements, the MNI152 standard space provides a normalized sagittal atlas that eliminates much of the individual variation problem. Several open-source tools can register your data to this space, though the registration itself introduces its own interpolation artifacts. If you are measuring something small, like hippocampal subfield volume, the registration error can exceed the actual biological difference you are trying to detect. The sagittal plane remains one of the most useful reference frames in clinical neuroimaging, but it is only as reliable as the care put into acquiring and interpreting it. The difference between a useful sagittal series and a misleading one usually comes down to slice thickness, alignment accuracy, and whether someone actually checked every slice in the stack instead of glancing at the midline. I still catch people making that last mistake, even among attending radiologists who should know better.