The awkward reality of Schizoid Personality Disorder Self Help
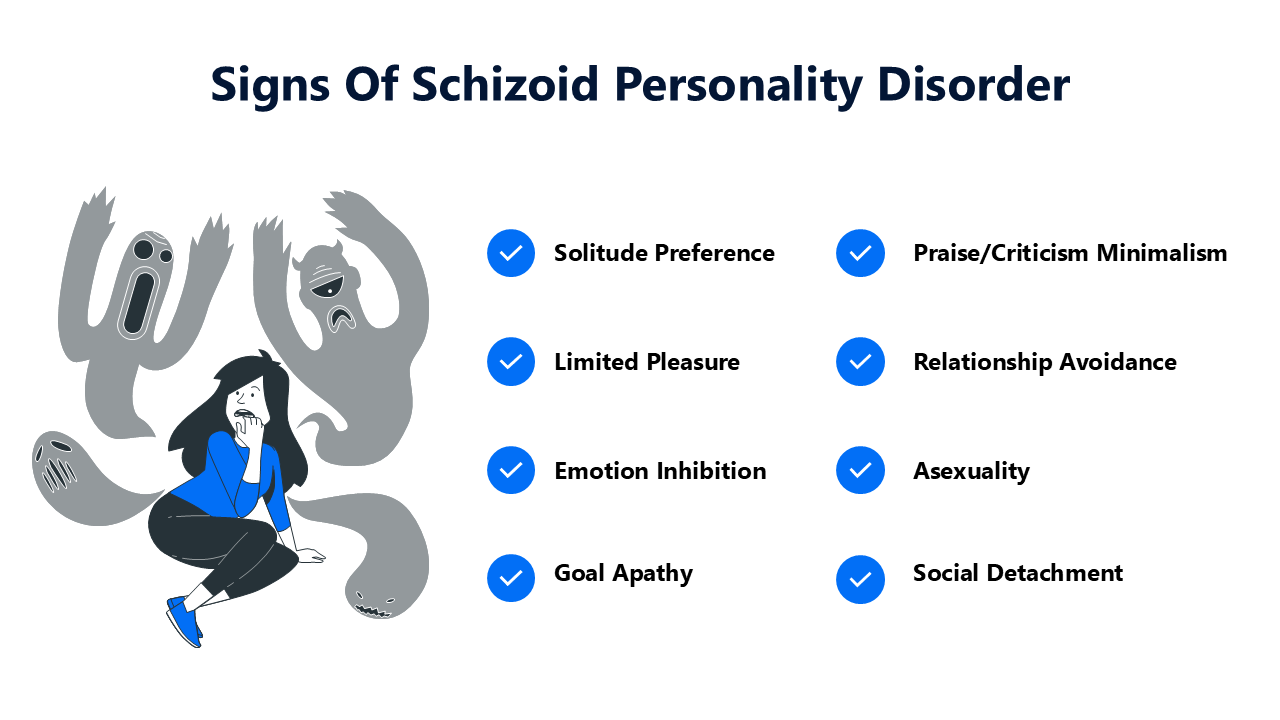
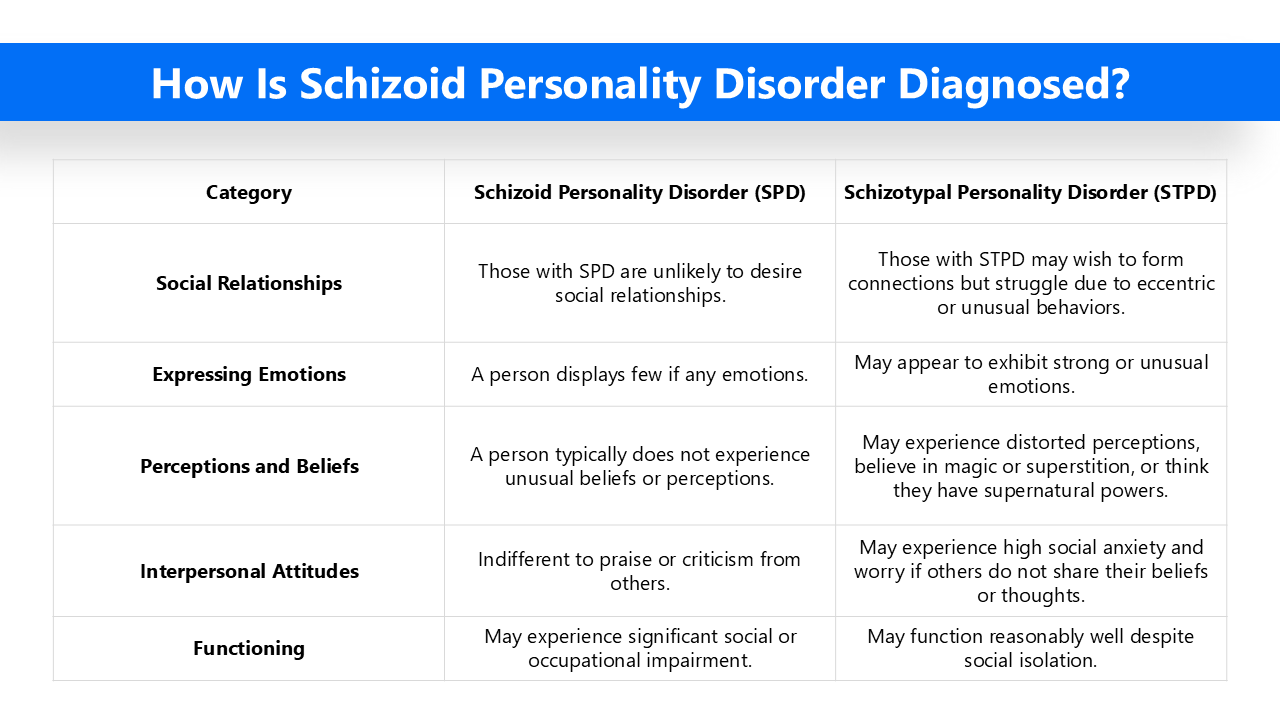
Most people think Schizoid Personality Disorder means you're just introverted. It isn't. It's a pervasive pattern of detachment from social relationships and a restricted range of emotional expression across contexts. The DSM-5 criteria include preferring solitary activities, little desire for close relationships, taking pleasure in few things, indifference to praise or criticism, and emotional coldness. Understanding that distinction matters because self-help approaches designed for social anxiety or shyness simply don't apply here and using them wastes time. I've spent years working with folks who fall somewhere on this spectrum, and the one thing I keep running into is that standard CBT tools assume a baseline desire for connection. That assumption breaks down quickly with schizoid presentation. The person isn't avoiding relationships out of fear. They're avoiding them because they genuinely don't want them. Pushing exposure therapy on someone who doesn't see social interaction as valuable is like telling a vegan to work through their fear of steak. It misses the entire frame.
Schizoid Personality Disorder Self Help: what actually moves the needle
The approach I recommend starts from a different premise than most self-help material does. Instead of trying to make the person want more social contact, you identify what they already find tolerable and build from there. The goal isn't necessarily to become extroverted. It's usually to reduce the functional impairments that come with complete social avoidance—things like workplace collaboration, healthcare navigation, or maintaining at least one relationship that can serve as a lifeline during a crisis. Here's how I structure it for clients: First, you map out the specific situations where isolation causes tangible problems. Not abstract ones. Concrete ones. Missing a medical appointment because you can't schedule it over the phone. Getting fired from a job where the role requires two synchronous meetings per week. These are the pressure points where change becomes motivation rather than just theory.
Second, you introduce micro-level social contact with zero expectation of emotional reciprocity. This looks like sitting in a library. Going to the same coffee shop at the same time each week so the barista learns your order. Joining an online forum about a niche interest where interaction is text-based and task-oriented. The key is low-stakes, predictable, and structured interaction. No small talk required. Third, you address the flat affect issue directly. Many people with schizoid traits aren't unaware of their emotions. They're disconnecting from them. I had a client who could describe the mechanics of grief perfectly but couldn't access the feeling. We worked on somatic grounding techniques—focusing on physical sensations, body position, breathing patterns—as a bridge back to emotional experience. This isn't about faking emotion. It's about reopening a channel that's been shut down for years. The counter-intuitive part that most guides skip: schizoid individuals often benefit more from parallel social presence than direct social interaction. Being in the same room as other people without requiring engagement—the co-working space model, shared commuting, group exercise classes where conversation isn't expected—can slowly desensitize the nervous system to social proximity without triggering withdrawal. I tried this approach with a client who couldn't manage a single conversation longer than three minutes but was able to attend a weekly board game group where dialogue was channeled through the game mechanics. Six months in, he initiated a non-game conversation voluntarily. The structure did the work for him initially.
Get the Full Details

The technical framework behind effective self-directed work
When you dig into the literature, there are a few evidence-backed methods that translate reasonably well to self-guided practice. The most promising is a modified version of schema therapy targeting the social isolation and emotional deprivation schemas. Unlike standard CBT, schema therapy works with deep-seated patterns rather than surface thoughts, which aligns better with how schizoid traits are structured. The self-help adaptation involves identifying triggers for social withdrawal, tracking the automatic thoughts that precede them, and slowly testing alternative behaviors in controlled settings. Another angle that gets overlooked is the sensory processing component. Some research suggests that schizoid personality traits may overlap with certain sensory sensitivity patterns. Overstimulation from social environments can feel genuinely overwhelming, not just anxiety-inducing. If this applies to you, environmental modification becomes a legitimate self-help strategy rather than avoidance. Noise-canceling headphones in social settings, scheduled decompression time after interactions, and choosing low-stimulus environments for necessary social tasks can make a measurable difference in how sustainable social engagement feels. There's also the matter of motivation. Since anhedonia is a core feature, finding intrinsic motivation for self-help is unusually difficult. The workaround I use is external anchoring. Linking social skill practice to something that already provides mild satisfaction—like the completion checklist aspect of a hobby, or the competitive element of an online game with cooperative mechanics. The social behavior becomes a means to an end that already feels worthwhile, not the end itself.
Where this approach fails and what to do instead
I need to be clear about the limitations. Self-help for schizoid personality disorder has a high ceiling problem. The strategies I've described can improve quality of life and reduce functional impairment, but they typically cannot restructure the underlying personality pattern on their own. People who try to work through this entirely independently often plateau within three to six months and then abandon the effort because they perceive no further progress. That's normal. It's not a personal failure. The bottleneck is usually therapeutic alliance. Psychodynamic approaches, particularly those focused on transference and the therapist-client relationship, have shown better outcomes for personality disorders in clinical trials. The relationship with the therapist becomes the vehicle for change rather than the techniques. This is hard to replicate through self-help because the therapeutic relationship is the intervention itself. If you can access therapy, even infrequently, it's significantly more effective than any self-guided program. For those who can't access therapy, the next best option is structured peer support. Online communities focused on neurodiversity or personality differences can provide the parallel social presence mentioned earlier in a more sustainable format. Discord servers, moderated forums, and async group formats allow interaction on your own terms without the pressure of real-time emotional performance. I found that participating in a text-based roleplaying community helped a client practice social reading and turn-taking without the demand for personal disclosure.
A practical weekly framework
If you're working on this independently, here's a structure that tends to produce results without causing burnout. Keep it simple and track it objectively. Monday through Friday: one planned micro-social interaction per day. This could be a brief greeting to a neighbor, a question to a store employee, a comment in an online forum. Duration under five minutes. Record the outcome neutrally—did you do it, and how did it feel on a scale of one to ten. No judgment attached. Saturday: one extended social exposure, thirty to sixty minutes, in a structured environment. A class, a club meeting, a volunteer shift. The structure provides scaffolding so conversation isn't entirely self-generated.

Sunday: complete social rest. No forced interaction. Recovery matters. Schizoid individuals often underestimate how much energy even minimal social contact consumes when your baseline wiring treats it as foreign. Monthly check-in: review your logs. Look for patterns. Are certain types of interaction consistently easier or harder? Do specific environments make a difference? Adjust the framework based on data, not feelings.
The medication question
There's no medication approved for schizoid personality disorder itself. However, comorbid depression and anxiety are common and treatable. SSRIs and other antidepressants can improve overall functioning enough to make self-help strategies more accessible. If you're experiencing significant low mood or anxiety alongside schizoid traits, a psychiatric evaluation is worth the effort regardless of whether you plan to take medication. Even a small improvement in mood regulation can lower the barrier to attempting social exposure. The bigger issue is misdiagnosis. Schizoid personality disorder is frequently confused with avoidant personality disorder, autism spectrum disorder, and sometimes schizophrenia spectrum conditions. Each has different treatment implications. Avoidant PD responds well to social skills training and exposure therapy because the person wants connection but fears rejection. Schizoid PD doesn't have that desire component. Autism involves developmental differences in social communication that extend beyond personality structure. If you've been self-diagnosing, getting a formal assessment from a clinician experienced in personality disorders can save you months of applying the wrong tools.
Resources that don't waste your time
The self-help book market for personality disorders is saturated with generic advice that assumes neurotypical motivation structures. A few titles are worth considering if you filter them properly. The Drama of the Gifted Child by Alice Miller touches on emotional detachment patterns, though it's not specifically about schizoid PD. When Havening Techniques by Rodney Martin offers some practical self-administered interventions that may help with emotional numbness. Most useful, though, are workbooks based on schema therapy like Schema Therapy: A Practitioner's Guide by Jeffrey Young, even though it's written for clinicians. The psychoeducation chapters alone are sharper than most consumer-level books. For academic-level understanding, the International Society for the Study of Personality Disorders publishes research that occasionally addresses treatment approaches for Cluster A personality disorders. The evidence base is thin compared to other conditions, but it's more accurate than anything you'll find on a self-help blog.

What to expect
Progress on Schizoid Personality Disorder Self Help is nonlinear and slow. You might notice small improvements in the first four to six weeks—slightly less dread around necessary social tasks, a bit more emotional recognition, maybe one or two interactions that don't feel completely draining. Beyond that, gains tend to plateau unless you introduce new variables or increase the depth of work. That's where professional support becomes relevant again. The most realistic outcome for sustained self-directed work is improved functioning in specific domains rather than a fundamental personality change. You may never want a large social circle. That's fine. The objective is usually to reach a point where isolation isn't causing preventable harm—to have enough social connectivity to access support when needed and to navigate institutional requirements without complete breakdown. That's an achievable target. Anything beyond that typically requires guided intervention. One thing I haven't seen addressed in most materials: the role of creative or intellectual pursuits as legitimate social proxies. Engaging deeply with a complex hobby, academic subject, or creative project can provide the stimulation and sense of competence that schizoid individuals often lack, while also creating natural pathways to occasional social contact through shared interests. This isn't a replacement for human connection. It's a buffer that makes the necessary connection more tolerable when it arises.
The broader point is that self-help for schizoid personality disorder works best when it's honest about what it can and can't do. There's no hack that will make you enjoy parties or transform you into a social butterfly. There are, however, evidence-informed strategies that can reduce the cost of existing in a world that assumes everyone wants the same kind of social life. The effort required is real, and the returns are modest, but for people who are motivated by practical outcomes rather than social expectations, it's usually worth the investment.