Approaching The Landscape Without Getting Lost
Most people think psychology is one field with different textbooks. It isn't. It is several separate traditions that sometimes agree, sometimes contradict each other outright, and very rarely share the same assumptions about what even counts as evidence. Learning Schools Of Thought In Psychology isn't about memorizing labels. It is about understanding which framework you are using before you start applying it, because mixing two incompatible schools in the same assessment will give you answers that sound confident and mean nothing. I ran into this exact problem once while reviewing a client's intake. They had been assessed using a cognitive-behavioral template but were being treated through a psychodynamic lens by their therapist. The case notes used language from both systems without any distinction. It looked thorough on paper. It was actually a mess. The cognitive section flagged thought distortions, but the psychodynamic section was reading those same thoughts as defense mechanisms. Both frameworks were technically sound. They just cancelled each other out when merged. I spent three hours untangling which observations belonged to which model and rewrote the formulation as two separate streams with a clear note about the incompatibility. That is the practical reality most programs don't tell you about.
What Schools Of Thought In Psychology Actually Looks Like In Practice
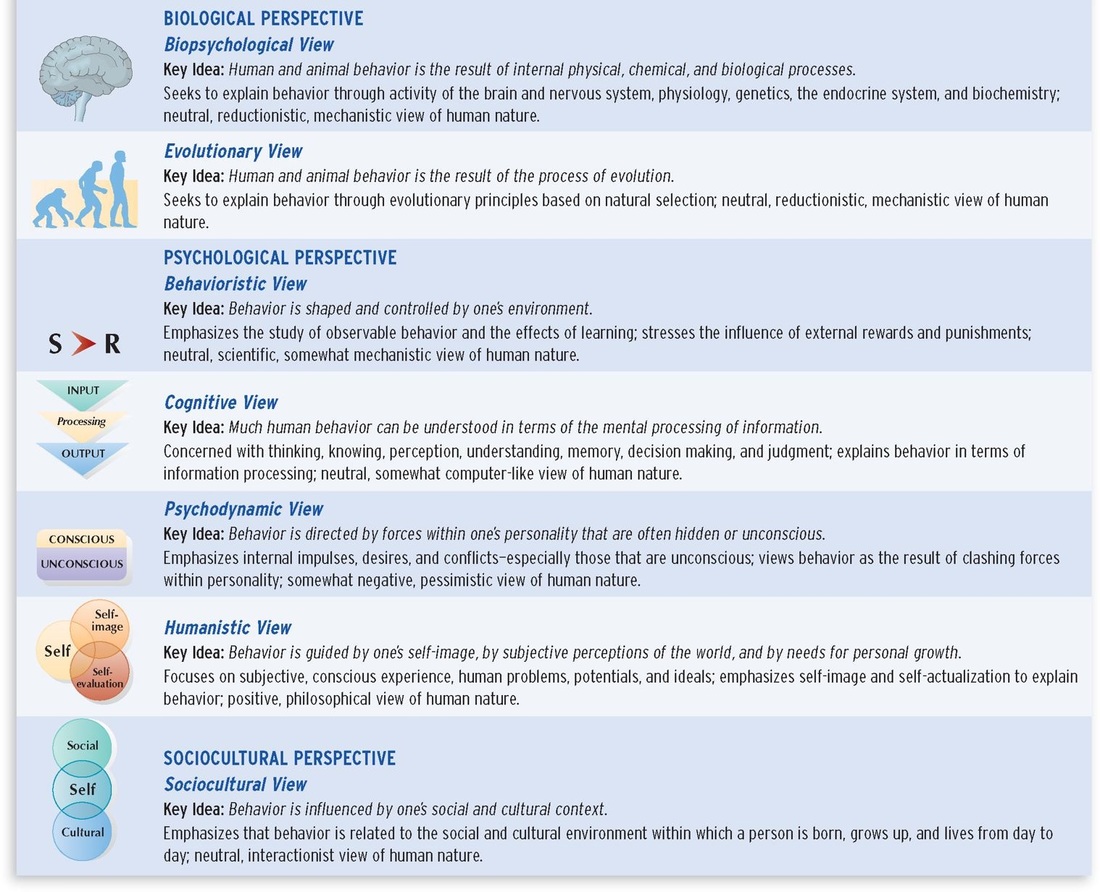
Here is the breakdown that matters, not the textbook summary. Psychoanalytic and Psychodynamic approaches treat the unconscious as primary and view present behavior as largely shaped by early relational patterns. The technique is long-term, insight-oriented, and relies heavily on free association, transference analysis, and dream material. What beginners miss is that this school doesn't actually require belief in Freud's specific metapsychology. Modern psychodynamic therapy has moved far beyond libido theory and structural drives. The active ingredient is the focus on affective patterns and relational repetition. The downside is that outcomes are hard to measure with standard RCT designs. Treatment lasts months to years. It works well for chronic relational difficulties and personality-level issues, and it struggles with acute crisis intervention where quick stabilization is needed. Cognitive Behavioral Therapy and its extensions dominate clinical training programs right now because they produce measurable outcomes quickly. The mechanism is straightforward: identify distorted or unhelpful thinking patterns, test them against behavioral experiments, and restructure the cognition. CBT was built on the assumption that cognitions mediate emotion and behavior. The third wave approaches, including ACT and DBT, modified this by arguing that trying to change thoughts directly is sometimes the wrong move and that acceptance and values-based action work better. A nuanced detail that people overlook is that CBT protocols are highly manualized, which helps with fidelity in research settings but can make them feel rigid in complex clinical presentations where the client doesn't fit the protocol neatly.
Humanistic and existential approaches treat the therapeutic relationship itself as the vehicle of change. Self-determination, unconditional positive regard, and genuine presence are the mechanisms. This school emerged partly as a reaction against the determinism of psychoanalysis and the reductionism of behaviorism. It works best with clients who have strong reflective capacity and motivation for growth-oriented work. It fails when working with acute psychosis, severe personality disorder with acting-out features, or crisis situations where structure and directive intervention are necessary. The research base is thinner than CBT but not empty. Process research on alliance and empathy outcomes is solid across modalities, which undermines the argument that humanistic therapy lacks any empirical support. Behavioral approaches focus on observable behavior and environmental contingencies. Classical conditioning, operant conditioning, and later social learning theory form the foundation. Applied Behavior Analysis uses these principles systematically for skill building and behavior reduction. Behavioral methods are highly effective for specific phobias, habit reversal, autism spectrum interventions, and organizational behavior management. The limitation is that behaviorism by itself does not address private events like thoughts and emotions in a functional way. That gap is partly what drove the cognitive revolution. Pure behavior therapy without cognitive components also tends to have higher relapse rates for depression and anxiety compared to combined approaches. Biological and neuropsychological frameworks treat psychological disorders as medical conditions with genetic, neurochemical, and structural components. Psychopharmacology, neuropsychological assessment, and increasingly, neuroimaging-guided treatment planning fall under this umbrella. This school has produced the most dramatic advances in treatment options over the last thirty years, particularly for severe mental illness. The pitfall is biological reductionism, which explains away the meaning of symptoms and neglects psychosocial factors that matter enormously for recovery. The best practitioners integrate biological data with psychological formulation rather than replacing one with the other.
Get the Full Details

Constructivist and social constructionist approaches argue that reality, including psychological reality, is constructed through language and social interaction. Narrative therapy and solution-focused brief therapy come from this tradition. These approaches are useful when the client's problem is maintained by dominant problem-saturated stories or when cultural and contextual factors are central. They are less suited for conditions where internal neurobiological dysregulation is the primary driver, such as bipolar disorder during a manic episode, where stabilizing medication and routine takes priority over narrative work.
How To Navigate Between These Frameworks Without Losing Your Mind
The real skill isn't mastering every school. It is knowing which one to reach for when and when to step back. Here is a practical decision tree I use and teach. Start with assessment. Determine whether the primary problem is symptom-level and time-sensitive or pattern-level and chronic. Acute phobias, OCD rituals, and ADHD management respond fastest to behavioral and cognitive-behavioral methods. Chronic interpersonal difficulties, identity issues, and recurrent relationship patterns respond better to psychodynamic or attachment-informed work. When in doubt, do a thorough differential diagnosis first. A lot of the confusion between schools comes from misdiagnosis, not theoretical disagreement. Consider the client's cognitive style and preferences. Some people need structure, psychoeducation, and concrete tools. Others need space to explore meaning and emotional experience. Neither preference is correct or incorrect. It is data. Matching the approach to the client's learning style and comfort zone improves engagement and retention, which is often the difference between outcome and no outcome regardless of theoretical orientation.
Watch for theoretical purity traps. I see trainees and even licensed clinicians get attached to one school the way people get attached to political identities. They start interpreting everything through that lens. A CBT-only clinician will see cognitive distortions in situations that are actually rational responses to real problems. A psychodynamic-only clinician will find unconscious conflict in behavior that is better explained by habit formation or environmental reinforcement. Both errors are common. Both produce poor outcomes. The workaround is to keep your formulation multi-axis. Use DSM or ICD criteria for diagnosis, dimensionally rate severity, map maintaining factors across cognitive, behavioral, emotional, and social domains, and then select interventions based on which factors are most amenable to change in that specific person. Integrative approaches exist for a reason. EMDR combines cognitive, behavioral, and psychophysiological elements. Integrative CBT blends techniques from multiple CBT-derived models. Most competent clinicians are integrative to some degree. The danger is sloppy integration, which is combining techniques without a coherent underlying rationale. Meaningful integration requires understanding why each technique works within its original framework and how the mechanisms interact when combined. One counter-intuitive point: the most effective therapists are not the ones who know the most schools. They are the ones who understand their own theoretical bias well enough to catch themselves applying it inappropriately. Self-awareness of theoretical allegiance is a stronger predictor of flexible, appropriate technique selection than theoretical knowledge alone.

The Measurement Problem Nobody Wants To Talk About
Different schools measure success differently. CBT uses standardized symptom scales like the BDI and GAD-7. Psychodynamic therapy might use the Core Conflictual Relationship Theme measure or the Penn Change Model. Humanistic therapy often uses session ratings and client-reported process measures. This isn't just academic preference. It affects how you evaluate whether treatment is working. If you only use symptom checklists with a psychodynamic client, you will miss therapeutic progress that happens in the relationship and shows up slowly over time. If you rely solely on qualitative process data with a CBT client, you might overlook that the client's depression score hasn't moved despite good session ratings. Use both. Track symptoms and process. Reconcile discrepancies when they appear. Another blind spot is the publication bias that favors CBT in empirical journals. This creates a distorted perception of the evidence base. Existential and humanistic therapies have meaningful outcome research, but it is published in different venues and in European journals more than American ones. Read broadly. Don't let journal hierarchy determine your theoretical education. The field is also moving toward transdiagnostic approaches that cut across traditional schools. The unified protocol for emotional disorders, for example, targets transdiagnostic processes like emotional avoidance and experiential avoidance rather than specific diagnostic categories. This suggests the future may be less about choosing a school and more about selecting mechanisms of change based on the individual's maintaining factors, regardless of which theoretical tradition those mechanisms came from.
If you want to actually learn this rather than just perform knowledge about it, start by picking one school and studying it deeply enough to understand its assumptions, its techniques, its evidence, and its limits. Then pick a second school and do the same. Compare them side by side on at least three case formulations. Notice where they agree and where they diverge. That divergence is where the learning happens. The rest is memorization.