Understanding The Connection Between The Piriformis And The Sciatic Nerve
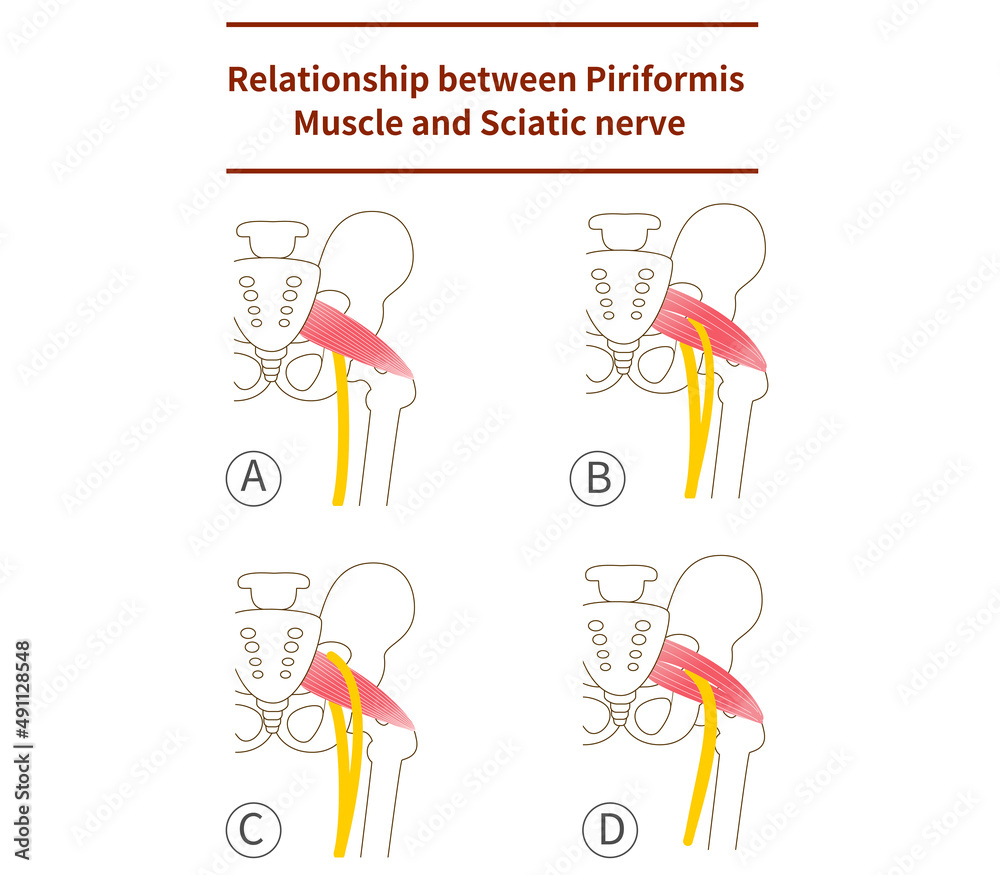
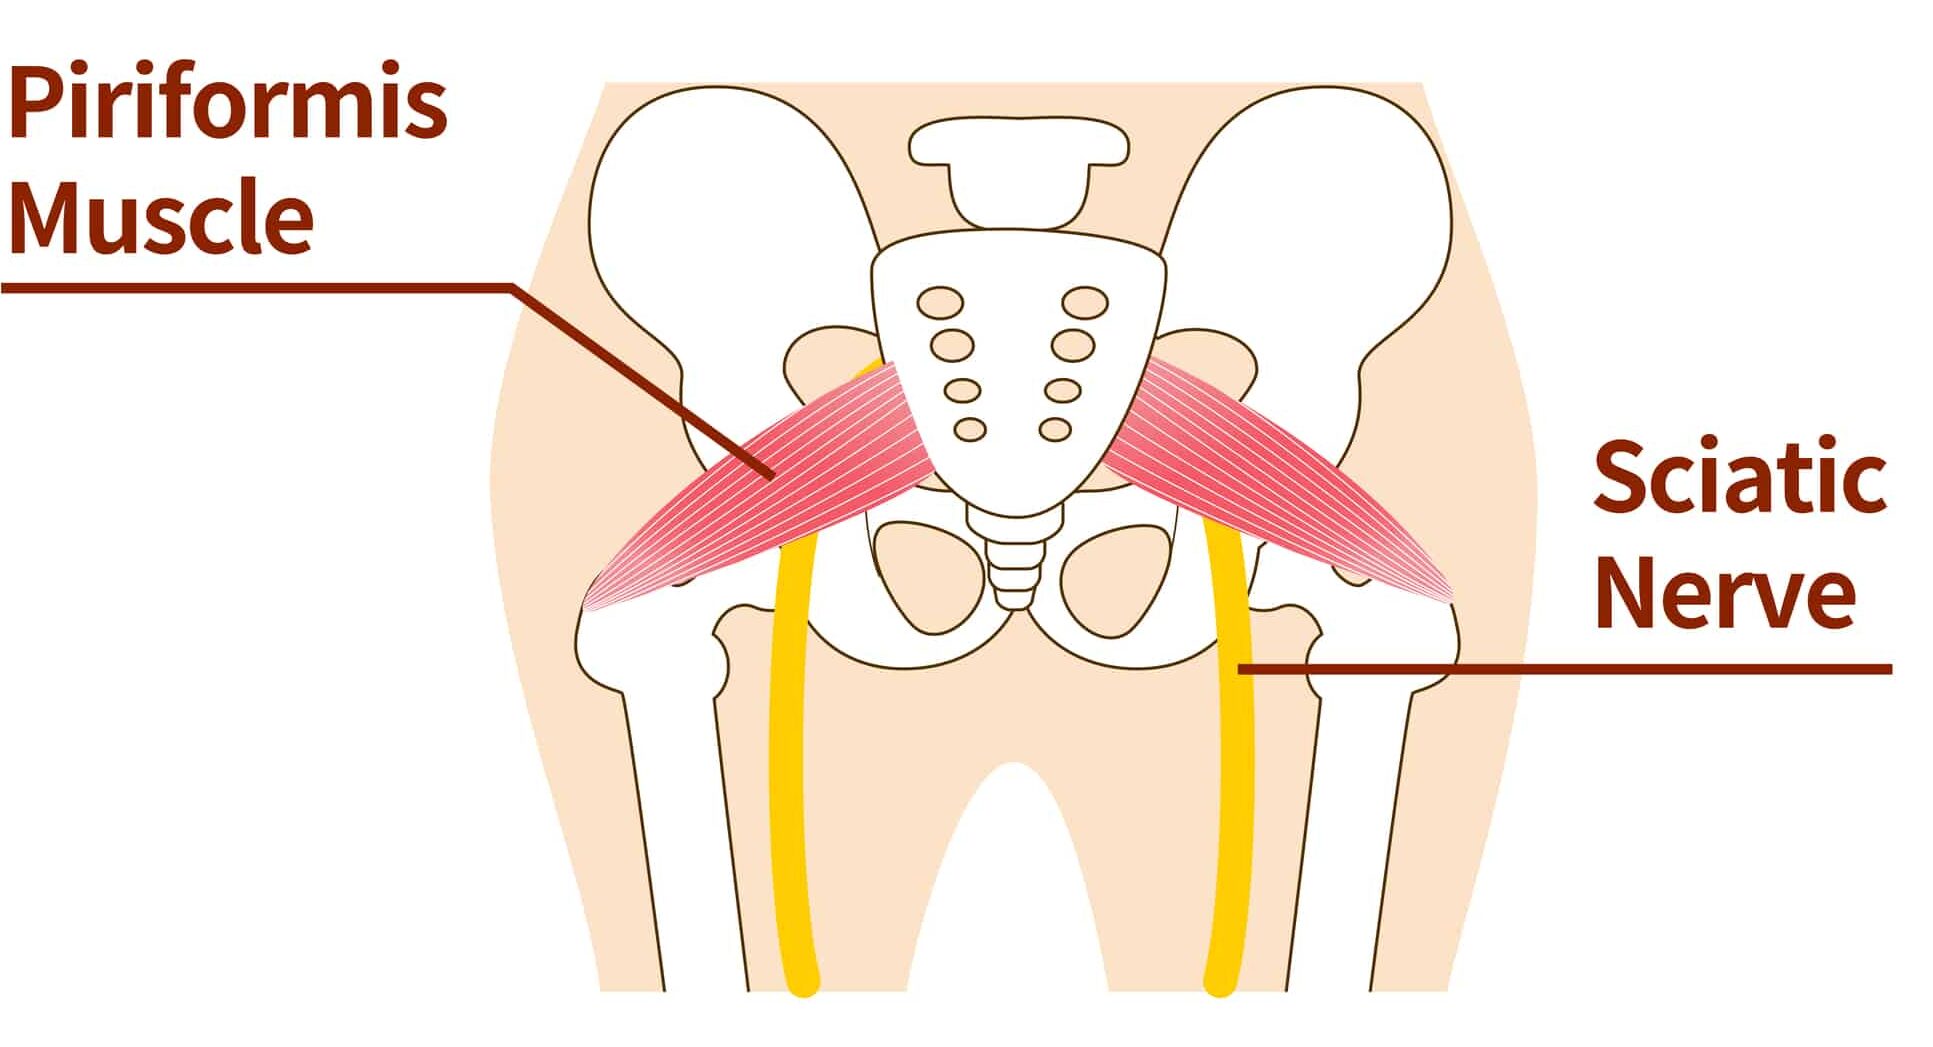
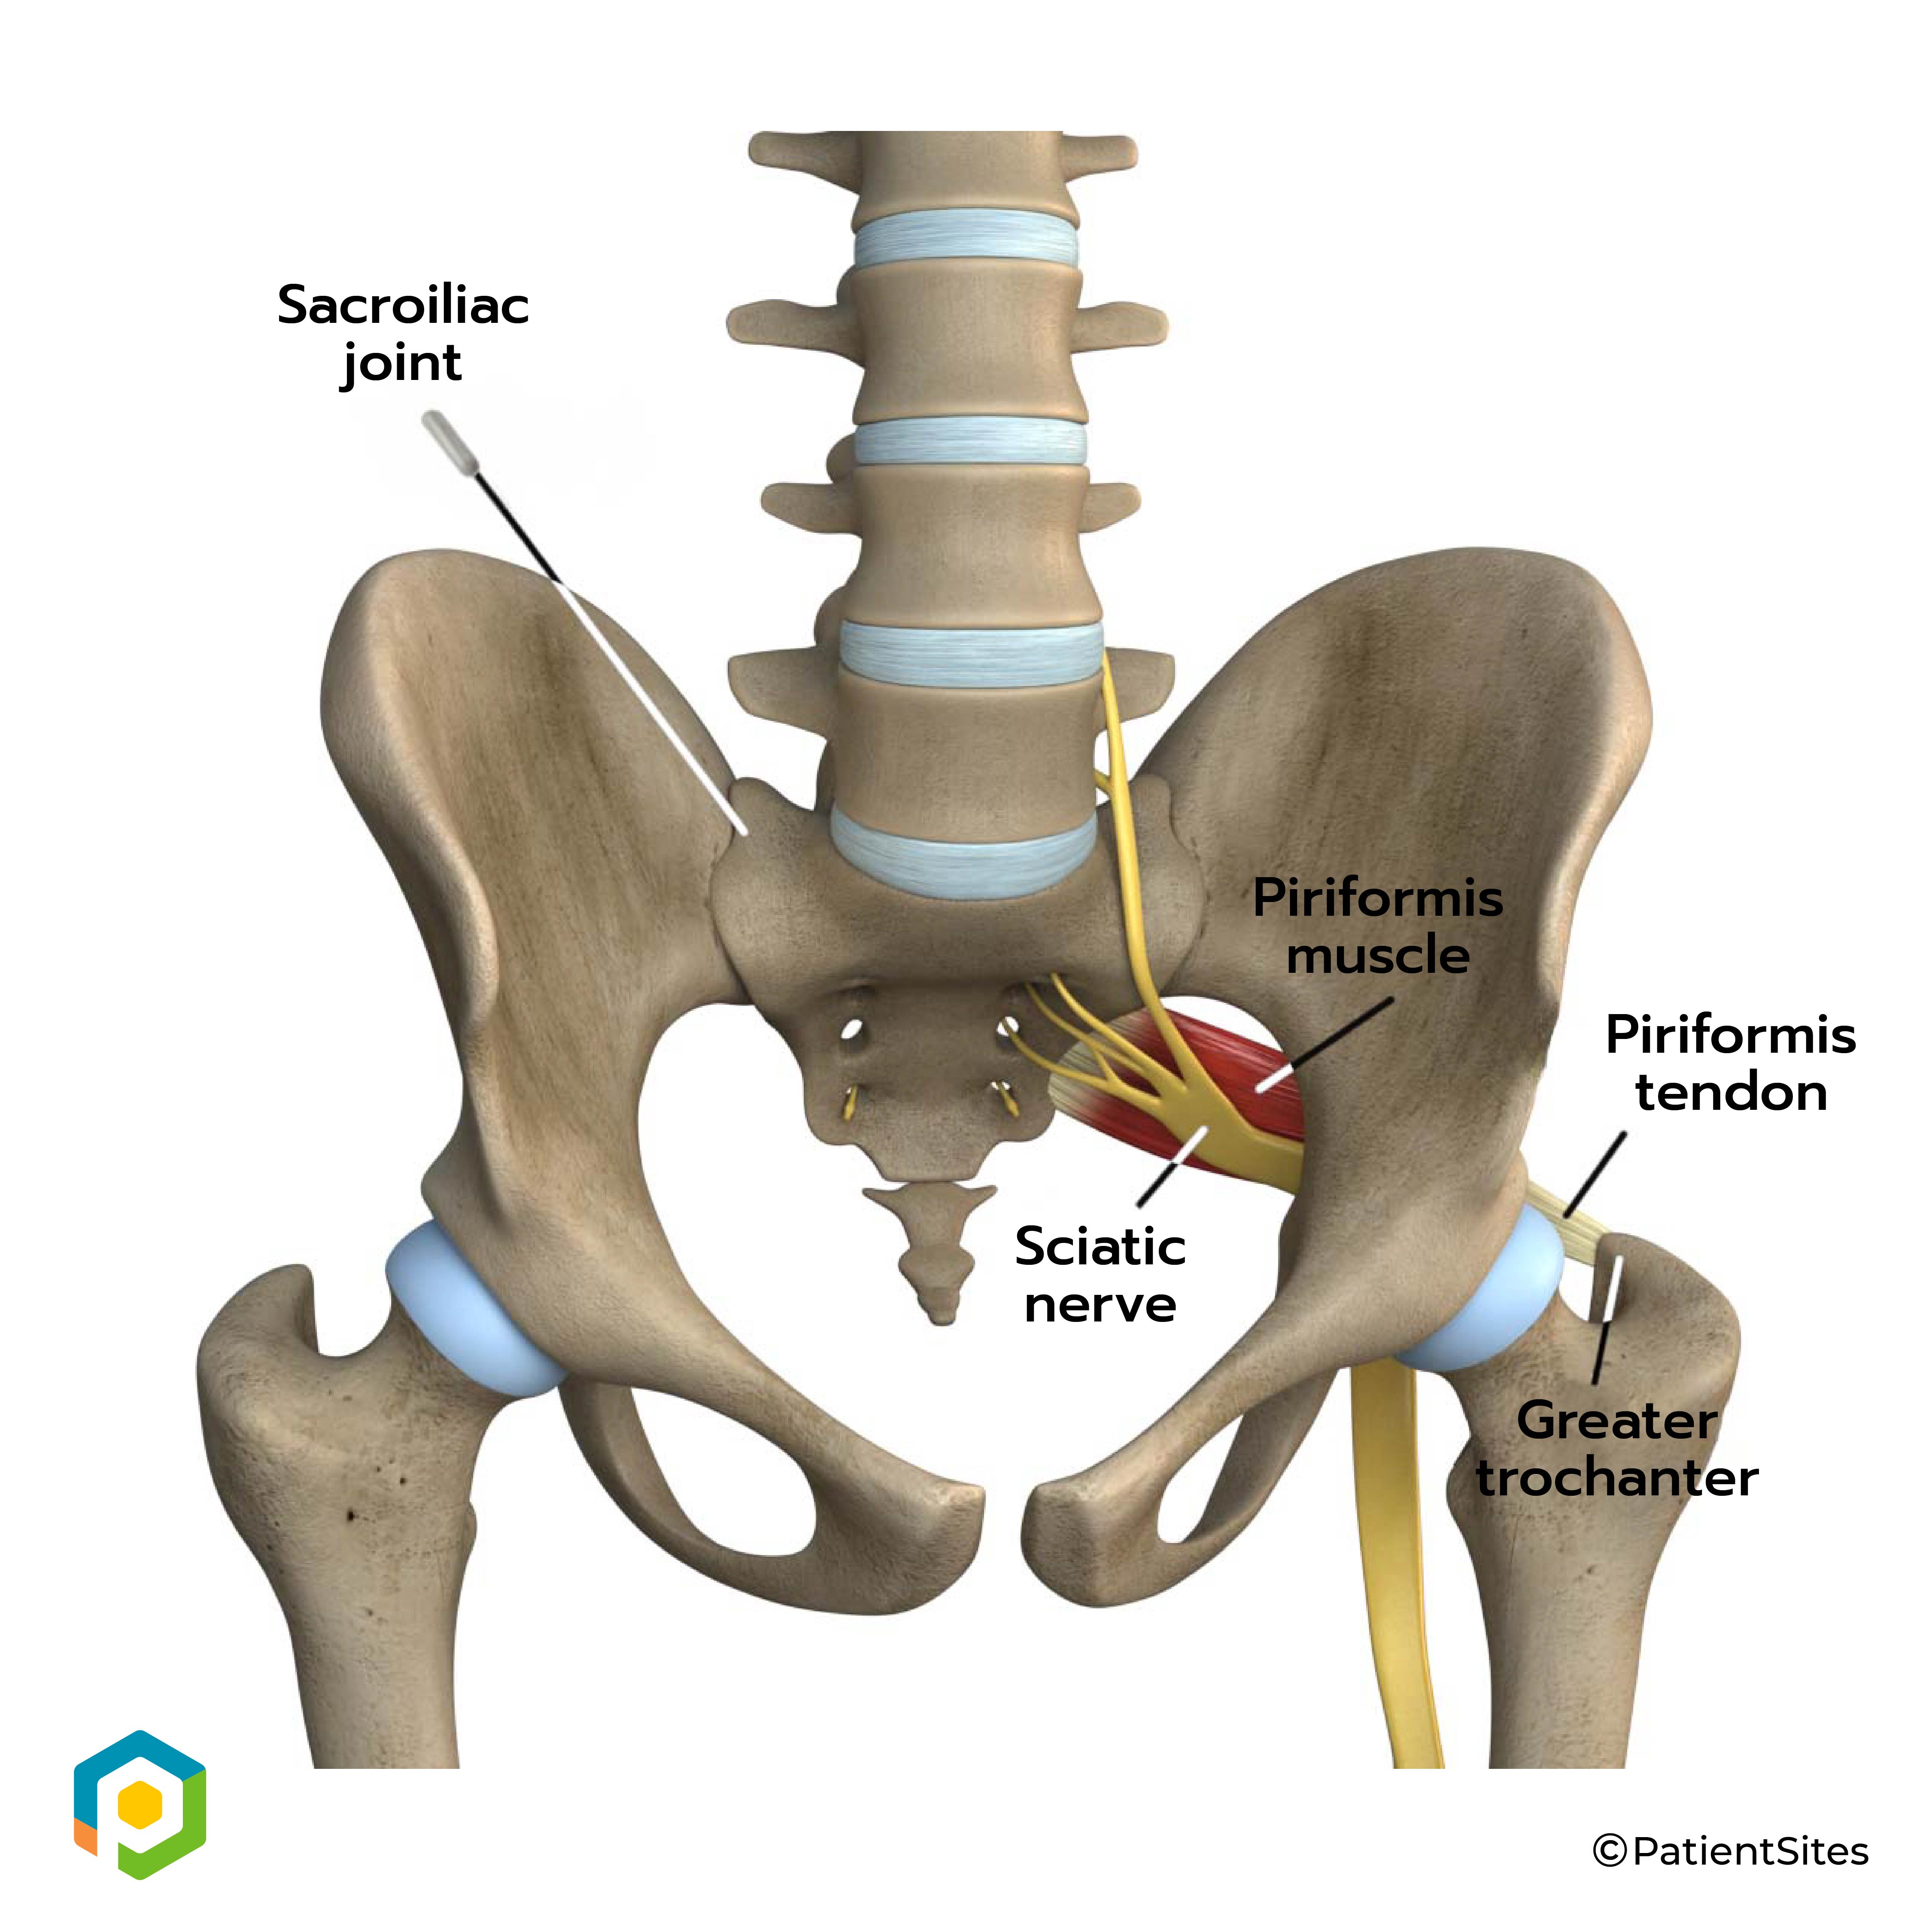
The piriformis is a small, pear-shaped muscle located deep in the buttock, originating from the anterior surface of the sacrum and inserting onto the greater trochanter of the femur. It acts primarily as a lateral rotator of the hip when the leg is extended. The sciatic nerve, the largest peripheral nerve in the human body, passes in close proximity to this muscle. Their relationship is anatomically variable and clinically significant. Most textbooks teach that the sciatic nerve passes underneath the piriformis. That is the standard pattern, accounting for roughly 85% of the population. But the remaining 15% tell a different story. The nerve can split around the muscle, pass through its belly, or sit entirely above it. I learned this the hard way during my first year of physical therapy clinical work. A patient came in with classic piriformis syndrome symptoms — deep gluteal pain, positive FAIR test, no lumbar source on imaging. I spent three weeks working her down the standard protocol. Nothing moved. Eventually, someone suggested a high-resolution ultrasound evaluation, which revealed the sciatic nerve was piercing directly through the piriformis belly. Standard stretching actually aggravated it because every time she reached end-range external rotation, the nerve was being compressed by the contracted muscle fibers traversing it. The workaround was straightforward once we knew the anatomy: she stopped stretching the piriformis entirely and switched to neural gliding techniques with a modified hip position, combined with targeted eccentric loading of the gluteus medius. Pain dropped by about 60% in two weeks. It was a good reminder that variant anatomy isn't rare — it just gets overlooked because the standard model is so pervasive.
Practical Considerations For Sciatic Nerve And Piriformis Anatomy
When assessing someone with posterior hip or buttock pain, you need to differentiate between actual piriformis involvement and lumbar radiculopathy, which can present with nearly identical symptom patterns. A straight leg raise test that reproduces distal symptoms below the knee points more toward a neural origin from the spine. Piriformis-related irritation typically causes referral patterns confined to the buttock, posterior thigh, and occasionally the lateral leg, but rarely extends past the knee. Palpation of the piriformis is tricky. The muscle sits deep beneath the gluteus maximus. To access it, the patient should be side-lying with the hip and knee flexed, or prone with the hip externally rotated. You locate the greater trochanter, then move approximately two to three centimeters medially and slightly superior into the gluteal fold region. The tissue here feels dense and fibrous when hypertonic. Pressing into it should reproduce the patient's familiar pain pattern, ideally referring distally along the sciatic distribution. This is called a positive Beatty sign when performed supine with the patient actively abducting the hip against resistance while you palpate the muscle. The blood supply comes primarily from the superior and inferior gluteal arteries, and innervation arises from the nerve to piriformis, which originates from the posterior divisions of the L5 and S1 nerve roots. These same nerve roots contribute to the sciatic nerve itself. That means a pathology at the nerve root level, such as a disc herniation at L5-S1, can cause both direct radiculopathy and secondary piriformis hypertonicity through altered motor innervation. Treating the piriformis in isolation when the actual driver is a compressive radiculopathy is a common mistake I see repeatedly. The muscle tightens up as a protective splinting response, not as the primary problem. You will see temporary relief after release work, but the symptoms return because the root irritation persists.
Imaging has real limitations here. MRI can visualize the piriformis muscle and identify anatomical variants of nerve course, but it cannot reliably show piriformis syndrome in a living, moving patient. Static imaging misses the dynamic compression that occurs during specific hip positions. Ultrasound is more practical for real-time assessment of muscle thickness and contractility, and it can confirm nerve variants. I have seen multiple cases where the initial MRI report read as normal, yet ultrasound demonstrated clear piriformis hypertrophy exceeding 1.8 centimeters in cross-sectional diameter compared to the contralateral side, with direct contact and displacement of the sciatic nerve. Treatment approaches vary depending on what you are actually dealing with. Manual therapy including myofascial release, instrument-assisted soft tissue mobilization, and ischemic compression can reduce resting tone in the piriformis. Stretching protocols, particularly those that combine hip flexion, adduction, and internal rotation, target the muscle effectively in most people. But if the nerve passes through the muscle, aggressive stretching becomes counterproductive. Neural mobilization techniques like the slump test progression or seated sciatic nerve glides are gentler and address nerve mobility without forcing the muscle into stretch. I typically start with gliding and progress to strengthening only after pain-free range of motion is restored. Injection therapy is another option worth understanding. Trigger point injections into the piriformis using local anesthetic alone have been shown in studies to provide both diagnostic confirmation and therapeutic relief. If injecting the muscle directly eliminates the referral pattern, you have confirmed the source. Corticosteroid injections can extend that relief window for patients who need a longer period to engage in rehabilitation. The procedure is usually done under ultrasound guidance to avoid accidental intraneural injection, which carries real risk of nerve injury. landmark-based blind injections are less reliable and carry higher complication rates.
Get the Full Details

Botox injections into the piriformis represent a more durable intervention for chronic cases that do not respond to conservative measures. The effect lasts approximately three to four months, providing a therapeutic window for targeted rehabilitation. Multiple case series have reported success rates around 70-80% for appropriate candidates. The downside is cost and the need for specialized injection training. Not every clinic offers this, and insurance coverage is inconsistent. Surgical decompression of the piriformis is reserved for refractory cases where all conservative and interventional options have failed. The procedure involves identifying the sciatic nerve, releasing the piriformis tendon or muscle fibers compressing it, and in some cases resecting the entire muscle. Long-term outcomes in published series show improvement in roughly 75-85% of patients, but surgical complications include sciatic nerve injury, recurrent scar tissue formation, and hip instability. I have referred patients to surgeons for this, but only after documenting that six months of structured conservative management produced no meaningful improvement. Surgery should be genuinely last resort. Prevention and self-management rely on addressing the underlying mechanical drivers. Prolonged sitting compresses the piriformis against the sacrum and reduces blood flow to the muscle, promoting adaptive shortening. Standing desks help somewhat, but the real issue is lack of hip mobility and weak external rotators that force the piriformis to compensate. Incorporating hip mobility work two to three times per week and gluteal strengthening sessions prevents recurrence in most people. The standard clamshell exercise, side-lying hip abduction, and banded lateral walks all load the gluteus medius and minimus, which reduces compensatory piriformis recruitment during single-leg activities like walking and climbing stairs.
A few people will find that their piriformis problems persist despite excellent compliance with stretching, strengthening, and posture modification. In those cases, the next question is whether the issue is truly piriformis-related or if there is an undiagnosed concurrent pathology. Sacroiliac joint dysfunction, lumbar facet arthropathy, hip labral tears, and greater trochanteric pain syndrome all overlap clinically with piriformis irritation. A thorough differential diagnosis is essential before committing to any single treatment pathway. Imaging and diagnostic injections are useful tools for narrowing the field, but clinical judgment matters more than any single test result.