Understanding the Sciatic Nerve in Canine Anatomy
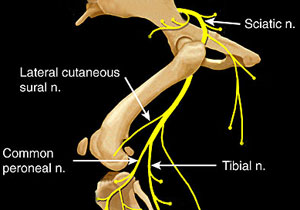
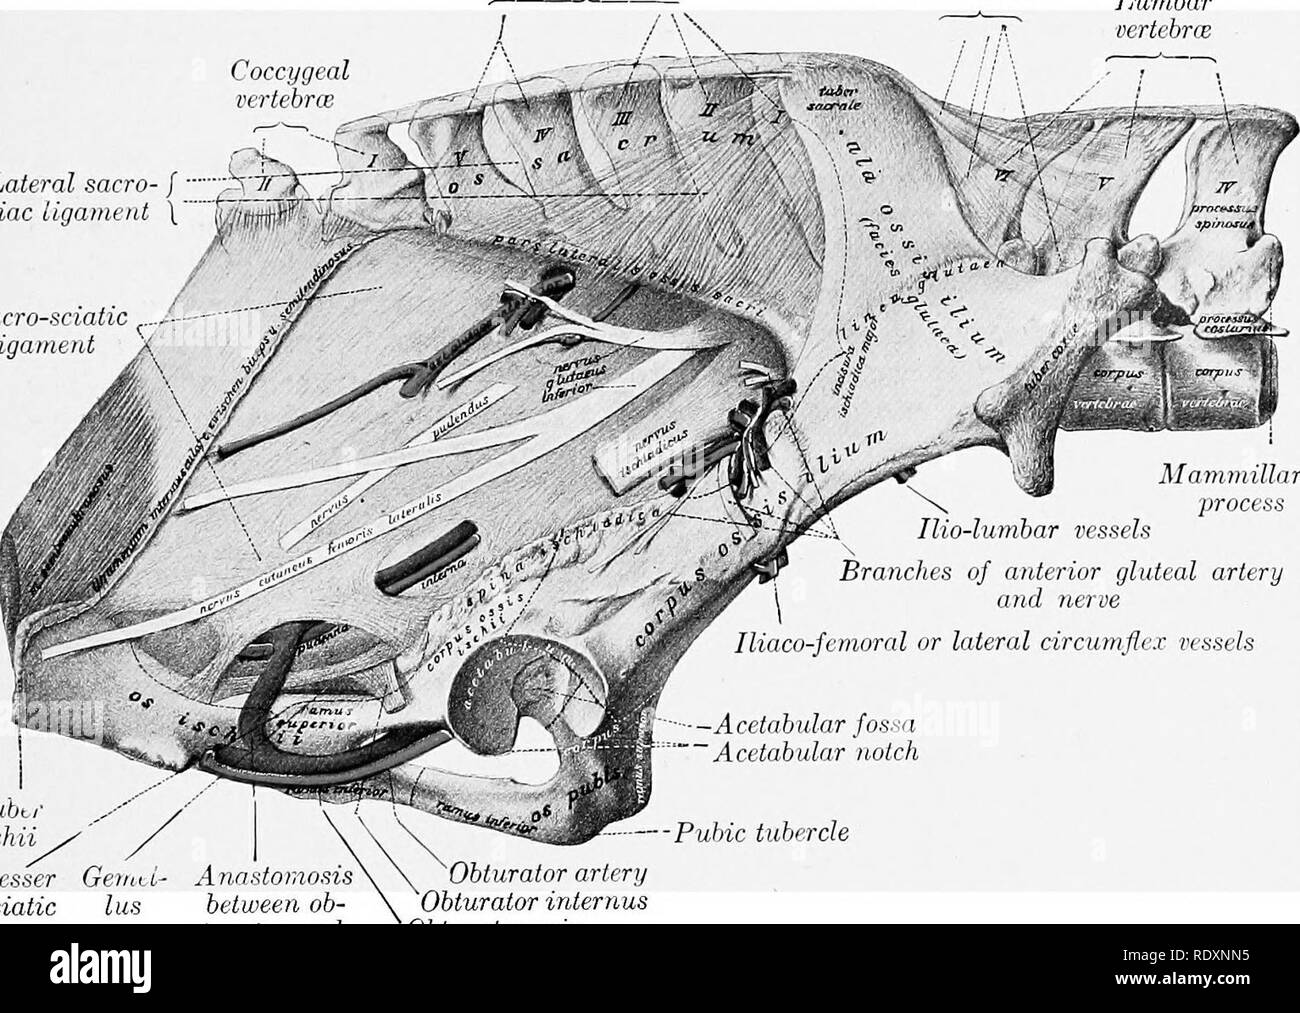
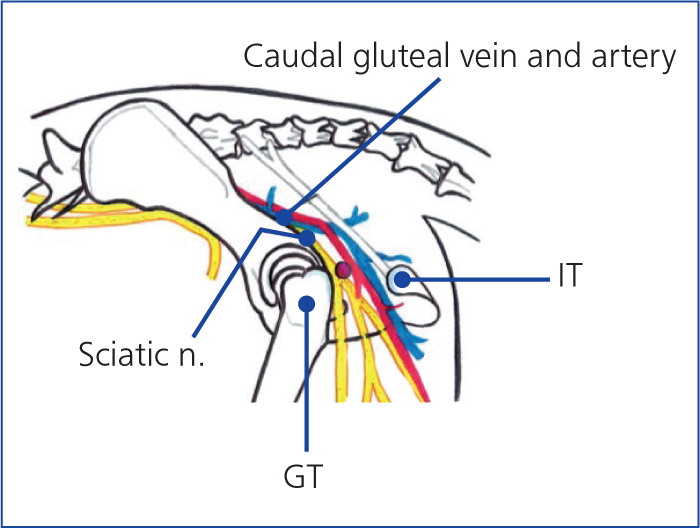
The sciatic nerve is the largest peripheral nerve in the dog's body, running from the lumbar and sacral spinal cord segments down through the hindlimb. If you are studying veterinary anatomy or working in clinical practice, this nerve deserves your attention because damage here produces noticeable gait changes. I spent about three years doing cadaver dissections during vet school, and I can tell you that finding the sciatic nerve consistently on the first attempt is harder than textbooks make it look. The nerve emerges from the ventral branches of L6, L7, and the first two or three sacral segments, then passes deep to the gemelli and obturator internus before exiting the pelvic canal through the greater sciatic foramen. From there it runs caudally along the medial aspect of the femur, usually sitting between the biceps femoris and the semitendinosus muscles. The branching pattern varies considerably between individuals, which I learned the hard way when I missed a significant branch during a practical exam. The nerve typically splits into the tibial and common fibular divisions somewhere around the knee region, though the exact location depends on the dog's size and conformation.
Clinical Significance and Common Pathologies
Sciatic nerve injuries in dogs most often result from hip dysplasia surgery, intramuscular injections placed too far caudally in the hindlimb, or blunt trauma to the hip region. A friend of mine who runs a small animal orthopedic practice told me he sees at least one iatrogenic sciatic injury per month, almost always from improper injection technique in the caudal thigh. The classic presentation includes inability to extend the stifle, reduced patellar reflex, and dragging of the affected limb. Sensory deficits may be less obvious because dogs compensate well for proprioceptive loss in one leg. Walking on hard surfaces reveals a shorter stride on the affected side, and you will often see the dog standing with the hindlimb abducted to relieve tension on the nerve.
Diagnostic Methods and Imaging Considerations
Ultrasound has become my go-to diagnostic tool for sciatic nerve assessment, though it requires a steady hand and experience with nerve imaging. The nerve appears as a hyperechoic structure with a honeycomb pattern on cross-section, becoming hypoechoic when inflamed or compressed. I typically scan from the greater sciatic foramen down to the point of division, noting any swelling, discontinuity, or abnormal echogenicity. Electromyography and nerve conduction studies provide objective data but are technically demanding. The labile nature of canine nerves means you need proper anesthetic protocols and temperature monitoring to get reliable results. I have found that maintaining rectal temperature above 38 degrees Celsius is essential, as cooler temperatures significantly slow conduction velocity and produce misleading measurements.
Get the Full Details

Surgical Approaches and Repair Techniques
When surgical intervention is necessary, the dorsal approach to the hip joint gives you access to the proximal sciatic nerve without disrupting major muscle groups. I prefer this over the lateral approach because it preserves the blood supply to the surrounding tissues and allows better visualization of the nerve's course through the pelvis. Nerve grafting with autologous saphenous nerve works well for segmental defects up to about five centimeters. For longer gaps, I use expanded polytetrafluoroethylene conduit devices, though outcomes are less predictable. Recovery timelines vary widely depending on the severity of injury and the dog's age, with younger animals showing significantly better regeneration rates than seniors.
Postoperative Management and Prognosis
Restricting exercise for six to eight weeks is standard protocol after sciatic nerve surgery, though I find that controlled leash walks beginning around day ten help prevent muscle atrophy without compromising healing. Physical therapy with passive range of motion exercises improves outcomes considerably, especially for maintaining joint flexibility during the immobilization period. Complete recovery depends on the type of injury. Neuropraxia from compression or stretching often resolves within weeks to months, while axonotmesis requires months of regeneration at roughly one millimeter per day. Neurotmesis from clean transection has the best surgical prognosis if repaired promptly, but crush injuries from trauma respond poorly to intervention regardless of timing.
Common Misconceptions About Canine Sciatic Nerves
One persistent misunderstanding I encounter is that the sciatic nerve innervates only the cranial thigh muscles. In reality it supplies the entire caudal thigh compartment including the hamstrings, plus most of the lower leg and foot through its tibial and common fibular branches. Dogs with complete sciatic denervation cannot extend their hocks or flex their stifle, producing a distinctive dropped-hock posture. Another misconception involves injection sites. Many pet owners believe the caudal thigh is a safe injection zone, but the sciatic nerve runs directly through this region in most dogs. I recommend the dorsal lumbar area or the lateral thigh for intramuscular injections whenever possible, as these sites place the needle well away from the nerve's course. The variability in branching patterns makes standardized descriptions somewhat misleading. Some dogs have early division of the nerve components, while others show late branching with unusual muscular innervation patterns. During my dissection work, I encountered a 7-year-old Labrador where the common fibular division wrapped around the lateral head of the gastrocnemius before joining the tibial component, a configuration that would have complicated surgical approaches from a standard textbook description.
Resources for Further Study
Mueller's Veterinary Anatomy remains the most comprehensive reference for canine nervous system anatomy, though the illustrations can be dated. I supplement this with Journal of Comparative Neurology articles for current research on peripheral nerve regeneration. Online video libraries from veterinary schools sometimes demonstrate the surgical approaches I described, which helps contextualize the dissection techniques. If you are preparing for board examinations, practice identifying the nerve on radiographs and CT scans, as modern veterinary medicine increasingly relies on cross-sectional imaging for preoperative planning. The sciatic nerve appears as a well-defined structure on contrast-enhanced myelograms, though artifacts from adjacent vascular structures can mimic pathology in inexperienced hands.
When to Refer and When to Manage Conservatively
Mild compression injuries often resolve with strict rest and anti-inflammatory medication, but I refer cases involving open wounds, suspected tumor involvement, or progressive neurological deficits to surgeons with peripheral nerve expertise. The decision tree gets complicated when owners cannot commit to the required confinement period, as even well-executed surgery fails without proper postoperative management. Financial considerations also factor into treatment decisions. Nerve conduction studies run $400 to $800 depending on the number of sites examined, while surgical repair with nerve grafting can exceed $3,000. Insurance coverage varies significantly, and I always discuss expected outcomes honestly before proceeding, because unrealistic expectations from owners lead to dissatisfaction even with technically successful procedures. Age affects regeneration capacity substantially. I have seen 3-year-old retrievers walk normally within four months of surgical repair, while geriatric dogs over 10 years often show incomplete recovery despite identical surgical techniques. The cellular mechanisms behind this difference involve both neuronal intrinsic properties and the quality of surrounding soft tissue envelopes, factors that become increasingly unfavorable with advancing age.