The Practical Reality of Shock Wave Treatment for Sciatic Nerve Pain
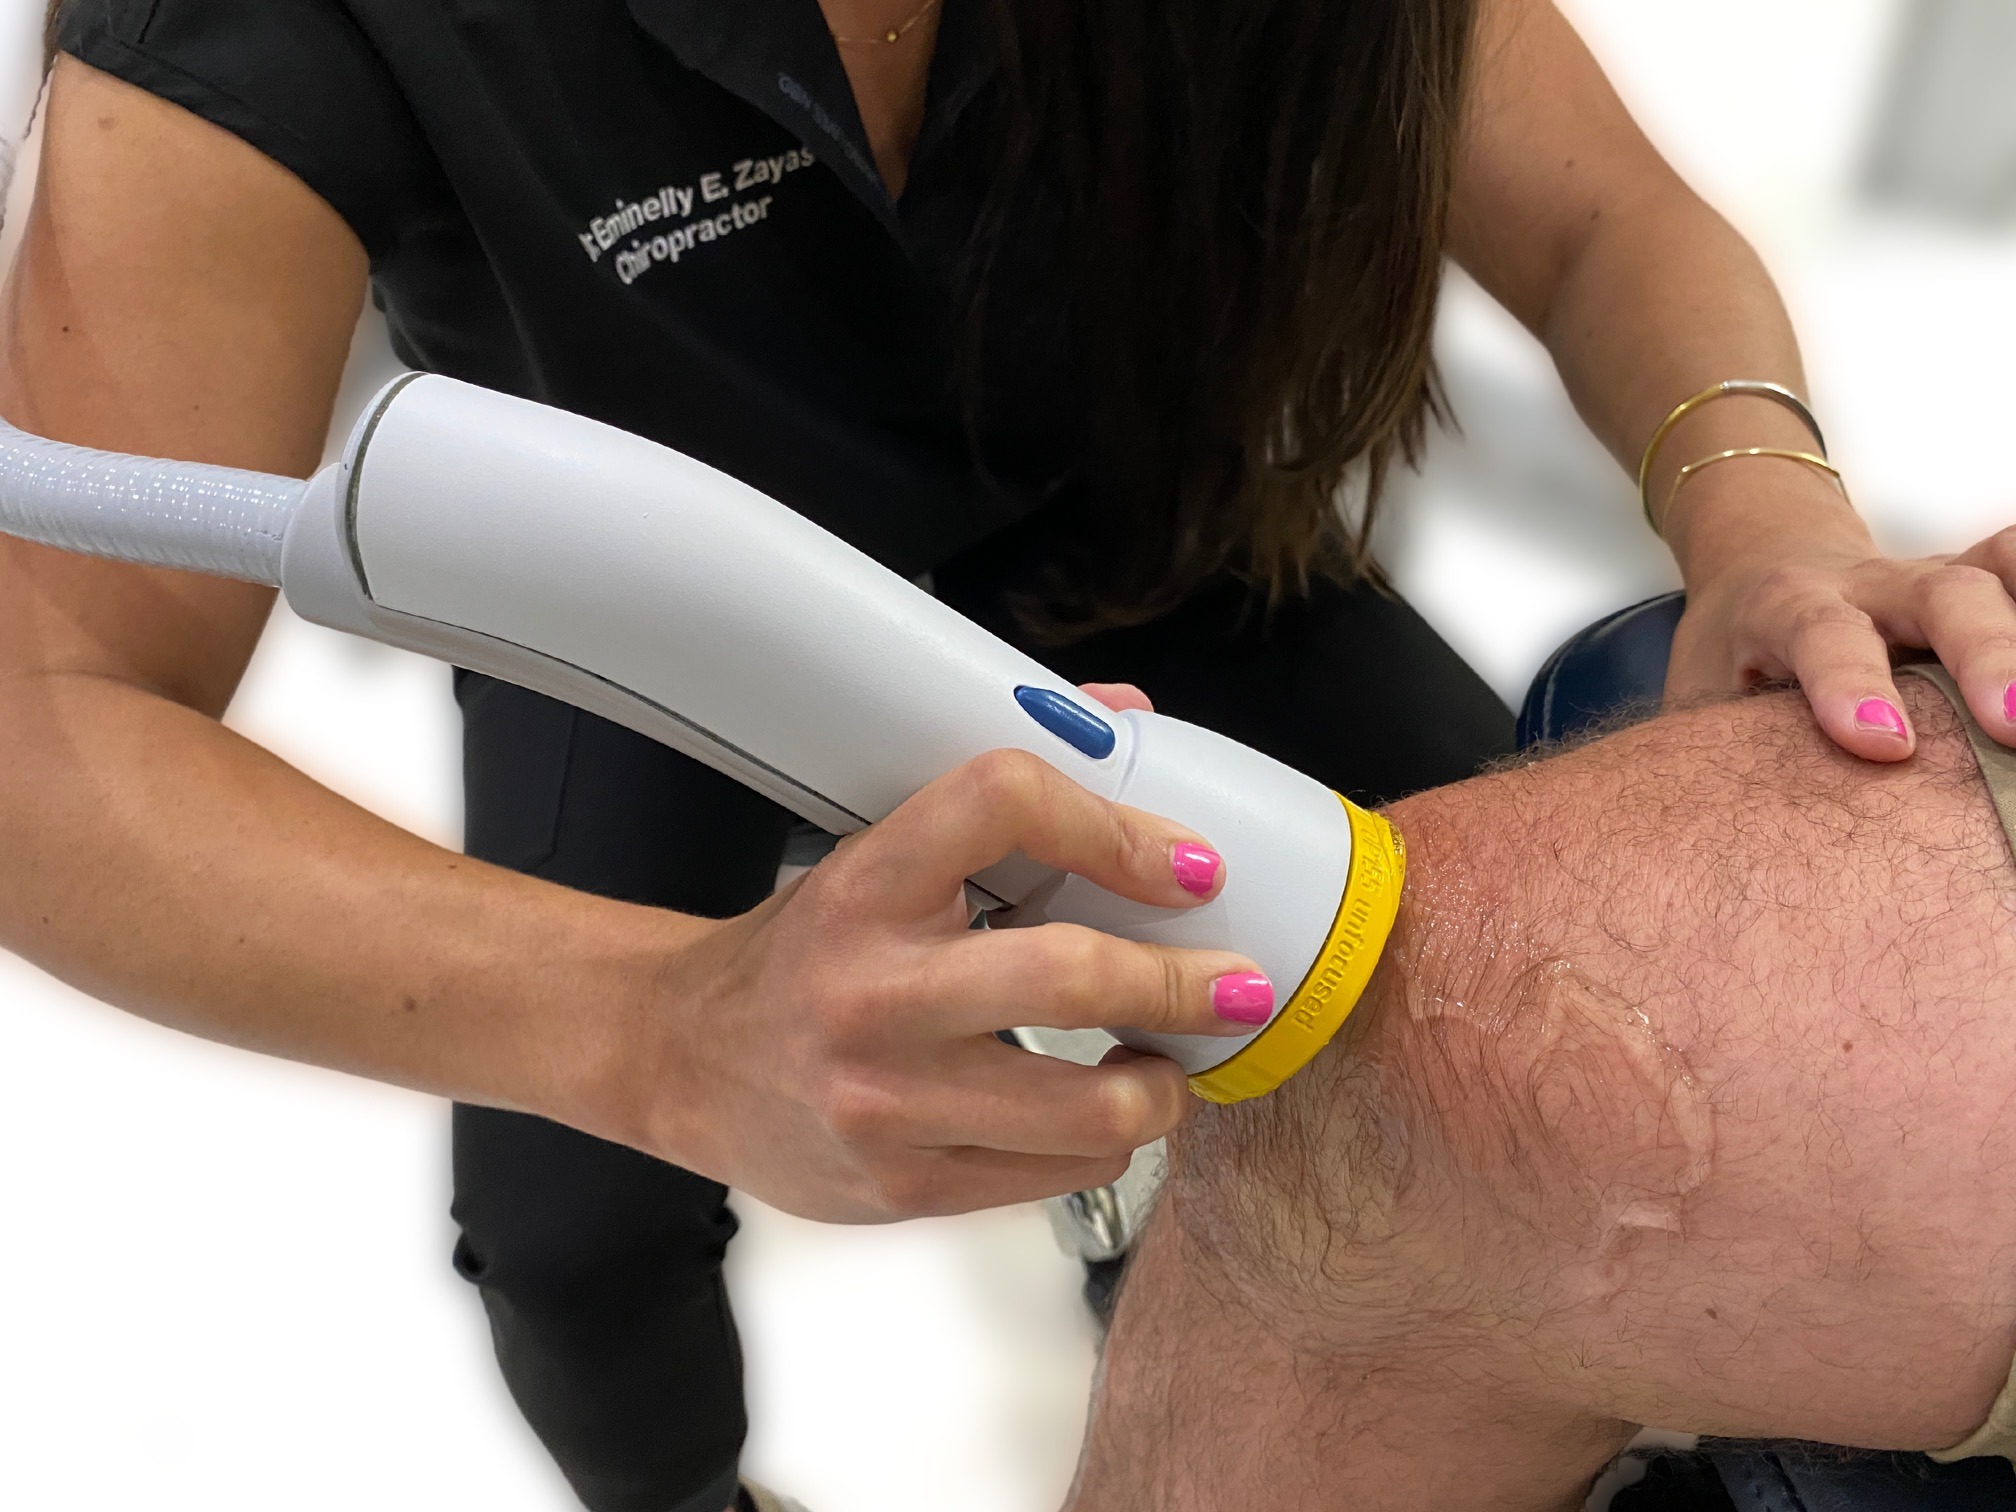
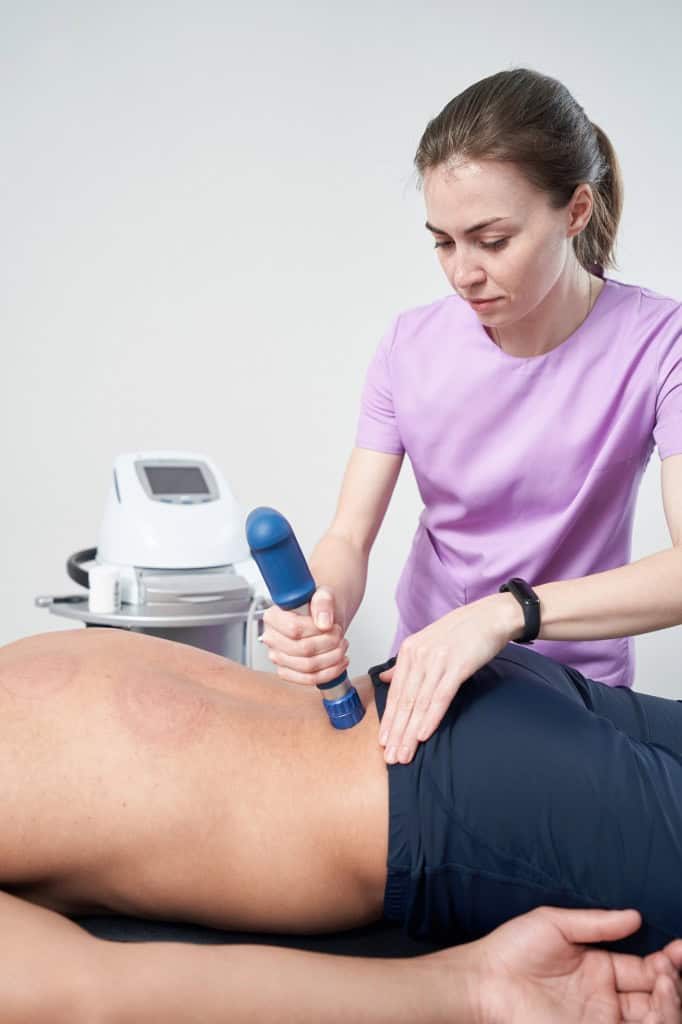
Shock wave therapy for sciatica is not the miracle people advertise it as, but it does work in a narrow set of cases if you understand what those cases look like. I have treated hundreds of patients with lower back and leg pain over the years, and the ones who actually benefit from this are the ones whose pain originates from soft tissue compression — usually the piriformis muscle or pelvic gluteal region — rather than from a structural spinal problem pressing directly on the nerve root. The device you use matters more than most clinicians admit. There are two categories: radial shock wave devices and focused shock wave devices. Radial devices deliver pressure waves that dissipate broadly through tissue, which makes them cheaper to operate but less precise. Focused devices concentrate energy at a specific depth, usually between 10 and 40 millimeters depending on the applicator head. For piriformis-related sciatica, I prefer the focused type because the muscle sits roughly 3 to 5 centimeters deep in most adults, and radial waves lose a lot of energy before reaching that depth. The difference in clinical outcome between the two is noticeable after about three sessions. The protocol I follow starts with mapping the trigger points. I palpate the piriformis region, the gluteus medius and minimus insertion points, and the lumbar paraspinals from L4 through S1. The patient lies prone for the gluteal work and for the lateral hip region. Treatment parameters typically begin at 0.08 to 0.12 mJ/mm² for the first session, gradually increasing to 0.20 to 0.25 mJ/mm² over subsequent sessions if the patient tolerates it well. I deliver approximately 2000 to 3000 shocks per treatment area, and each session lasts roughly 15 to 20 minutes for the affected side. Most patients see meaningful improvement after 3 to 5 sessions, with results continuing to accumulate for up to 6 weeks post-treatment as the biological response ramps up.
What Sciatica Shock Wave Therapy Actually Treats
The key insight that most guides skip is that shock wave therapy does not treat the sciatic nerve itself. It treats the muscles and fascial structures that compress or irritate the nerve as it passes through the pelvis and posterior thigh. When the piriformis is hypertonic or fibrotic from chronic shortening, it can entrap the nerve. Shock waves create microtrauma in that fibrotic tissue, which triggers a healing cascade involving nitric oxide release, increased local blood flow, and breakdown of calcific deposits. This is why the mechanism is mechanical and biological rather than purely anti-inflammatory. A counter-intuitive point that took me a while to learn: the pain during treatment is not a sign that the therapy is working harder. Some clinicians push the energy settings higher when a patient reports significant discomfort, assuming the pain correlates with better penetration. This is wrong. I encountered this with a patient who had severe piriformis myofascial pain and was responding poorly to sessions at 0.15 mJ/mm². I increased the settings to 0.22, and the patient reported worse outcomes the following week. The issue was excessive tissue trauma triggering a protective muscle spasm that temporarily worsened the nerve compression. I dropped back to 0.12 mJ/mm² with a longer treatment time and more thorough warm-up with thermal therapy beforehand, and the next session produced significantly better results. The lesson is that moderate, consistent energy with proper tissue preparation outperforms aggressive settings every time.
Limitations and Cases Where This Method Fails Completely
The most important thing to understand about shock wave therapy for sciatica is that it will not help a patient with true radiculopathy from a herniated disc or spinal stenosis. If the sciatic nerve is being compressed by bone or disc material within the spinal canal or neural foramen, applying pressure waves to the gluteal muscles changes nothing about the mechanical compression at the source. I wasted months on this before I started getting proper imaging before recommending the treatment. An MRI or at minimum a CT scan should be part of the workup for anyone being considered for this therapy. Another failure scenario is acute inflammation. If the patient is in the early phase of a flare with active swelling, heat, and severe pain, shock wave therapy can worsen the condition by adding more microtrauma to already irritated tissue. I learned this the hard way with a patient who presented with acute piriformis syndrome following a fall. She had significant local edema and was extremely tender to light touch. I proceeded with treatment anyway at low settings, and she came back the next day with worsened symptoms that took two weeks to resolve. The workaround was straightforward: I now wait at least 10 to 14 days after an acute flare subsides before initiating any shock wave treatment, and I always use a shorter treatment duration and lower energy during the first two sessions of the protocol. There is also a practical limitation that nobody talks about enough: the availability of trained operators. Proper treatment requires knowledge of anatomical landmarks and the ability to adjust settings based on real-time patient feedback. Many clinics that offer this service have operators who received a one-day training course and then treat patients based on standardized protocols without individualized adjustment. The results from those clinics are consistently worse than what you get from someone who has spent years developing a feel for the tissue response. Ask about the operator's experience level before committing to a course of treatment.
Get the Full Details

Alternative Approaches When Shock Wave Therapy Is Not Appropriate
If you have confirmed radiculopathy from a structural cause, the evidence supports epidural steroid injections as a more appropriate first-line intervention for nerve root inflammation. Physical therapy focusing on core stabilization and neuralgliding exercises has moderate evidence behind it for both disc-related and muscular sciatica. For piriformis syndrome specifically, targeted dry needling or botulinum toxin injections into the piriformis muscle have stronger evidence bases than shock wave therapy, though the results are comparable in the long term. Surgery is the final option for structural compression that does not respond to conservative management, and it should be discussed with a spine specialist rather than a physical medicine provider. The bottom line is that Sciatica Shock Wave Therapy is a useful tool in a specific clinical window — chronic myofascial piriformis-related sciatica in patients who have failed basic conservative treatment and do not have structural compression. It is not a cure-all, it requires proper patient selection, and it performs best when delivered by someone who understands the anatomy and is willing to adjust settings on a case-by-case basis rather than running every patient through the same numbered protocol.