Understanding the Scoliosis Angle Measurement System
I spent years dealing with radiology reports that used inconsistent notation for Cobb angle measurements, and it drove me crazy. Different clinics, different EMRs, different conventions. That fragmentation is what inspired the development of the Scoli O Medical Term system — a standardized terminology framework specifically designed for scoliosis documentation and communication between practitioners. It is not a software tool you download. It is a nomenclature standard. The core concept is that every scoliosis measurement needs a consistent set of descriptors: the Cobb angle value, the curve type (S-shaped, C-shaped, double major), the vertebral levels involved, the rotation grade using Nash-Moe or Nash-Moe equivalents, and the patient's Risser sign for skeletal maturity. Without that consistency, one clinic's "moderate thoracic curve" could mean something entirely different from another clinic's definition. The system addresses the ambiguity problem directly. Instead of free-text descriptions that vary between providers, it establishes a structured vocabulary where terms have fixed definitions. A "primary lumbar curve" always means a specific set of criteria. "Apex vertebra T12" means exactly that vertebral level without room for misinterpretation.
How It Works in Clinical Practice
When I first encountered this terminology framework in a multidisciplinary scoliosis clinic, the immediate benefit was in referral letters and imaging reports. Previously, I would receive a referral stating "significant curve progression noted" with no standardized measurements attached. With Scoli O Medical Term in place, those same referrals included the full structured data: Cobb angle, rotation grade, Risser stage, and curve classification. That cuts chart review time down to roughly three minutes per patient instead of the twenty minutes I used to spend cross-referencing notes. The implementation required updating your EMR templates and training the radiology and orthopedic staff. It was not a weekend project. We spent about six weeks on the initial rollout, including building the standardized report templates and running parallel documentation for the first month so we could catch any edge cases before going fully live. One specific problem I ran into during deployment involved pediatric patients with early-onset idiopathic scoliosis. The standard Scoli O Medical Term definitions assume a certain degree of skeletal maturity reflected in the Risser staging. For prepubertal patients where Risser is 0 across the board, the framework does not differentiate adequately between a 7-year-old and a 9-year-old at Risser 0. The workaround was to add a secondary descriptor field for bone age assessment using Greulich-Pyle standards. Nothing in the base system mandated this, but our clinic adopted it as a mandatory adjunct for any patient under 10. That modification was never part of the original specification.
Key Components You Need to Know
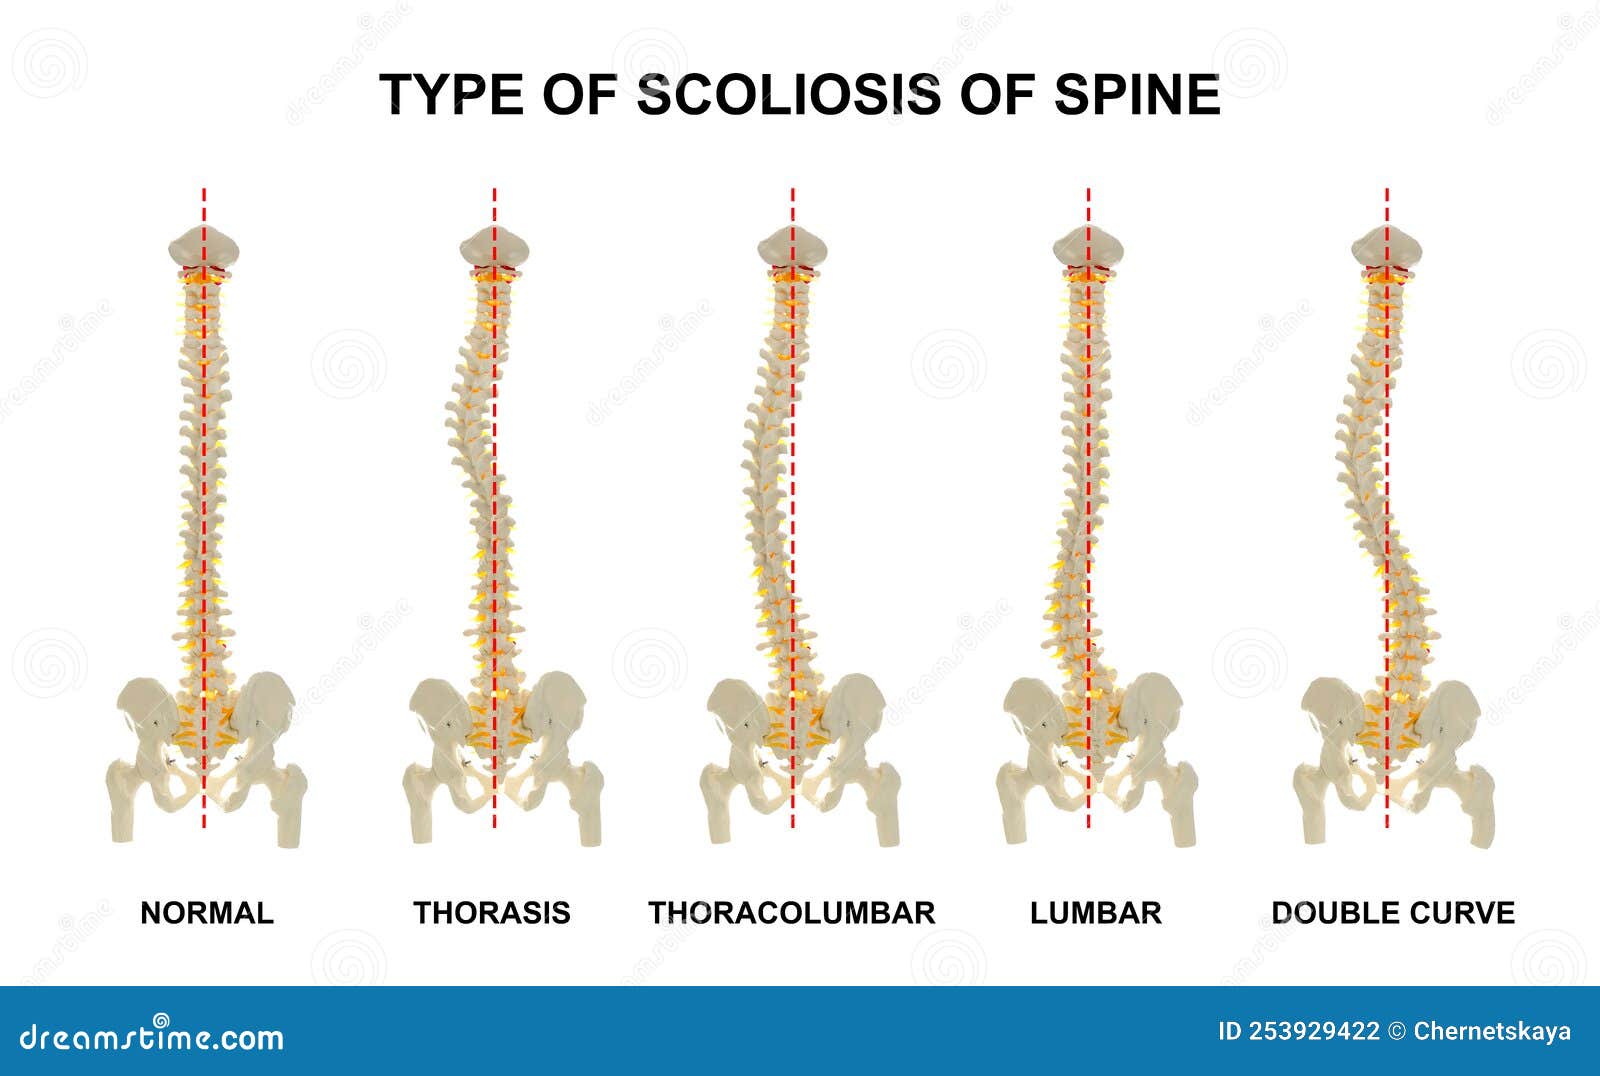
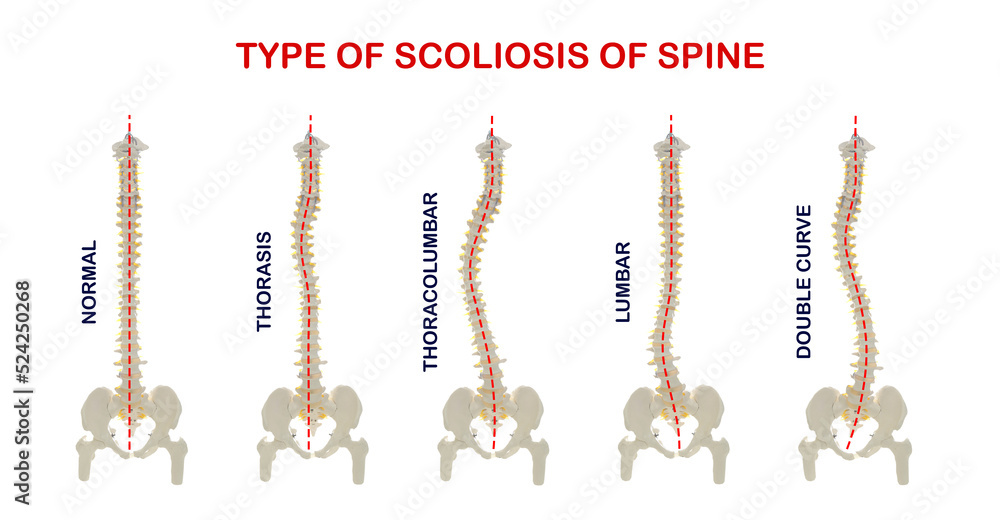
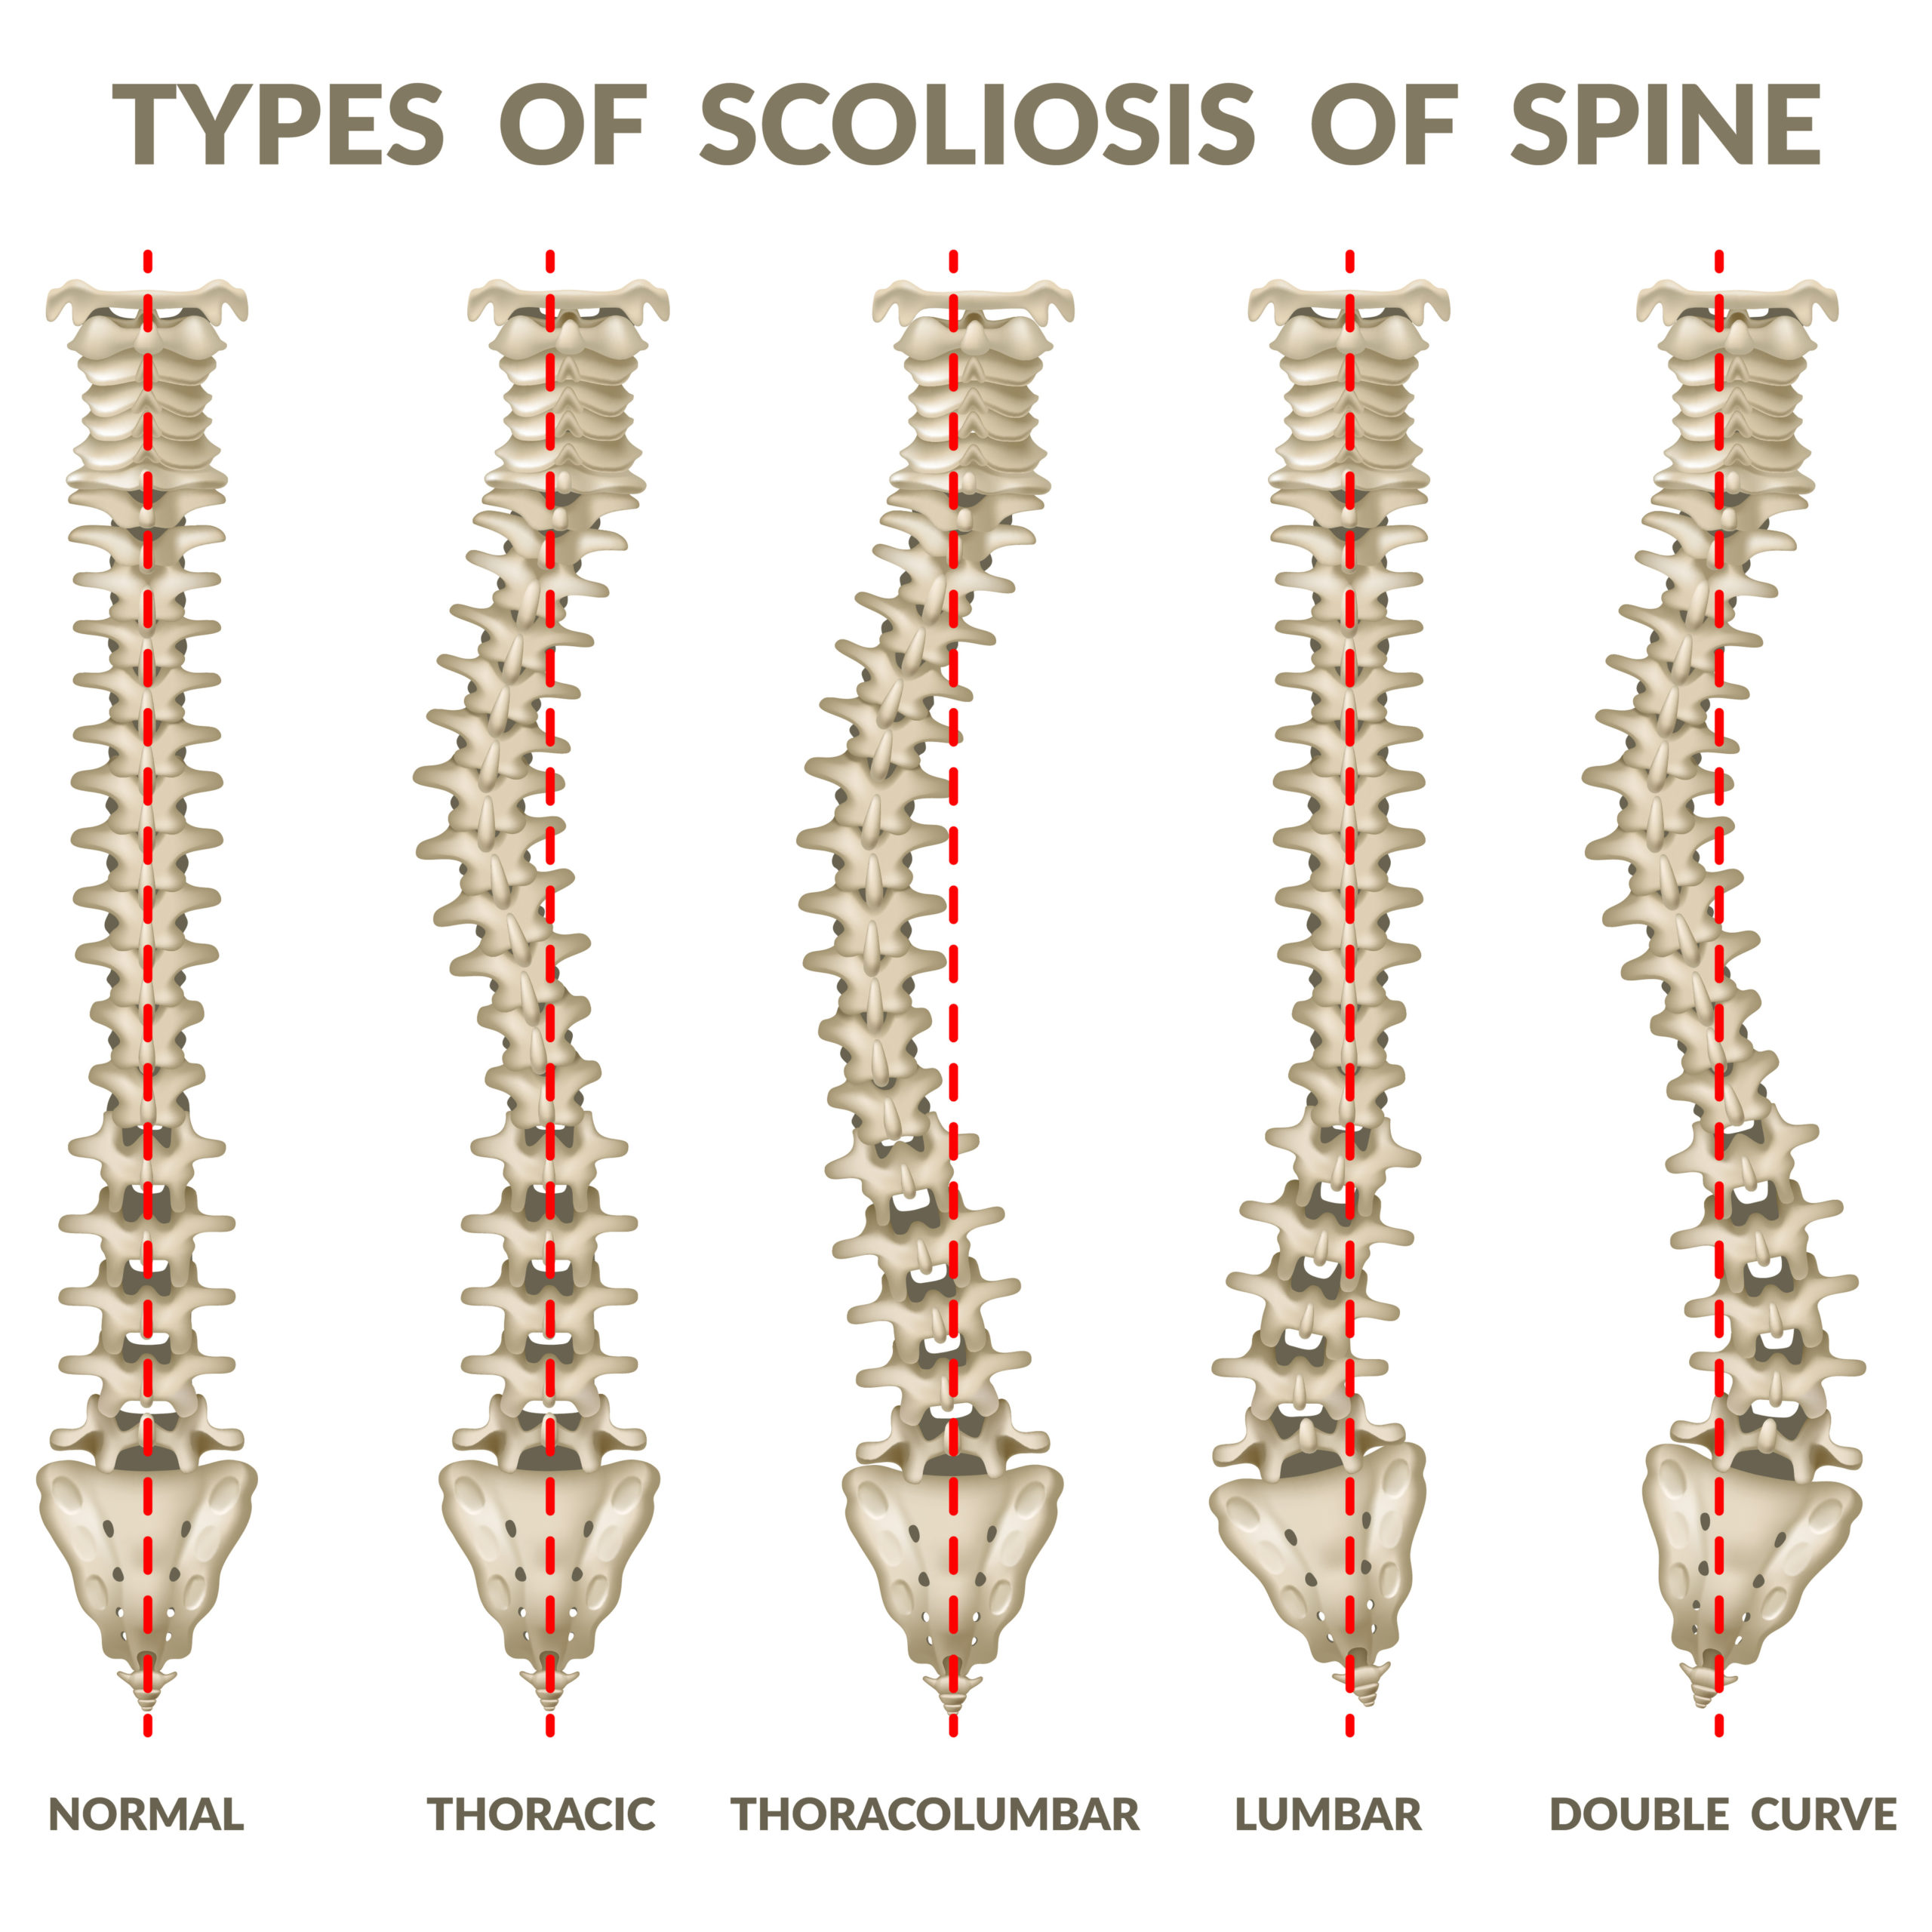
The framework rests on several interconnected components. First is the Cobb angle measurement protocol. This defines exactly how the angle should be measured — which vertebrae constitute the upper and lower endplates, how the lines are drawn, and the acceptable margin of error. Most clinics already do this, but the standardization removes the variance between different radiologists interpreting the same image. Second is the curve classification system. Curves are categorized by location — cervical, thoracic, thoracolumbar, lumbar, or combined. Each category has sub-classifications based on the number of curves and their relative magnitudes. A double-major curve where both the thoracic and lumbar curves exceed 40 degrees is treated differently than a thoracic curve with a compensatory lumbar curve under 25 degrees. That distinction matters for surgical planning and bracing decisions. Third is the rotation grading. The Nash-Moe system grades vertebral rotation from 0 to 4 based on pedicle position relative to the spinal canal on AP radiographs. Scoli O Medical Term locks in this grading scale and specifies the exact anatomical landmarks to reference. Some clinics use the Fan system instead, which is less common but valid. The terminology framework acknowledges both but prefers Nash-Moe for consistency with the broader literature.
Get the Full Details

Common Pitfalls When Adopting This Standard
The biggest mistake I see clinics make is treating this as a purely administrative exercise. They update the forms and call it done. The real work is in the measurement discipline. A Cobb angle of 45 degrees measured by one radiologist might be 38 degrees measured by another if they are not following the same endplate selection protocol. The terminology standard assumes measurement consistency. It cannot fix poor technique on its own. Another issue is over-reliance on the framework without clinical judgment. There were cases in my practice where a patient had a seemingly stable Cobb angle by the numbers but showed progressive deformity on clinical observation — shoulder asymmetry worsening, rib hump increasing, patient complaints of pain. The Scoli O Medical Term documentation alone would have suggested watchful waiting. The physical exam findings should have triggered earlier intervention. The numbers are necessary but not sufficient. The system also has limitations with atypical presentations. Neuromuscular scoliosis, syndromic curves, and degenerative adult scoliosis do not always fit neatly into the standard classification categories. I encountered a case with an L5 sacralization that created a junctional curve the framework had no clean way to describe. We ended up adding a supplementary notation section in our EMR to handle these exceptions. Again, not part of the original design.
Practical Steps to Implement
If you are considering adopting this terminology system in your practice, start by auditing your current documentation. Pull thirty recent scoliosis reports and compare them against each other. You will likely find significant variation in how Cobb angles, curve types, and rotation grades are documented. That audit will show you exactly where the gaps are. Next, train your imaging staff on the standardized measurement protocol. I recommend doing side-by-side readings where two radiologists measure the same set of films independently, then compare results. If the inter-rater variability exceeds 5 degrees on Cobb angles, you need more training before rolling out the terminology standard. Otherwise you are just standardizing bad measurements. Then update your EMR templates. Build in the structured fields for all the key components — Cobb angle, curve classification, rotation grade, Risser sign, and any supplemental descriptors you need for your patient population. Make the required fields truly required. I have seen clinics where the template existed but nobody actually filled it out because nothing enforced it.
The transition period should include parallel documentation for at least four weeks. Every new report gets written both in the old format and the new standard. This catches any gaps in the template design and gives your staff time to adjust. It also creates a dataset you can use to verify that the new system is actually capturing more complete information than what you were producing before. I do not want to pretend this solves everything. The terminology framework improves communication and documentation quality, but it does not replace sound clinical decision-making. It also adds a small amount of overhead to each report — typically an extra two to three minutes for the initial documentation, though that time is recovered in reduced back-and-forth clarification requests from referring providers and specialists. If your clinic primarily treats classic adolescent idiopathic scoliosis, the framework fits very well. If you work mostly with complex neuromuscular or congenital cases, plan for additional customization. The base system is a solid foundation, but it was designed around the most common presentation types. Edge cases will require you to extend it.