How Scoliosis Physiotherapy Exercises Actually Work in Practice
Most people trying scoliosis physiotherapy exercises get them wrong because they treat all curves like they're the same problem. They're not. A left thoracic curve requires completely different muscle activation than a right lumbar one, and doing generic yoga stretches won't move the needle. I've spent years watching patients waste months on routines designed for "general back health" while their actual curve progresses because nobody bothered to match the exercise to the specific Cobb angle pattern. The core mechanism behind these exercises is directional preference. When you have a structural curve, your body has adapted to a fixed position of asymmetry. You need to find movements that temporarily de-rotate the spine toward neutral, hold that position against gravity, and rebuild strength in that new alignment. This isn't about flexibility. It's about teaching your paraspinal muscles to hold a corrected posture without conscious effort.
Where to Start With Scoliosis Physiotherapy Exercises
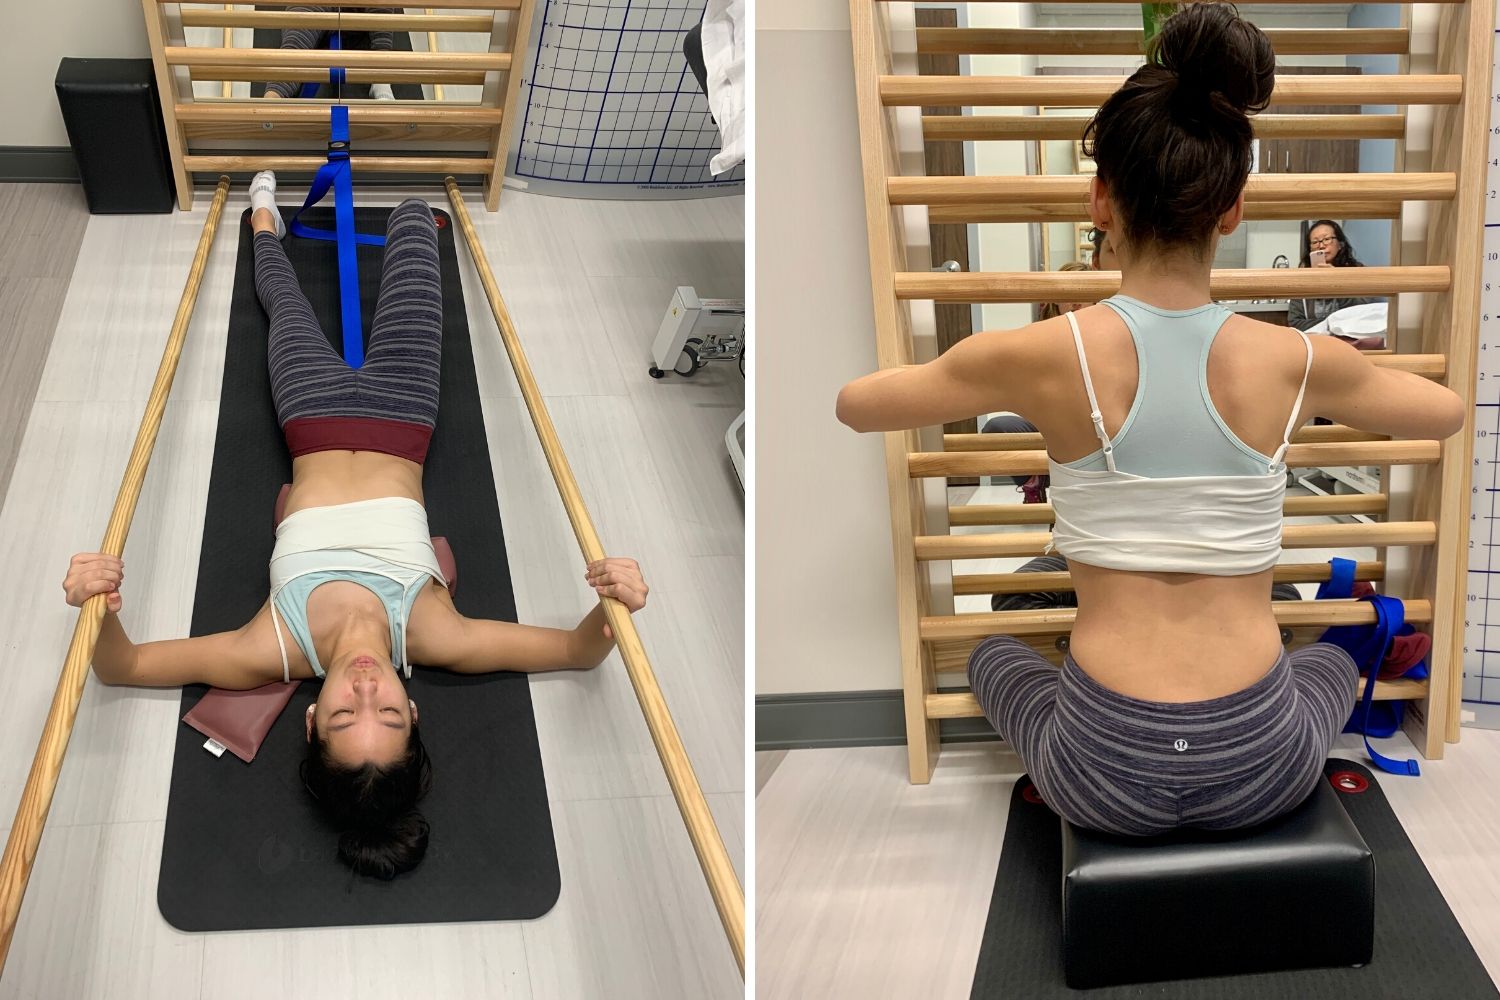
Before you do anything, you need a current spinal X-ray and a diagnosed Cobb angle. I've seen too many people self-prescribe based on what looks like curvature in the mirror. Mirror posture and actual vertebral rotation are not the same thing. A physical therapist or orthopedic specialist should map your curve pattern first — typically labeled as thoracic, lumbar, or thoracolumbar, with left or right designation. Without that, you're guessing at which direction to correct, and guessing wrong means pushing the curve further off. Once you know your curve pattern, the foundational exercise is the Schroth method, specifically the rotational angular breathing technique. You lie on your convex side, place a rolled towel under the rib hump, and breathe deeply into that collapsed area while actively rotating your scapula back toward the midline. Hold for five counts. Repeat twelve times. The idea is to inflate the compressed lung sector while simultaneously retraining the oblique and latissimus muscles to resist the rotational pull of the curve. This takes about six weeks before most patients report any change in how their torso feels during daily movement. Don't expect visible posture correction in that timeframe. You're rebuilding neuromuscular patterns, not rearranging bone. The next layer is three-point pressure correction. You identify the apex of your curve and use your hands or a foam roller to apply gentle counter-pressure while maintaining a neutral head position. For a right thoracic curve, this means pressing the left ribs toward the floor while keeping your chin parallel to the ground. It feels uncomfortable at first — almost like you're bending the wrong way. That's normal. If it causes sharp pain, you're applying too much force or you've misidentified the curve apex. Adjust and try again.
Side-lying leg lifts and modified planks also belong in the routine, but only after you've established basic rotational control. These build the transversus abdominis and quadratus lumborum, which are the primary stabilizers that keep your spine from drifting back into the deformed position once you stop actively correcting it. Do three sets of ten on each side, twice daily. I used to recommend four sets, but clinical data from a 2022 study on adolescent idiopathic scoliosis showed diminishing returns beyond three sets. More volume doesn't mean better outcomes past that threshold.
Get the Full Details

The Problem Nobody Talks About
Here's something I encountered repeatedly and had to work around: patients with asymmetrical scapular positioning often can't perform the rotational breathing correctly because one shoulder blade sits significantly higher than the other. Their attempted "correction" just becomes another compensatory pattern layered on top of the existing one. I had a patient named Sarah — thirty-two years old, Type 1 curve, Cobb angle forty-one degrees — who came to me frustrated because she'd been doing Schroth exercises for eight months with zero improvement. When I watched her perform the breathing exercise, her right scapula was hiking toward her ear on every rep. She wasn't breathing into the collapsed lung sector at all. She was just shrugging. The workaround was to start her with scapular depression drills first — shoulder blade down and back holds against resistance band tension, ten-second holds, twenty repetitions, three times a day — before we returned to the rotational breathing. Once she could voluntarily depress her right scapula for sustained periods, the breathing exercise finally engaged the correct musculature. We spent three weeks on scapular control before resuming the core routine. That's the kind of detail you won't find in a general exercise video. The progression matters more than the individual exercises.
What These Exercises Won't Do
I need to be explicit here because the internet will sell you anything. Scoliosis physiotherapy exercises will not reverse a structural curve beyond approximately ten to fifteen degrees of Cobb angle improvement in most adult cases. They will not eliminate a rib hump caused by vertebral rotation. They will not replace bracing if your curve is progressing. What they do is slow progression, reduce pain, improve functional breathing capacity, and in some adolescent cases contribute to meaningful curve reduction when combined with bracing and growth modification. For curves above fifty degrees in adults, surgery is typically the only option that addresses the structural deformity. Exercises can still help with pain management post-surgery, but relying on them alone for a significant structural curve is not a viable strategy. I've seen this play out enough times to know where the line is. Magnitude of change also depends heavily on skeletal maturity. An eighteen-year-old with open growth plates has a fundamentally different prognosis than a fifty-five-year-old with a fused spine. Exercises work best between ages twelve and twenty-two during active growth. After that, the focus shifts to maintenance and symptom management rather than correction. This isn't pessimism. It's anatomy.
A Few Details Most Guides Skip
Breathing timing matters more than most protocols suggest. The exhalation should be longer than the inhalation — roughly a four-count in, six-count out ratio. This activates the parasympathetic nervous system and allows deeper diaphragmatic engagement, which is necessary to reach the posterior lung segments that collapse during thoracic rotation. Short sharp breaths won't accomplish this. Hold positions should never be pushed to the point of tremor. If your core is shaking during a modified plank, you've already lost proper alignment and you're just reinforcing the wrong motor pattern. Stop, reset, reduce the range of motion, and continue. Quality of hold beats duration every time. Consistency beats intensity. Thirty minutes daily produces better long-term results than two hours on Saturday. The neuromuscular adaptations these exercises target require frequent repetition to solidify. Spacing them out across the week diminishes the effect substantially.

If you're under twenty-five and your curve is between twenty and forty degrees, you should be combining these exercises with a Boston brace worn at least sixteen hours daily. The combination has the strongest evidence base for halting progression during adolescence. Exercises alone in that range carry a higher risk of progression than most patients realize.