Understanding What An LPN Can Actually Do On A Shift
The Scope Of Practice For Lpn varies from state to state, and that single fact is what causes the most headaches for both new graduates and nurses transitioning between states. I spent six years working med-surg and long-term care before moving into dialysis, and every single transition period meant re-learning my boundaries because the rules shifted at the border. An LPN operates under a different level of autonomy than an RN. The core difference comes down to assessment depth, clinical judgment, and IV medication authority. LPNs handle focused assessments rather than comprehensive ones. They collect data. RNs analyze that data and adjust care plans based on findings. That's the textbook version. The actual workplace version involves a lot more gray area, especially in long-term care facilities where staffing models blur those lines regularly. Most LPNs administer oral medications, intramuscular injections, subcutaneous injections, and insulin. Many states allow LPNs to start and manage IV fluids and certain IV medications with additional certification. Wound care, catheter insertion, and specimen collection fall within standard practice almost everywhere. What does not fall within standard practice is initiating complex assessments, performing triage decisions independently, or making nursing diagnoses that change the course of treatment without RN or physician involvement.
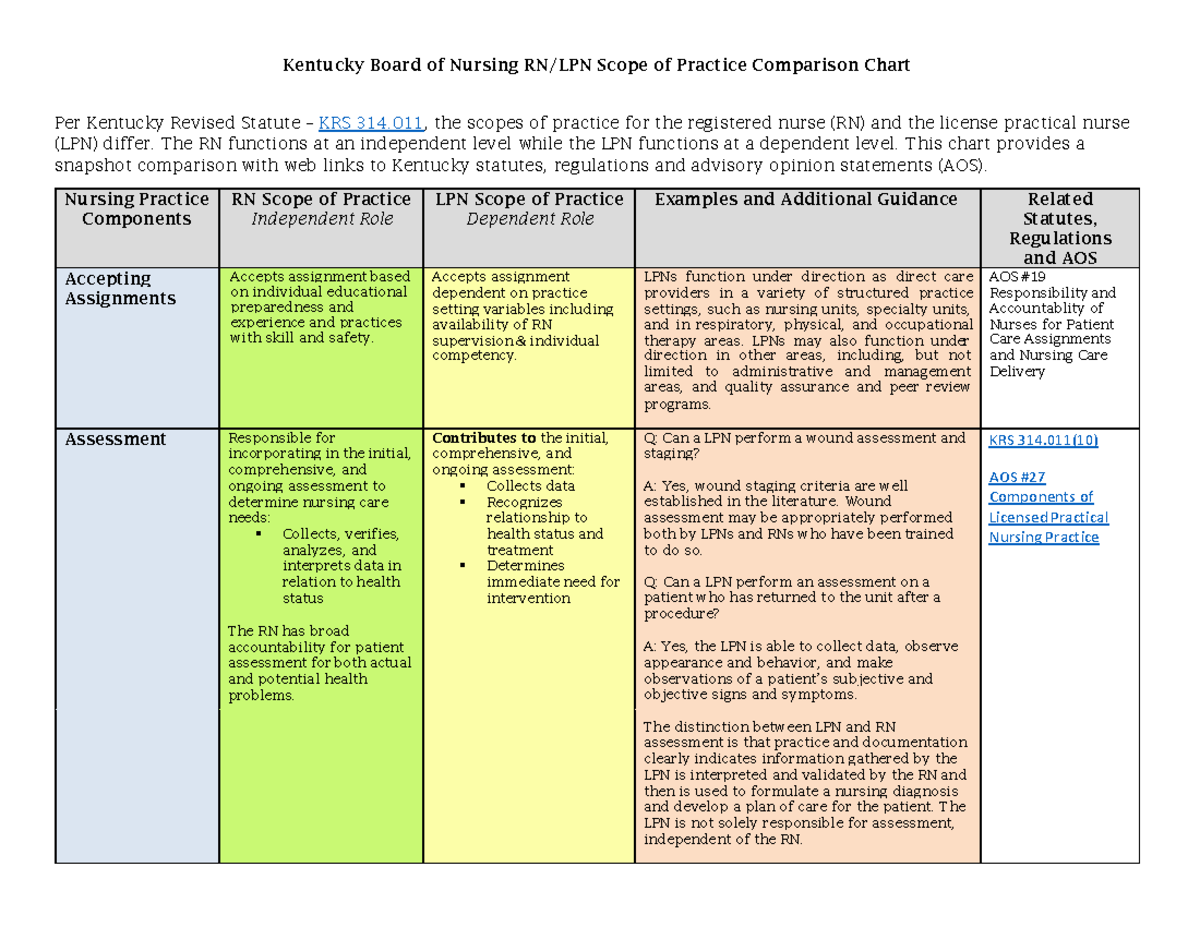
I remember one specific situation that highlighted the gap between what the handbook says and what actually happens. I was working in a rural long-term care facility in Kentucky. Our RN position was being filled during a hospital conversion project, so for three weeks there was no RN on the night shift. A patient with a history of heart failure came in with increased shortness of breath and edema. The scope of practice technically said I should contact the attending physician or a visiting RN for assessment guidance. What actually happened was I assessed the patient, noted the crackles at the lung bases, tracked the intake and output over twelve hours, and called the physician with a clear clinical picture. The physician made the decision to increase the diuretic. It worked out fine. But that situation absolutely should not have played out that way, and it exposed a serious staffing problem that nobody wanted to admit.
Where LPN Scope Gets Complicated
The complication usually arises around IV therapy. Some states allow LPNs to administer IV push medications after completing a board-approved course. Others restrict LPNs to continuous IV infusions only. North Carolina lets LPNs do IV push antibiotics and pain medications with a 75-hour approved program. Texas restricts LPN IV practice more tightly and requires additional competency validation. California allows LPNs to manage IV therapy in acute care settings but with significant restrictions compared to RNs. Clinical judgment is another area where the boundaries get fuzzy. LPNs are expected to recognize when a patient is deteriorating and escalate appropriately. That is actually part of the scope. What is not part of the scope is diagnosing the deterioration or determining the treatment plan independently. I have seen LPNs successfully catch early signs of sepsis and get patients saved because they understood their responsibility to communicate findings quickly. I have also seen LPNs hesitate too long because they were unsure if something was within their wheelhouse. Both scenarios are common and both are valid concerns. A counter-intuitive thing about LPN practice is that the narrowest scope often produces the safest outcomes. When an LPN sticks to well-defined parameters, medication errors drop, documentation improves, and patient outcomes stay consistent. The moment someone pushes beyond established boundaries because they think it will help, that is when problems start. Not because LPNs lack competence. Because the system did not train them to operate in that expanded capacity, and no amount of willingness bridges that gap.
Get the Full Details

What LPNs Cannot Do In Most Jurisdictions
Initiating a nursing diagnosis is off limits in nearly every state. This is the process where a nurse identifies a specific health problem based on assessment data. It requires the kind of clinical reasoning and legal accountability that comes with an RN license. LPNs contribute assessment data. They do not finalize the diagnosis. Evaluating the effectiveness of a nursing intervention on its own is also restricted. LPNs can report observations and changes in patient condition. But formal evaluation of whether a plan is working requires RN or physician involvement. This is not about trust. It is about liability and legal structure. Patient education at the comprehensive level belongs to RNs. LPNs reinforce teaching that has already been established by the RN or physician. I can tell a post-operative patient how to use an incentive spirometer because the RN already covered the purpose and expected outcomes. I cannot be the one who initially explains the surgical procedure risks, recovery timeline, and red flag symptoms. Those conversations require the broader assessment and teaching competencies that come with an RN license.
Practical Navigation Tips
Download your state's nursing board actual scope documents. The summaries on hospital websites are often incomplete or outdated. The official board document for your state will list every procedure, medication type, and clinical activity an LPN is authorized to perform. Kentucky's document runs about forty pages. Florida's is shorter but references multiple advisory opinions that modify the baseline rules. Read the whole thing. Highlight the sections that contradict what your employer told you during orientation. They probably will. Keep a personal reference card with your state's key limitations. I wrote mine on a small laminated card that fits in my scrub pocket. It lists what IV meds I can push, what assessments I'm expected to complete on admission, and the escalation protocol for when something falls outside my scope. This card has saved me more than once when a charge nurse asked me to do something I knew wasn't within my boundaries but couldn't immediately recall the exact regulation. Build relationships with the RNs on your unit. The best LPN-RN partnerships I have had were built on mutual respect and clear communication, not on anyone trying to expand or contract roles. When an RN knows you understand your limits and will speak up when something feels wrong, they trust you more with complex tasks. When an LPN stays silent about scope concerns, trust erodes quickly. I watched one unit's charge nurse essentially forbid LPNs from questioning medication orders after a near-miss incident. That culture lasted three months before three more incidents pushed the staff to restart the conversation. The underlying issue was never the LPNs' willingness to speak up. It was the system that punished good judgment instead of rewarding it.
The biggest limitation of understanding LPN scope is that enforcement depends entirely on individual employers and state boards. There is no universal standard. An LPN licensed in Ohio cannot simply transfer those privileges to Georgia and expect the same responsibilities. Each state board maintains its own rules, and those rules change periodically. Georgia modified its LPN IV therapy requirements in 2022, expanding what LPNs could administer but adding mandatory competency verification. New York has maintained some of the most restrictive LPN scope rules in the country, particularly around IV therapy and pain management. If you are considering relocation, check the current board document before you accept any position offer.