Let's talk about scope of practice
Most people think it's just a set of rules about what you can and can't do. It isn't. It's the boundary line between legal employment and losing your license. The difference matters in ways that don't show up on any exam. I worked on a med-surg floor for years. One night I had a post-op hip replacement who became tachycardic and hypotensive at 2 AM. His surgeon was unreachable. The standing order allowed me to give a 250mL bolus of normal saline, but not to push fluids faster than that rate. His BP kept dropping. I called the charge nurse, we ran through the situation, and I documented everything before I went beyond the standing order and held his hand while waiting for the rapid response team to arrive. If I'd just pushed fluid without the escalation, I'd have been out of my scope. The borderline between good judgment and negligence in those moments isn't written anywhere except in your state's nursing practice act and your facility's policies. Knowing the exact text saves you more than knowing protocols does.
Scope Of Practice Of A Nurse
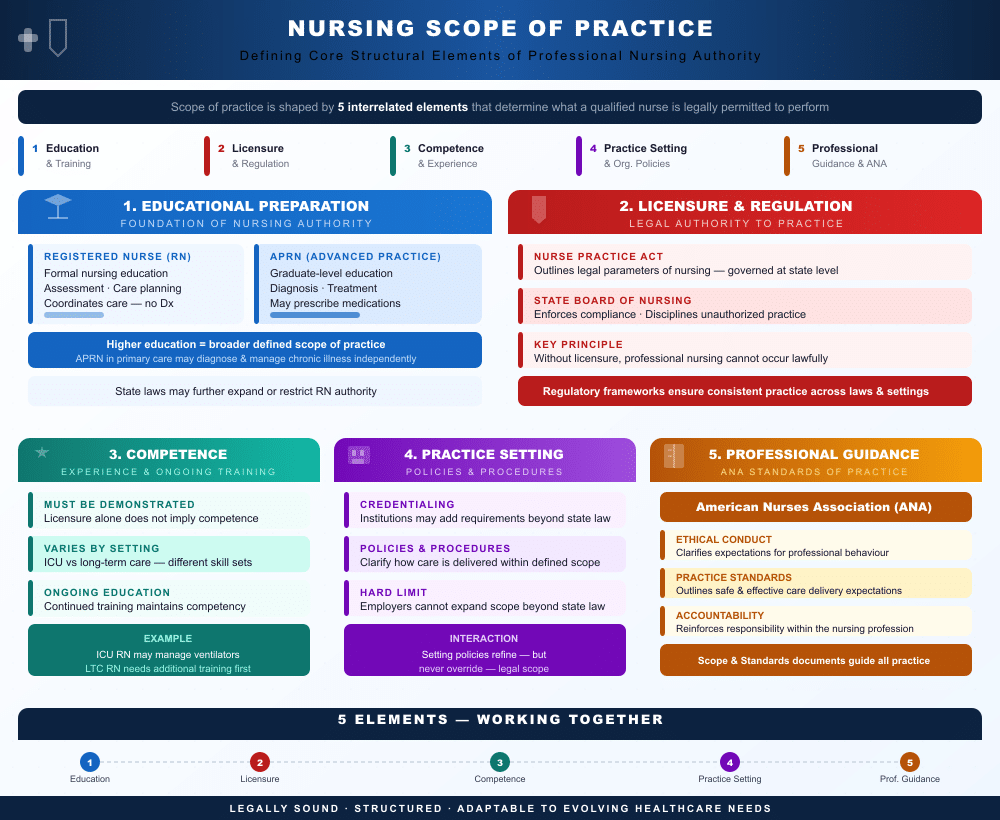
Your nursing scope of practice comes from three overlapping sources. First, the state board of nursing. This is your legal floor and ceiling. It defines what a registered nurse may do independently versus what requires a physician or advanced practice order. Second, your facility's policies. These can be stricter than state law but never looser. Third, your individual competency and education. Even if the state says you can do something, your employer can limit that right based on verified training and credentialing. The actual scope changes by state. Some states have adopted the National Council of State Boards of Nursing model act language. Some have added independent practice provisions for certain assessments or interventions. Others restrict nursing assessment in areas that most nurses assume are standard. If you move between states, the scope changes. Don't assume reciprocity means identical authority. One thing most new nurses miss is the gap between what the law permits and what your employer will let you do. Your state may authorize nursing assessment of wound depth using a sterile probe. Your hospital's policy may restrict that to certified wound care nurses only. In practice, you operate inside the tighter boundary. That's how it works on the floor.
Another counterintuitive point is that scope isn't static for an individual nurse. It shrinks and expands based on credentialing, privileges, and documented competencies. You can hold an RN license in good standing and still not be credentialed for central line dressing changes on a particular unit. That's normal. It's also the reason you should always check your current privileging list before taking on a new skill, even if you've done it before at another job. Advanced practice registered nurses operate under a different framework entirely. The APRN scope includes diagnosis, prescribing, and often independent practice authority depending on the state. But even here, collaborative agreements and institutional bylaws matter. A nurse practitioner with full prescribing authority in one state may need a signed collaborative agreement with a physician in a neighboring state. The license doesn't travel. The authority attached to it doesn't either. Here's a practical edge case I ran into. A patient on my unit had a peripherally inserted central catheter and developed redness and swelling at the site. I assessed it. I documented the size, erythema extent, and pain level. I could legally perform the assessment under my state's scope. However, when it came to removing the line, my facility required a specific vascular access certification and a physician order. Removing it without that order would have crossed my scope, even though the assessment itself was fully within it. The workaround was straightforward: I called the vascular access team, they came, removed the line, and I managed post-removal care within my scope. Two hours and no incident. The lesson is that assessment and intervention often live in separate legal buckets, and that distinction is where people get tripped up.
Get the Full Details

Common mistakes I see regularly: Mistake one: assuming that completing a continuing education course expands your legal scope. It doesn't. Course completion may satisfy employer requirements, but the legal boundary remains set by your state board. You can be certified in chemotherapy administration and still violate scope if your state doesn't authorize that intervention for general RNs without a specific order or protocol. Mistake two: treating scope as a personal judgment call. It isn't. Scope is defined by statutes, administrative code, board rules, and facility policy. Personal belief about what makes clinical sense doesn't override any of that. When there's ambiguity, the conservative interpretation protects your license.
There's also a blunt downside most people don't want to hear. Relying solely on textbooks, videos, or quick-reference guides for scope isn't sufficient. These materials summarize, and summaries leave out the jurisdiction-specific amendments, the recent board decisions, and the policy updates that happen constantly. A PDF downloaded today might reflect scope rules that were changed six months ago in your state. Use them as a starting point, then verify against your current state board website and your employer's policy library. That's the only safe workflow. If you want a quick reference that covers the core definitions and common procedure boundaries for general RN practice in most states, you can download this reference document here: Scope of Practice Quick Reference for RNs (PDF). It's organized by intervention category with state-specific footnotes where authority diverges. It won't replace your board's official documents, but it's useful for shifting quickly between jurisdictions or orienting to a new position. The scope of practice concept has genuine limitations. It cannot protect you from a hostile employer who expects you to perform out-of-scope procedures under pressure. It cannot replace documentation habits that show your clinical reasoning stayed within boundaries. It cannot shield you from a board complaint filed by a colleague who disagrees with your judgment. Knowing scope well reduces risk, but it doesn't eliminate it. The risk is managed by combining knowledge of your legal framework with clear communication, appropriate escalation, and thorough documentation.
For practical purposes, the workflow looks like this: Check your state board's current nursing practice act before taking on any unfamiliar intervention. Cross-reference your facility's policy manual for that specific procedure. Confirm your individual credentialing and competency list. If any layer restricts the intervention, escalate rather than proceed. Document the decision process, including who you consulted and what you were told. This takes roughly five to ten minutes and prevents the kind of legal exposure that can end a career in a single filing. The most useful resource after the state board act is your professional organization's scope and standards documents. The American Nurses Association publishes detailed scope and standards for different practice settings. These aren't legally binding, but they establish the professional baseline that boards, employers, and courts frequently reference. They're especially helpful when your state's regulations are vague on a particular intervention.

Another area worth attention is the interaction between scope and telehealth. Remote assessment, triage, and follow-up have expanded what nurses do daily, but telehealth scope varies significantly by state. Some states require in-person evaluation before certain nursing recommendations. Others allow broader independent tele-nursing action. The platform you use doesn't change the legal standard. Your location and the patient's location both matter for jurisdictional purposes. Finally, a note about scope in leadership roles. Charge nurses, resource nurses, and clinical nurse specialists often navigate scope ambiguities because they're the ones being asked to fill gaps. The authority to delegate, assign, or temporarily expand nursing duties on a unit usually comes from the nurse manager or director, and that authority exists within the bounds of your state's regulations and your employer's policies. Acting beyond those bounds as a leader carries the same license risk as acting beyond them as a staff nurse, plus additional liability because of your position. Scope of practice isn't dramatic. It's administrative, legal, and deeply practical. It determines what you can do without losing your livelihood. Read the actual documents. Keep them current. Verify before you act. That's the process.