What Semantic Feature Analysis Actually Looks Like in Practice
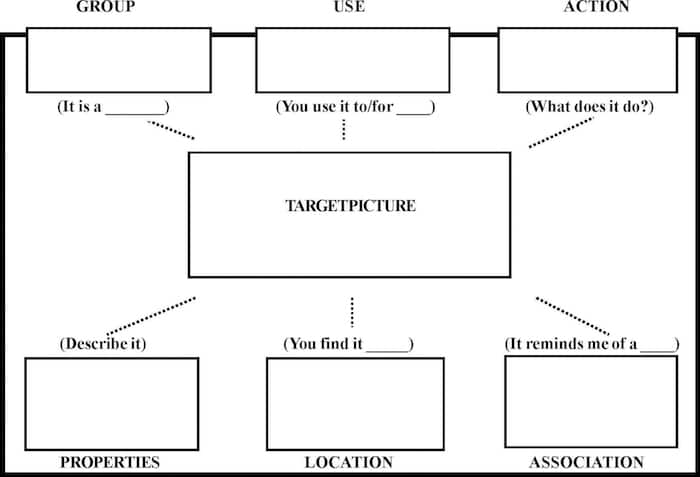
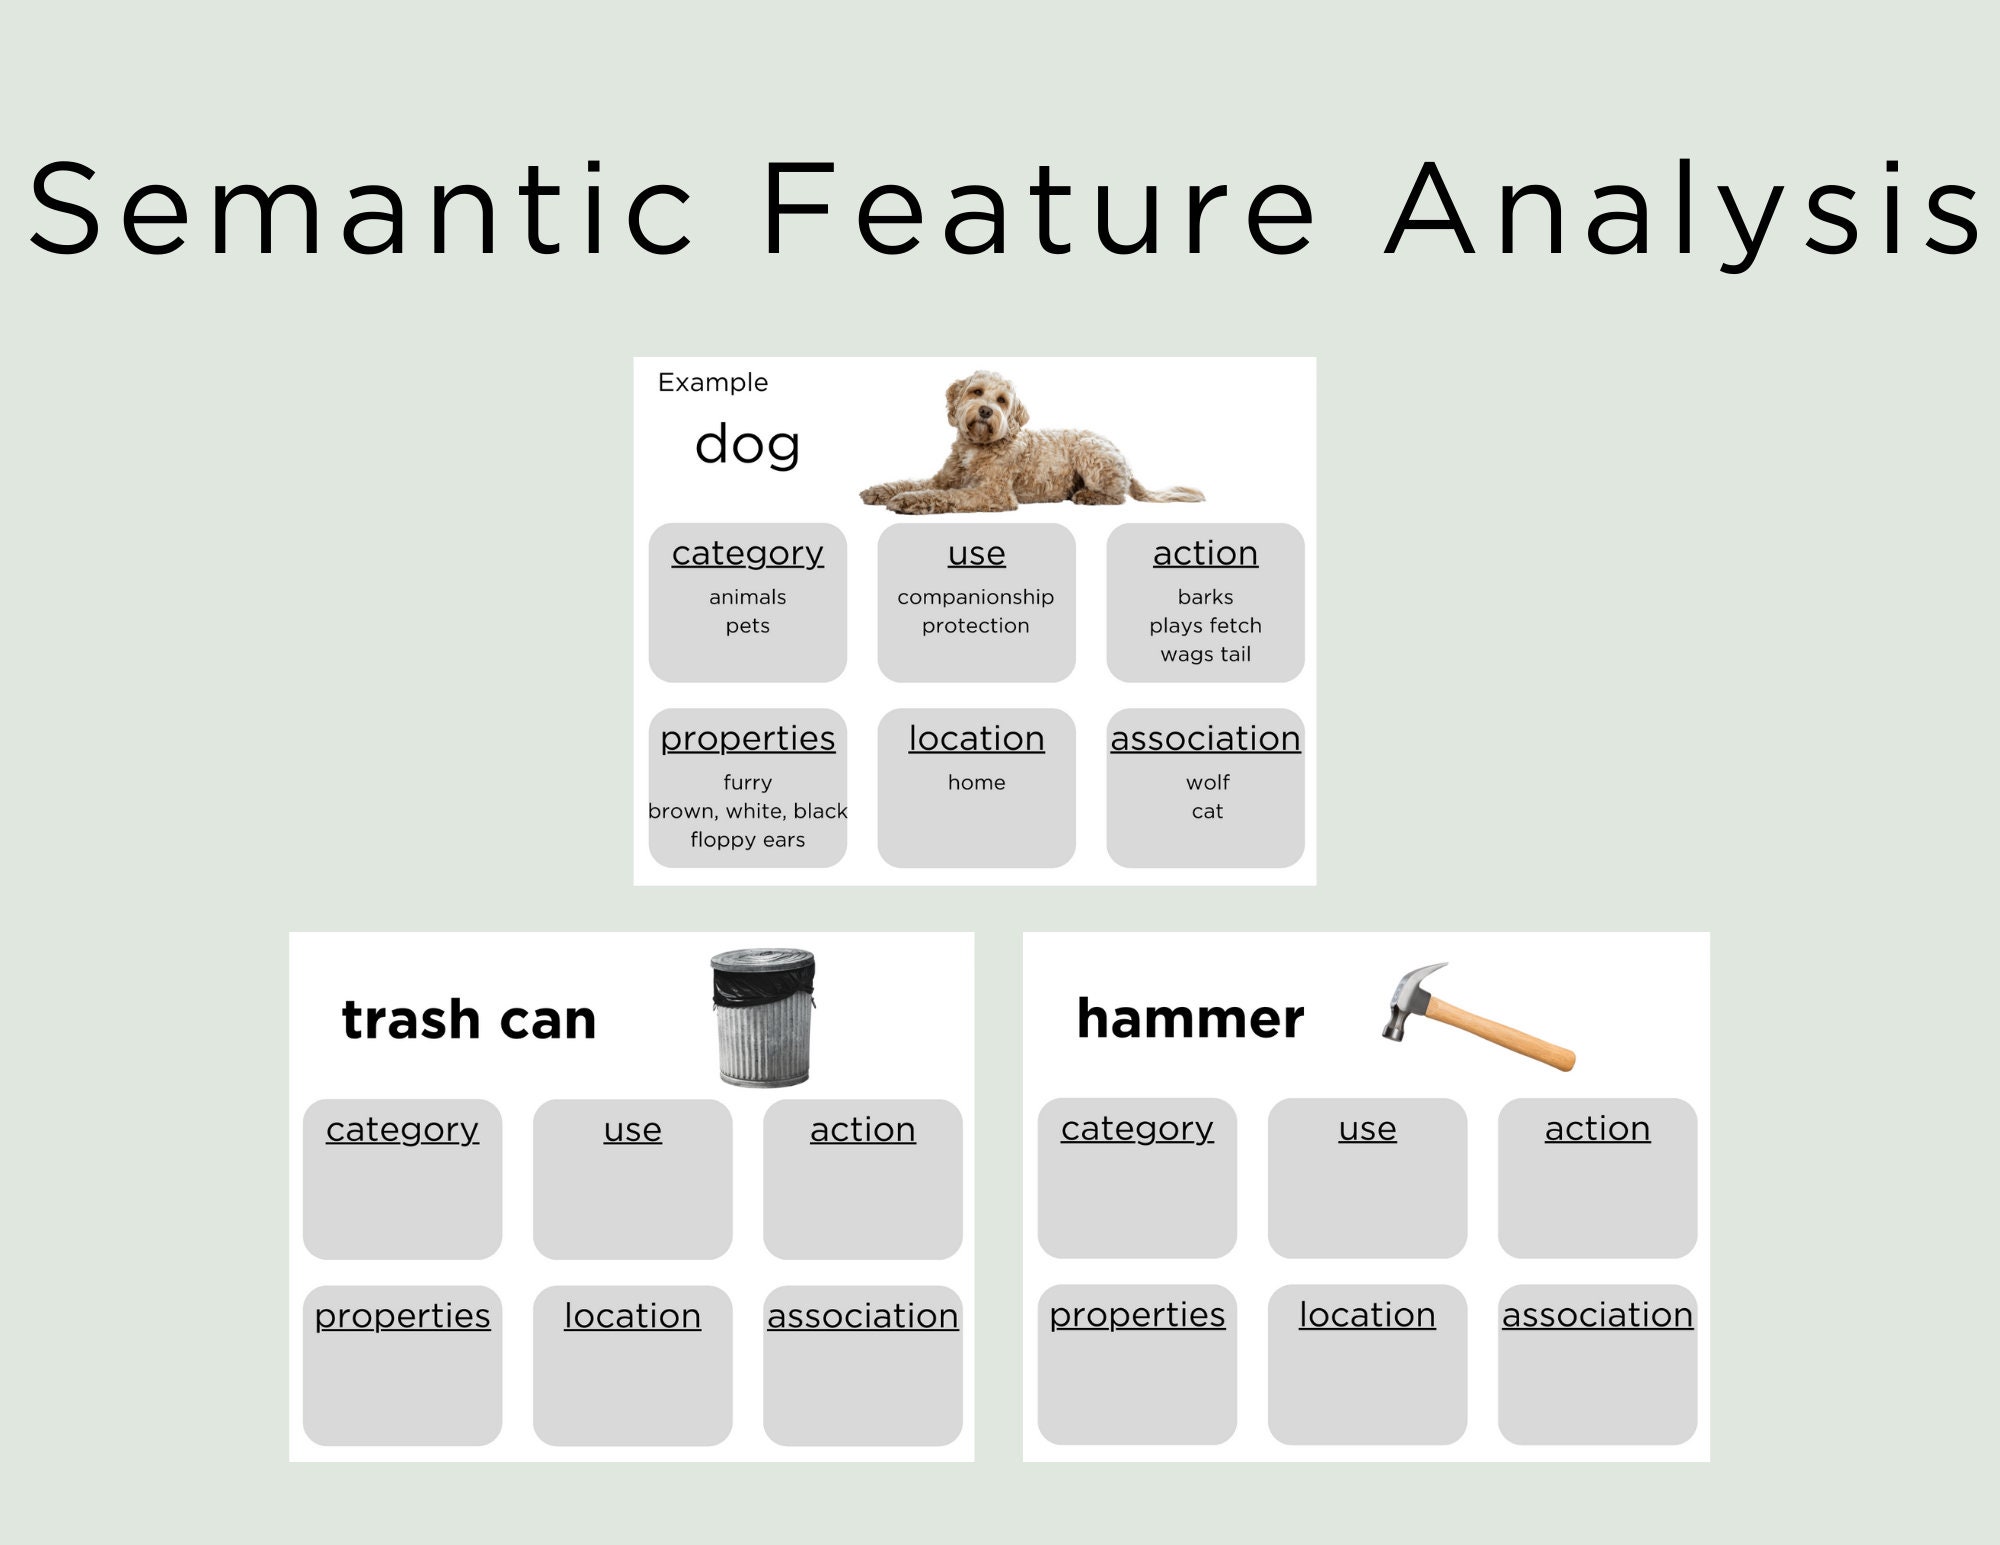
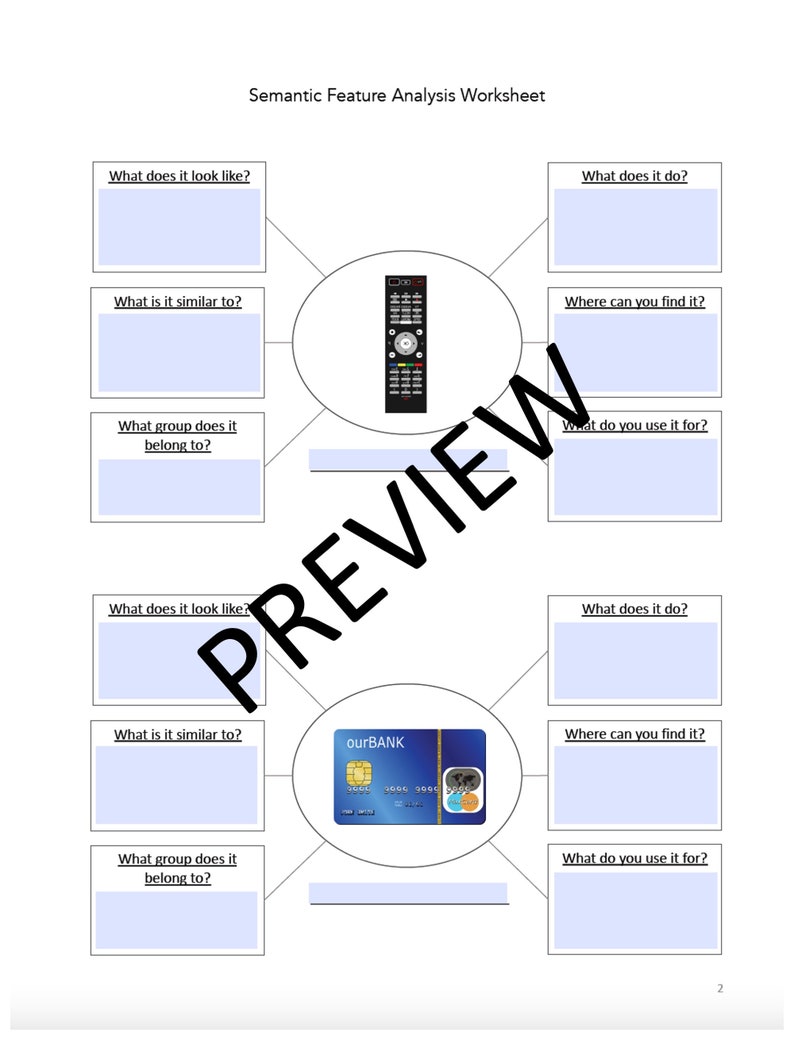
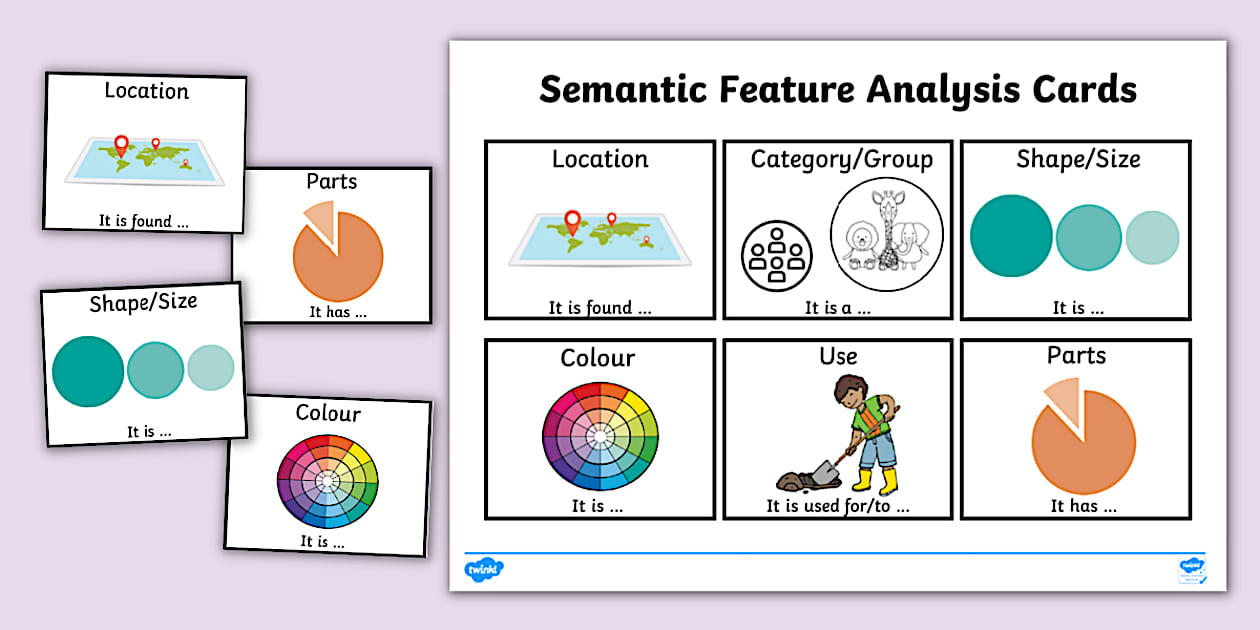
Semantic Feature Analysis is a treatment approach for naming deficits, mostly in aphasia. The clinician picks a target word, then walks the patient through a grid of semantic categories — what it's used for, where it's found, what it looks like, how it feels, its category membership. The patient checks off which features apply. Over repeated sessions, the goal is to strengthen the network of connections around that word so retrieval becomes faster and more automatic. It is not a magic bullet. I learned that the hard way with a post-stroke patient whose anomia was severe but whose comprehension was relatively preserved. We did SFA on concrete nouns for six weeks. She improved on trained items. Generalization was minimal. The workaround was pairing SFA with phonological component analysis — working on sounds and syllable structure alongside the semantic work. Combined, the gains carried over to untrained items noticeably better than SFA alone ever did.
Semantic Feature Analysis Goal Bank
A Semantic Feature Analysis Goal Bank is just a compiled set of ready-to-adapt clinical goals written in measurable language, organized around the SFA framework. Instead of drafting goals from scratch for every patient who presents with a naming deficit, you pull from a library of tested formulations. The goals should be specific, observable, and tied to a performance criterion and a condition — the standard SMART format everyone in the field still pretends to follow. Here is what that looks like on paper: Goal example: Given aSemantic Feature Analysis worksheet targeting 10 high-frequency nouns, the patient will correctly produce the target word upon semantic cueing in 4 out of 5 trials across 3 consecutive sessions, as measured by clinical observation.
The important detail most people skip: the condition matters. "Upon semantic cueing" is different from "without cueing." If your goal says the latter but your data shows the patient only succeeds with cues, you are not measuring what you think you are measuring. Write the goal to match the actual testing condition. I have seen entire insurance denials hinge on that mismatch.
Get the Full Details
How to Use a Goal Bank Without Making It Useless
Pull a goal that matches your patient's profile. Adjust the target word set, the number of items, and the cueing level. Keep the measurable parts — the trials, the sessions, the criterion — intact unless you have a reason to change them. Document every modification. Insurance auditors do not care that you thought the original was too easy. They care that your written goal matches what you actually documented in your notes. Another thing nobody writes about: the goal bank is only as good as your baseline data. I once used a pre-written goal that specified 80% accuracy across 5 sessions on a patient who scored 30% on initial assessment. We missed the goal by a wide margin even though the patient improved meaningfully. The goal bank gave me a convenient target, but it was the wrong target for that person. Always run your own baseline before adopting a template goal verbatim.
Where SFA Actually Breaks Down
It does not work well for patients with significant comprehension deficits. If the patient cannot process "what is it used for" or "what category does it belong to," the entire feature analysis collapses into a guessing game. I stopped using pure SFA with moderate-to-severe Wernicke's aphasia patients and switched to melodic intonation therapy or phrase compression instead. The naming gains were marginal at best with SFA in that population, and the session time felt wasted. It also struggles with abstract nouns. SFA thrives on concrete, easily categorized items — fruit, tools, animals. Try it with "freedom" or "justice" and you will watch the patient stare at the worksheet for ten minutes. The semantic features become philosophically debatable rather than clinically useful. Limit your target word selection to concrete vocabulary in the early phases of treatment.
What a Realistic SFA Goal Set Looks Like
Short-term objectives should track the mechanics of the therapy itself before expecting word retrieval gains: Given a Semantic Feature Analysis grid with 8 categorical prompts, the patient will correctly identify and mark at least 6 applicable features per target noun in 4 out of 5 trials. Mid-term goals bridge features to production:

Given a Semantic Feature Analysis worksheet and verbal prompt to "tell me about it," the patient will produce the target word within 10 seconds in 4 out of 5 trials across 3 consecutive sessions. Long-term goals address real-world use: During a structured naming task with 20 high-frequency objects, the patient will independently retrieve the target label without cueing in 70 percent of opportunities across two clinical days.
Each of those is testable. Each has a clear condition, a measurable behavior, and a criterion. The first one measures comprehension of features. The second adds retrieval time as a variable. The third removes cueing entirely. That progression mirrors how the therapy actually works — comprehension first, then access, then independence.
One Practical Detail That Saves Time
Build your feature grids in a spreadsheet before the session. Columns for the target word, the semantic category, the patient response, and the cue level needed. Rows for each feature dimension. When you are in the room with a patient, you should be talking, not fumbling with a printed worksheet that has a smudge on it or a missing column header. A clean digital grid cuts prep time to under five minutes per word set and makes data collection during the session trivial. I export the completed grids as PDFs at the end of each session for documentation. Takes thirty seconds and keeps your progress notes accurate. If you are building a Semantic Feature Analysis Goal Bank from scratch, start with the core SFA components — feature identification, feature-to-word mapping, cued retrieval, and independent retrieval — and write one goal for each stage. Use published SFA protocols as reference points, not templates to copy directly. Cassells and Wingfield are the standard citations here. Their work establishes the feature sets that actually move the needle. Anything beyond that is usually filler. The goals need to reflect the severity of the naming deficit. A patient who can single-word reproduce but not converse-navigate needs different targets than someone who cannot name a pictured object at all. Match the goal language to the actual clinical picture, not to the most convenient pre-written option in the bank.