
Getting Sensory Integration Therapy Right
Most people treat sensory integration activities like a menu you pick from. You can't. That's the first mistake I see repeatedly in clinic settings and at home programs that fall apart after two weeks.Sensory Integration Therapy Activities work by targeting the brain's ability to organize and interpret sensory input from the body and environment. The core framework comes from A. Jean Ayres' occupational therapy model. Vestibular, proprioceptive, and tactile input get strategically introduced to help someone build better neural regulation over time. This isn't a one-session fix. It's a protocol built on measurable progress across weeks and months. Here's what actually happens when you do this properly. You introduce a controlled amount of disorienting input—say, spinning on a swing for exactly twenty seconds—then immediately follow it with a grounding task like pushing against a wall for thirty seconds. The vestibular challenge creates a temporary dysregulation state. The proprioceptive work afterward gives the nervous system something concrete to latch onto. That cycle is what builds integration. Do it right, you see measurable improvements in attention and emotional regulation within three to four weeks. Do it wrong, and you either under-stimulate the person or push them into overload where nothing productive happens.
What Sensory Integration Therapy Activities Actually Look Like
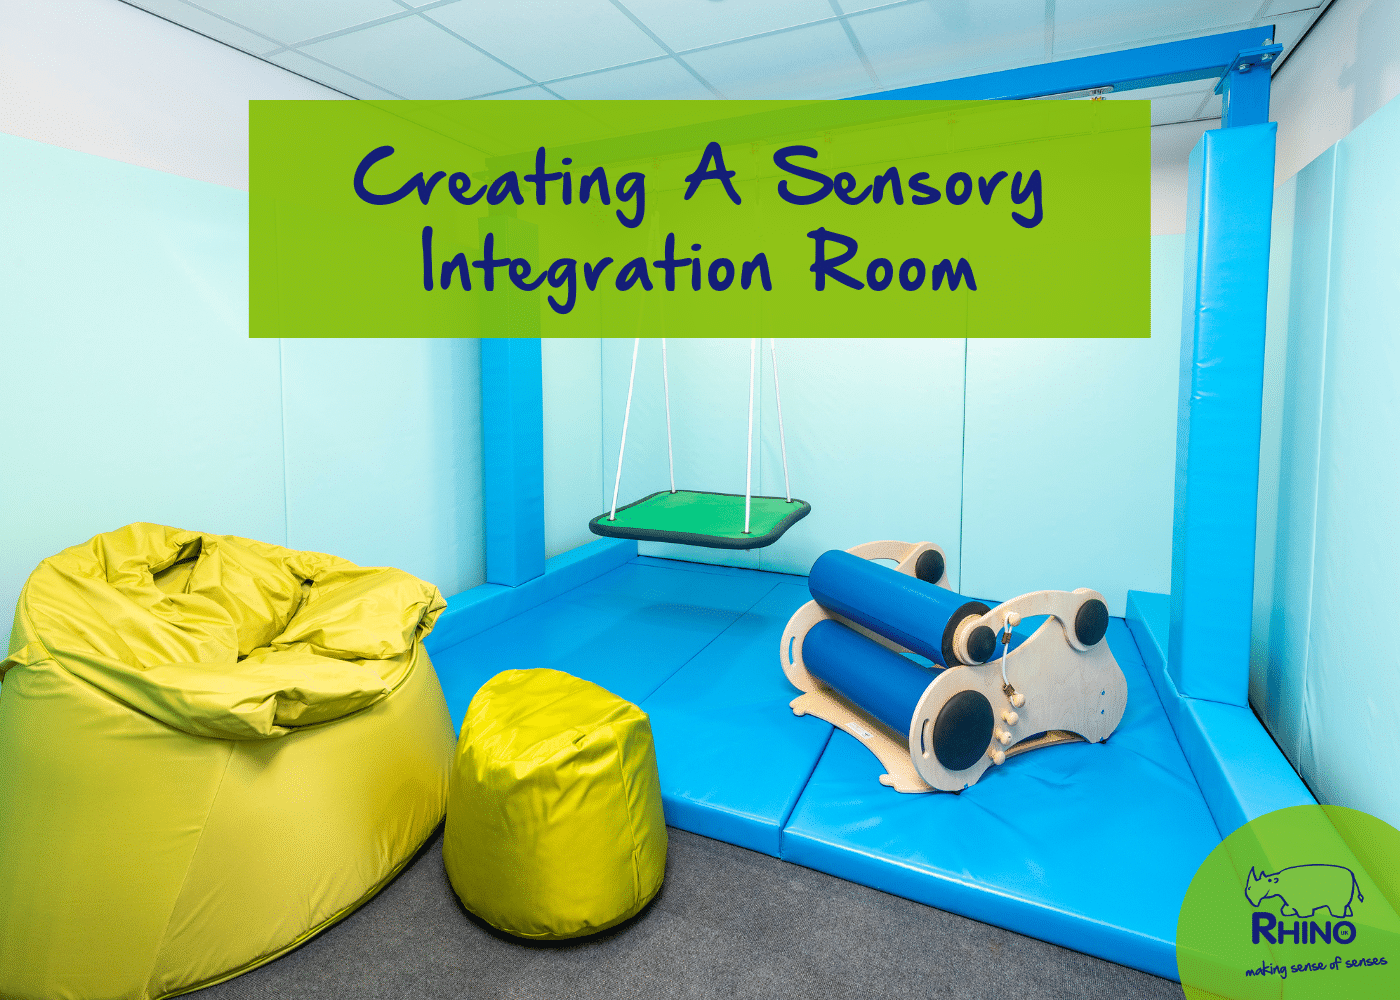
The activities themselves break into categories based on which sensory system they target. Vestibular work involves movement through space—swings, spinning, rocking. Proprioceptive input comes from resistance and compression, like weighted blankets, wall pushes, or carrying heavy objects. Tactile activities range from brush-and-press protocols to textured bins. Auditory and visual components round out the mix but are usually secondary unless there's a specific processing deficit. A typical session runs about forty-five minutes. I spend the first ten minutes doing a quick baseline observation, noting eye contact, frustration tolerance, and gross motor control. Then I rotate through three to four stations, each running eight to ten minutes. The last five to ten minutes are always a calm-down period with no new input. That buffer matters more than people realize. I had a kid last year who was registered for a full sensory diet program but his parents were also giving him high-intensity vestibular activities at home every single day. He came in deregulated before we even started. His therapist wanted to increase the swing intensity. I told them to cut everything back for two weeks and just do the floor-based proprioceptive work. He stabilized in eleven days. Pushing harder on an already fried system is the most common error I've seen, and it's almost never addressed because people assume more input equals more progress. It doesn't. The nervous system needs recovery windows as much as it needs stimulation.
Setting Up a Practical Protocol
Start by identifying the dominant sensory modulation pattern. Is the person under-responsive, meaning they seek input constantly and seem glued to movement or touch? Or over-responsive, where normal sensations feel overwhelming and they avoid certain textures, sounds, or movements? The intervention looks completely different for each. For under-responsivity, you use alerting input. Deeper pressure, faster movement, louder auditory cues. For over-responsivity, you use organizing input instead. Slower rhythmic movement, consistent deep pressure, and you avoid sudden changes in the environment. Mixing these up makes things worse. I've watched people do this because they found an activity online that worked for one child and assumed it would work across the board. Track your data. Write down what you introduced, how long, what the person's reaction was on a scale of one to five, and whether they recovered within ten minutes. Without that record, you're just guessing. My own tracking sheets show that about sixty percent of the activities I try on a new person either need modification or complete replacement within the first two weeks. That's normal. It's part of the process.
Get the Full Details
Common Mistakes That Derail Progress
Duration is the biggest problem. People run activities for fifteen or twenty minutes straight thinking they're building endurance. What they're actually doing is pushing past the regulation window into either shutdown or escalation. Eight to ten minutes per activity station is the sweet spot for most school-age children. Toddlers need five. Teens can handle up to twelve if the intensity is appropriate. Another issue is skipping the transition phase. Going from high-energy swinging directly into seated work is a setup for meltdown. The nervous system doesn't switch gears that fast. You need a three to five minute bridging activity with moderate input, something like pushing a weighted cart across the room or squeezing a therapy putty ball. Environmental control gets overlooked too. If the room has fluorescent lights buzzing, a window with direct sunlight, and background conversation from the hallway, none of your carefully planned activities will land correctly. The sensory load from the environment eats into the person's capacity before you even start. Turn off the lights if you can. Close the door. Use noise-canceling headphones as a preemptive measure, not a last resort.
When This Approach Won't Work
Sensory Integration Therapy Activities won't solve every behavioral or attention issue. If a child has uncorrected vision problems, hearing loss, or an underlying medical condition affecting motor planning, no amount of swing time or weighted vests is going to fix the root cause. You need to rule those out first. Occupational therapists usually handle the referral chain, but if you're working at home without that support, pay attention to red flags and get a professional evaluation before spending months on the wrong intervention. There's also a point where pure sensory work hits diminishing returns. After about six to eight weeks of consistent daily practice, progress slows significantly. That's when you layer in cognitive and behavioral strategies alongside the sensory component. Social stories, visual schedules, and self-monitoring checklists complement the foundation the sensory work builds. Standing on that alone indefinitely isn't optimal. The best outcomes I've seen come from combining structured sensory protocols with clear communication between whoever is implementing the activities and the actual therapists. Without that loop, you end up doing the same thing wrong for three months and wondering why nothing changed. Track everything. Share it. Adjust based on what the data tells you, not what you hope is happening.


