So You Need to Sequence Activities for a Patient
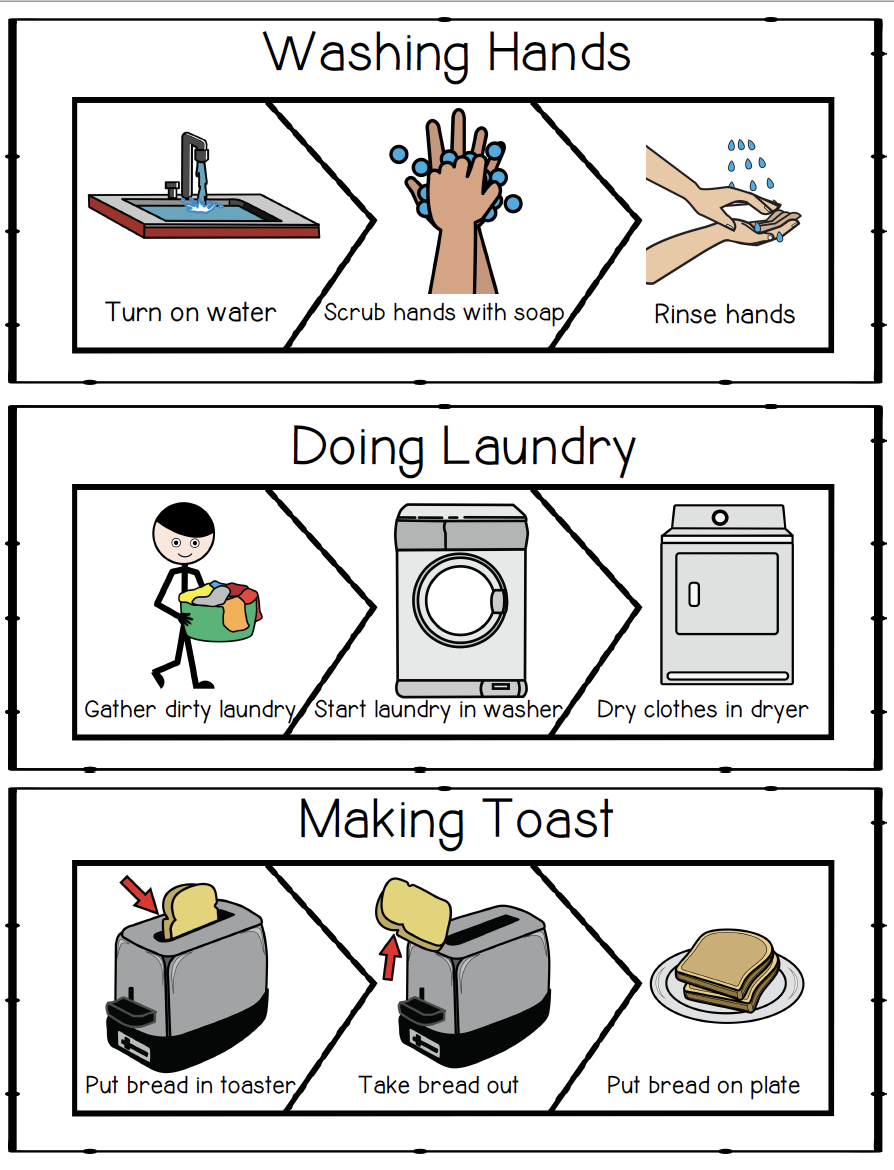
The usual approach starts with breaking a task into its component steps. You pick something like making a cup of tea or getting dressed, write out each step on a card, and hand them to the patient. They arrange the cards in order. It works fine for some people. It doesn't work for others, and you will figure that out pretty quickly. Sequencing Activities Occupational Therapy is built on the idea that many clients struggle not because they can't perform individual motor actions, but because the executive function needed to hold a chain of steps in working memory is impaired. That shows up a lot after TBI, with ADHD, or in elderly patients showing early dementia. The intervention isn't fancy. It's methodical repetition with fading support.
Sequencing Activities Occupational Therapy
Let me walk through how I actually do this in a session, because the textbook version leaves out the bits that eat your time. Start with task analysis. Pick one functional daily activity. Something the person actually needs to do, not something you think would be good practice. I once spent forty-five minutes reducing "making breakfast" into twelve discrete steps for a stroke patient. Turned out he could feed himself with a spoon but couldn't navigate the spatial sequence from fridge to counter to pan. The exercise was useless because it didn't match his actual deficit. We switched to "opening the fridge and retrieving one item" as the sequenced task. Progress was immediate. Use forward chaining when the patient has difficulty initiating the first step but can manage later ones once they start. You do step one, have them do step two, guide through the rest. Each session, they take on one more step from the beginning. This is the version most people reach for first and it's usually the right call for patients with low frustration tolerance because they experience success early in the chain every time.
Use backward chaining when the patient can follow directions but abandons the task before finishing it. You complete every step except the last one and have them perform the final step. They get the natural reward immediately. Swap in the next-to-last step the following session. This is counter-intuitive for new OTs who want the patient to feel like they did the whole thing, but the data on task completion rates favors backward chaining for people with executive dysfunction. Here's the part nobody tells you in grad school: the sequencing material matters less than the prompting hierarchy. Visual cards, written lists, verbal cues, physical guidance — you need to move down the hierarchy only when the client stalls, not on a fixed schedule. I keep a simple decision tree taped to my desk. Visual model first. If they look at it and don't start, gesture to the first card. If they touch it but don't place it, use an open-handed physical prompt, not a hand-over-hand. Save hand-over-hand for the rare cases where they freeze completely. It destroys carryover if you use it too early because they learn to wait for your touch rather than retrieving the sequence from their own memory. I ran into a specific edge case last year with a 68-year-old post-stroke client who had severe ideational apraxia. She could name every step of making tea, could even pantomime each action correctly in isolation, but when asked to sequence them she'd start with the kettle, then pick up the empty mug and hold it under the tap. The problem wasn't sequencing. It was that her understanding of the goal state of each step had degraded. Writing down the steps didn't help. What worked was using a video model — I recorded her previous successful attempt at a simpler task, she watched it for three minutes before each session, and the visual-spatial imprint of the correct end-state for each step re-anchored her performance. It took eight sessions before she could chain "put water in kettle" to "turn on kettle" without prompting. Without the video she never got there.
Get the Full Details

Another nuance: temporal shading. This is where you gradually increase the time interval between steps, training the client to hold each step in working memory before moving forward. I use a kitchen timer set to 10 seconds between steps for the first session, then 15, then 20. Most clients can manage the 10-second gap by session two. If they can't, they need more work on the individual steps before you increase the timing, not less. Pushing the interval before the steps are solid just creates failure repetition, and that's where motivation erodes. For visual sequence supports, I default to photo-based cards rather than line drawings. Photos of the actual objects in the person's own home reduce the abstraction load. A line drawing of a toothbrush requires a cognitive translation step that a photo of their own toothbrush on their own sink doesn't. I take the photos with my phone, print them on cardstock, laminate them, and put a small hook at the bottom so they can hang each card on a ribbon string after completing it. The physical act of moving the card from left to right while talking through the step reinforces the temporal order in a way that just pointing at a page doesn't. There are real limitations here. Sequencing interventions have very weak transfer effects to untrained tasks. A patient who learns to sequence a dressing routine typically cannot apply that skill to cooking without significant additional training. Don't promise families that learning to sequence one activity will generalize across the board. It won't. You're building a specific procedural pathway, not a general executive function superpower. The research on transfer is clear about this and clinics that sell sequencing as a magic bullet for cognitive rehabilitation are overstating their outcomes.
Another bottleneck: these interventions are time-intensive. A single task analysis with a moderate-severity client takes about 45 to 60 minutes to develop properly. Maintenance sessions run 20 to 30 minutes each. If you're seeing more than four clients per day and trying to do sequencing work alongside everything else, you'll either rush the analysis or drop it entirely. I batch my sequencing cases — two per day max — and schedule them in the morning when my cognitive bandwidth is highest. The quality of the task analysis directly predicts how fast the client progresses, so protecting that process matters more than throughput. If sequencing work isn't moving after six to eight sessions with consistent methodology, you should reassess whether the primary barrier is actually sequencing or something else — working memory capacity, motor planning, motivation, or a sensory regulation issue masquerading as a cognitive one. I've lost count of the number of times I saw a "sequencing problem" turn out to be undiagnosed anxiety causing task avoidance. The client wasn't failing to sequence. They were selectively freezing at step three because step three involved a physical activity they found humiliating or frightening. The workaround was stopping the sequencing protocol entirely and addressing the avoidance behavior first through graded exposure. For clients who need something more structured than cards, there are commercially available sequencing apps and software packages. I don't recommend them as a replacement for hands-on work with functional tasks, but they can serve as supplemental practice in the home setting. The problem is that digital sequencing games almost always use abstract ordering — color sequences, number sequences, animal ordering — which has almost zero ecological validity compared to sequencing an actual daily routine. They're fine for warm-ups. They're not treatment.
The bottom line is that sequencing work in OT is mechanical, repetitive, and occasionally frustrating, but it produces measurable gains when you match the chaining method to the client's actual profile and don't mistake a non-sequencing problem for a sequencing problem. Most failures in this area come from misdiagnosis of the barrier, not from the technique itself.