What actually happens when you assess elderly care needs
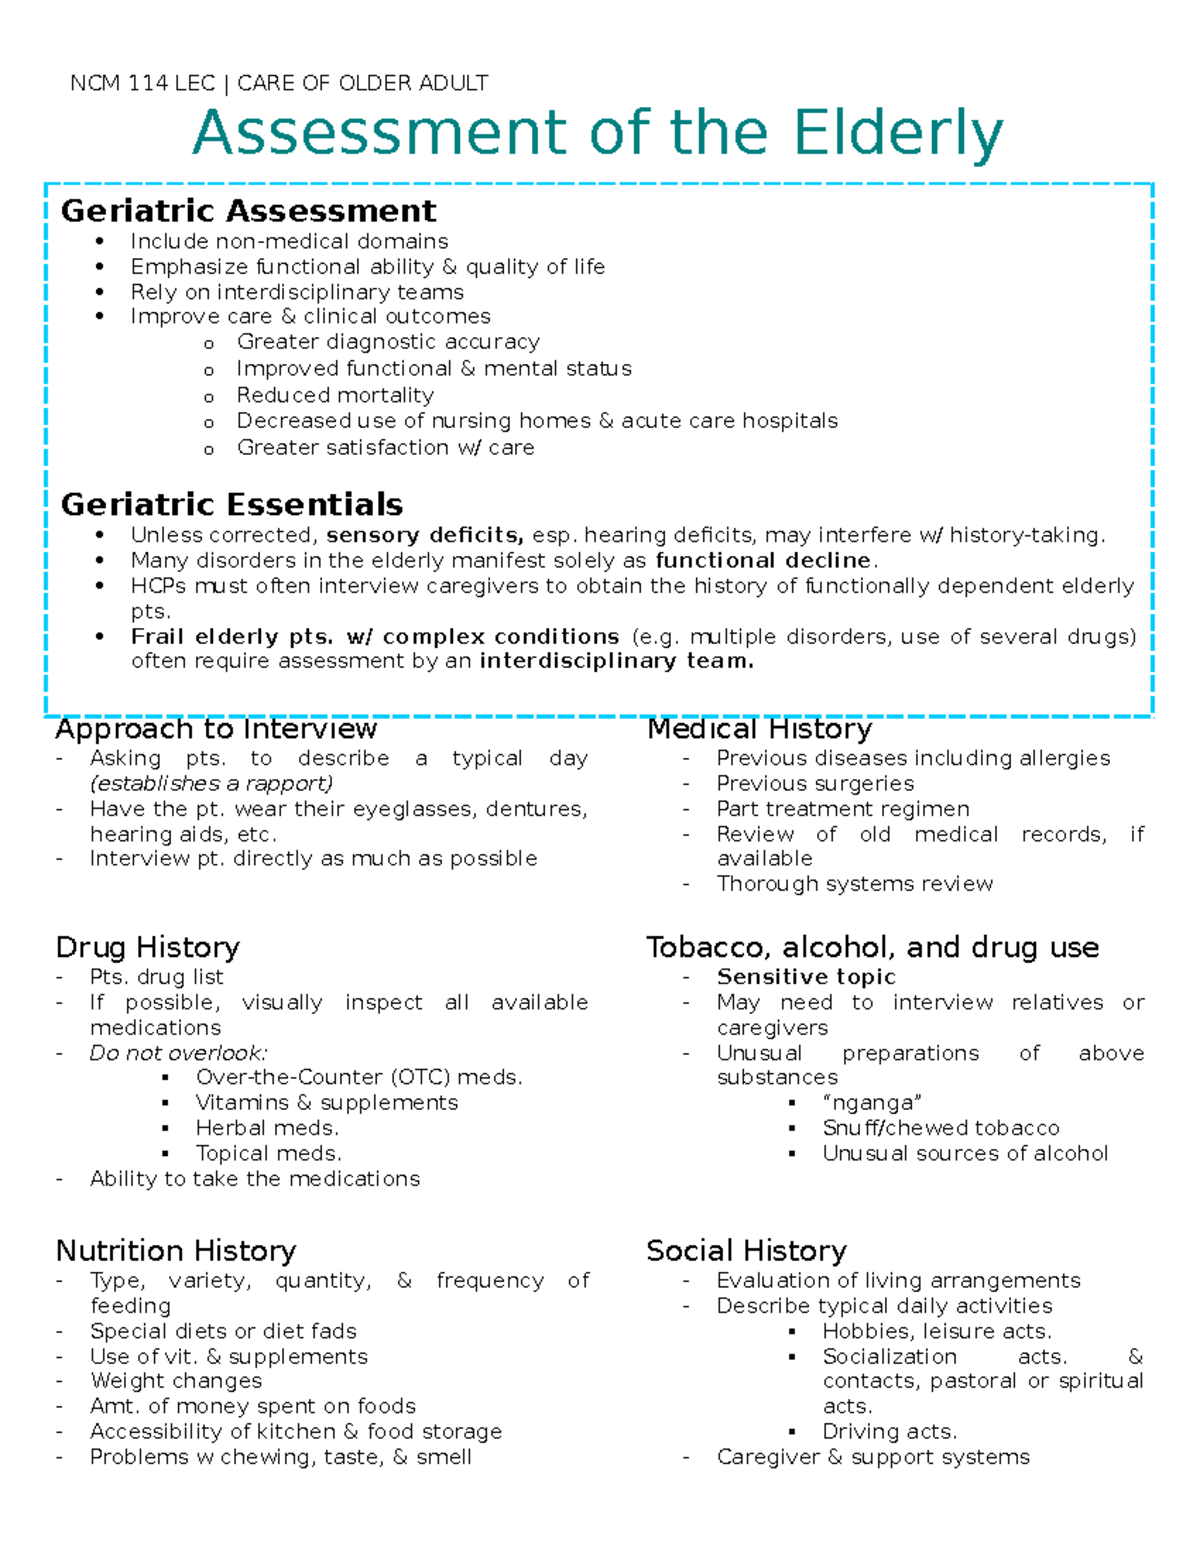
The first thing I need to say is that Services Elderly Care Assessment is not a single document you fill out and hand to a social worker. It is a process that spans several weeks, multiple site visits, and usually at least three different stakeholders arguing about what the data means. The word "assessment" implies a moment of clarity. In practice it is more like slowly narrowing a circle of uncertainty while everyone involved has a different idea of where the boundary should be. I have watched competent assessors produce immaculate paperwork and then watch the care plan collapse within forty-eight hours. The failure point is almost never the clinical scoring. It is the transition between the assessment phase and the services delivery phase. Here is the edge case that burned me once: an elderly client with mild cognitive impairment passed a standard cognition screen because they had a daughter sitting next to them during the interview, prompting correct answers through environmental cues. The assessment scored them as low-risk. Two weeks later they wandered into a neighbour's garden at 2am because no one had actually observed them navigating their own home unaided. The workaround I use now is simple but unpleasant. I stop allowing family members to sit in during the functional observation portion unless the client specifically requests their presence. I also build a mandatory independent home visit into every assessment, regardless of what the paperwork says. That home visit takes ninety minutes I would rather not spend, but it catches the gap between what people report and what they actually do.
The methodology most people skip
Standard frameworks like the Minimum Data Set or the CGA tool give you structure, but they do not teach you how to spot the discrepancy between self-report and observable behaviour. The actual skill lives in the triangulation method: compare what the client says, what the caregiver says, what the records show, and what you see when nobody is watching. When all four data points align you can proceed. When they diverge, you do not resolve the divergence on the spot. You flag it, you document which source conflicts with which other source, and you extend the assessment window. I have found that the most useful metric in any Services Elderly Care Assessment is not the raw score. It is the velocity of decline over the preceding six months. A client who scored moderately impaired last month but was independent two months ago needs a completely different intervention than a client who has been at that same impairment level for three years. The static snapshot misleads everyone. The trajectory tells you what is actually happening.
Tools that matter and tools that do not
Barthel Index for ADLs. Lawton IADL scale. MMSE or MoCA for cognition. Fall risk assessment with a timed up-and-go test. These are table stakes. What most assessors forget is the medication reconciliation piece. I once identified a polypharmacy problem that was causing gait instability simply by having the client bring every bottle to the appointment. The assessment tool did not flag this. A twenty-minute conversation with the pharmacy label open did. Electronic health record integration is supposed to make this easier. In practice it adds another layer of friction because most care assessment platforms do not talk to each other, and the data export formats are inconsistent across providers. You end up copying information from one system to another manually, which introduces transcription errors and takes additional time. The workaround is to build a standardised paper backup form that captures everything in one place, then enter it into the electronic system after the assessment is complete rather than trying to do it live.
Get the Full Details

When the assessment process breaks down completely
There are scenarios where Services Elderly Care Assessment produces unreliable results no matter how careful you are. Severe dementia in the advanced stage. Active substance misuse that the client is not disclosing. Acute psychiatric episodes that make consistent testing impossible. Homeless or severely socially isolated clients who have no informant source. In these cases the assessment score you generate is essentially a best guess with confidence intervals you cannot quantify. The honest move is to state that uncertainty explicitly in the documentation rather than pretending the number means more than it does. An alternative approach in these situations is to shift from a static assessment model to a repeated-measures monitoring model. Instead of producing one definitive score, you schedule brief check-ins at two-week intervals and track directional trends. The data is messier but it is more reliable than a single high-stakes evaluation performed under adverse conditions. This takes more clock hours but produces better decisions because you are observing recovery or decline in real time rather than inferring it from a snapshot.
The bureaucratic trap most people do not see coming
Assessment tools are often designed for funding eligibility rather than clinical utility. The thresholds that determine whether a client qualifies for in-home support or residential placement are arbitrary constructs created by budget committees, not clinical reality. You will encounter clients whose scores sit just below a funding threshold who are actually at higher risk than clients who barely cross it. The system rewards people who can perform well on assessment days and penalises people whose conditions fluctuate. This is not a bug in the process. It is the feature. What I do about this is document the limitation directly in the referral packet. I note the specific score, the threshold it fell short of, and the clinical rationale for why the number does not reflect actual risk. This does not always change the outcome, but it creates a paper trail that protects everyone when the client's condition deteriorates and someone asks why the assessment missed it.
Practical timeline for a standard assessment cycle
A complete Services Elderly Care Assessment cycle runs approximately three to four weeks from initial referral to final care plan. Week one covers intake, records review, and the primary clinical interview. Week two includes the home observation and collateral informant conversations. Week three is documentation and interprofessional consultation. Week four delivers the care plan and transitions to implementation. Rushing this timeline produces incomplete assessments. Taking longer than five weeks usually triggers re-referral requirements or funding expiration depending on the jurisdiction. The bottleneck is almost always week two. Home visits are difficult to schedule because both the assessor and the client need availability windows that overlap, and cancellations cascade. I keep a buffer of two alternative dates in every calendar and confirm the home visit seventy-two hours before the scheduled time rather than waiting until the morning of. This simple habit reduced my missed appointment rate from roughly eighteen percent to under four percent over a fourteen-month period.

What the paperwork actually requires versus what it requires you to believe
The official forms will suggest that a single trained professional can complete a comprehensive assessment in ninety minutes. This is administratively convenient and clinically inaccurate. A thorough assessment with home observation, medication review, informant interviews, and cognitive screening typically requires two and a half to three hours of direct contact time spread across at least two visits. Anything shorter is a screening, not an assessment. Calling it an assessment creates liability exposure when the findings later cause harm. I separate my work into two distinct deliverables: a screening summary for rapid triage and a full assessment report for care planning. The screening takes forty-five minutes and uses abbreviated tools. The full assessment follows the complete protocol. Both documents exist in the same file but serve different purposes. This distinction saves time because not every referral requires the full cycle, and it protects accuracy because the screening results are not mistakenly treated as definitive by subsequent providers.