Understanding the Sesamoid Bones: What They Actually Are
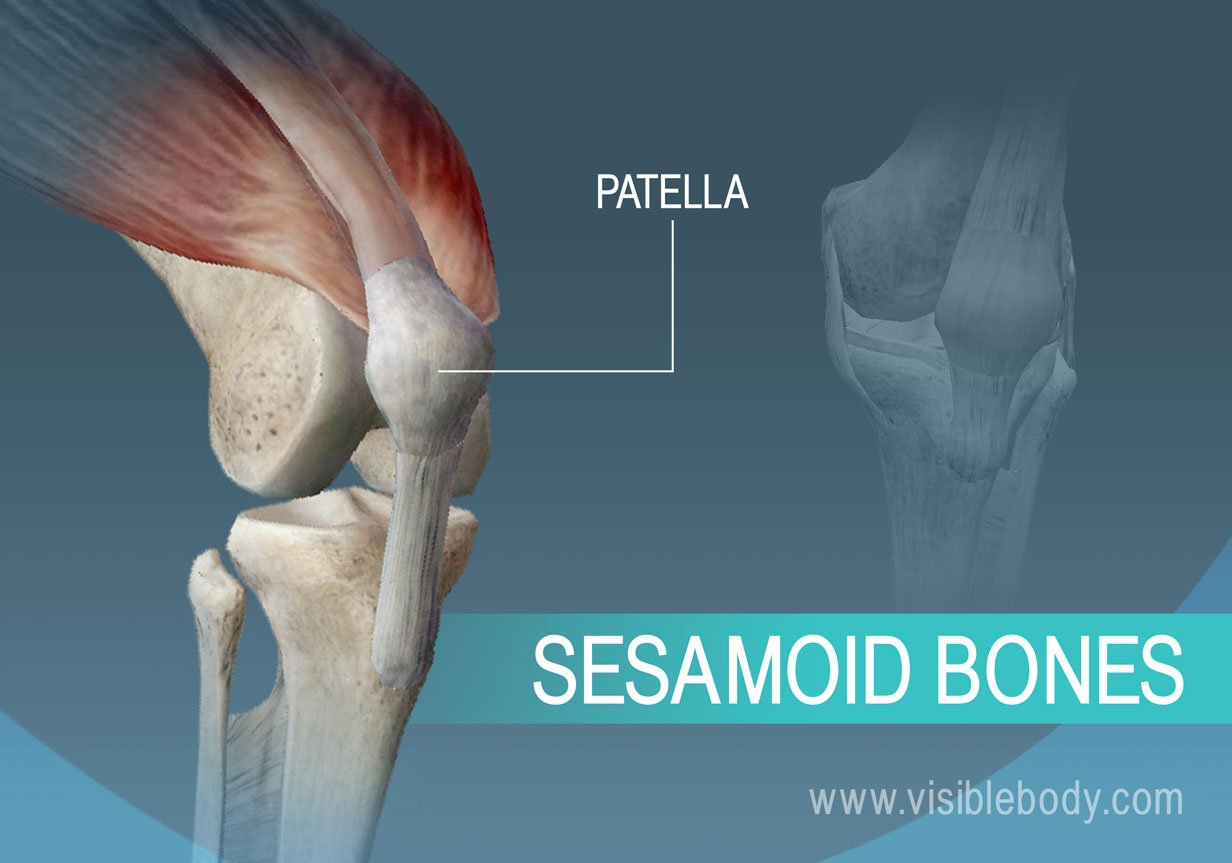
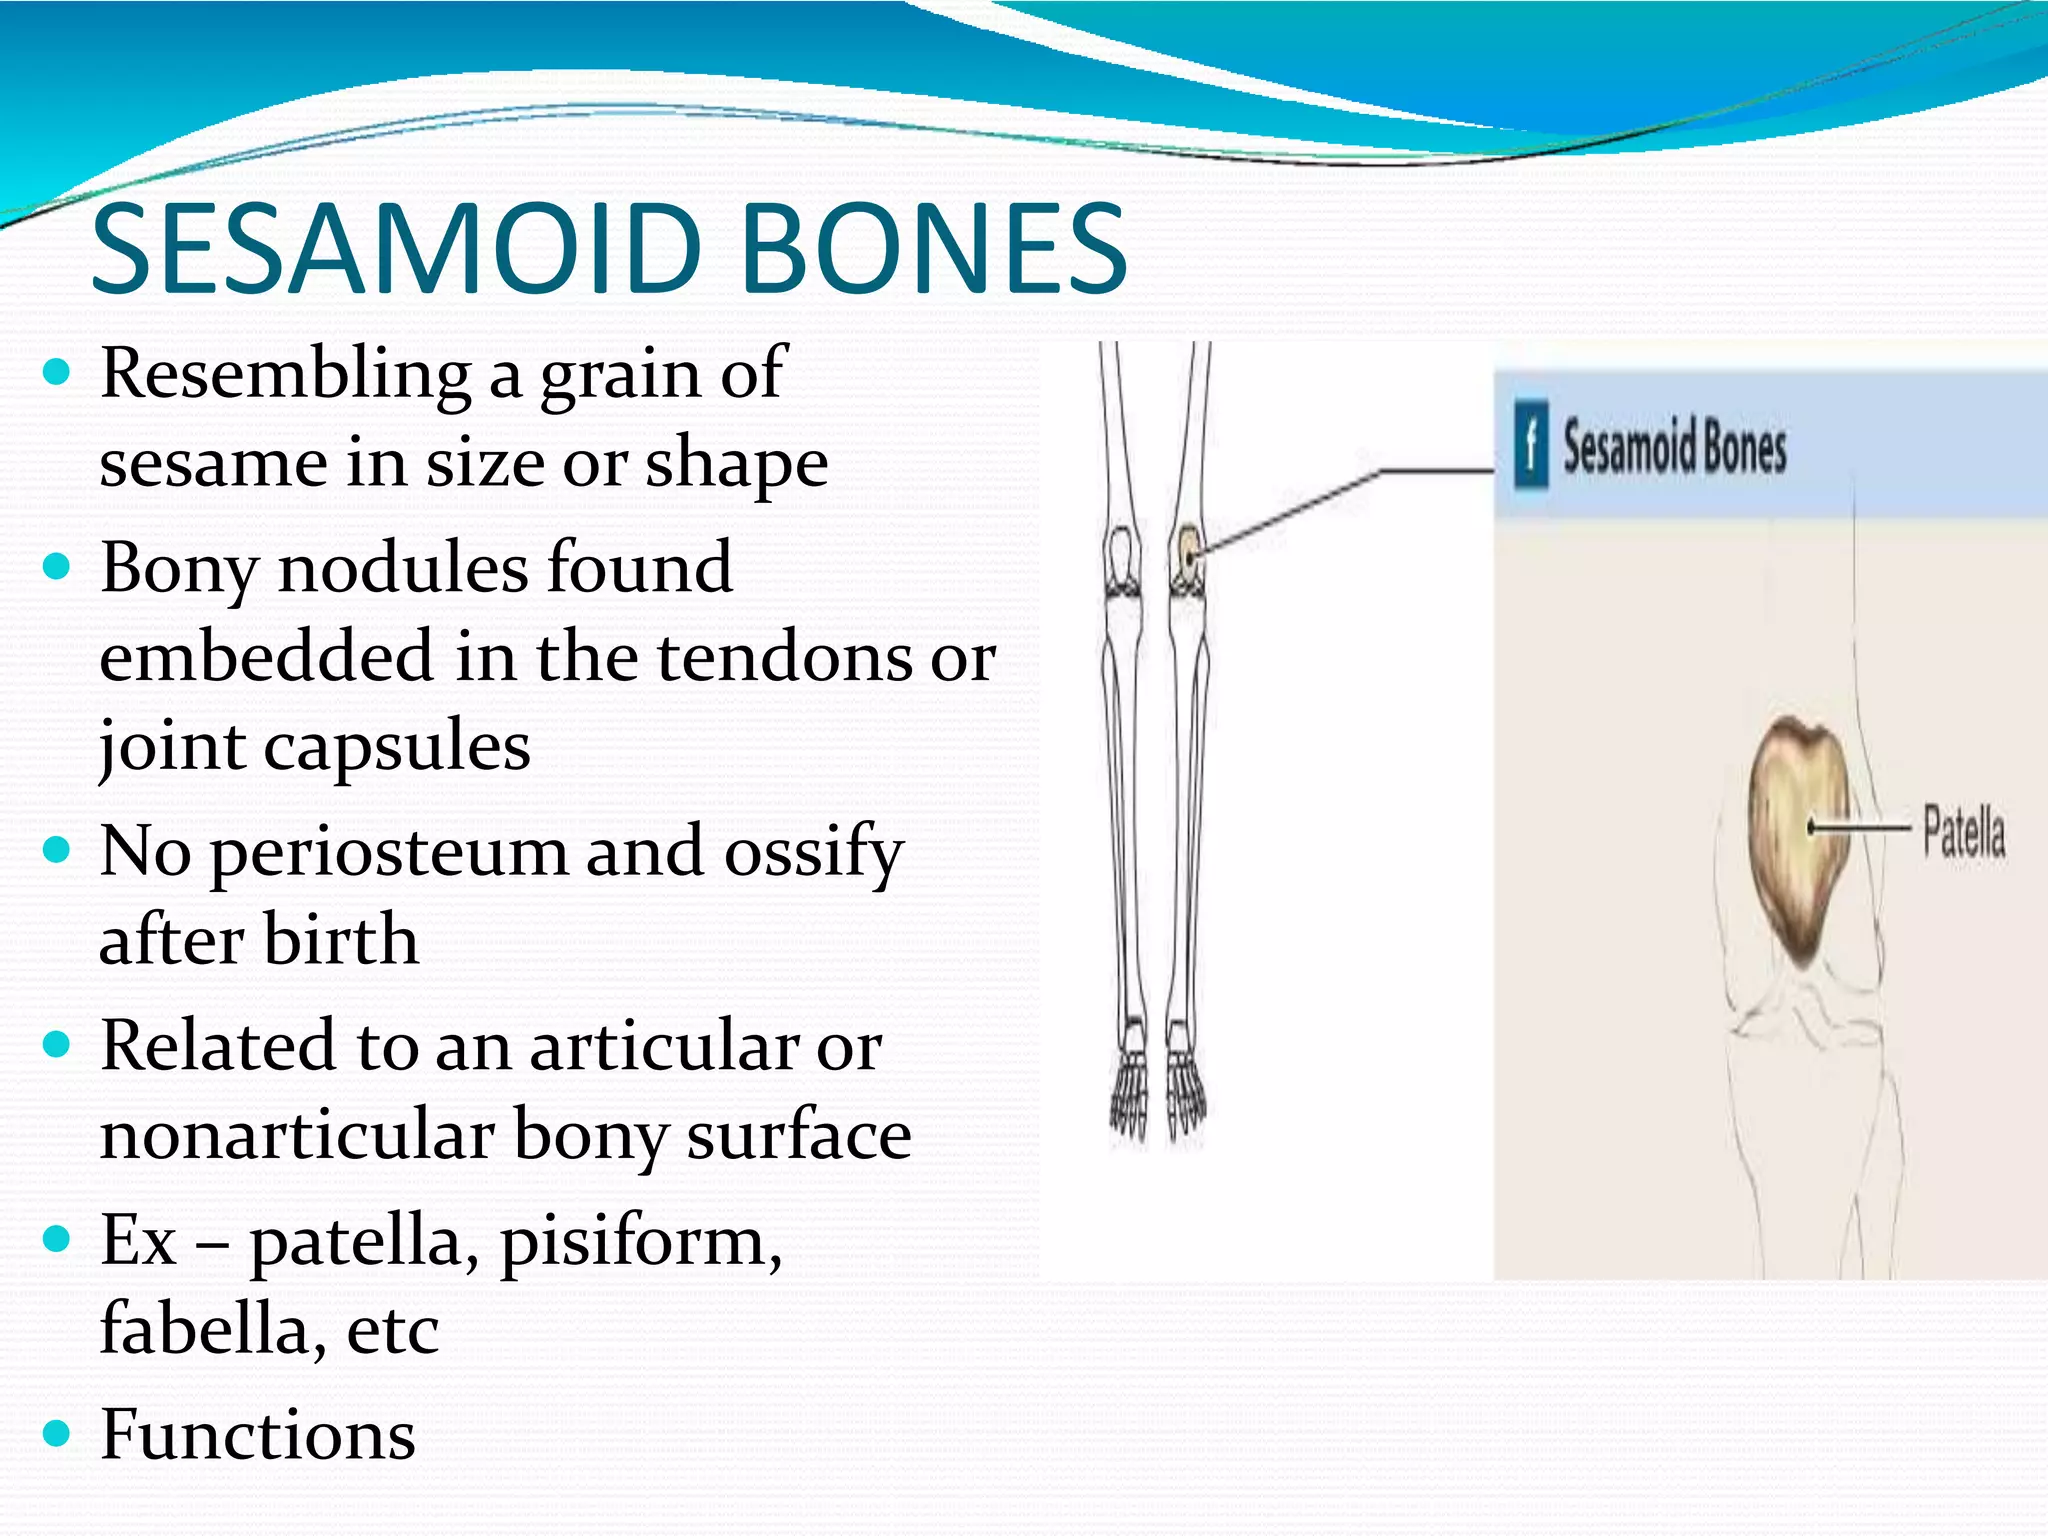
The sesamoid bones are small, round bones embedded within tendons. Most people have them under the big toe on both feet. They're not part of the standard 206-bone count you learn in intro anatomy because they vary from person to person. Some folks have extra ones, some don't have any at all. The primary pair sits inside the flexor hallucis brevis tendon at the metatarsophalangeal joint of the hallux. Two bones, usually, on each side of the tendon. They act as a pulley system, redirecting the force of that tendon and giving it better mechanical advantage when you push off during walking or running. I ran into a patient last year who came in with persistent plantar forefoot pain that wasn't responding to standard treatment. X-rays showed a bipartite right sesamoid with a clear synchondrosis between the two ossicles. The left side looked completely normal. We spent weeks trying conservative measures first — orthotics, taping, activity modification, even a corticosteroid injection near the area, which felt risky but gave us a diagnostic clue. When the pain didn't budge after six weeks, we went to a CT scan to map the exact fibrocartilaginous junction. That's when everything changed. We confirmed it was a symptomatic bipartite sesamoid, not the usual sesamoiditis. The distinction matters because the treatment path is completely different. Surgery to remove a bipartite fragment carries a real risk of iatrogenic hallux valgus if you're not careful about which portion you take out. In that case, we referenced the medial one, preserving the lateral weight-bearing portion. Recovery took longer than a standard sesamoidectomy would have, but the functional outcome was solid. He was back to light jogging around four months in. This is where most people get confused about Sesamoid Bone Definition Anatomy. The textbook says two bones per foot under the first metatarsal head. Reality is messier. Roughly 3% of the population has a bipartite sesamoid. Another small percentage has a tripartite configuration or even an isolated os suprascapulare variant, though that's more relevant to shoulder anatomy. The medial sesamoid is typically larger and bears more load than the lateral one. You can see this clearly on a weight-bearing axial radiograph. The medial sesamoid sits closer to the midline and has a broader articular surface against the metatarsal head.
On imaging, there's a specific sign you need to watch for. If you see a sesamoid with smooth, corticated margins at the fracture line, it's almost certainly a bipartite bone that's been there since development. A true acute fracture will have sharp, irregular edges without any sclerosis. Mistaking a bipartite sesamoid for a fracture is one of the most common errors I see in emergency radiology reports. It happens constantly. The clinical context is what separates them. A bipartite sesamoid usually causes pain only when directly manipulated or under extreme load. An acute fracture typically follows a specific traumatic event — a hard landing, a direct blow, or a sudden forceful plantarflexion of the big toe. The blood supply to the sesamoids is another detail that gets glossed over. They receive dual supply from branches of the first plantar arterial arch and the medial plantar artery. This matters clinically because both the medial and lateral sesamoids are at risk for avascular necrosis, especially after surgical intervention. When I worked through orthopedic rotations, we saw two cases of sesamoid AVN within a single month, both post-surgical. One was after a simple excision of what was thought to be a fragmented sesamoid. The other happened after aggressive debridement of chronic sesamoiditis. The takeaway here is that sesamoid preservation should always be the priority whenever possible. Excision is a last resort, not a first line of treatment. There's also the question of sesamoid position relative to the first metatarsal head. On a lateral weight-bearing X-ray, you can estimate how much the sesamoids are involved in load transmission. If more than 75% of the sesamoid's diameter overlaps the metatarsal head contour, that foot is under significantly higher sesamoid load. This is called a hypermobile first ray situation when combined with metatarsus primus varus. It's a common finding in patients with recurrent sesamoid pain who've failed conservative care. The workaround I use isn't fancy — it's just a stiff-soled shoe with a metatarsal pad positioned proximal to the sesamoids. Not directly under them. Proximal. Putting the pad under the painful area just increases pressure on an already compressed structure. Moving the load forward shifts it off the sesamoids entirely. This alone resolved a significant chunk of the cases I've managed over the years without needing to escalate to surgery.
The adductor hallucis muscle also deserves attention here. Its oblique head inserts directly onto the lateral sesamoid, and its transverse head forms the deep transverse metatarsal ligament complex that connects all the sesamoids together. Tightness or hypertrophy in the adductor hallucis can contribute to lateral sesamoid compression and pain that mimics a fracture. I've had patients who improved dramatically after targeted myofascial release of that muscle, something most general practitioners wouldn't consider as a first-line intervention. The reason it works is simple biomechanics — reducing lateral pull on the sesamoid complex decreases the compressive force between the lateral sesamoid and the metatarsal head. If you're looking for reference material, the most useful atlas for sesamoid anatomy is the one by Clanton and Potter, published in the American Journal of Sports Medicine. It includes detailed cadaveric dissections and radiographic correlation that goes beyond what standard anatomy textbooks cover. There's also a freely available Open Anatomy resource from Visible Body that has 3D models of the forefoot with sesamoid labeling, which is decent for visualization but lacks the clinical depth you'd get from the peer-reviewed literature. The main limitation of current imaging for sesamoid pathology is that plain radiographs simply cannot rule out early stress reactions or bone marrow edema. MRI is the gold standard when you need definitive answers, but it's expensive and not always accessible. A DEXA scan can show you bone mineral density variations between the medial and lateral sesamoids, which sometimes correlates with chronic overloading patterns. This isn't routine practice, but in stubborn cases where the diagnosis remains unclear, it provides data that changes management decisions. I've had patients who avoided unnecessary surgery because a DEXA scan revealed asymmetrical density suggesting a chronic stress reaction rather than a structural defect.
Get the Full Details