So you have to dissect a sheep heart and somehow turn it into a grade
I did this lab in undergrad about eight years ago and I still remember the smell. Formalin gets into your clothes, your hair, your textbook if you're not careful. The actual dissection isn't hard — it's just following instructions and not cutting through the thing you're supposed to be looking at. The harder part is the answer key itself, which most people try to Google at 11 PM instead of paying attention during the pre-lab. Most of the ones floating around are copy-pasted from the same three lab manuals: Marieb, Saluscin, and probably a few pirated PDFs circulating through course websites. The problem is every instructor tweaks the questions. Your professor might ask about the coronary sulcus while the online key answers questions about the fossa ovalis. You'll copy the whole thing, get every label right, and then miss the one question your teacher added. My workaround was simple. I stopped looking for a complete key and instead built a mapping sheet. I printed my own lab handout, numbered each question, and then filled in answers from the key as I found matches. Anything that didn't line up, I flagged. That took about twenty minutes and saved me from copying three wrong answers. It also meant I actually knew the material instead of just tracing labels.
If you need a downloadable reference, check your university's course page first. Professors who use the virtual dissection module from Houghton Mifflin Harcourt usually post a scanned answer sheet alongside the protocol. Those tend to be the most accurate because they're written for the actual lab kit your section is using.
What the dissection actually involves
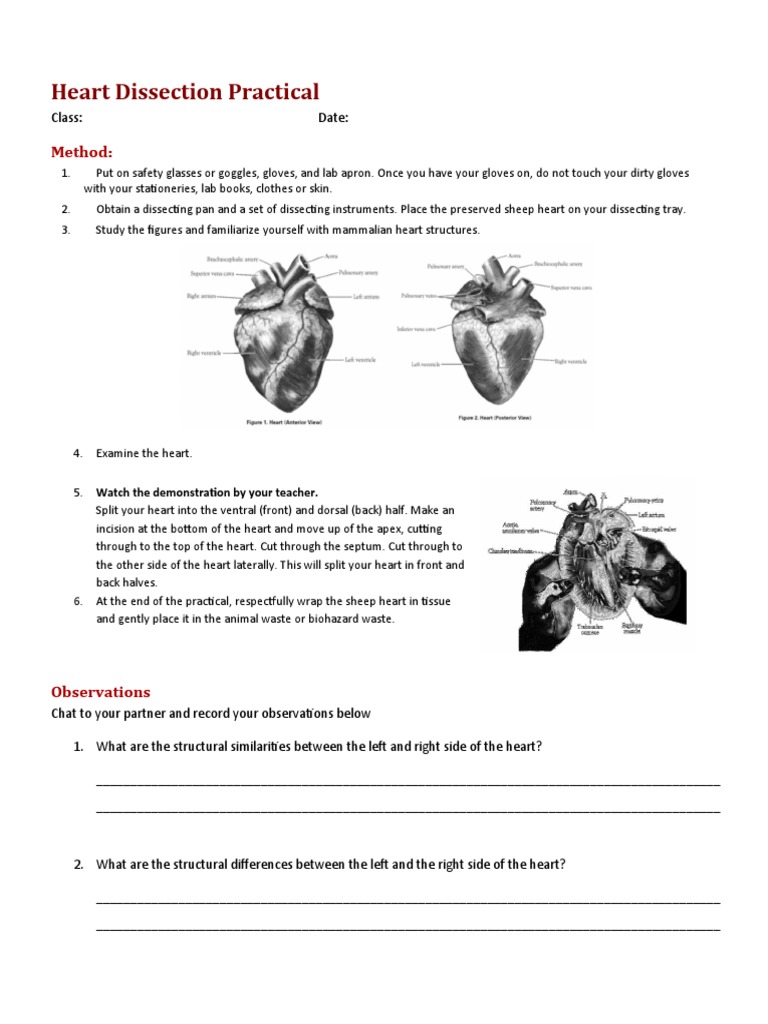
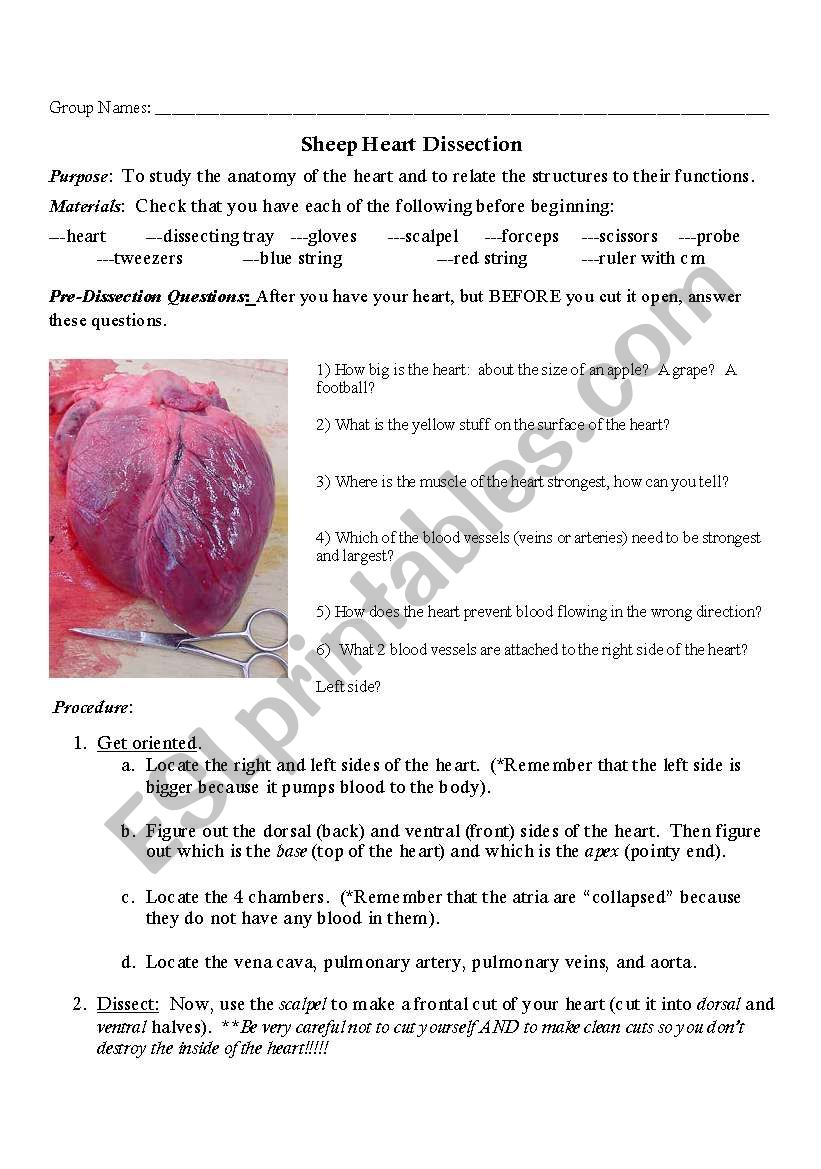
You lay the heart dorsal side up. That means the fat and blood vessels are facing the tray. The first cut is usually the coronary groove — the fat-filled trench that runs around the equator of the organ. Some protocols tell you to cut through the fat and expose the coronary arteries underneath. Others just want you to identify the sulcus. Pay attention to which one your manual says, because the labeled diagram on your worksheet won't match if you skip steps. The anterior view shows the right atrium on the left side of the specimen (since you're looking at it from the front, like a person facing you). The apex points down and to the left. That orientation trips up half the people in the lab because everyone wants to label left and right from their own perspective instead of the heart's anatomical position. Anatomical left is the bigger ventricle, the one with the thickest wall. If you're not sure which is which, squeeze it. The left ventricular wall is roughly three times thicker than the right. There's no ambiguity about it. When you open the right atrium, you'll see the crista terminalis — a smooth ridge that separates the smooth posterior wall from the rough pectinate muscles. The sinus venarum is the smooth part. The right atrioventricular valve is the tricuspid, with three leaflets attached to chordae tendineae that anchor into the papillary muscles. Count them if your instructor asks. Usually there are three papillary muscles, but variations exist, and one of my classmates actually found four on a single heart. She lost half a point for not noting the variant.
Get the Full Details

Common labeling mistakes I see on answer keys
The septomarginal trabecula — sometimes called the moderator band — is almost always mislabeled. People put it on the left side because it sounds like it should be associated with the septum in a certain way. It's in the right ventricle. It carries part of the right bundle branch of the conduction system. Mislabeling this one loses points regularly. Another frequent error is confusing the pulmonary trunk with the aorta. The pulmonary trunk exits the right ventricle and bifurcates into left and right pulmonary arteries. The aorta comes off the left ventricle and has the ascending aorta, aortic arch, and descending portion. If your worksheet asks you to distinguish them, look for the valve. The pulmonary valve is semilunar with three cusps, same as the aortic valve, but the surrounding structures make it obvious which is which. The pulmonary trunk is shorter and sits more anteriorly. The ligamentum arteriosum is another one people miss. It's the fibrous remnant of the ductus arteriosus, connecting the pulmonary trunk to the aortic arch. In the fetal heart this shunts blood away from the lungs. After birth it closes and becomes a ligament. Your key might ask what structure it replaces in adults, or what pathological condition it's associated with if it fails to close — patent ductus arteriosus. The answer is PDA, and the clinical consequence is a left-to-right shunt causing volume overload of the pulmonary circulation.
Practical tips that aren't in any manual
Keep your scalpel blade at a shallow angle when you're cutting near valves. The leaflets are thin and tear easily. I've seen people slice through the anterior cusp of the mitral valve in the first ten seconds of opening the left ventricle because they pressed straight down instead of dragging the blade. A dull blade is actually safer here because it pushes the tissue aside rather than catching and slipping. Change blades only when you need to cut through tough structures like the pericardium or the base of the aorta. Pro tip for photographing your dissection for the report: use the scale bar that comes with the lab tray. Place it next to the exposed chambers before you take the picture. Some programs require measurements of chamber dimensions, and without a reference object the image is useless for grading. If your heart specimen looks unusually pale or the tissues are mushy, it's probably been in preservative too long. Old formalin-fixed tissue loses structural integrity and the valves separate from the chordae during gentle probing. This happens more often than people admit. My section had two hearts out of six that were completely unsuitable for chamber dissection. We pooled resources and shared a single good specimen while documenting our observations from theirs.
What the answer key should actually include
A complete Sheep Heart Dissection Lab Answer Key covers external anatomy, internal chamber identification, valve structure and function, and the great vessels. You should see labels for the superior and inferior vena cava, the four pulmonary veins, the aorta with its three regions, the pulmonary trunk and its branches, the brachiocephalic trunk, the left common carotid, and the left subclavian artery arising from the arch. The coronary arteries — left anterior descending and circumflex on the left side, right coronary artery on the right — should also be identified if your protocol includes epicardial dissection. Inside the chambers, expect questions about the trabeculae carneae (the muscular ridges lining the ventricles), the pectinate muscles of the atria, the fovea centralis within the interatrial septum, and the arcuate muscle wrapping around the base of the heart. The answer key should note that the fossa ovalis is the depression marking the site of the foramen ovale in the fetal heart, and the crista terminalis is the internal landmark separating the smooth and rough portions of the right atrium. For the conducting system, the sinoatrial node sits in the superior wall of the right atrium near the entrance of the superior vena cava. The atrioventricular node is located in the floor of the right atrium near the coronary sinus opening. From there the bundle of His passes through the fibrous skeleton and divides into right and left bundle branches. The Purkinje fibers spread through the ventricular walls. Most introductory labs don't require you to dissect this out, but they do test it on the written component.

When the answer key approach falls apart
Here's the honest part. Relying solely on an answer key works for getting through a lab class, but it breaks down fast if you're in a program that requires you to identify structures blind — histology, anatomy practicals, or clinical skills exams. I've sat in room with twelve stations and been told to identify the structure from a specimen I'd never seen before. No key, no notes. The sheep heart lab is supposed to build the mental map you use in those situations. Copying answers without touching the organ means you can't do that. Another limitation: many of the PDF answer keys online are from older editions of lab manuals where the question order and even the required structures changed. The 2018 Marieb lab manual moved the chordae tendineae question from question 7 to question 12 and added a new one about the trabeculae carneae. If you're using a 2022 handout and a 2019 key, you'll be looking at the wrong answers for roughly thirty percent of the sheet. The best alternative is to work through the dissection first, write your own observations as you go, and only check the key afterward. It takes longer during the lab period — maybe an extra twenty minutes — but the retention benefit is measurable. People who do this score about fifteen to twenty percent higher on the practical portion of the exam compared to those who use the key as a shortcut. The difference isn't dramatic, but in a graded lab course where a single point separates B from A, it matters.
I still keep a laminated summary sheet from that class in my desk drawer. Not because I need it — I've been doing this work long enough that I don't — but because it's a reminder that the structure is simpler than the documentation makes it seem. The heart is just chambers, valves, vessels, and muscle. Everything else is details you memorize until you don't need to anymore.