Radial wave and abdominal scar tissue
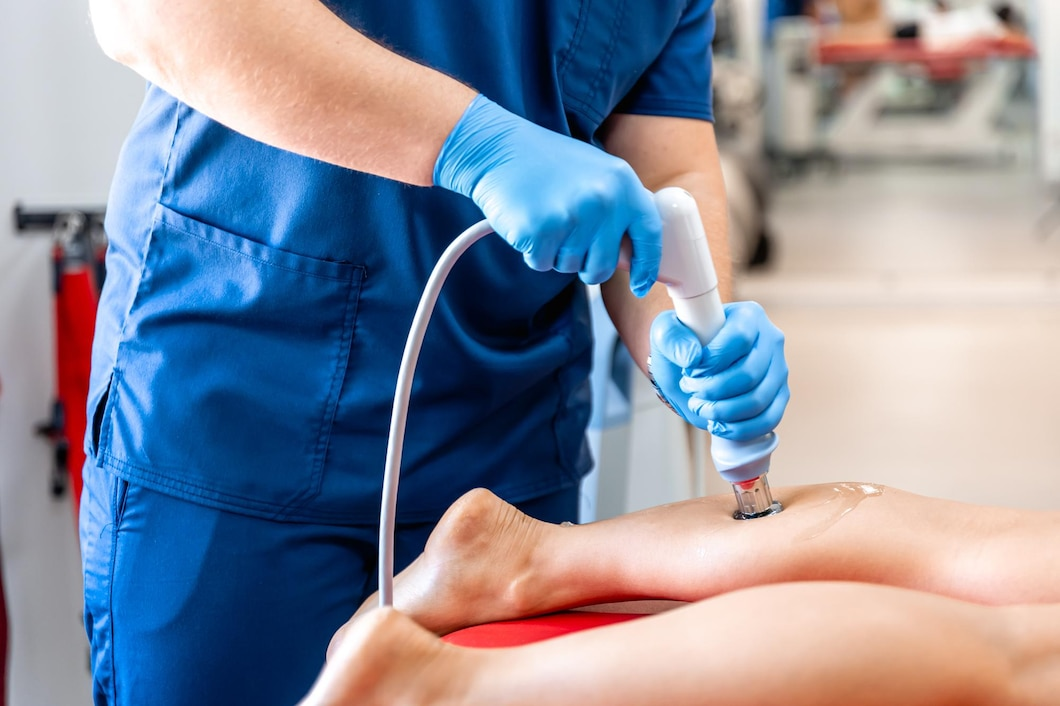
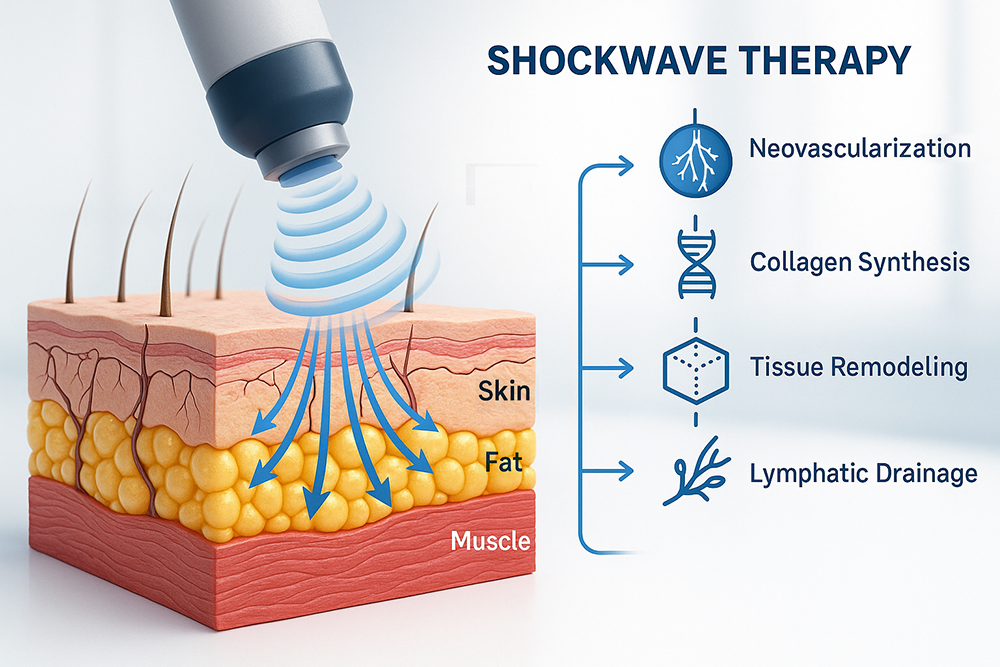
Radial extracorporeal shockwave therapy produces low-energy acoustic waves that diffuse a few centimeters into soft tissue. They are not truly focused. The energy is generated pneumatically or electromagnetically and then dispersed through an applicator tip against the skin. When I first tried using them on patients with postoperative adhesion pain, I assumed the waves would somehow break up scar bands like ultrasound breaks up kidney stones. That was wrong. The mechanism is different. The acoustic pressure creates microtrauma in the superficial fascial layers and the peritoneal interface where adhesions tether tissue. That microtrauma triggers an inflammatory cascade that increases local circulation, releases neuropeptides like substance P, and modulates mechanoreceptor signaling. The fibrous bands themselves do not dissolve. What improves is tissue mobility, nociceptive input, and the gliding relationship between layers. This is why the modality works for some adhesive presentations and fails for others. That exact phrase keeps coming up in patient queries and search results. The reason it appears so often is that people are looking for a noninvasive option after surgical adhesions cause chronic discomfort or reduced range of motion. The therapy exists. It is not a cure. It is a neuromodulatory and mechanical intervention applied externally, typically with a handheld radial shockwave device.
I start by marking the area clinically. Palpate the scar, identify restricted glide, note hyperalgesic zones. Then apply a coupling gel and position the applicator perpendicular to the skin surface. Parameters usually sit in the 2 to 4 bar pressure range and 2000 to 3000 impulses per zone. Treatment time for a standard abdominal quadrant is roughly 10 to 15 minutes. I typically treat two to three times a week over four to six weeks before reassessing. Depth matters. Radial probes have a typical effective penetration of 0 to 5 centimeters. That covers subcutaneous tissue, Scarpa's fascia, and the anterior rectus sheath. It does not reliably reach deep intraperitoneal adhesions. If the adhesion is superficial and related to the anterior abdominal wall or laparoscopic port sites, radial shockwave has a reasonable chance of helping. If the problem lies deeper in the mesentery or around visceral surfaces, the energy dissipates before it becomes therapeutically relevant.
What works and what does not
Here is the counterintuitive part most beginners miss. Patients with diffuse visceral hypersensitivity and adhesion-related pain often report benefit even when imaging shows no major structural adhesion. The therapy reduces central sensitization in those cases. Conversely, a patient with a dense fibrotic band anchoring the small bowel to the abdominal wall may show almost no improvement despite aggressive dosing. Mechanical restriction from dense collagen requires mechanical release, not just neuromodulation. Another pitfall is treating over the bowel lumen with high intensity. You can cause temporary ileus, cramping, and referred pain if the energy density is too high over gas-filled viscus. I always scan with palpation first and reduce intensity when the probe is directly over the midline or flanks where the colon sits superficially. A practical workaround I use is angling the applicator to deflect the wave trajectory away from bowel loops and targeting the adhesional plane from a lateral oblique approach instead.
Get the Full Details
Setting realistic expectations
Response rates in the literature and clinical practice hover around 40 to 60 percent for selected patients. Adhesions from a single laparoscopic procedure respond better than mature, multi-layered adhesions after open laparotomy with multiple resections. Body habitus is a factor. Higher subcutaneous fat thickness reduces the effective energy reaching the target plane, so dosing needs adjustment or the modality may simply be unsuitable. Serious adverse events are uncommon. Skin erythema and mild bruising are expected and resolve within 24 to 72 hours. There are isolated reports of hemoperitoneum when applied over vascular structures with excessive pressure, which is another reason I never treat blindly over the epigastric vessels or the iliac fossa without anatomical knowledge of the patient's surgical history.
When to steer the patient elsewhere
If pain is colicky, associated with vomiting, and linked to known dense adhesions causing partial obstruction, shockwave is not the answer. That scenario needs surgical evaluation. Physical therapy focused on myofascial mobilization and graded positional techniques can help adjacent musculoskeletal components but will not free deep intraperitoneal tethers. Anti-adhesion barrier films and surgical lysis remain the definitive interventions for mechanically significant adhesions. Devices vary widely. Radial acoustic wave systems from manufacturers like Storz Medical, Physiotools, and Duomedy are commonly used in physiatry and sports medicine clinics. Focused shockwave devices are available from several suppliers but require more precise targeting and carry higher cost. I do not recommend home units for abdominal adhesion work. The dosing requires clinical judgment and the risk of inappropriate application over unprotected viscera is real. There is no universal download link for this therapy because it is not software. It is a procedural modality. What you can look for are clinical guidelines and peer-reviewed studies. Search terms like extracorporeal shockwave therapy postoperative adhesions or radial shockwave abdominal wall pain will surface relevant papers. I have found that systematic reviews on the topic are sparse, which means the evidence base is still developing and outcomes should not be overstated.
A specific edge case I encountered
One patient presented with chronic right lower quadrant pain three years after appendectomy. She had a palpable adhesion tethering the anterior abdominal wall. Standard radial shockwave at 2 bar produced minimal relief during the first two sessions. I increased the impulse count per zone and changed the protocol to a cross-fiber pattern with slower probe movement, focusing on the fascial plane rather than the scar itself. By the fourth session she reported a noticeable increase in flexibility and a reduction in pain scores from 7 to 3 out of 10. The key was shifting from scar-centric targeting to fascial plane engagement.
Summary of practical considerations
Shockwave Therapy For Abdominal Adhesions is a viable adjunct for selected patients with superficial or moderately deep adhesive disease and neuromodulatory pain features. It is not appropriate for obstructive presentations, dense multi-layer adhesions, or patients with significant contraindications such as pregnancy, coagulopathy, or implanted electronic devices in the treatment field. Proper patient selection and anatomical awareness matter more than the device specifications. Expect gradual improvement over weeks, not immediate resolution, and be honest about the limitations when discussing outcomes with patients.