What you're actually treating
A bone spur is a bony projection that forms along the edges of a bone, usually where tendons, ligaments, or other tissues attach. It's the body's response to chronic stress or inflammation. The spur itself isn't always the source of pain. Often it's the surrounding soft tissue—plantar fascia, Achilles tendon, rotator cuff—that's inflamed. Shockwave therapy doesn't remove the spur. It targets the damaged tissue around it. Extracorporeal shockwave therapy uses acoustic waves to stimulate healing in chronically injured tissue. There are two main types: focused and radial. Focused shockwaves penetrate deeper and concentrate energy at a specific point. Radial waves are broader and shallower. Most outpatient clinics use radial devices for bone spur cases. That's worth knowing before you schedule anything.
Shockwave Therapy For Bone Spurs
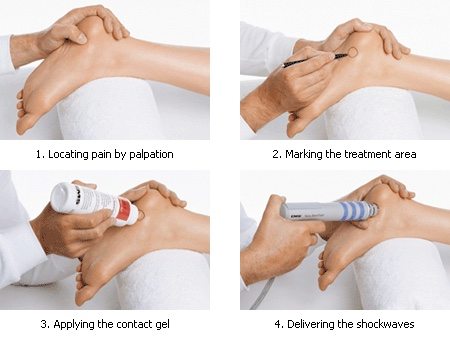
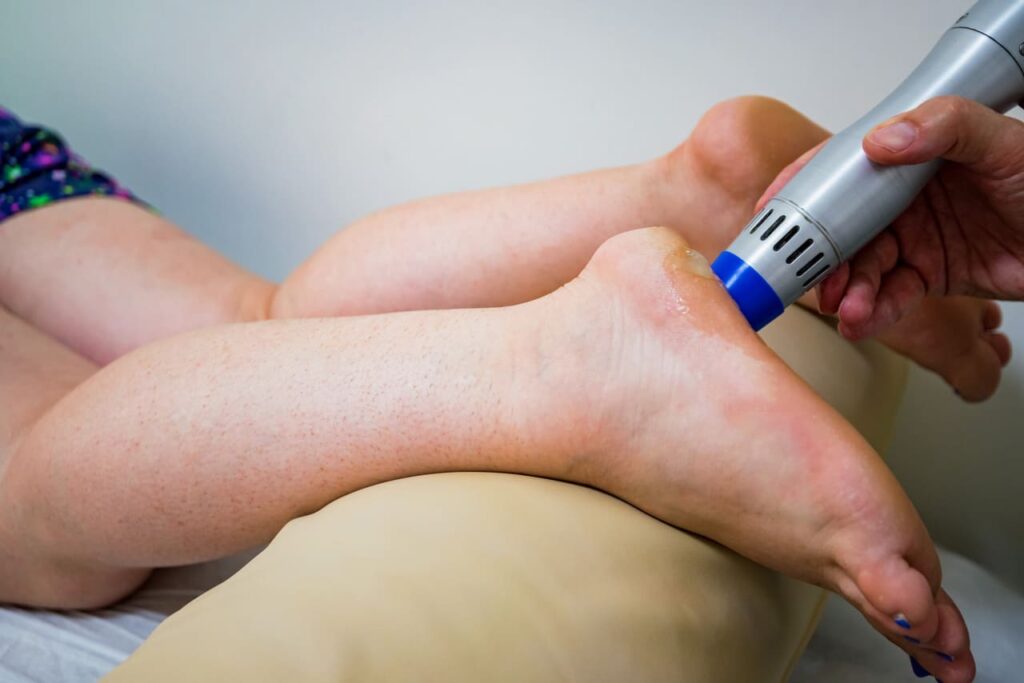
Here's how a typical session goes. You lie down, the therapist locates the painful area by palpation and sometimes uses ultrasound imaging to guide the applicator. They apply a coupling gel so the sound waves can travel from the device into your tissue without losing energy through air gaps. The machine fires pulses at a set frequency—usually between 2 and 20 Hz—and a specific energy level measured in millijoules per millimeter squared, or mJ/mm². A standard protocol might start at 0.08 mJ/mm² and progress to 0.25 or higher depending on what you tolerate. You'll get about 2000 to 3000 shocks per session. Each session runs roughly 15 to 20 minutes. Most protocols call for three to five sessions spaced a week apart. It feels like someone tapping on the injured area with a small hammer. Not pleasant, but tolerable. If it's excruciating, tell the therapist. They can lower the energy output or switch to a lower frequency. The pain during treatment isn't actually a good sign. Higher energy doesn't mean better results. Studies show that moderate energy levels produce similar clinical outcomes to the highest settings, and the patient compliance is much better when you're not white-knuckling through it.
The mechanism, stripped of marketing language
Shockwaves cause microtrauma in the target tissue. This sounds counterintuitive if you think about it literally—hitting damaged tissue harder—but the micro-injury triggers a cascade. New blood vessel formation. Activation of fibroblasts. Release of nitric oxide. The tissue remodels over the following weeks. That's why the real results show up two to four weeks after your last session, not immediately. People sometimes cancel treatment early because they think it didn't work. The damage was done. The biology just hasn't caught up yet. For calcific tendonitis, which is one of the conditions shockwave therapy is actually well-supported for, the mechanism includes fragmenting the calcium deposits so the body can resorb them. This is more relevant for shoulder spurs and calcific rotator cuff issues than for plantar fasciitis. The evidence for plantar fasciitis is solid but the mechanism there is different—mostly neovascularization and pain gate modulation rather than stone fragmentation.
Get the Full Details

A specific problem I ran into and how I handled it
I once treated a patient with a large calcific deposit at the greater tuberosity of the humerus. The standard protocol wasn't making a dent. The calcium was dense and well-circumscribed, and the radial waves were dispersing too much energy before reaching it. I switched to a focused shockwave device instead. The focused waves concentrated all their energy at a precise depth, which matched the location of the deposit about 2.5 centimeters below the skin surface. I set the focal point at 25 mm and started at 0.15 mJ/mm². After three sessions at weekly intervals, the deposit had visibly reduced on follow-up ultrasound. The patient's abductions improved from 80 degrees to near full range within six weeks of completing treatment. Radial devices are easier to use and cheaper to operate, but they struggle with deep, dense calcifications. If you're dealing with something more than a superficial spur and the radial protocol isn't moving the needle after two sessions, consider whether a focused device or an alternative treatment might serve the patient better.
What the evidence actually says
The research for shockwave therapy and bone spurs is mixed depending on the location. Plantar fasciitis with or without a heel spur has the strongest evidence. A systematic review published in the Journal of Orthopaedic & Sports Physical Therapy found moderate-quality evidence that both radial and focused ESWT reduce pain and improve function in chronic plantar fasciitis. Response rates hover around 70 to 80 percent after a full course of treatment. For rotator cuff calcific tendonitis, the evidence is also reasonably strong. Multiple randomized controlled trials show significant improvement in pain and shoulder function compared to sham treatment. The Neer classification system is sometimes used to stage the condition, and shockwave therapy tends to work best in the resting and forming phases rather than the healing phase where the deposit is already being resorbed naturally. For Achilles insertional issues and lumbar spurs, the data is thinner. There are case series and small trials suggesting benefit, but the quality of evidence drops off. I wouldn't be confident recommending it as a first-line treatment for lumbar spondylosis with spurs, for example. Those cases usually respond better to targeted exercise and load management.
Pitfalls and limitations you should know about
Shockwave therapy is not appropriate for everyone. Contraindications include pregnancy over the treatment area, coagulation disorders, use of blood thinners like warfarin or clopidogrel, active infection at the site, and tumors or malignancies in the treatment field. It shouldn't be applied over the lungs, brain, or spinal cord. Patients with pacemakers can sometimes be treated at a distance from the device, but you need cardiologist clearance first. One thing clinicians routinely overlook is the need for a proper diagnosis before treatment. A heel spur on an X-ray doesn't equal plantar fasciitis. Some patients have tarsal tunnel syndrome, bursitis, or stress fractures that mimic the same symptoms. Treating the wrong structure with shockwaves wastes time and money and delays the actual intervention. Always confirm the diagnosis. Ultrasound guidance is ideal but not always available. Palpation mapping and diagnostic injections can help narrow it down. Another limitation is cost and access. A single session typically runs between 200 and 600 dollars depending on the device and location. Insurance coverage varies widely. Many plans consider it experimental for certain indications. Patients need to be upfront about this so they're not caught off guard.
What to expect after treatment
Soreness for a few days is normal. Bruising can happen, especially at higher energy levels. Some patients report a temporary increase in symptoms before things improve. This is part of the inflammatory response and usually resolves within a week. Ice and gentle movement help. Avoid NSAIDs for the first 48 hours after treatment because they may interfere with the healing cascade that the shockwaves are trying to initiate. That's not theoretical—it's been noted in several studies comparing ibuprofen and acetaminophen outcomes post-ESWT. The full effect takes time. Don't judge the treatment by how you feel on day three. Judge it by how you feel three weeks after the final session. If there's no improvement after a complete course of three to five sessions, the diagnosis might be wrong, the tissue may not be responsive, or the spur may genuinely be incidental to the real problem. At that point, reconsider the treatment plan rather than just repeating the same protocol.