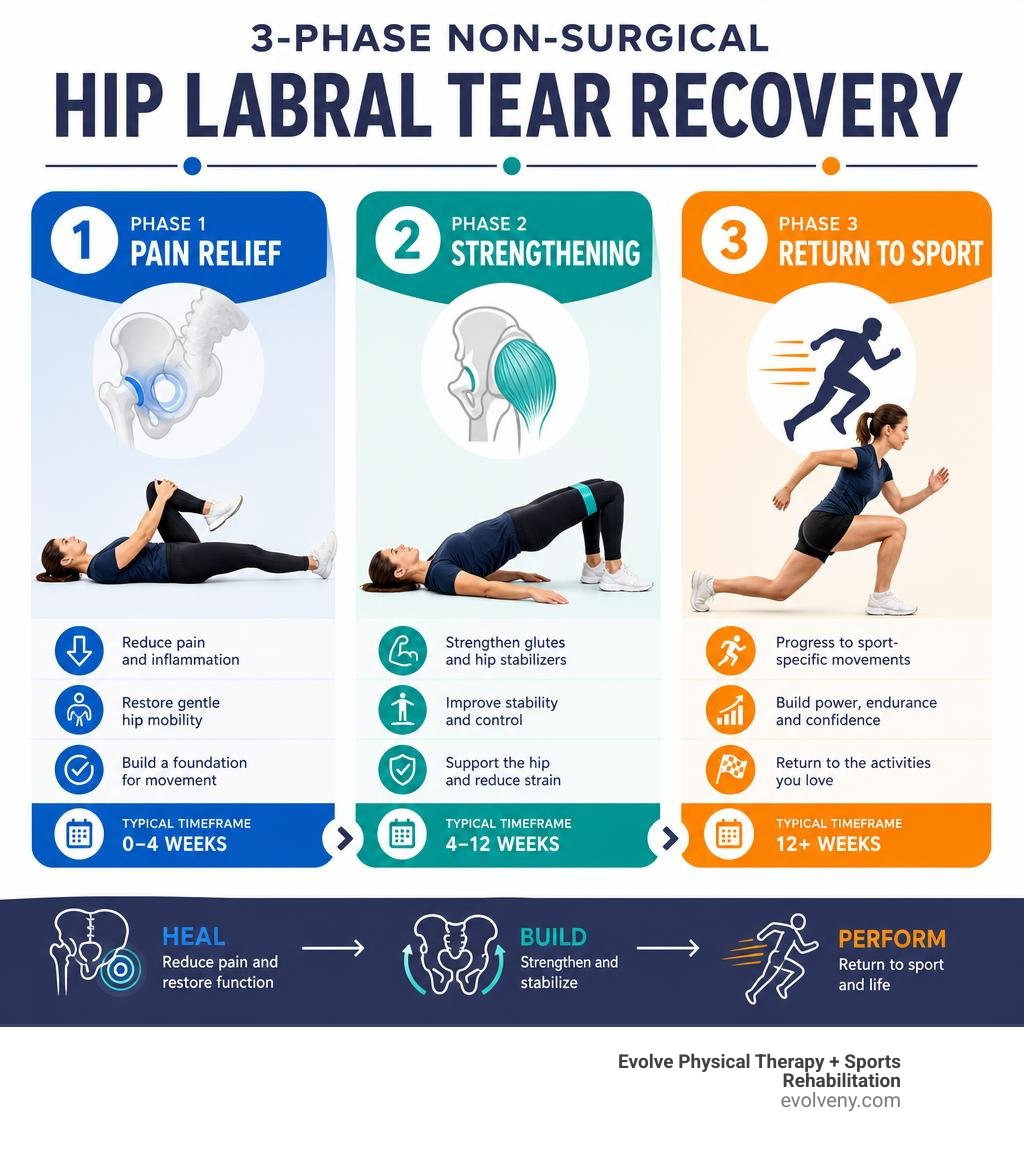
What Actually Happens When You Use Shockwaves On a Hip Labral Tear
Radial and focused shockwave therapy is used off-label for hip labral tears more often than the literature might suggest, mostly because clinicians are looking for non-surgical options that can stimulate tissue repair without going under anesthesia. The basic mechanism is straightforward enough: acoustic waves are delivered into the affected area, creating microtrauma that triggers a cascade of healing signals. New blood vessel formation follows, fibroblast activity increases, and the general inflammatory response gets reset toward a remodeling phase rather than staying stuck in chronic irritation. The thing most people don't realize is that the labrum itself has very poor blood supply. It's mostly avascular in the central regions, which means any treatment that claims to accelerate healing there is fighting an uphill battle from day one. Shockwave therapy doesn't change anatomy. What it does is potentially improve the vascular environment around the periphery of the tear, where the fibrocartilage transitions into the vascular zone. That's a meaningful distinction because it tells you exactly where this therapy can and cannot help.
Shockwave Therapy For Hip Labral Tear
From a practical standpoint, I've worked with a fairly standard protocol: radial shockwave at around 2 to 4 bar of pressure, 2000 to 3000 shots per session, applied directly over the anterior hip joint line where the labrum is most accessible. Sessions are typically spaced one week apart, with three to five sessions making up a standard course. Pain during treatment is notable but tolerable. You feel it as a deep, dull ache, not a sharp surface sting, and patients usually report the discomfort peaking about halfway through the session before settling down. Post-treatment soreness is common for 24 to 48 hours, sometimes longer if you're hitting a particularly irritable quadrant. One edge case I ran into recently involved a patient who had a degenerative labral tear with mild femoroacetabular impingement. Standard protocol didn't move the needle for them at all. What I found was that their symptoms were coming from a combination of labral irritation and significant tensor fasciae latae tightness compressing the same region. When I adjusted the approach and concentrated the shockwave energy more laterally, targeting the TFL and iliotibial band insertion before addressing the joint line directly, the treatment became effective. That shift alone cut what was otherwise a fruitless six-session protocol down to three sessions with clear improvement. The takeaway is that you need to treat the surrounding soft tissue environment, not just the labeled tear site. There's a misconception that more energy equals better results. It doesn't. Higher amplitude settings increase the risk of tissue bruising and reactive inflammation, which can temporarily worsen hip mechanics and push a patient backward. The effective dose sits in a narrow middle range. If you're new to this, start conservative and build up across sessions. Your assessment of tissue tolerance should drive the escalation, not a predetermined protocol sheet.
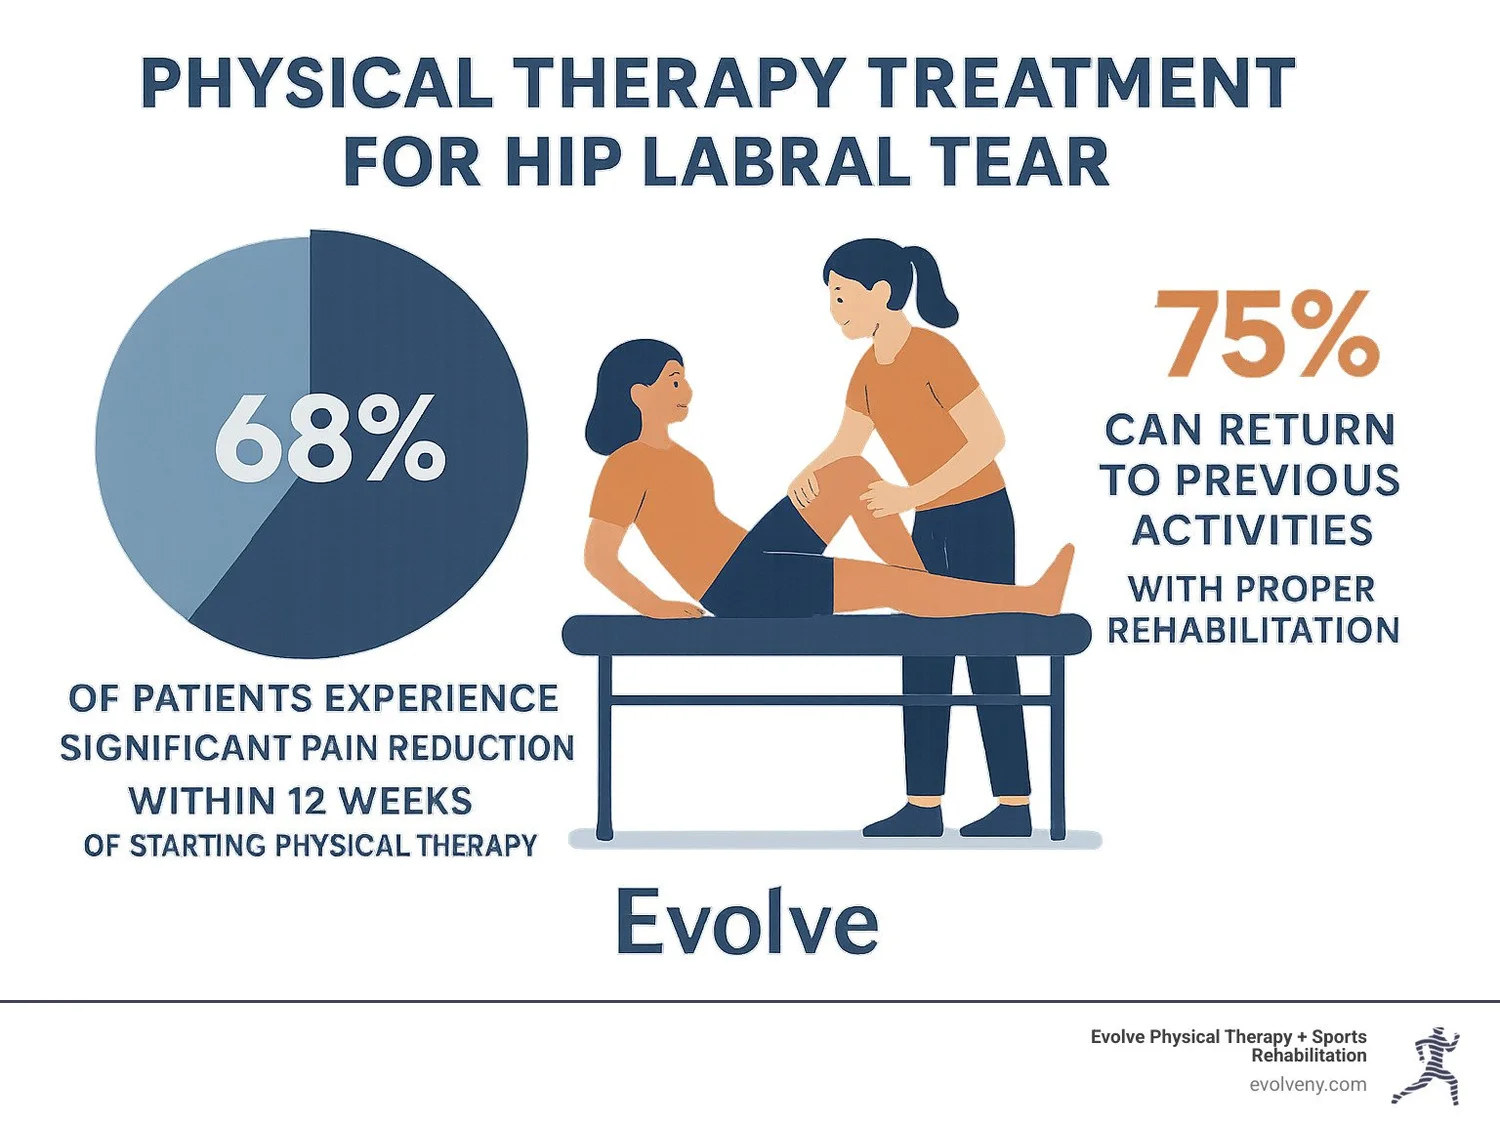
Another counter-intuitive point involves the timing of weight-bearing activities after treatment. Most protocols recommend avoiding heavy loading for 48 hours post-session, but I've seen patients recover faster when they reintroduced gentle, controlled movement within the first 24 hours. Complete rest after shockwave creates stiffness and reduces the mechanotransduction signal that the therapy relies on. Light hip circles, gentle range of motion work, and walking are fine. Heavy squats, sprints, and deep hip flexion under load should wait. The window between too much rest and too much load is narrow but survivable if you pay attention to what the hip tells you. Contraindications matter more than most clinicians admit. Coagulation disorders, use of blood thinners, active infection in the treatment area, malignancy in the region, and pregnancy near the hip all rule this out immediately. Less obvious is the presence of significant osteoarthritis alongside the labral tear. Shockwave won't help cartilage loss and may aggravate an already inflamed joint capsule. In those cases, the therapy can create more problems than it solves. Joint injection with corticosteroid within the past 90 days is another stop signal, as the suppressed tissue response will blunt whatever effect the shockwave might have produced. Success rates in published studies vary widely, which is partly due to differences in tear classification, energy parameters, and what "success" actually means in each trial. Broadly speaking, moderate evidence supports meaningful pain reduction and functional improvement in roughly 60 to 70 percent of appropriately selected patients. That leaves a significant portion who see minimal benefit, and those cases usually involve structural issues that mechanical stimulation simply cannot address.
Get the Full Details
If this route doesn't produce results after a full course, the next steps typically involve diagnostic injection to confirm the pain generator, advanced imaging to assess tear complexity, and discussion of arthroscopic options. Shockwave is not a substitute for structural repair when the tear is large, unstable, or causing mechanical symptoms like catching and locking. Using it as a delaying tactic in those scenarios only wastes time and money. The equipment landscape is split between radial wave devices, which are more common and cheaper to operate, and focused wave devices, which deliver deeper penetration but require more technical precision. Radial devices scatter energy across a broader area and work well for superficial soft tissue structures. Focused devices concentrate energy at a specific depth, making them theoretically better suited for deep labral targets, but they also carry higher risk if the targeting is off by even a centimeter. A missed target with focused shockwave can irritate the surrounding capsule or bursae and set the patient back weeks. Insurance coverage for this application remains inconsistent. It's still considered off-label by many payers, which means prior authorization is often necessary. Documentation should include the specific diagnosis, the failure of conservative measures like physical therapy and activity modification, and the parameters being used. Without that paper trail, claims get denied regularly, and patients end up paying out of pocket at rates that can range from $150 to $400 per session depending on the device and region.




