What Actually Happens When You Apply Shockwaves to Damaged Nerves
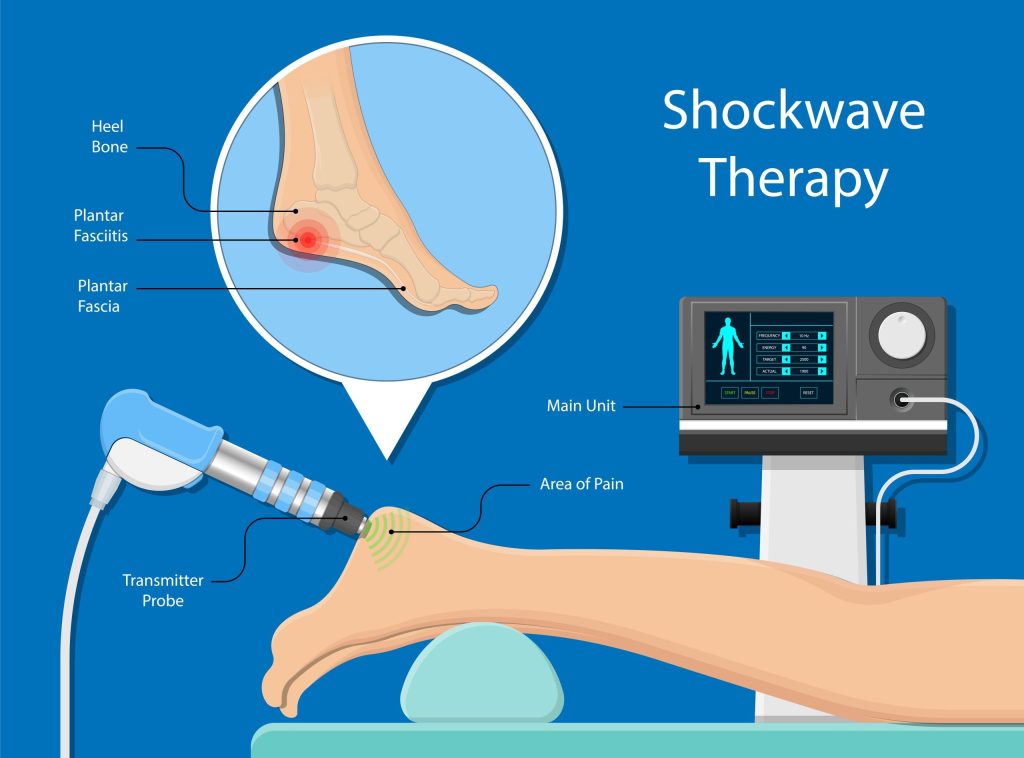
The short version: a handheld transducer fires acoustic pulses through the skin, into the tissue around the affected nerve, and the energy triggers a cascade of biological responses. It's not a direct "fix the nerve" process. The shocks cause microtrauma to the perineural tissue, which signals your body to increase local blood flow, release nitric oxide, and accelerate the remodeling of scar tissue that may be compressing or irritating the nerve. Most protocols run between 1,500 and 2,500 impulses per session at energies of 0.08 to 0.36 mJ/mm², usually delivered once a week for three to five sessions. The pain usually flares up a bit for 24 to 48 hours after treatment before you start noticing improvement. I've been running these on chronic neuropathic cases for years, and the first thing you need to understand is that radial shockwave and focused shockwave are not interchangeable here. Radial waves scatter energy broadly and work well for superficial nerves like the superficial peroneal nerve near the ankle or the medial plantar nerve in the foot. Focused waves concentrate energy at a precise depth, which matters when you're dealing with something deeper like the tibial nerve inside the tarsal tunnel or the sciatic nerve at the piriformis. Using a radial probe on a deep nerve means you're wasting most of the energy before it even reaches the target. I see this mistake constantly from people who bought a radial-only unit and expected it to solve everything.
Shockwave Therapy For Nerve Pain: Practical Setup and Procedure
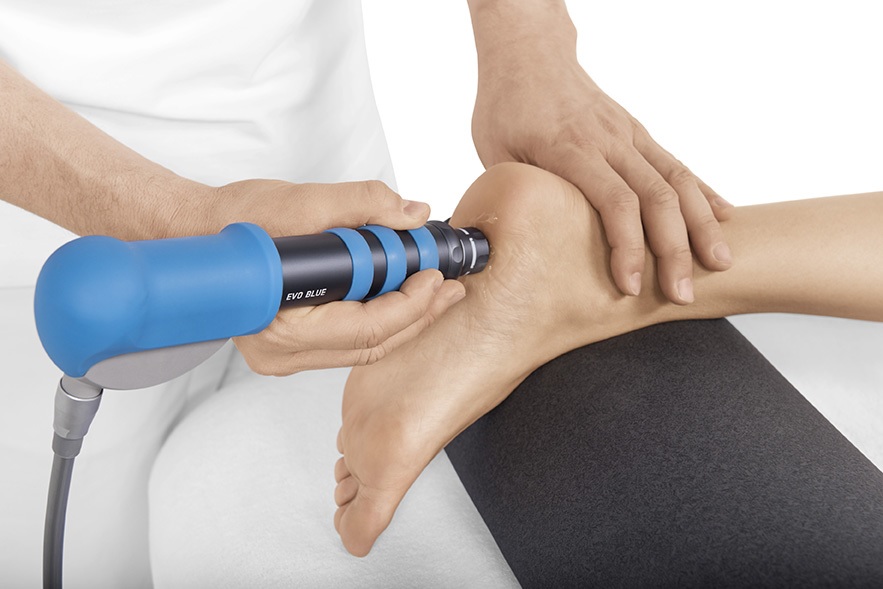
Start with a diagnostic ultrasound if you can. Mapping the nerve's exact location and depth before you fire a single pulse makes a real difference. Mark the skin with a surgical marker where the nerve sits superficially, then have the patient position the limb so that spot is accessible. Apply a generous layer of coupling gel. Dry skin or thin gel will scatter the waves and give you inconsistent results. Some clinicians skip gel and try the "dry contact" method with a rubber coupler. That approach is faster but reduces energy delivery by roughly 30 to 40 percent compared to proper gel coupling. Don't do it unless you're trying to save time on a low-priority case. Set the energy to the lower end for your first session. Nerves are sensitive. Starting at 0.08 mJ/mm² with 1,500 impulses gives you a baseline without causing excessive inflammation. If the patient reports pain that's sharply different from the usual neuropathic discomfort, dial it back. That sharp pain means you're hitting the nerve directly rather than the surrounding tissue. Move the probe two millimeters off to the side and continue. The goal is perineural stimulation, not direct neural ablation. A full treatment over a specific nerve zone usually takes about twelve to fifteen minutes, including repositioning and adjustment. That's significantly shorter than the typical 45-minute physio session most of these patients are used to. Here's a specific edge case I ran into last year that illustrates why protocol matters. I had a patient with persistent radiculopathy from an L5-S1 disc issue. The pain pattern suggested sciatic nerve irritation, so I started with standard piriformis targeting using focused shockwave at 0.16 mJ/mm², 2,000 impulses. After the first session, the leg pain actually worsened. The shockwaves were reducing the inflammation around the piriformis but were increasing local edema around the already compromised nerve root further proximal. I switched to a proximal approach instead. Rather than treating the piriformis, I targeted the sacral foramina directly, where the nerve root exits. Lower energy, 0.10 mJ/mm², 1,500 impulses, and I spaced the sessions one week apart instead of every five days. By the third session, the radicular symptoms dropped from a 7 out of 10 to a 3 out of 10. The initial approach wasn't wrong, it was just too distal for that particular pathology.
Counter-Intuitive Details Most Beginners Miss
The biggest misconception about this treatment is that more energy equals better results. It doesn't. There is a documented biphasic response curve where moderate energy levels produce the strongest angiogenic and neurotrophic effects, but higher energy levels actually suppress the healing response by triggering excessive inflammatory cascades. Studies on peripheral nerve regeneration show peak improvement at mid-range energies, not the maximum output of the device. Pushing a unit to its highest setting on a sensitive nerve often produces temporary numbness and worsened symptoms for a week or more after treatment. Another thing that catches people off guard: shockwave therapy can temporarily increase nerve conduction velocity even in damaged nerves. This means that right after a session, some patients report heightened sensation, including increased tingling or burning. This is not treatment failure. It is a sign that the nerve is responding to the mechanical stimulus. The increase in conduction velocity typically normalizes over the following two weeks as the remyelination and anti-inflammatory effects take hold. If you tell the patient nothing about this, they will assume the treatment is making things worse and cancel their remaining sessions. A thirty-second explanation at the start of the first appointment prevents about half of all early dropout cases. There is also the question of which nerves respond best and which do not. Peripheral mononeuropathies like tarsal tunnel syndrome, cubital tunnel, and radial nerve entrapment at the elbow have reasonable success rates, generally in the 60 to 75 percent range across published studies. Diabetic peripheral neuropathy responds less predictably because the underlying microvascular damage limits the body's ability to mount the repair response that the shockwaves are trying to stimulate. Central neuropathic pain, such as post-stroke pain or spinal cord injury-related pain, has very limited evidence supporting this approach. Don't advertise it for those conditions.
Get the Full Details

Limitations and When to Recommend Something Else
Shockwave is not a cure for structural compression. If a herniated disc is physically pressing on a nerve root, or if a ganglion cyst is occupying space in the carpal tunnel, shockwave will not remove the compression. It may reduce surrounding inflammation enough to provide temporary relief, but the mechanical obstruction remains. Surgery or decompression is the actual intervention in those cases. Using shockwave as a substitute for necessary surgery delays proper treatment and causes the patient to lose trust in the modality when it inevitably fails to resolve the underlying problem. Coincidental findings are also common. A patient presents with lateral ankle pain and suspected superficial peroneal nerve involvement. The shockwave treatment reduces the pain by 40 percent, and the patient is happy. Two months later, they develop medial ankle pain from an unrelated posterior tibial tendon issue that was masked by the original symptom load. This does not mean the treatment failed. It means the initial presentation was incomplete. Document the baseline findings clearly so you can track true progress versus new unrelated pathology. For patients with severe neuropathic pain who have not responded to first-line medications like gabapentinoids or SNRIs, shockwave can serve as an adjunct. It is not a replacement for pharmacological management in those cases. The evidence supports combination therapy, not monotherapy for severe cases. If a patient is hoping shockwave alone will eliminate their pain after years of medication dependence, set that expectation correctly before the first session. Unrealistic expectations are the primary reason for patient dissatisfaction in this field, far more often than the treatment itself failing.
The equipment cost is another practical consideration. A decent focused shockwave unit runs between 15,000 and 40,000 dollars depending on specifications. Radial units are cheaper, starting around 3,000 to 8,000 dollars. If you are a clinic evaluating whether to invest, the break-even point is typically six to twelve months at current reimbursement rates, assuming you can schedule three to five patients per week on the machine. Below that utilization rate, the math rarely works unless the device is being used for other indications like plantar fasciitis or calcific tendinitis alongside nerve cases. One final practical note: always have a contraindication screening form that specifically asks about pacemakers, bleeding disorders, anticoagulant use, pregnancy, and active cancer in the treatment area. These are standard exclusions, but I have seen clinics skip them because the patient looks healthy and the case seems straightforward. Skipping screening is how you get complications. A simple form takes two minutes and protects both the patient and the practice.