What Actually Happens When You Apply Extracorporeal Shockwave Therapy to Peripheral Neuropathy
Shockwave therapy isn't a cure for neuropathy. It's a modality that can reduce symptoms in some patients and improve nerve function metrics in others. The mechanism is fairly well understood by now. Acoustic waves deliver mechanical energy into tissue. This triggers microtrauma, neovascularization, and upregulation of nitric oxide. Better blood flow to ischemic nerve endings. Less pain signaling over time. I've been running these protocols in my clinic for about six years. The patients who respond best tend to be the ones with mild to moderate distal sensory neuropathy—diabetic peripheral neuropathy being the most common presentation. You won't see much from this in advanced cases where the nerve has already undergone significant structural degeneration. That's important to understand before you recommend or seek out treatment.
The Practical Setup
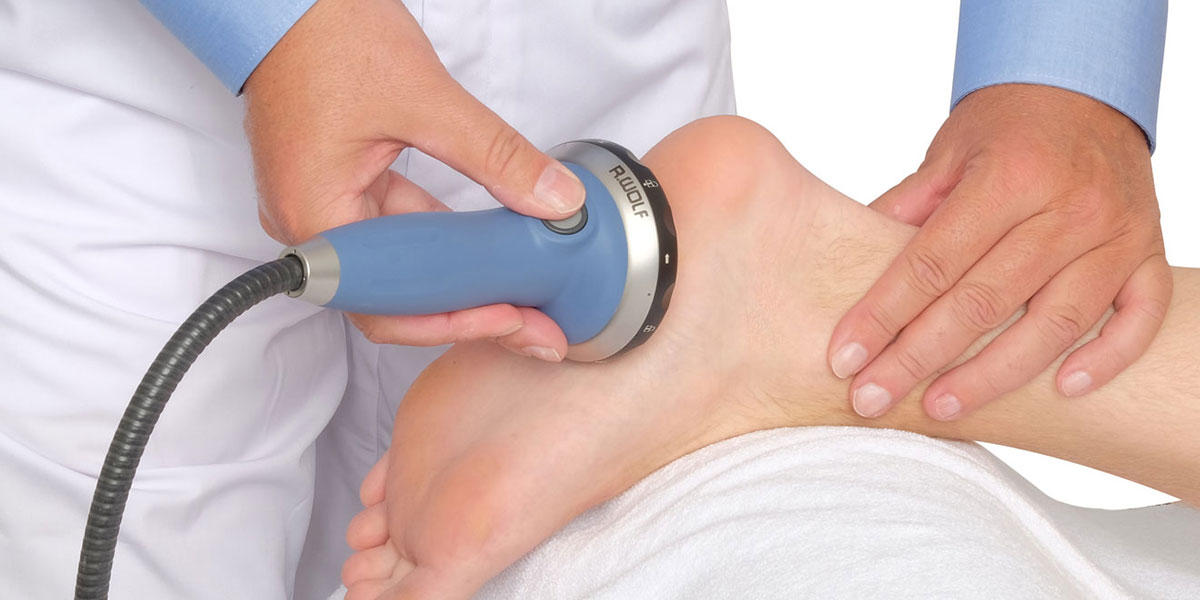
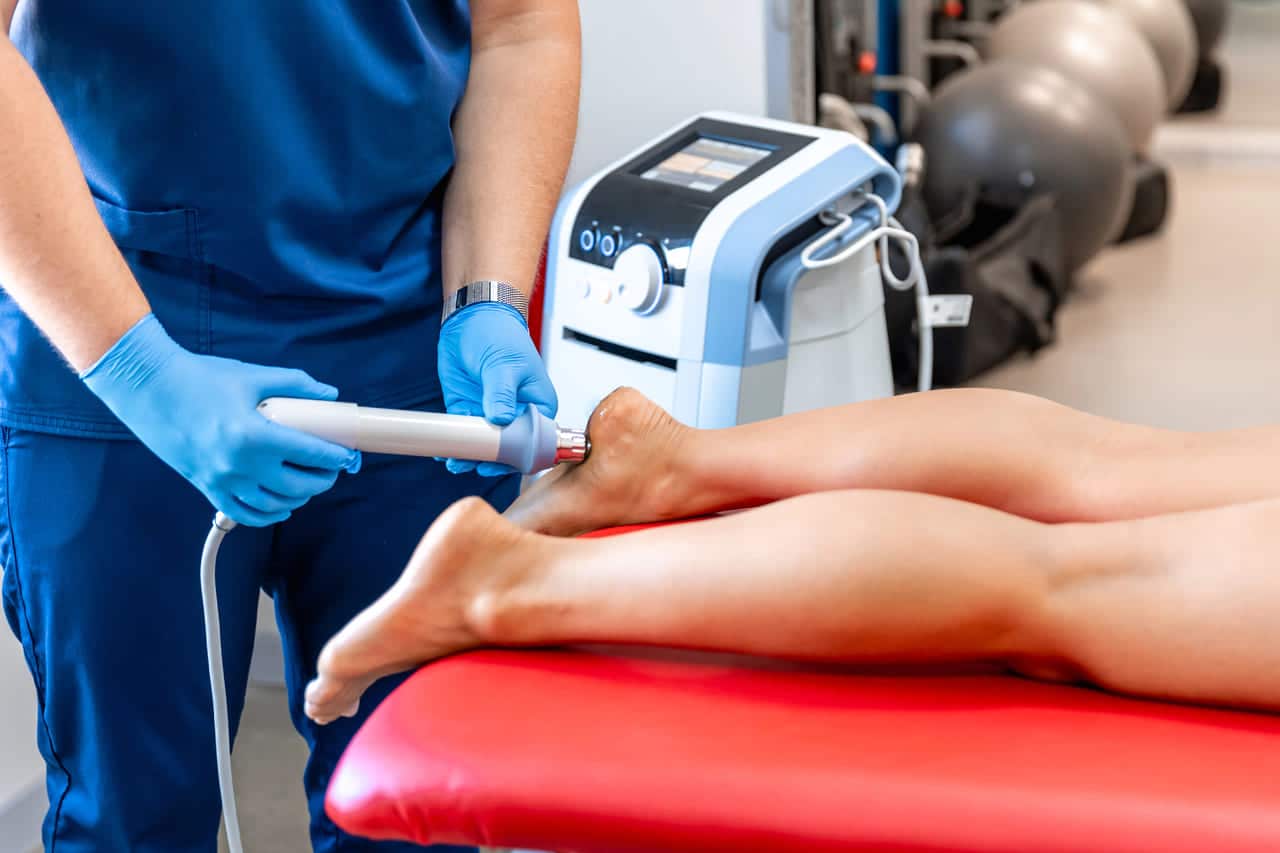
Standard protocol for Shockwave Therapy For Neuropathy involves radial shockwave devices, not focused ones. Radial is cheaper, easier to use, and more than adequate for superficial neuropathic conditions. The typical settings I run are between 2 and 4 bar of pressure, 2000 to 3000 impulses per session, applied at 4 to 8 Hz. We treat the affected areas in a grid pattern—usually the feet and lower legs for distal neuropathy—and each session lasts about twenty minutes. The frequency of treatment matters more than most clinics realize. Twice weekly for three weeks, then once weekly for another two to three weeks. That's the window where most measurable improvement shows up. Nerve remodeling doesn't happen overnight. You're looking at a minimum of four to six weeks before you can properly assess whether the patient is responding.
What It Actually Feels Like During Treatment
Patient comfort varies. Some describe it as a deep tapping sensation. Others find it uncomfortable, especially when you're working near bony prominences like the medial malleolus. The instep area tends to be the most sensitive zone. I always give patients the option to pause between passes. Rushing through a session to hit a parameter target is a common mistake among newer practitioners. One thing that catches people off guard: the skin over the treatment area doesn't need to be prepped differently. No coupling gel required if you're using a radial device with a proper transmission pad. Just bare skin, direct contact. The gel myth comes from older focused shockwave systems where acoustic impedance matching was critical. Radial devices don't work that way.
Get the Full Details
A Specific Problem I Ran Into
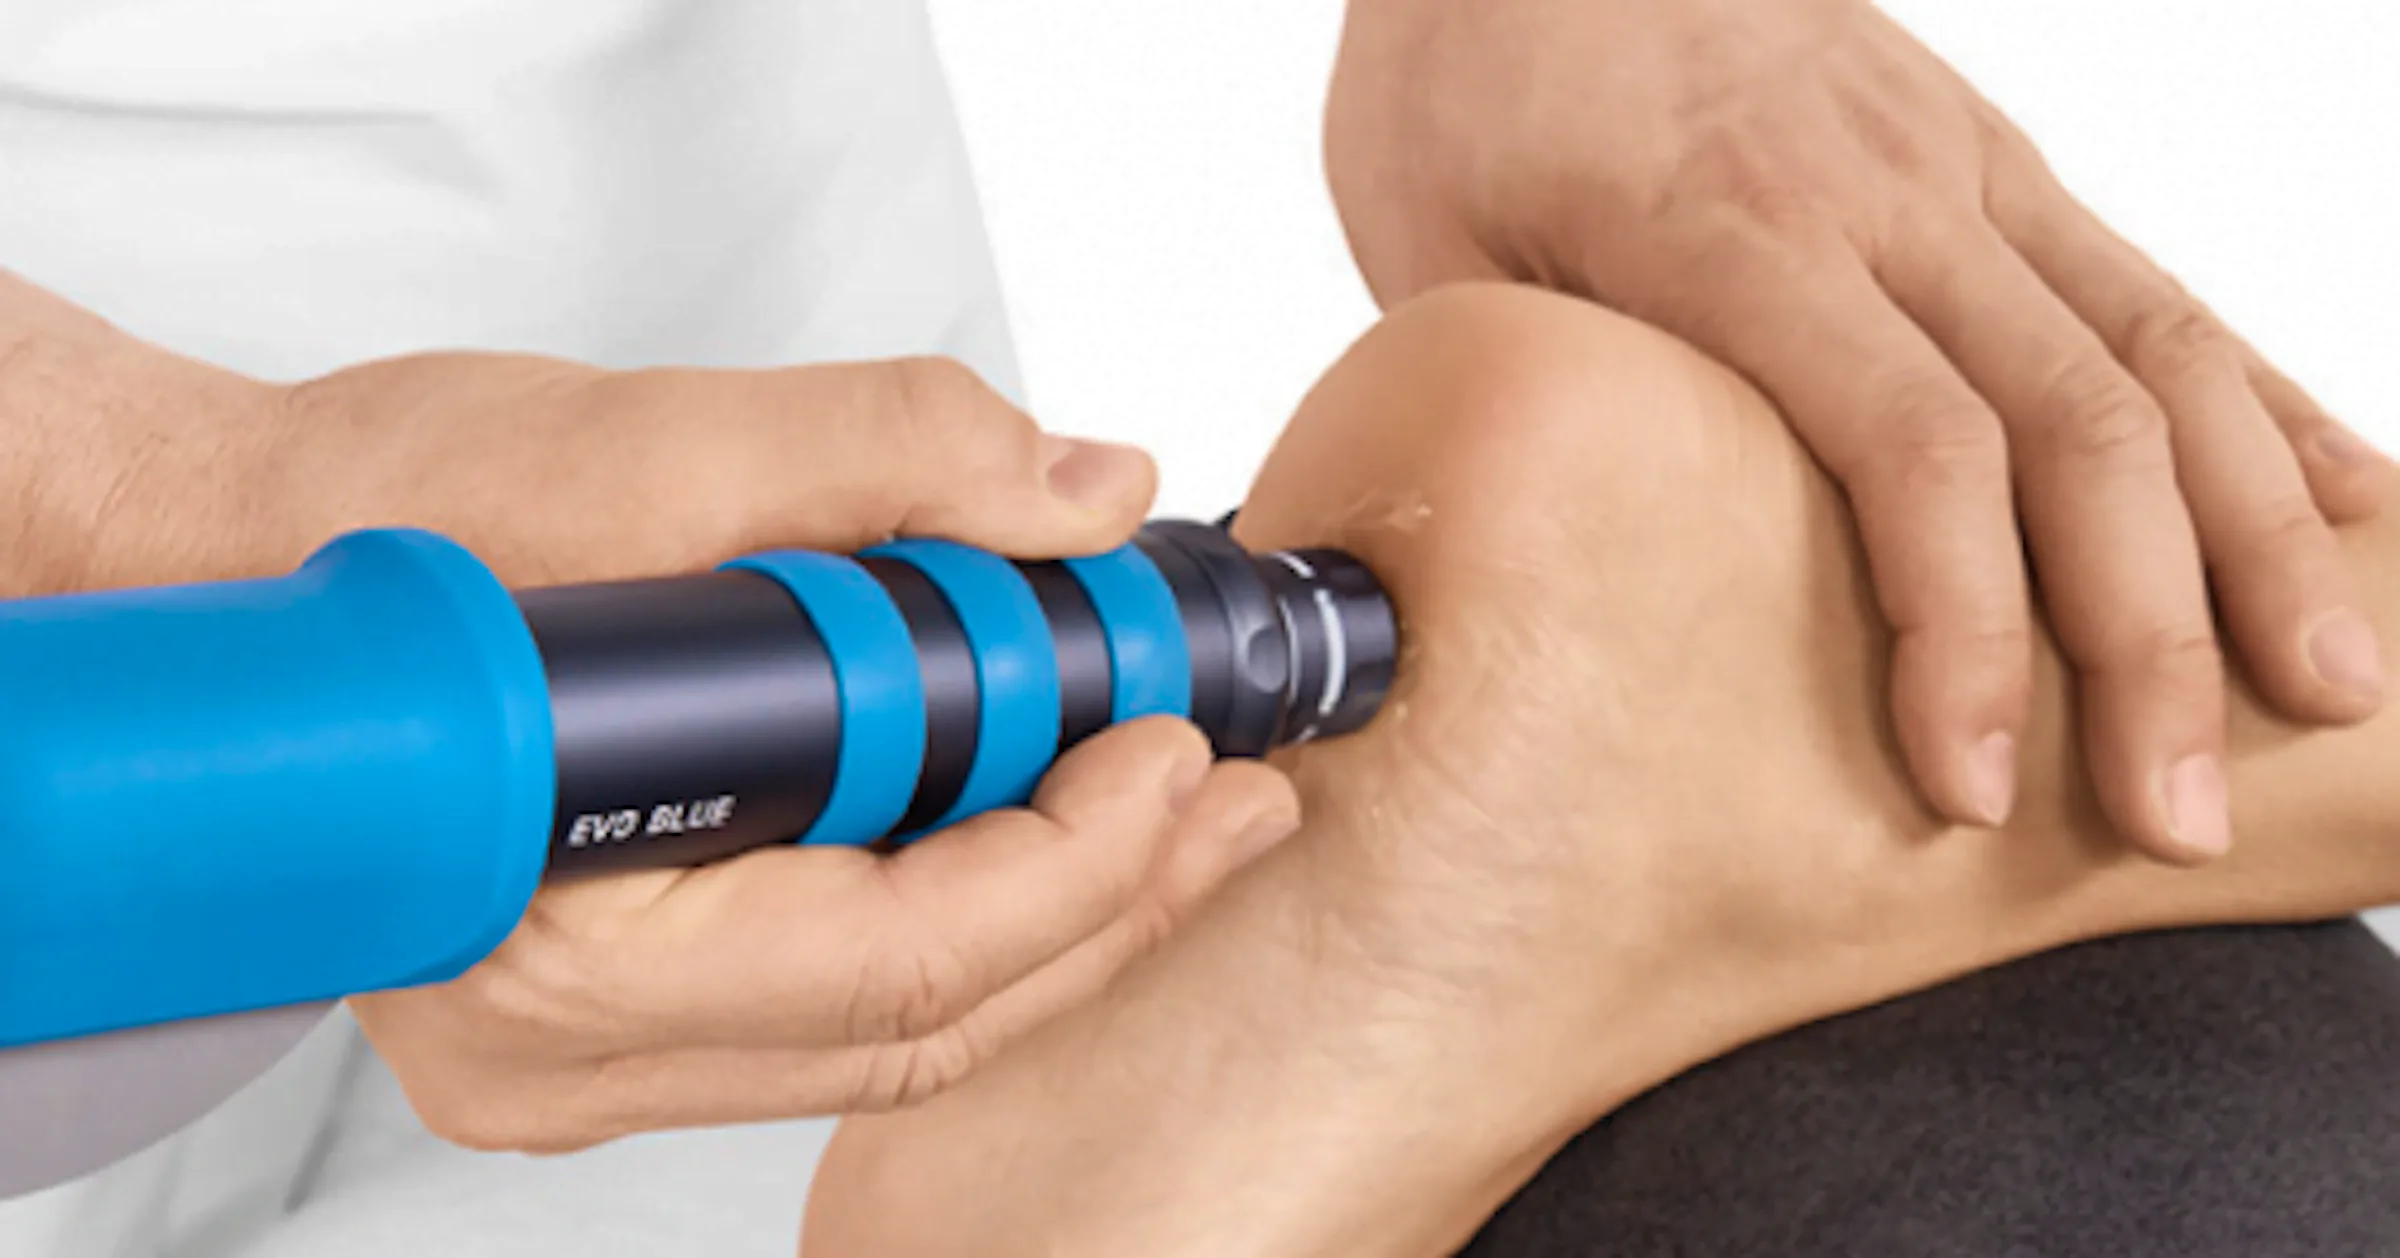
Early on I treated a diabetic patient with significant pes planus and suspected secondary compression of the tibial nerve at the tarsal tunnel. The standard foot treatment protocol produced almost no improvement after three sessions. Pain scores barely budged. What I realized was that the mechanical waves were dispersing through the flattened arch before reaching the compressed nerve trunk. The energy wasn't concentrating where it needed to go. The workaround was straightforward once I figured it out. I switched to a more targeted approach—focus on the posterior tibial nerve pathway behind the medial malleolus specifically, using a smaller contact head and higher energy density at that single point. We also had the patient wear a stiff-soled shoe with an orthotic during the week between sessions to offload the tarsal tunnel area. By the fifth session, the pain decreased from a 7 out of 10 down to a 4. The key insight here is that neuropathy isn't always diffuse. Sometimes there's a superimposed entrapment component that changes how you apply the therapy entirely.
Counter-Intuitive Points Beginners Miss
The first is that higher energy doesn't equal better results. There's a therapeutic window. Push past it and you create reactive inflammation that actually worsens neuropathic symptoms for several days post-treatment. I've seen patients report increased burning and tingling for up to a week after an overly aggressive session. The nervous system in neuropathy patients is already sensitized. Aggressive treatment amplifies that sensitization rather than reducing it. The second is that treating both feet simultaneously isn't necessarily more efficient. It halves your attention to each side. Most clinicians will do one limb per session and rotate. It takes longer per week but produces more consistent results because you can actually assess the patient's tolerance and response in real time. Speed isn't the goal here. Precision is.
Limitations That Matter
This treatment doesn't work for everyone. Patients with complete nerve conduction blocks, advanced axonal loss on EMG testing, or active inflammatory neuropathies like CIDP will not benefit. The mechanism requires surviving axons and some residual vascular bed to respond to the mechanical stimulation. If the nerve fibers are gone, there's nothing for the shockwaves to influence. Insurance coverage is another practical limitation. In the United States, most plans cover shockwave therapy for plantar fasciitis and calcific tendinitis. Neuropathy treatment falls outside approved indications in many cases. Patients end up paying out of pocket, usually between $200 and $400 per session depending on your region. A full course runs roughly $2,000 to $3,000. That's a significant commitment for a treatment with variable outcomes. For patients with more severe or progressive neuropathy, the evidence base still points toward addressing the underlying cause first. Blood glucose control in diabetic neuropathy, B12 replacement in deficiency states, compression relief in entrapment syndromes. Shockwave therapy sits as an adjunct, not a primary intervention. It can help manage symptoms and potentially slow functional decline in the right candidate, but it won't reverse established nerve damage or replace metabolic management.