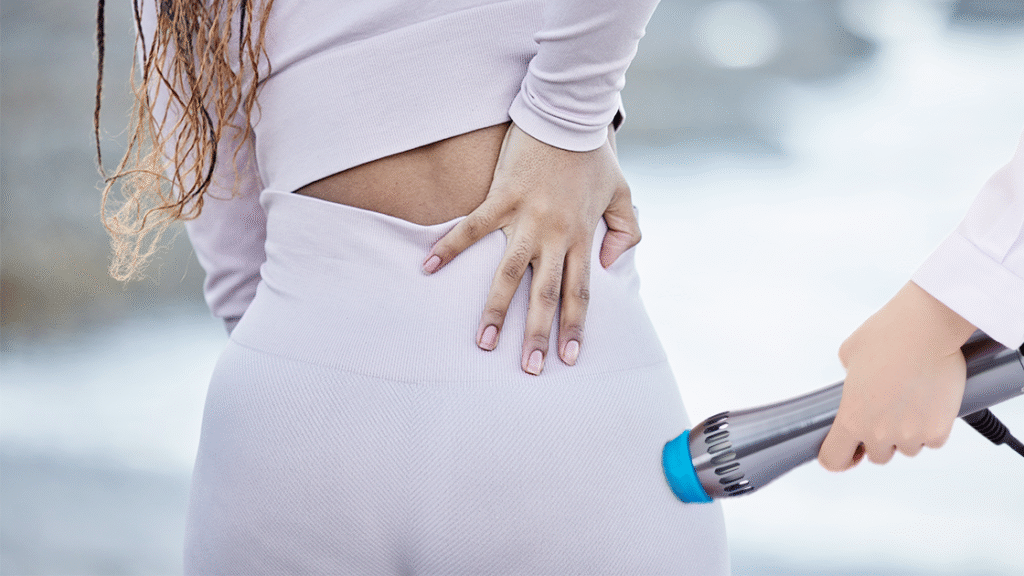What actually happens when you use shockwave on that muscle
Piriformis syndrome is one of those conditions where every anatomy textbook says the piriformis compresses the sciatic nerve, but nobody tells you that most people presenting with "piriformis syndrome" actually have a gluteal or lumbar referral pattern masquerading as it. The shockwave doesn't care about your differential diagnosis though. It just delivers mechanical energy into tissue and creates a biological response. That's it. Radial shockwave therapy uses acoustic waves that travel through air and decay over distance. Focused shockwave concentrates energy at a specific depth. For piriformis work, I usually reach for radial because the muscle sits deep under the gluteus maximus and you need coverage over a broader area. Focused is better for precise calcifications or trigger points, but getting the beam aligned when your patient is in prone position and you're trying to locate the exact spot by palpation? That's a different kind of pain.
Shockwave Therapy For Piriformis Syndrome Protocol
Standard settings I use: 2 to 4 bar energy flux density, 2000 to 3000 shots per session, frequency at 8 to 12 Hz. Treatment lasts roughly 15 to 25 minutes depending on how much scar tissue is in there. One patient I treated had been dealing with what they called piriformis pain for fourteen months across three different physiotherapists. The tissue around the right ischial tuberosity was basically leather. We went to 4 bar on that area and they winced at shot number fourteen. That's the kind of feedback that tells you exactly where to concentrate the dose. The mechanism isn't really about breaking up scar tissue the way people describe it. It's more about neovascularization and the upregulation of growth factors. VEGF gets released, new capillaries form, and the chronic hypoxic environment of that muscle shifts. Nitric oxide plays a role too, which is why you'll sometimes see patients describe warmth or tingling during the session. That's not the sound waves heating the tissue. That's biochemical. Sequence matters more than most guides will tell you. I start peripheral and move inward. Gluteus medius insertions first, then the iliac crest insertions, then tracking along the obturator internus fascia, and finally the ischial tuberosity where the piriformis actually originates. If you hit the origin point first on someone with an irritable nervous system, you've made them tight, not loose. They'll guard, you'll miss targets, and you'll waste thirty minutes chasing pain.
The parts nobody talks about
Most clinics doing this for piriformis are setting the probe at a ninety-degree angle to the skin surface. That works fine for superficial muscles. The piriformis runs at roughly a forty-five degree angle deep in the buttock. Angling the probe downward toward the greater sciatic notch actually matches the fiber direction better and puts more of the energy into the target tissue instead of scattering it through the gluteus maximus first. You'll need fewer shots to get the same therapeutic effect. Another thing: the sciatic nerve sits right behind the piriformis in most people. During treatment, some patients report electric sensations if you're tracking too deep or using too high an energy density. That's not a sign that you're hitting the nerve. It's usually just nerve irritation from proximity. I drop to 2 bar and widen the focal area when that happens. If the electric sensation persists, you back off completely and reconsider whether the pain generator is actually the piriformis or something lumbar. I ran into a patient once who had recurrent piriformis symptoms after three rounds of shockwave. Everything looked normal on imaging. The breakthrough came when I stopped treating the buttock and started treating the L5-S1 facet joint on the same side. The piriformis is innervated by branches from L5 through S2. Facet referral can track down into exactly the same region. We shifted focus and the symptoms dropped by sixty percent in two sessions. The shockwave still helped, just not where we were putting it.
Get the Full Details

What it actually feels like
First session, most people rate it around six out of ten on a pain scale. The second session usually feels softer because the tissue has responded. By session three, it's more of an uncomfortable pressure than actual pain. Some patients fall asleep. That's a good sign. It means your settings are appropriate and the nervous system is settling. Post-treatment soreness is normal for twenty-four to forty-eight hours. The area can feel bruised or deep-achy. Ice helps for the first twelve hours, then switch to heat. I've had patients who wanted to push through the soreness and return to heavy lifting the next day. That just resets the inflammatory cascade and you're back to square one. The therapeutic window after each session is roughly seventy-two hours. Respect it or waste the treatment. Sessions are typically spaced one week apart. Three to five sessions is the standard protocol for most soft tissue conditions including piriformis. Evidence starts weakening after five sessions at the same parameters. If someone hasn't improved after three sessions, reassess the diagnosis before doing session four.
When it won't help
Structural bony impingement of the sciatic nerve by the piriformis itself is rare. True anatomical variants where the nerve splits through the muscle belly don't respond to shockwave because there's no soft tissue pathology to modulate. Surgical release is the actual intervention there. Similarly, lumbar radiculopathy that's mimicking piriformis symptoms won't benefit. The shockwave treats local tissue dysfunction, not proximal neurological compression. Pregnant patients shouldn't receive shockwave over the gluteal region due to proximity to the uterus, even though the energy doesn't penetrate deeply enough to cause direct harm. Better to be conservative. Same with patients on blood thinners. The bleeding risk under the skin is low but real, and you'll get hematomas that make subsequent sessions painful and less effective. Diabetic patients with peripheral neuropathy often show blunted responses because their angiogenic capacity is reduced. VEGF production doesn't spike the same way. They can still benefit from the neuromodulatory effects, but expect fewer results per session and a longer treatment course. Six to eight sessions instead of three to five.
Practical setup notes
If you're setting up a practice for this, the coupling medium matters more than people realize. Standard ultrasound gel works but it's runny and migrates. A thicker hydrogel or even a water bath technique gives better acoustic transfer and lets you maintain consistent contact while moving the probe. For deep piriformis work I prefer the water bath method. Fill a basin with warm water, have the patient submerge the gluteal region, and apply the probe through the water. The water eliminates air gaps completely and the thermal component adds a mild vasodilatory effect on its own. Docimetry or palpation-guided targeting beats image guidance for most cases. Ultrasound guidance is expensive and slow. A trained finger can locate the trigger bands along the piriformis border faster and with enough accuracy for clinical purposes. The key is having the patient in side-lying or prone with the hip flexed and internally rotated to bring the muscle taut and more accessible. Combining shockwave with stretching produces worse outcomes than shockwave alone in my experience. The mechanical stress of stretching immediately after disrupts the early inflammatory healing response. Wait at least two hours, preferably longer, before any aggressive stretching of the gluteal region. Gentle walking is fine. Stretching is not.