How to Actually Use Shockwave Therapy On a Tendon Without Wasting Time
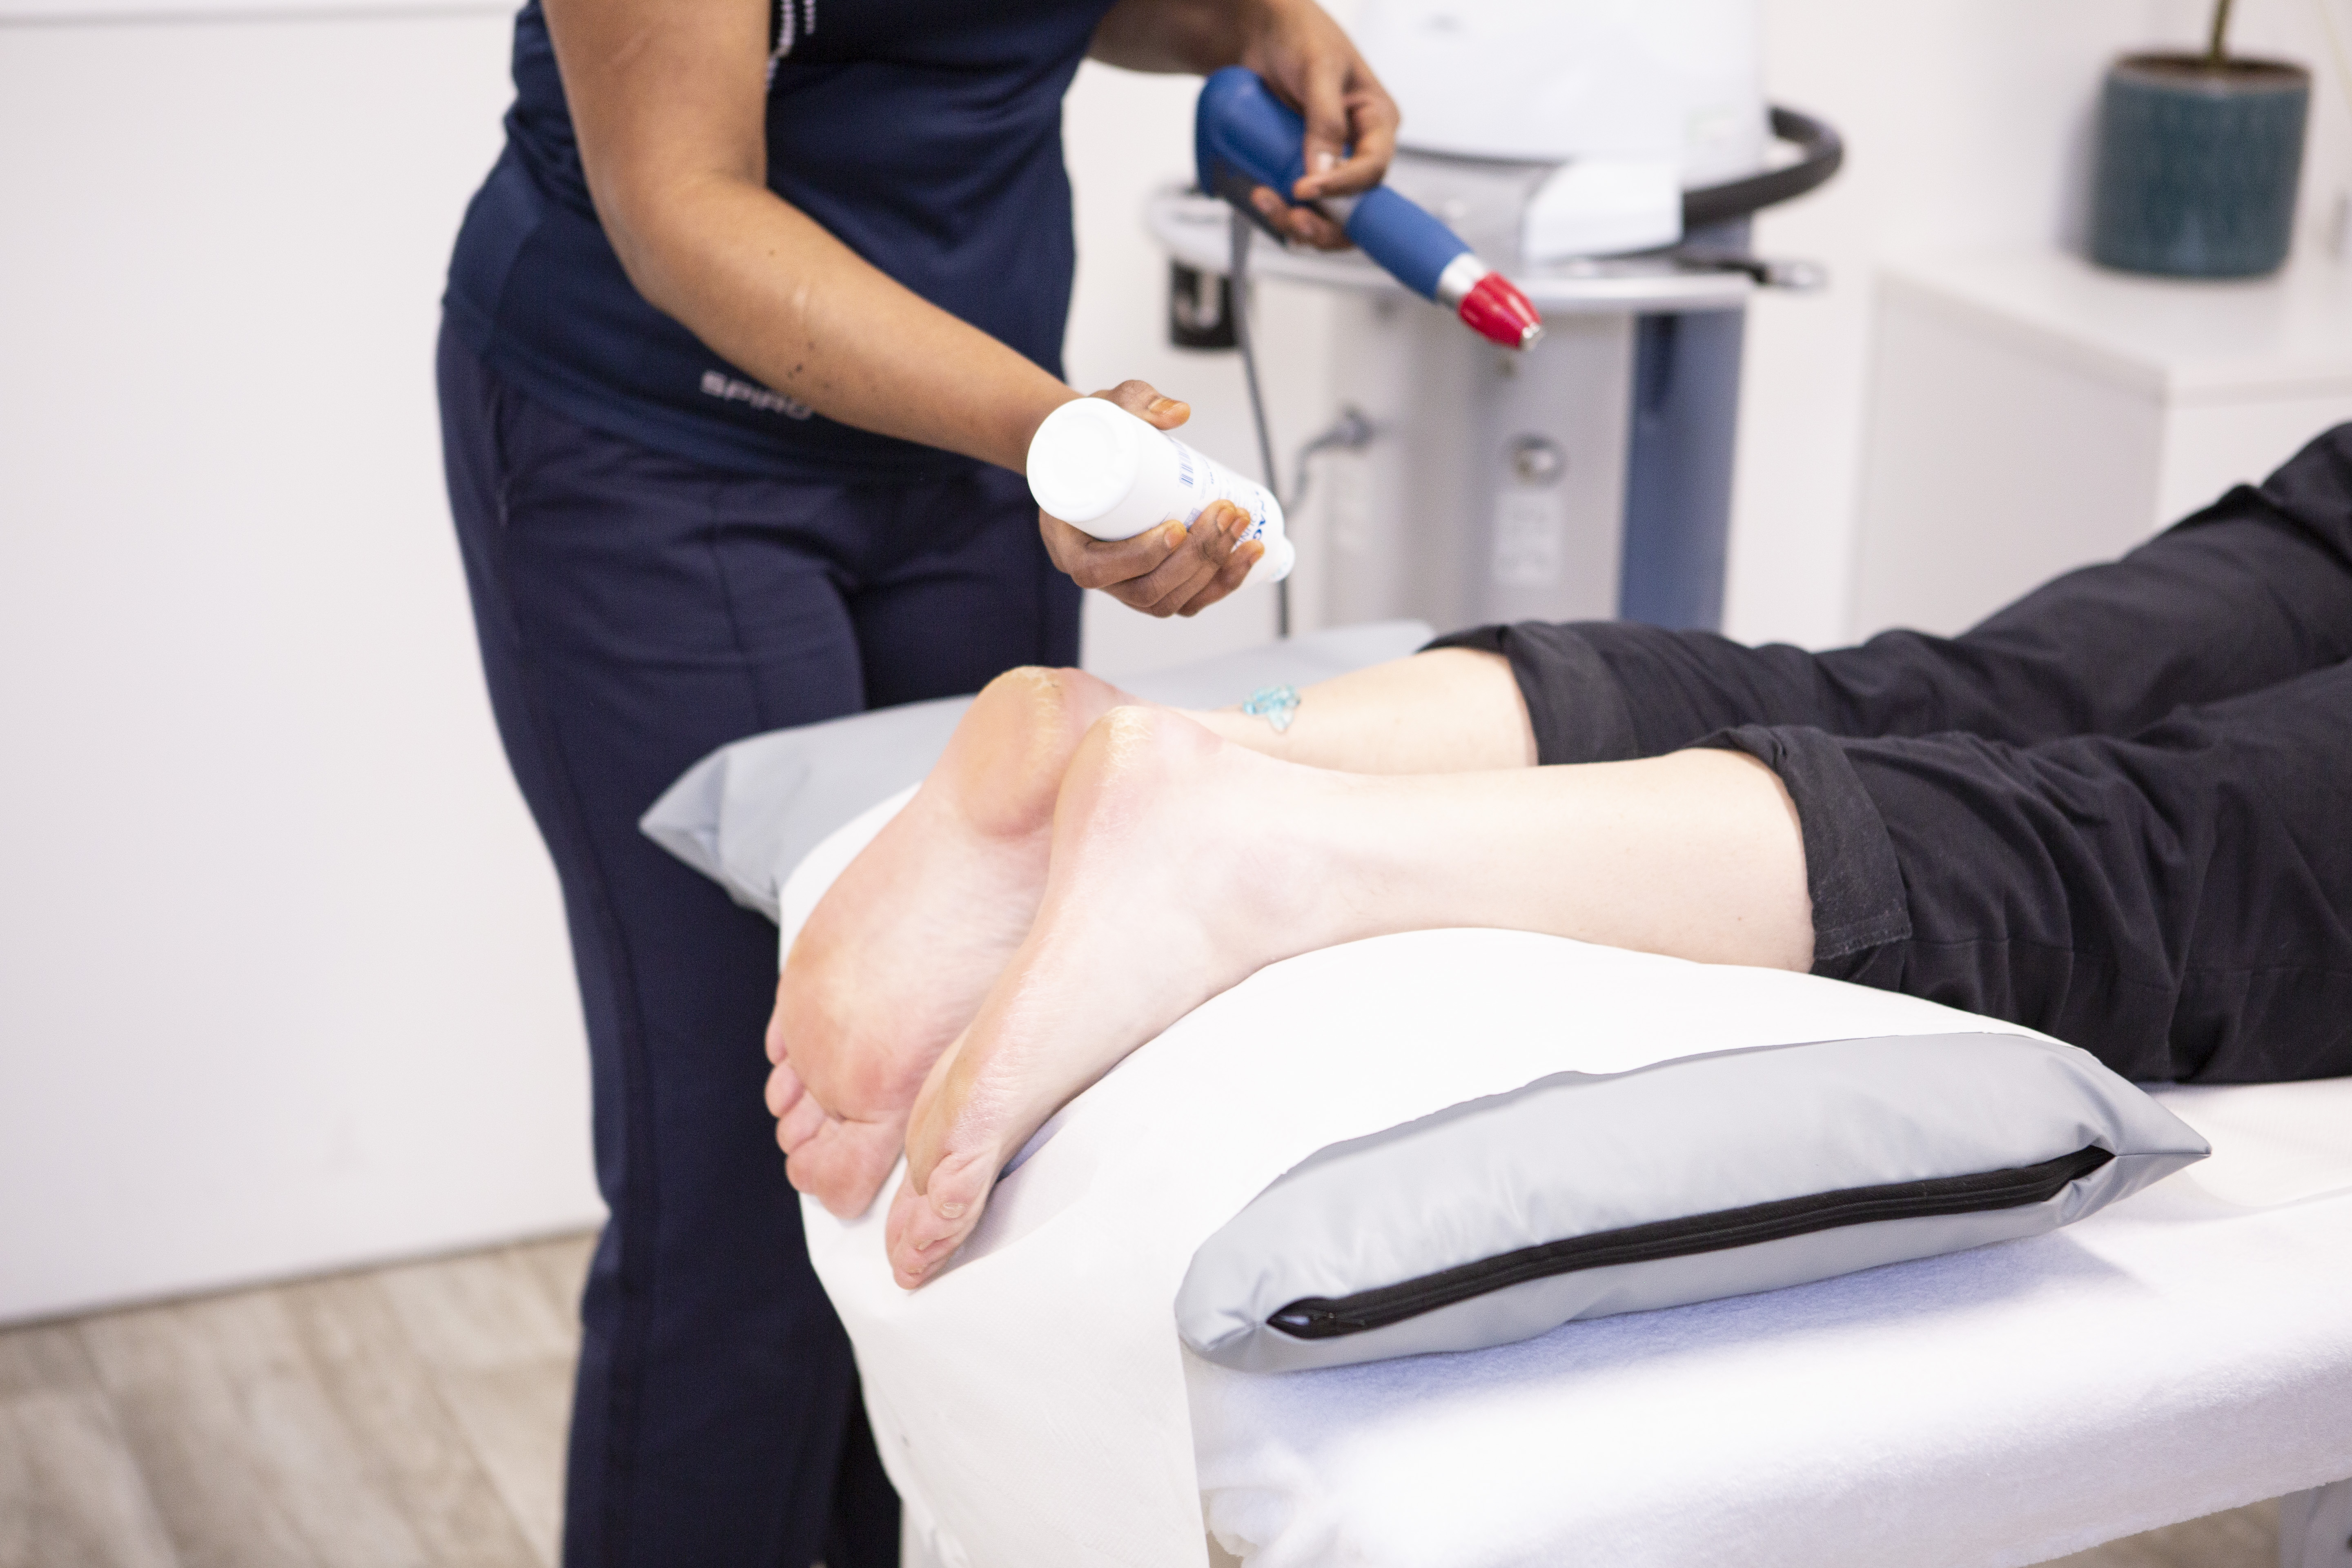
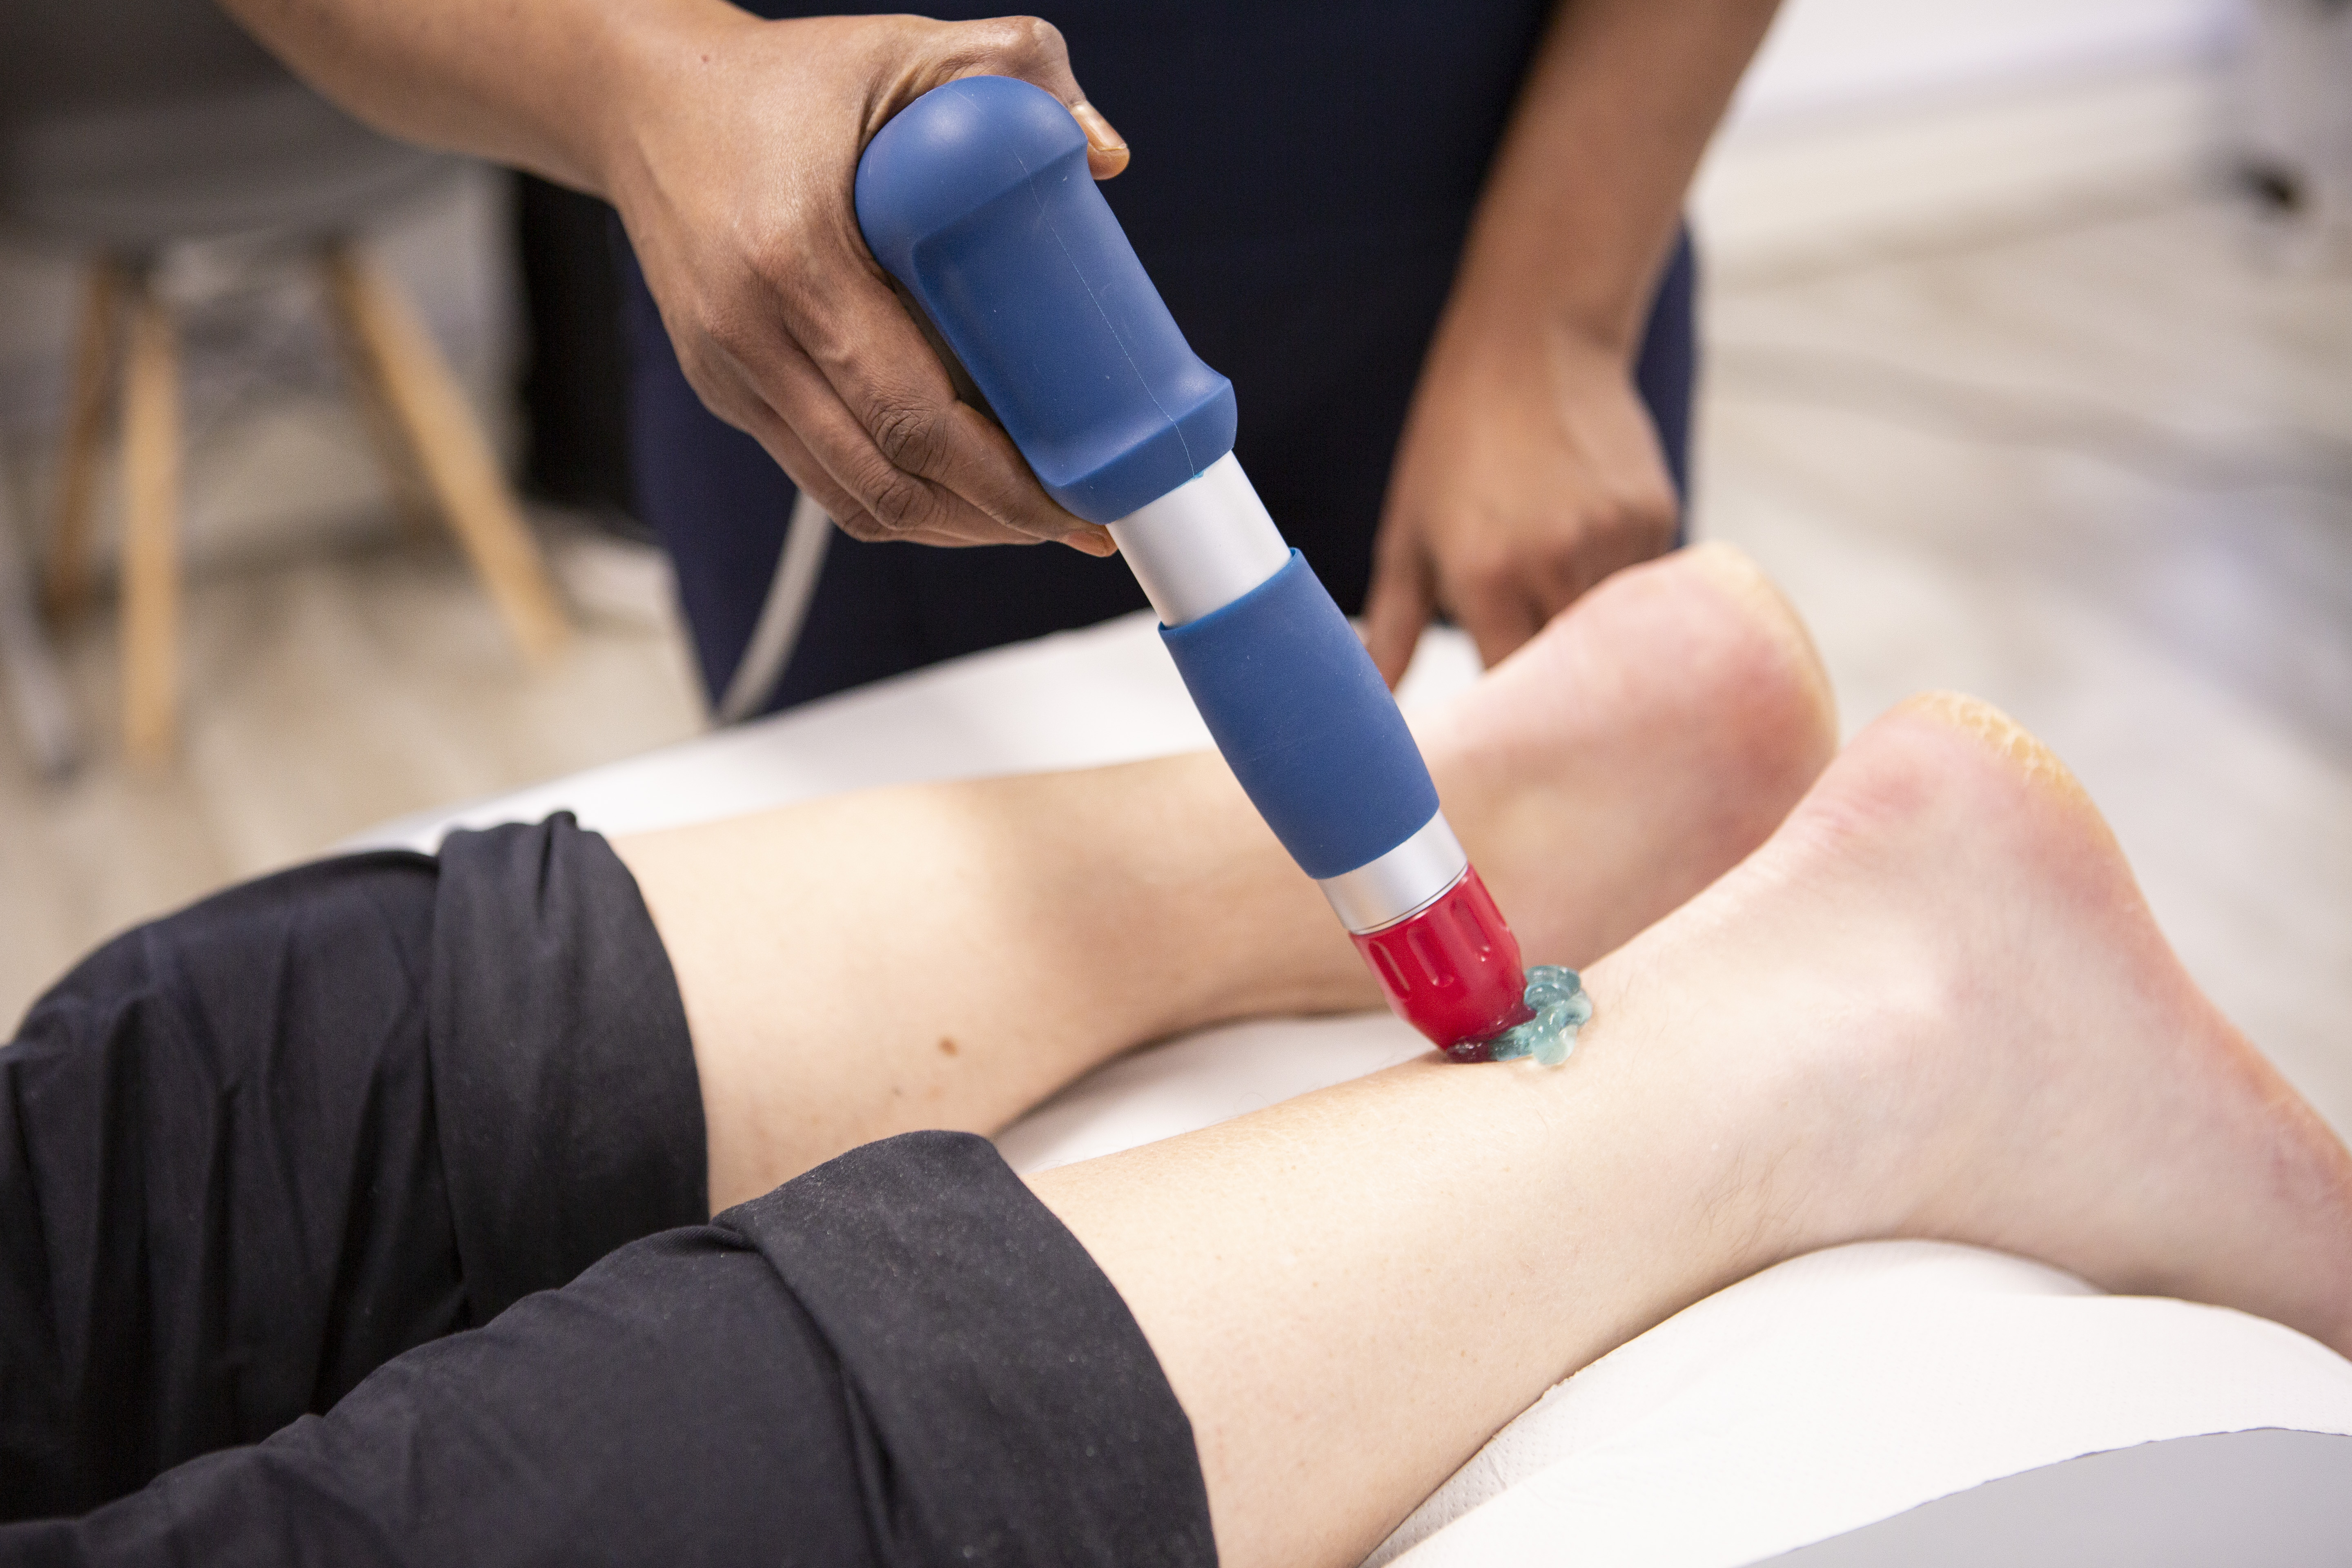
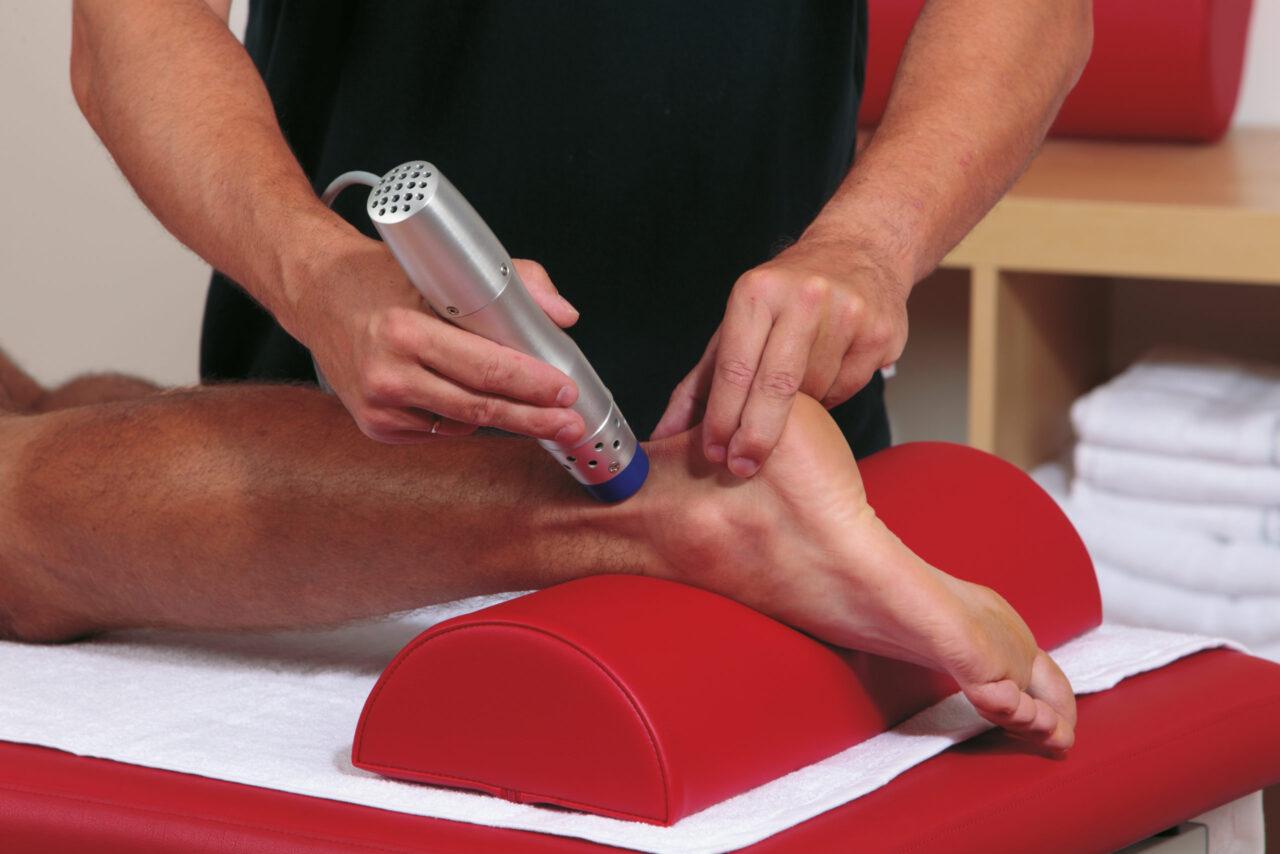
The machine outputs acoustic pulses at a set frequency measured in hertz. The most common setting for chronic tendinopathy is between 15 and 18 hertz. Energy fluence is the other knob you turn, usually starting at 0.15 to 0.25 mJ/mm² for radial shockwave and going a bit higher if the tissue tolerates it. You move the transducer slowly over the affected area. Each point gets roughly 100 to 200 pulses before you shift position. A full session for a single tendon usually takes about 8 to 12 minutes. The two main delivery methods are radial and focused. Radial shockwave scatters energy through a coupling pad. It is cheaper to run, covers a larger area quickly, and is fine for most tendons near the surface like the Achilles or lateral epicondyle. Focused shockwave concentrates energy at a precise depth. That matters when the pathology sits deeper, like the patellar tendon insertion or the rotator cuff near the humeral head. Most clinics in the US use radial devices because focused units cost significantly more and require more training to interpret the target zone correctly.
Shockwave Therapy For Tendon Repair: What Happens After the First Few Sessions
I have treated dozens of chronic insertional Achilles cases with this approach. The protocol I rely on is three sessions spaced one week apart, using radial ESWT at 0.20 mJ/mm² and about 2000 pulses per session. Patients report soreness during treatment and a dull ache for 24 to 48 hours after. That soreness is normal and usually means the tissue is responding. If a patient has zero pain during the session and zero post-treatment ache, I increase the fluence slightly on the next visit. The tissue needs a mechanical stimulus strong enough to provoke a biological reaction. The mechanism is not just about breaking up calcifications, although that does happen with focused waves in calcific tendinitis of the shoulder. The real drivers are neovascularization through upregulated VEGF, disruption of nociceptive nerve endings, and a localized inflammatory cascade that pushes tenocytes back toward a healthier matrix pattern. Collagen type I synthesis increases over the following weeks. That is why results are rarely immediate. The tendon remodels slowly, and the best outcomes show up at six to eight weeks after the final session. Here is a detail most guides skip. Treatment comfort is not a reliable proxy for efficacy. I once had a patient with severe lateral epicondylalgia who could barely tolerate the probe. His pain score during treatment was a nine out of ten. We dropped the fluence to 0.12 mJ/mm², used a broader contact area, and applied the probe perpendicular to the fiber direction instead of at an angle. He still got adequate mechanical stimulation because the total pulse count stayed high. He finished the three-session course and had meaningful improvement by week six. Pushing fluence too hard on a hypersensitive tendon just causes defensive muscle guarding, which changes your coupling and makes the treatment less precise.
Another counter-intuitive point is that rest after treatment is worse than light movement. I tell patients to avoid heavy loading for three to five days after a session, but they should walk, do gentle wrist or ankle range of motion, and keep blood flowing. Complete immobilization blunts the healing signal. I also avoid combining shockwave with corticosteroid injections within a four-week window. Steroids impair the very angiogenic response the therapy depends on. There are real limitations. Shockwave will not fix a full-thickness tendon tear. If your ultrasound shows a complete rupture or a significant retraction, sending that patient to a surgeon is the only responsible move. It also struggles with acute inflammatory tendonitis where the tissue is already swollen and hypersensitive. In those cases, loading management and anti-inflammatory strategies come first. Shockwave belongs to the chronic degenerative bucket, not the acute pain bucket. Contraindications you need to check before every session: pregnancy over the treatment area, coagulopathy or blood thinner use that raises bleeding risk, active infection, malignancy in the field, and growth plates in pediatric patients. I also avoid direct placement over major nerves and blood vessels. The radial probe is forgiving, but focused waves can cause damage if misaligned. An ultrasound image of the target tendon before treatment cuts down on guesswork and keeps the energy where it belongs.
Get the Full Details
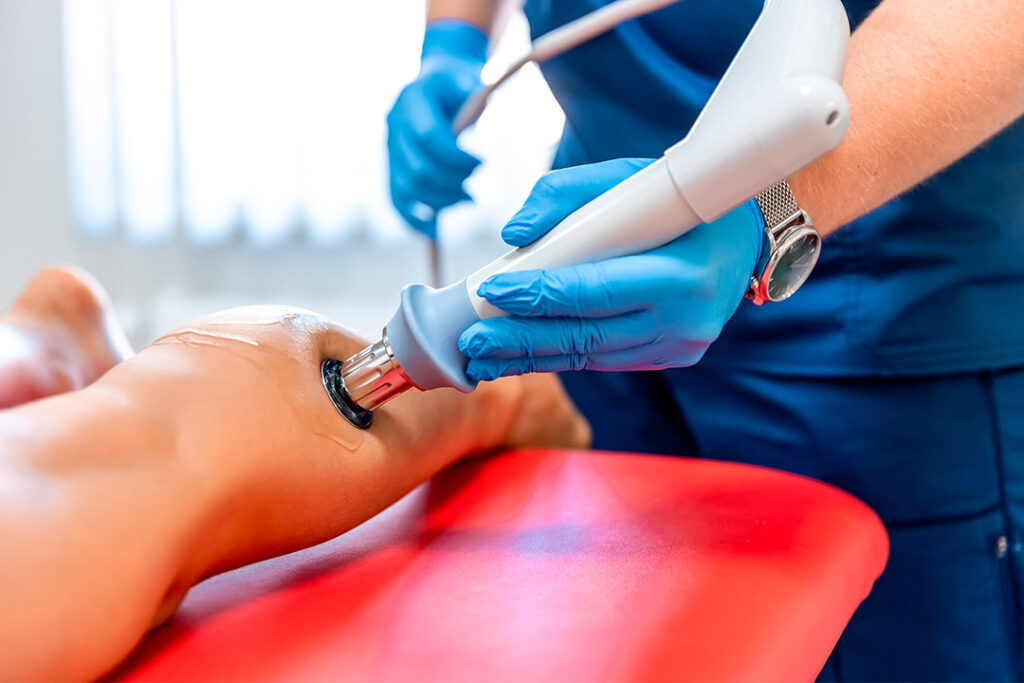
The evidence base is reasonably solid for specific indications. Lateral epicondylitis, proximal Achilles tendinopathy, plantar fasciitis, and calcific shoulder tendinitis all have decent randomized controlled trial support. Rotator cuff tendinopathy without impingement also responds well. Indications like patellar tendinopathy show mixed results in the literature, and hamstring insertions are still a gray area. Treat the condition, not the machine, and you will get better outcomes than following a rigid protocol. If you are setting up a clinic and deciding whether to buy a device, pick one with adjustable fluence, a clear pulse counter, and a warranty that covers the transducer. Transducers wear out. The coupling surface degrades after thousands of pulses, and output drops off even if the machine still displays the same numbers. I replaced my primary transducer after about 80,000 pulses. Output testing with a calibrated hydrophone should happen quarterly if your facility has that capability. It costs time but protects you from underdosing patients because of worn equipment. Patient selection is the biggest determinant of success. Chronic symptoms lasting more than three months, failed conservative care including a proper loading program for at least six weeks, and no structural tear on imaging. That is your sweet spot. Skip those criteria and you will wonder why the therapy did not work, when the real issue was treating the wrong stage of tendon disease.