Practical Notes on Using Shockwave for Nerve Repair
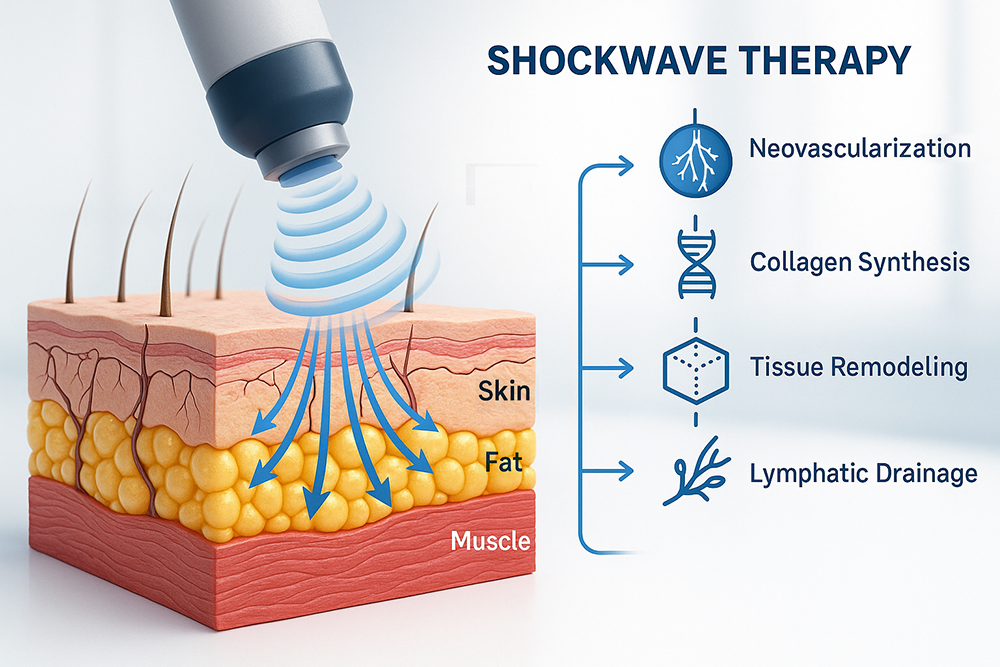
I spent about three years working with radial shockwave machines in a peripheral nerve clinic. Most people asking about this want to know if it can regrow nerves, and the honest answer is more complicated than the marketing materials suggest. The technology exists, the mechanism is understood at a cellular level, but clinical outcomes vary depending on a dozen variables most beginners don't account for. Shockwave Therapy Nerve Regeneration relies on low-intensity extracorporeal shockwave application to stimulate angiogenesis and modulate inflammatory signaling around damaged nerves. It doesn't magically reconnect severed axons. What it does is create a microtrauma response that upregulates vascular endothelial growth factor, nitric oxide release, and certain neurotrophic factors like BDNF and NGF in the local tissue environment. The nerve itself still needs structural continuity to regenerate along - the shockwave just makes the bed more favorable for that process.
How I Approach the Protocol
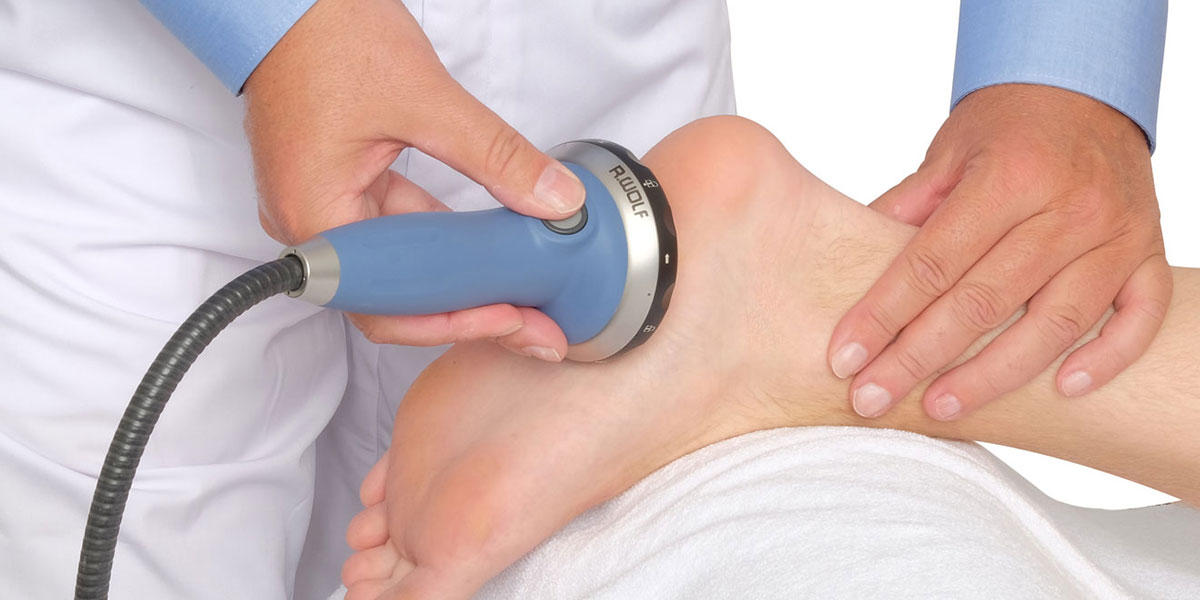
For mild compression neuropathies like superficial peroneal nerve entrapment or medial plantar nerve issues, I typically start at 2.0 bar with 2000 shots at 4 Hz frequency. That's moderate energy flux density, roughly 0.12 to 0.18 mJ/mm². You're not trying to ablate tissue here. The goal is sub-threshold mechanical stimulation of the endoneurium and perineurium. The application pattern matters more than most operators realize. Don't just blast the entire nerve path uniformly. I map the point of maximum tenderness first, usually where the nerve transitions from mobile to fixed tissue, and concentrate the initial passes there. Then I work proximally and distally in overlapping strips. Each strip gets about 200 to 300 shots. Total treatment time for a single session runs around 10 to 15 minutes for a relatively small nerve territory. Frequency of sessions: weekly for four to six weeks, then reassess. Some patients show measurable improvement in nerve conduction velocity by session three. Others don't show anything until six weeks out. The nerve regeneration timeline is fundamentally slow regardless of adjunct therapies. Schwann cell proliferation and axonal outgrowth at optimal conditions run roughly one millimeter per day in the best-case scenarios. That's theoretical maximum speed. Clinical reality is slower.
The Edge Case That Changed My Protocol
I had a patient with a chronic ulnar nerve neuropathy at the elbow, roughly eight months post-injury. Standard protocol produced minimal improvement after four sessions. Nerve conduction studies showed only a 5 m/s change in motor velocity, which is essentially within measurement error. I was about to write it off as non-responder territory when I noticed something during the ultrasound imaging that I'd overlooked before. The ulnar nerve wasn't just compressed at the cubital tunnel. There was a secondary bottleneck approximately three centimeters proximal where the nerve passed through a fibrous band connecting the medial epicondyle to the medial intermuscular septum. This wasn't on the standard anatomical diagrams. It's a variant most clinicians never check for. I redirected the shockwave energy to focus on that proximal band, applying higher intensity locally at 2.5 bar while reducing overall shot count to 1500 to avoid excessive tissue trauma in an already irritated nerve segment. By session six, the patient reported a noticeable decrease in paresthesia. By session eight, nerve conduction improved by 12 m/s on the motor branch. That's clinically meaningful. The lesson here is that shockwave therapy for nerve issues requires detailed sonographic mapping before you start shooting. Treating the textbook compression site without identifying anatomical variants means you're wasting sessions and potentially aggravating the nerve without addressing the actual bottleneck.
Get the Full Details
What the Literature Gets Wrong
Most published studies on radial shockwave and nerve repair use animal models with transection injuries followed by surgical repair. That's a fundamentally different scenario from compressive or traction neuropathies, which represent the majority of clinical presentations. The regeneration stimulus needed after a clean surgical coaptation is different from what a chronically compressed nerve needs. Compressed nerves have adapted structural changes, fibrotic investment, and altered hemodynamics that simply don't exist in acute transection models. There's also a misconception about energy levels. Higher isn't better for nerve tissue. I've seen operators crank machines up to 3.5 bar and wonder why patients get worse. Nerve tissue is mechanically sensitive. Excessive energy causes micro-edema within the fascicles, which increases intraneural pressure and worsens symptoms temporarily. The therapeutic window for nerve applications is surprisingly narrow. You're walking the line between sufficient mechanotransduction stimulus and iatrogenic nerve irritation. The counter-intuitive part: some patients with more chronic, longer-standing neuropathies actually respond better than acute cases. After about six to eight weeks of compression, the nerve develops metabolic changes that make it more responsive to the angiogenic and anti-inflammatory effects of shockwave. Acute compression under two weeks often resolves without intervention anyway. The chronic cases are where the technology adds real value because the spontaneous recovery trajectory has flattened out.
When It Completely Fails
Shockwave won't help if the nerve is completely severed with no surgical repair option. It won't help if there's a space-occupying lesion like a schwannoma or ganglion cyst causing the compression - you need to remove the physical obstruction first. It won't help in advanced diabetic polyneuropathy where the pathology is metabolic and systemic rather than focal. And it won't help if there's significant fascicular fibrosis that has replaced functional neural tissue. In those late-stage cases, the nerve is structurally incapable of regeneration regardless of what growth factors you stimulate. Contraindications include pregnancy over the treatment area, active infection, coagulopathy or anticoagulant therapy that can't be paused, malignancy in the treatment field, and over major vascular structures without ultrasound guidance. I always use ultrasound when treating nerves near the femoral triangle or popliteal fossa. The femoral artery is not something you want to accidentally subject to repeated shockwave pulses.
Combining With Other Approaches
The best results I've seen combine shockwave with structured nerve gliding exercises and sometimes low-level laser therapy in the same session. The shockwave creates the favorable biological environment. The nerve glides mechanically mobilize the regenerated tissue through its pathways, preventing adhesion formation. Doing them together takes about 25 minutes total and produces better functional outcomes than either modality alone in my experience. Some operators add topical nitric oxide donors or vitamin B complex supplementation to support the axonal growth phase. The evidence for this is mixed, but nothing harmful about it in most cases. The B vitamins at least address a common nutritional deficit in patients with chronic nerve issues who may have marginal status regardless of their presenting complaint. Follow-up assessment should include both clinical examination and nerve conduction studies at baseline, four weeks, and twelve weeks. Patient-reported outcome measures like the Patient-Reported Outcomes Measurement Information System for peripheral neuropathy give you objective tracking between visits. Relying solely on subjective reports misses subtle improvements that conduction studies can detect earlier.