How the Short Form Actually Works in Practice
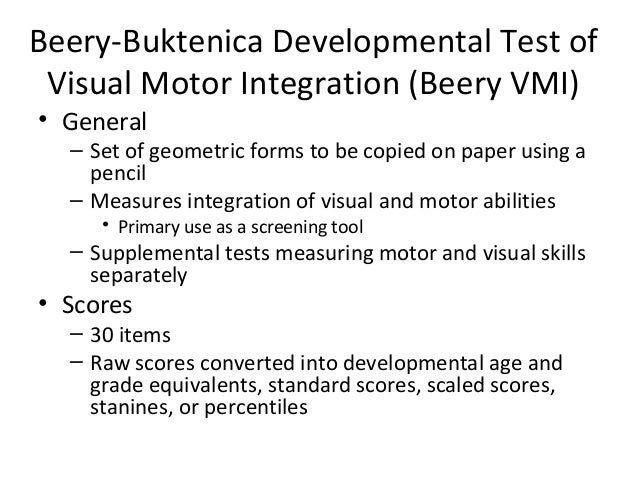
The Beery-Berkuteik Visual-Motor Integration, Brief Form gives you 15 items instead of the full 36. That sounds straightforward, but the scoring quirks trip people up more than the administration itself. The booklet shows each figure with a dashed-line copy model and a blank space underneath for the client. You mark what's right, what's wrong, and which specific errors occurred. The manual walks through it, but a lot of practitioners still miss the subtleties. Here is how I actually go through it every time. You administer the 15 figures in order. Each figure gets one point for a correct response. Then you look at the scoring sheet, which has error codes — spatial lapses, rotations, proportions issues, perseveration, omitted lines, extra details. You tally those separately. The raw score out of 15 becomes a percent correct, which you then convert to standard scores using the age-normed tables in the back of the manual. That is the whole mechanical process. The thing nobody emphasizes enough is the timing component. There is no time limit on the Brief Form, but you still need to record how long it took. If a client takes more than roughly 30 minutes on just 15 items, that is data in itself — not a standard score, but clinically meaningful information about visual-motor stamina and frustration tolerance. I usually note it right on the scoring sheet in the margin so it does not get lost in my notes later.
I ran into a real problem last year with a 10-year-old who produced near-perfect copies on almost every item but had consistent clockwise rotations on about half the figures. The standard error coding treats rotation as a single category, but the direction and consistency of the rotation actually mattered here. I flagged it as a specific qualitative error in my report rather than letting it dissolve into a generic rotation count. That distinction changed how I interpreted the profile entirely. It was not a pure visual-motor integration issue — it pointed more toward a spatial reasoning difference that the norm-referenced score alone would have smoothed over.
Common Scoring Pitfalls I See Repeatedly
The first mistake is conflating the full form and brief form norms. They are not interchangeable. The standard score tables are completely different between the two, and using the wrong table will give you numbers that mean nothing. I have seen this happen in clinic handoffs where someone pulls a brief form report and applies full form percentiles because they were in a hurry. It happens often enough that it bears saying twice. The second mistake is under-scoring qualitative errors. The manual provides a detailed error classification system, and skipping it to just count right and wrong is a shortcut that cost you most of the diagnostic value. A client scoring 12 out of 15 might look fine on paper, but if those three errors are all spatial misplacement rather than proportion errors, that pattern tells you something specific about where the visual-motor breakdown is occurring. The standard score alone cannot do that. There is also a boundary issue with the copy task that the manual does not address explicitly. When a client adds extra lines or modifies the figure in a way that is borderline between creative addition and error, you need a consistent rule. My approach is simple: if the addition changes the fundamental structure of the figure, it counts as an error. If it is decorative and the original structure remains intact, it does not. Write down that decision rule somewhere in your scoring notes so anyone reading your report knows your standard was applied consistently.
Get the Full Details

What the Brief Form Does Not Tell You
This is where I want to be blunt about limitations. The Brief Form cuts the items nearly in half, which means the standard error is larger. A difference of three raw points between two administrations could easily fall within measurement error rather than reflecting real change. If you are using this for progress monitoring or intervention outcomes, you need to look at confidence intervals, not just raw score changes. A raw score going from 10 to 13 on the Brief Form is not the same kind of meaningful gain you would interpret from the full form. Another limitation: the Brief Form does not include a separate visual-perceptual subtest the way the full battery does. If your referral question involves distinguishing between visual-motor integration deficits and broader visual-perceptual weaknesses, the brief form alone will not answer that. In those cases I supplement with the VMI Visual Perceptual portion or switch to the full form depending on what the clinical picture needs. No single score answers every question. The norms are also fairly old. The last major norming update was several years ago, and demographic shifts in the population mean the percentile ranks may not perfectly reflect current distributions. This does not make the test invalid, but it is worth noting when you are making high-stakes educational placement recommendations. The test is still widely used and accepted, but blind faith in the norm table without considering the child's specific context is where practitioners get into trouble.
Practical Setup for Scoring Efficiently
I keep a printed copy of the manual's scoring chapter as a bookmarked reference and use the error code chart on a laminated card at my desk. Going back to the full manual every time wastes about five to ten minutes per client, which adds up over a day of assessments. Having the quick-reference chart cut that down to under a minute per form. The investment in laminating a couple of pages was worth it on day one. When scanning or photographing completed forms for your records, make sure the images are clear enough that error markings are legible. I once had to rescore a form because the scanned copy showed a faint pencil mark that looked like an omission but was actually a smudge. The original booklet resolved the ambiguity immediately. Always keep the physical booklet until you have verified the scan quality, even if you think you will not need it. One final practical note: if you are administering this as part of a larger battery and the client is fatigued, consider whether the Brief Form is even appropriate that day. A tired client will not perform representatively on a visual-motor task, and no amount of careful scoring will fix a data set collected under poor conditions. I have ended up rescheduling assessments because the client was clearly drained halfway through a prior subtest. It delays things by a week, but it is better than having to explain a compromised score to a school team later.