Short Term Therapy Models
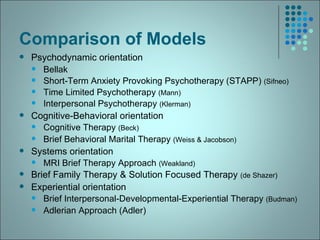
I've been working in clinical psychology long enough to see every trend come and go, and short term therapy models have been around in one form or another since the 1960s, but they still get misunderstood constantly. People treat them like a cheap shortcut to full-blown psychoanalysis, which is backwards. The reality is more nuanced and honestly more honest if you're actually doing this work. Let's start with what actually happens in the room. A short term therapy model typically runs between 6 and 20 sessions. You establish the problem early, you set concrete goals, and you work toward measurable outcomes. There is no aimless exploration of childhood trauma unless that trauma is directly blocking progress on the stated goal. That distinction matters because I have seen too many clinicians fumble it by drifting into open-ended territory and losing the structure that makes these models effective. The most common models are solution-focused brief therapy, brief psychodynamic therapy, and structured cognitive behavioral approaches. Each has its own rhythm. SFBT operates almost entirely in the present and future, asking clients to identify exceptions to their problems and build on what already works. Brief psychodynamic therapy identifies a core conflict pattern, usually interpersonal, and works through it over a compressed timeframe. CBT-based short term models are more skills-based and psychoeducational, teaching coping strategies and cognitive restructuring.
I ran into a specific case last year that exposed a real limitation most people don't talk about. A client came in with what looked like a straightforward panic disorder, perfect for a CBT short term protocol. Six sessions in, the panic was clearly lifting. But there was this underlying relational pattern that kept resurfacing in every discussion of coping skills. I had structured the treatment around symptom reduction, and the client was complying perfectly. The problem was that symptom relief alone was creating a secondary issue. Once the panic faded, the client felt guilty about not being distressed enough to justify seeking help from their family, who had been mobilized around the anxiety. The short term framework was too tight to address that. I extended two sessions into a metaposition discussion about the family system and the client's role in it. It wasn't dramatic, but it was the only way to prevent the symptoms from returning under a different guise. That experience changed how I approach these models. The limitation is real. Short term therapy models are not designed for complex comorbidity, severe personality pathology, or deep-seated relational trauma. They work best when the presenting problem is circumscribed and the client has sufficient ego strength to engage with directive interventions. If you try to force them into a case that doesn't fit, you get either incomplete treatment or early termination that looks like failure when it's actually misapplication.
Structuring a Short Term Course
Session one is where everything hangs or holds. I spend the first 20 minutes gathering history but I frame it differently than long-term work. Instead of a broad biopsychosocial interview, I ask three questions: what brings you here now, what would make this worth your time, and what have you already tried. The answers tell me everything I need to know about whether this client is suited for short term work. Clients who can articulate a specific goal and have some self-awareness about what hasn't worked are strong candidates. Clients who say "I just feel bad" with no sense of what changed or who to contact are not. By session three you should have a written treatment plan. I mean literally write it down and put it in front of the client. Something like "We will meet eight times. Our focus is social anxiety in workplace settings. You will practice exposure exercises between sessions and we will review progress at session five." This sounds rigid but it prevents the slow drift that kills short term work. I have lost count of the number of times a client and I ended up in session seven discussing the same thing we covered in session two because no one had set a deadline for that topic. The mid-point is critical. Around session five or six, I do a formal check-in using a brief measures battery. GAD-7 for anxiety, PHQ-9 for depression, or the specific measure tied to the presenting problem. If scores haven't moved at all, I either change technique or discuss termination. Staying the course with no measurable progress is a waste of everyone's time. I once had a client whose depression scores stayed flat across four sessions of behavioral activation. We switched to a behavioral experiment approach focused on testing the client's core belief that "nothing matters," and scores dropped significantly in the next two sessions. The model stayed the same. The technique shifted based on the data.
Get the Full Details
Termination And Aftercare
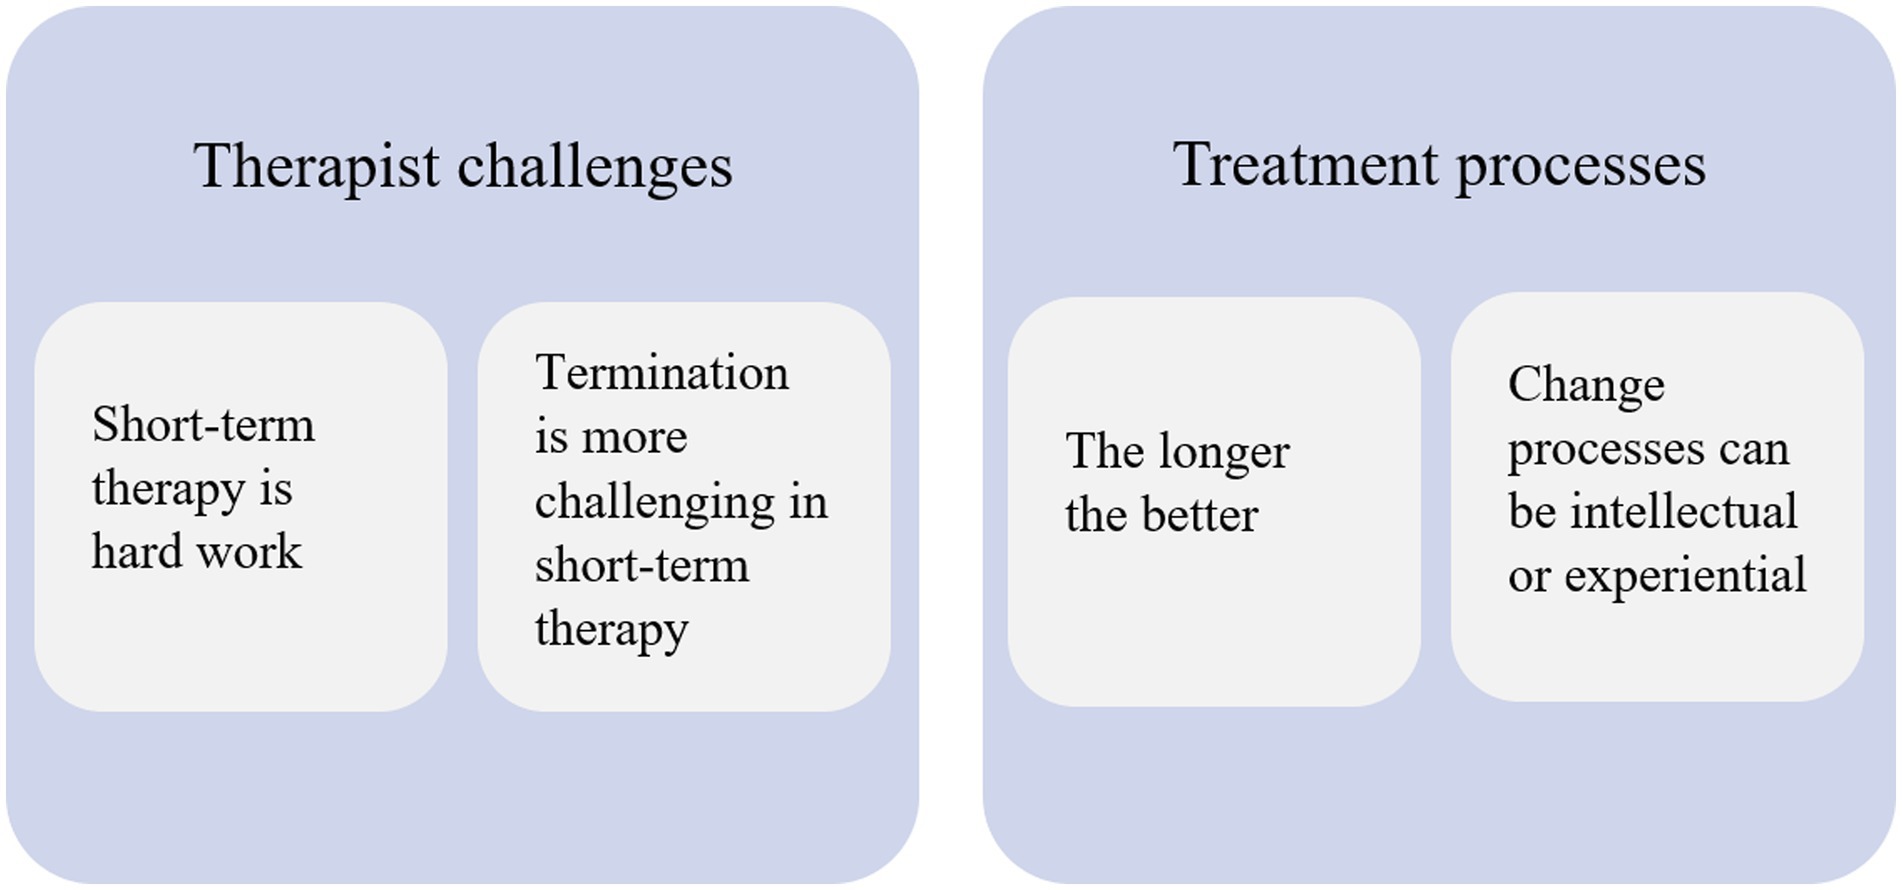
Termination in short term therapy is not an afterthought. It is the final therapeutic intervention. I schedule a dedicated session for wrap-up, usually the second-to-last or last session. We review what changed, what didn't, and what the client will do when things get hard again. I give them a one-page summary of the strategies we used, written in plain language, so they have something concrete to reference. Clients often forget the specifics under stress, and having that page makes a real difference in preventing relapse. The dropout rate in short term therapy models is higher than long term work, and that needs to be acknowledged honestly. Some of it is normal attrition. Clients get better and leave. Some of it is friction with the structured approach. Clients who prefer a more exploratory style often feel rushed or dismissed by the brevity. That is not a flaw in the model. It is a mismatch. The skilled clinician recognizes that mismatch early and refers out rather than pushing forward. I recommend short term therapy models for anxiety disorders, adjustment disorders, mild to moderate depression, grief, and specific phobias. I do not recommend them for borderline personality disorder, complex PTSD, active substance dependence, or cases where the client's primary need is attachment repair. Those require longer duration and a different therapeutic stance. Trying to shorten those treatments produces fragile gains that collapse once the structure is removed.
The research base is solid for the indicated conditions. Meta-analyses consistently show short term CBT and brief psychodynamic therapy producing effects sizes comparable to longer term treatment for the conditions I listed, with the added benefit of lower cost and faster access. The counter-intuitive finding that keeps coming up is that shorter does not mean worse when the fit is right. In some studies, highly structured short term protocols actually outperform open-ended therapy for specific diagnoses because the directionality forces engagement with the target behavior or cognition rather than allowing avoidance disguised as processing. What gets lost in the literature is the clinician's judgment call about when to deviate from the protocol. No model covers every edge case. I had a client with OCD who was making excellent progress on exposure and response prevention by session four, then suddenly started missing homework assignments without explanation. The protocol said to address noncompliance directly in session. Instead I asked a single open question about what was getting in the way, and the client revealed that a parent had been silently reinforcing the compulsions at home. We adjusted the exposure hierarchy to include parental presence and continued. The model held, but only because I was willing to bend the structure enough to address the new information rather than treating the missed homework as pure resistance. That flexibility within a time-limited frame is what separates competent short term work from rushed short term work. You are still bounded by the session limit, but you are not blindly following a manual. The structure is there to keep you focused, not to replace your clinical thinking.