Getting the Shoulder Moving When Everything Else Is Too Hard
Most people expect shoulder work to be the priority after a stroke, and honestly that is usually wrong. The hand and fingers get all the attention in therapy because recovery there is more visible, but the shoulder joint is where things go sideways fastest. I saw this happen to my own mother during her rehab. Her hand was improving by increments, but the shoulder started subluxing within weeks because nobody was managing it properly. By the time we caught it, she had developed a chronic pain pattern that set her back months. What most clinics don't tell you is that the shoulder is structurally unstable in hemiplegic patients because the muscles that normally hold the humeral head in the glenoid fossa simply stop firing. Gravity does the rest. Without active muscle control, the weight of the arm pulls the joint down and forward, stretching the capsule and ligaments until the shoulder sits lower on one side than the other. This is called subluxation, and it happens in roughly 50 percent of stroke patients if you just leave the arm hanging.
The Basics of Shoulder Exercises After Stroke
Shoulder Exercises After Stroke fall into three categories, and you need to understand which one applies to the patient before starting anything. Passive range of motion is when someone else moves the arm for the patient. Active-assisted is when the patient tries to move it with some help. Active is when the patient moves it alone. Each category has completely different purposes and timelines. Passive exercises start immediately, usually within days of the stroke, as long as the doctor clears it. The therapist or caregiver supports the elbow and wrist and gently moves the arm through forward flexion, abduction, and external rotation. The goal is not to strengthen anything, it is to maintain joint capsule elasticity and prevent adhesions from forming while the nerves heal. You are keeping the door from rusting shut while you wait for the person who opens it to come back. I learned the hard way that passive motion has a speed limit most people ignore. Move too fast and you risk capsular damage. Move too slow and you get nothing. The sweet spot is roughly one repetition per second, pausing at the end range for two or three seconds, then returning. Do not bounce or force through pain, because pain means you are already past the safe limit. After a stroke, the sensory feedback is unreliable anyway, so the therapist's hands need to be your eyes.
Active-assisted exercises come later, usually weeks or months in, once some voluntary movement returns. The patient uses their good arm to help move the affected one, or they use a pulley system overhead, or they do table slides with the palm flat against a slick surface. The key insight here is that the affected arm does not need to generate much force, it just needs to move through the correct path repeatedly. Neuroplasticity works through repetition and accuracy, not through effort alone. Active exercises are the final stage, and most stroke patients never reach them on the affected side. That is not a failure of the patient, it is a reflection of how severe the motor pathway damage was. When active shoulder movement does return, it is usually weak and poorly coordinated. The shoulder girdle muscles, especially the rotator cuff, fire out of sequence, which means the arm might lift but it might also hike up toward the ear instead of moving smoothly overhead.
Get the Full Details

Specific Exercises That Actually Matter
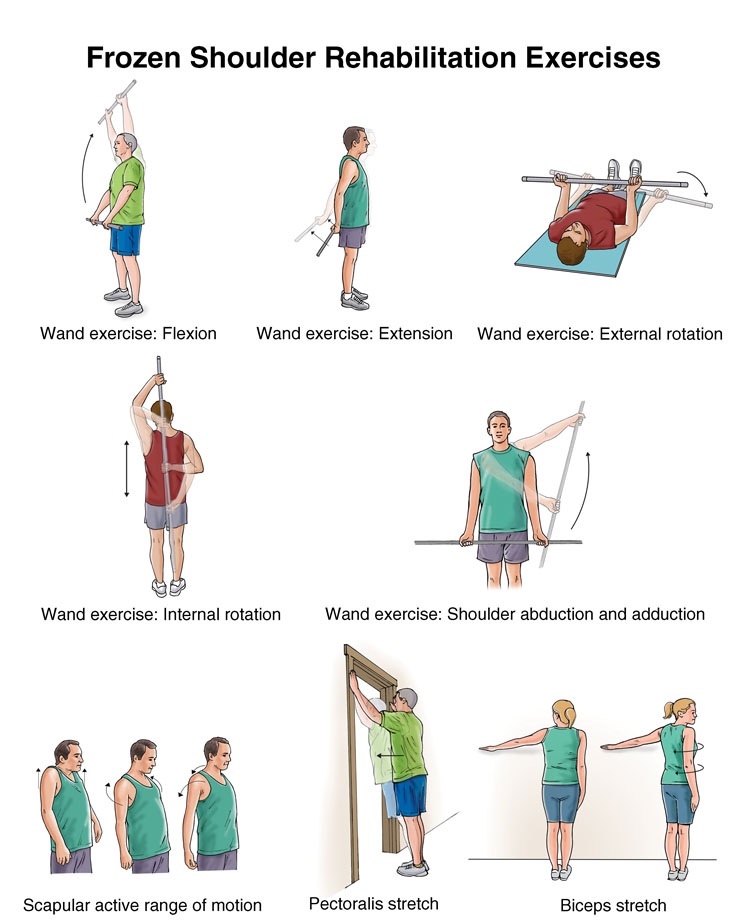
Forward flexion is the simplest and most important movement. Have the patient lie on their back with the arm at the side, or sit upright if they can manage balance. Support the elbow and gently lift the arm straight up toward the ceiling, stopping before any compensatory shrugging appears. The moment the shoulder blade starts hiking up, you have gone too far and the deltoid is cheating. Lower slowly. Five repetitions, twice daily, is plenty. More than that does not help and can irritate the joint. Scapular retraction and depression is an exercise most people skip because it does not look like a shoulder exercise. Sit or stand with the arms at the sides. Gently pull the shoulder blades down and back, as if trying to slide them into the back pockets. Hold for five seconds, release. This strengthens the lower trapezius and serratus anterior, which are the muscles that stabilize the scapula during arm movement. Without scapular stability, humeral movement is chaotic and painful. Twenty reps per day is a realistic target for most patients. Pendulum exercises, also called Codman exercises, are deceptively useful. Lean forward, supporting the good arm on a table, and let the affected arm hang down completely relaxed. Use gentle body momentum to swing the arm in small circles, forward and backward, and side to side. The circle diameter should start small, maybe six inches, and grow only as relaxation improves. This uses gravity to create gentle traction on the joint capsule without requiring any muscle activation from the affected side.
I ran into a specific problem with pendulum exercises that I never found in any textbook. Some stroke patients cannot actually relax the shoulder on the affected side, even when lying down. The spasticity pattern locks the arm in adduction and internal rotation, so swinging it around just yanks on already tight structures. The workaround was to first do gentle manual stretch in the opposite direction, holding the external rotation and abduction for 30 seconds before attempting pendulums. It sounded backwards at first, but the stretch reduced the tone enough that the pendulum actually worked instead of hurting. Table slides require a smooth surface and a towel or slipper under the hand. Lie on the back with the arm extended forward on the table. Slide the arm up toward the head, using body lean rather than shoulder effort to create movement. Keep the elbow straight but not locked, and stop before any sharp pain appears. This is one of the few exercises that combines weight-bearing through the joint with active movement, which provides both proprioceptive input and controlled loading at the same time.
What to Avoid
Do not pull on the affected arm. This sounds obvious, but it happens constantly in hospitals and homes. Caregivers grab the wrist or hand to reposition the patient in bed, to transfer them to a chair, or to guide them while walking. Every time you pull on a flaccid shoulder, you are stretching the inferior capsule and accelerating subluxation. Teach everyone who touches the patient that the arm must be supported at the elbow and forearm whenever it is moved, not grasped at the hand. Avoid forced overhead reaching in the early stages. Many rehabilitation programs push patients to touch their toes or reach high shelves as a goal, but a weak shoulder does not have the rotator cuff control to stabilize the joint at extreme ranges. Forced overhead movement without adequate scapular control is a direct path to impingement and rotator cuff strain. Work on horizontal plane movements first, where the joint is naturally more stable, before progressing to vertical planes. Sit-ups and crunches can aggravate the shoulder in stroke patients because the abdominal contraction pulls the rib cage down against an unsupported arm. If the affected arm is hanging at the side during core exercises, the weight of the trunk movement drags on the shoulder joint. Support the arm on a pillow beside the body, or bring it across the chest, before attempting any core work.

Equipment Options
Shoulder pulleys are the most common piece of equipment, and they work well for active-assisted flexion and abduction. A strap hangs from a door-mounted bar, and the patient uses their good hand to pull the strap, which moves the affected arm through the desired range. The pulley system essentially turns the good arm into a crane for the weak one. Cheap ones cost fifteen dollars, expensive ones cost sixty, and they all do the same thing. Buy the cheap one. Weights are generally not appropriate for early shoulder recovery after stroke. The concern is not the weight itself, it is the uncontrolled drop. A weak grip means the patient might let go mid-repetition, and the arm falling back to the side can yank the shoulder joint. If weights are used at all, they should be very light, half a pound to a pound, and only in the later stages when the patient has reliable motor control and can consciously release the grip on command. Sloping boards or waxed tables work well for table slides. The smooth inclined surface reduces friction enough that even minimal muscle activation can produce movement. This is particularly useful for patients who have almost no voluntary shoulder control, because it translates tiny amounts of force into visible motion, which provides important feedback to both patient and therapist about what the movement should feel like.
Timeframes and Expectations
Passive exercises begin immediately post-stroke, usually day two or three, assuming medical stability. Active-assisted work typically starts two to four weeks out, depending on when voluntary movement first appears. Active movement may take months, and some patients never achieve independent shoulder elevation on the affected side. The statistics are not encouraging here, roughly 60 percent of stroke survivors have persistent shoulder weakness at three months, and about 20 percent develop chronic shoulder pain within the first year. The timeline I have seen in practice varies enormously. A patient with a small lacunar stroke might regain active shoulder flexion to ninety degrees within six weeks. A patient with a large MCA infarct might never move the shoulder independently past thirty degrees. Both outcomes are normal. The rehabilitation approach should match the prognosis, not the other way around, so getting honest neuroimaging results early is essential for setting realistic expectations.
When Exercises Are Not Enough
If subluxation is already significant, or if pain is severe and persistent, exercises alone will not fix it. Glenohumeral subluxation greater than ten millimeters on X-ray, or shoulder pain that prevents sleep for more than two weeks, usually requires additional intervention. Taping or bracing can provide mechanical support while the tissues heal. Botulinum toxin injections into the pectoralis major or latissimus dorsi can reduce the spastic pull that is dragging the arm down and inward. Surgical suspension is rarely needed but has been described for chronic severe cases. The hardest truth about shoulder recovery after stroke is that prevention matters more than treatment. Once the capsule is stretched and the rotator cuff is damaged, those changes are largely permanent. The exercises described here are maintenance and rehabilitation, not reversal. Doing them consistently from day one, even when there seems to be nothing to work with, is the single most effective thing you can do for long-term shoulder function.