Understanding the Protocol
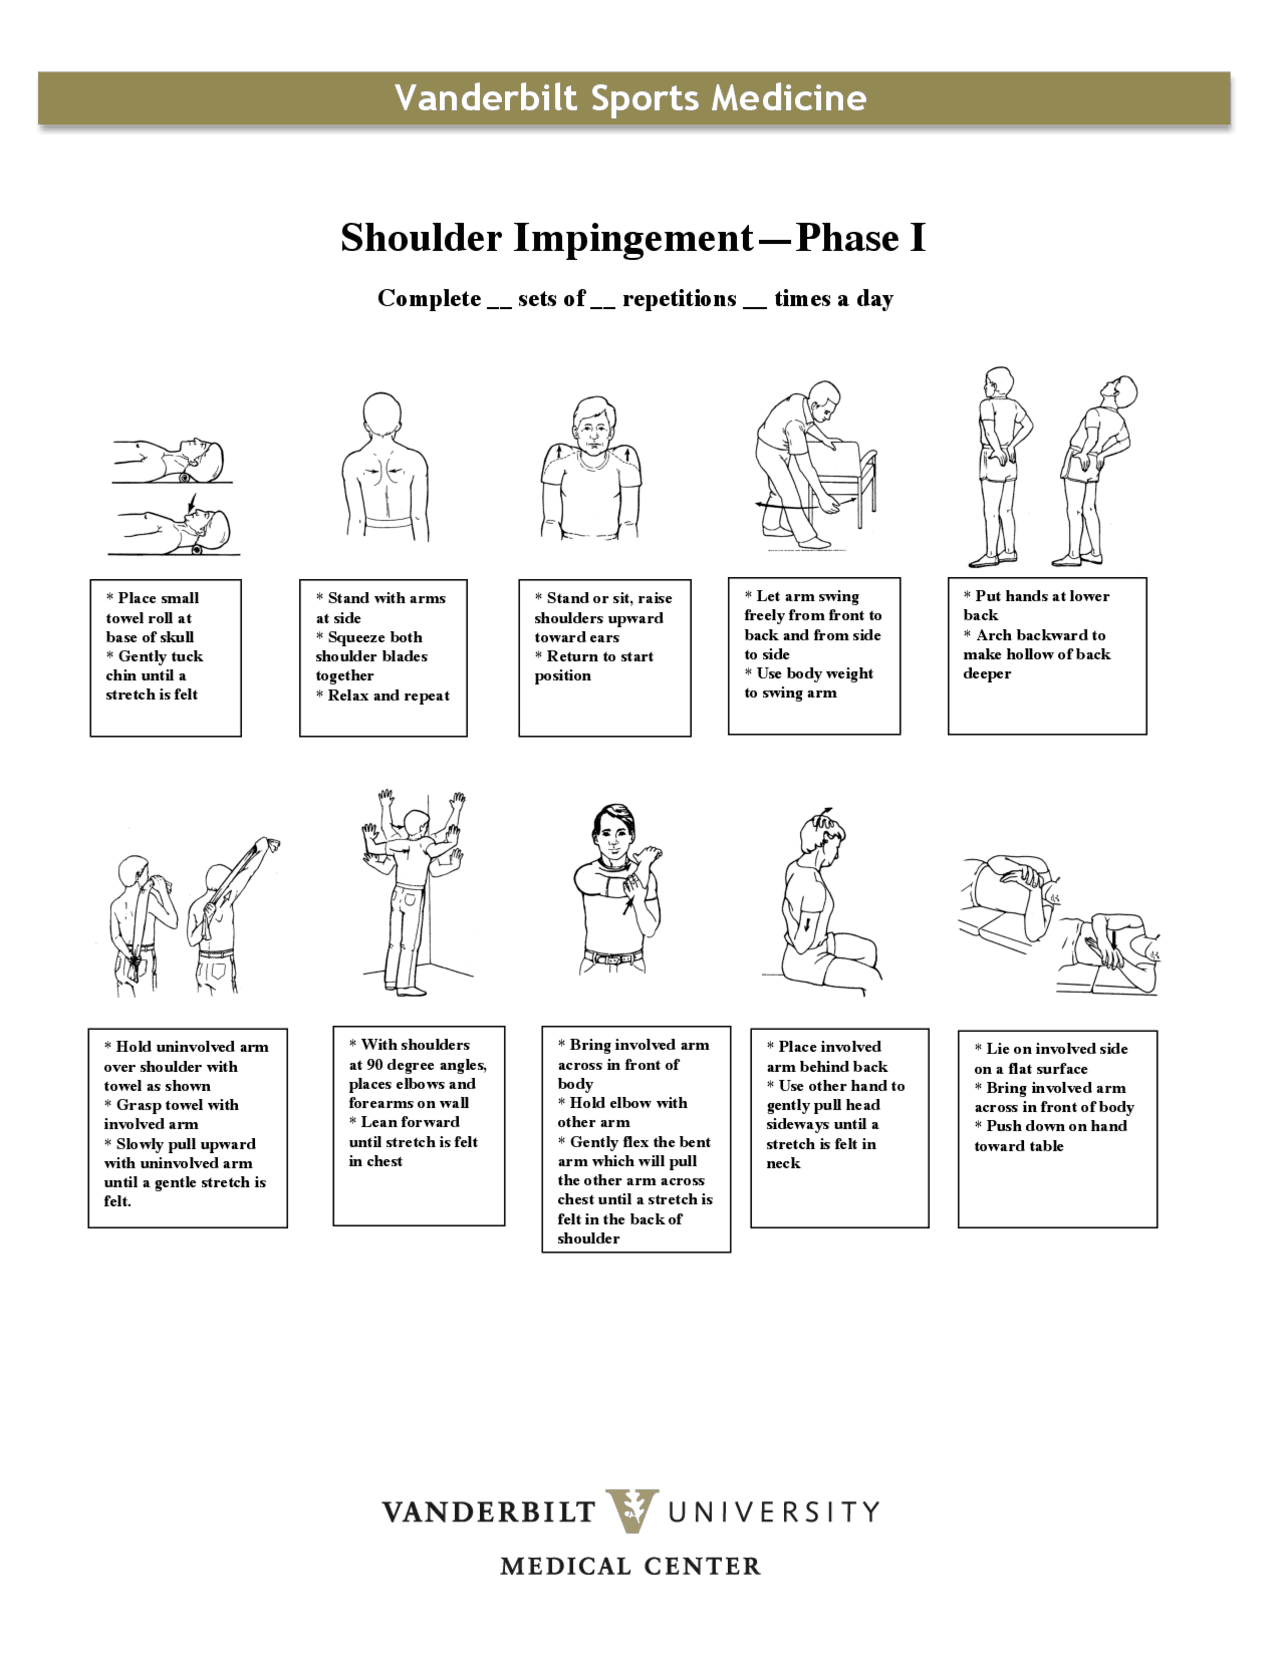
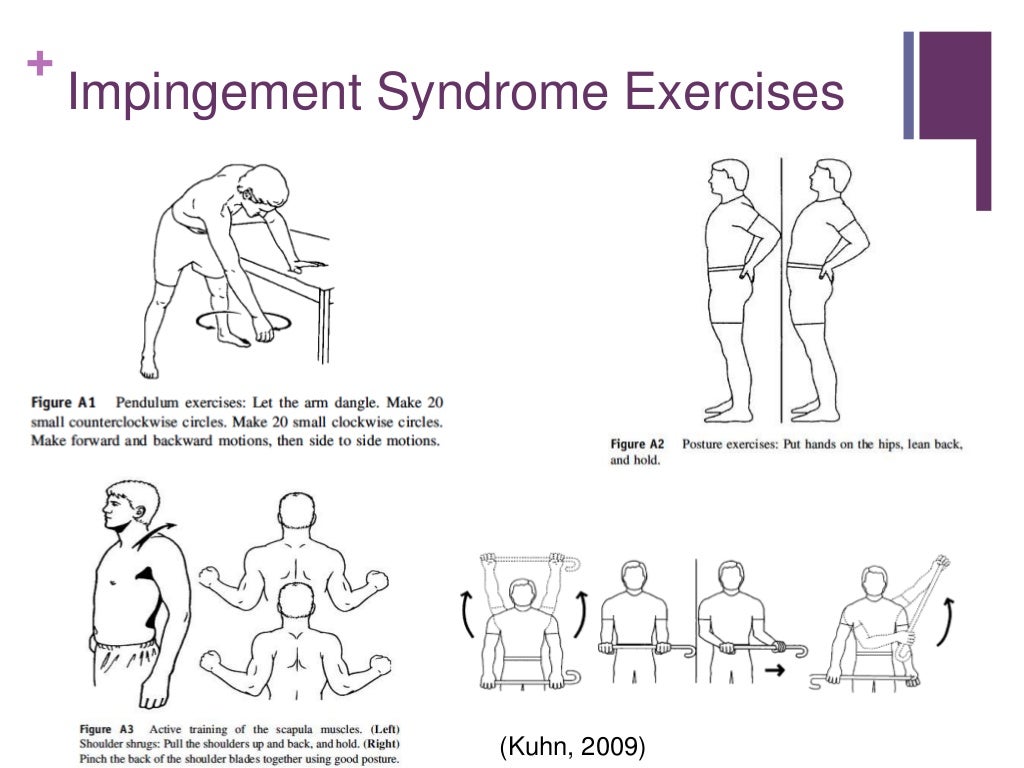
Most people with shoulder impingement don't actually have a structural pinching problem anymore. The research has shifted hard away from purely subacromial decompression as a first-line treatment. What we're really dealing with is a combination of rotator cuff tendinopathy, scapular dyskinesis, and often some glenohumeral joint hypomobility that creates secondary symptoms. The physical therapy protocol I use has been through roughly 6-8 weeks typically, and it's more about loading capacity than stretching or foam rolling for half an hour daily. The core of it starts with isometric loading of the rotator cuff in positions that are pain-free. That means external rotation and internal rotation isometrics against a wall or towel, held for about 30-45 seconds, 3-5 reps each. We do that at the beginning of every session because it tends to reduce pain acutely - probably through some neurophysiological mechanism rather than anything structural. After that, we move into scapular setting work: prone Ys, T's, and then later loaded scapular retraction with resistance bands. Not heavy yet. You want the serratus anterior and lower traps firing before you overload anything. Here's something most beginners miss: the humeral internal rotation deficit is usually the thing that sets off the cascade. Limited internal rotation at the glenohumeral joint posteriorly means the humeral head rides up during overhead motion. So posteroinferior capsule stretches and cross-body adduction mobilizations matter way more than people think. I'll do a sleeper stretch for 2 minutes and then immediately follow up with some posterior capsular rocking with the patient side-lying. Takes about 5 minutes total but it changes the mechanics for everything else.
The Loading Progression
Once basic pain comes down to a manageable level, usually within 2-3 weeks if the person's consistent, we start loading the rotator cuff dynamically. Side-lying external rotation with light dumbbells - 2-5 pound range, sometimes even just water bottles. Three sets of 12-15 reps, every other day. Scaption raises in the scapular plane with those same light weights, stopping where it starts to feel like it should hurt but doesn't quite cross that line yet. And reverse flyes for the rhomboids and mid-traps. These aren't glamorous exercises but they build the actual capacity needed for daily life. The part I see most people skip is the proximal strengthening around the shoulder girdle. You'd be surprised how often someone has decent arm strength but zero trunk or scapular control. Pallof presses, bird dogs, dead bugs with a deliberate focus on keeping the shoulder blades stable while the limbs move. This isn't rehab fluff. I had a patient - warehouse worker, late 40s - who came in with what looked like textbook impingement but was actually holding her shoulder up toward her ear every time she reached. Scapular upward rotation was barely firing. Once we added serratus punches and wall slides with a band around the forearms, the whole picture changed faster than with any single intervention alone.
Common Pitfalls I See Regularly
One major mistake is stretching the posterior capsule too aggressively without addressing the weakness underneath. Sleeper stretches can actually make things worse if the rotator cuff isn't stabilizing properly. I recommend controlling the stretch through the end range with isometric holds instead of just forcing passive mobility. Another pitfall is rushing the overhead loading. Full-can empty-can debate aside, getting someone to 90 degrees of forward flexion with weight too early is a fast track back to square one. The tendon doesn't care about your motivation. There's also the issue of cervicothoracic involvement. A stiff mid-back or weak deep neck flexors can absolutely perpetuate shoulder symptoms. I routinely assess cervical rotation and upper thoracic extension because restrictions there change scapulohumeral rhythm enough to matter. It's not always the root cause but it's frequently a contributing factor that gets ignored when the focus stays entirely on the shoulder joint itself.
Get the Full Details

What This Protocol Won't Fix
I need to be blunt about limitations. This approach works well for most cases of soft tissue impingement and rotator cuff tendinopathy in the 80% or so of patients who don't have a significant structural lesion. It does not reliably fix a large full-thickness tear, advanced osteoarthritis with joint space narrowing, or a true osseous impingement like a type III acromion with significant bone-on-bone mechanics. In those cases, referral for imaging and surgical consultation is the appropriate next step, not more isometric holds. Another scenario where this falls apart is when the dominant issue is glenohumeral instability masquerading as impingement. People with multidirectional laxity can get caught in a cycle of excessive humeral head translation that mimics impingement symptoms but responds very differently to treatment. If you notice apprehension tests are positive or the patient reports a sense of looseness or shifting during certain movements, that changes the entire clinical picture and the protocol needs adjustment accordingly.
Practical Implementation
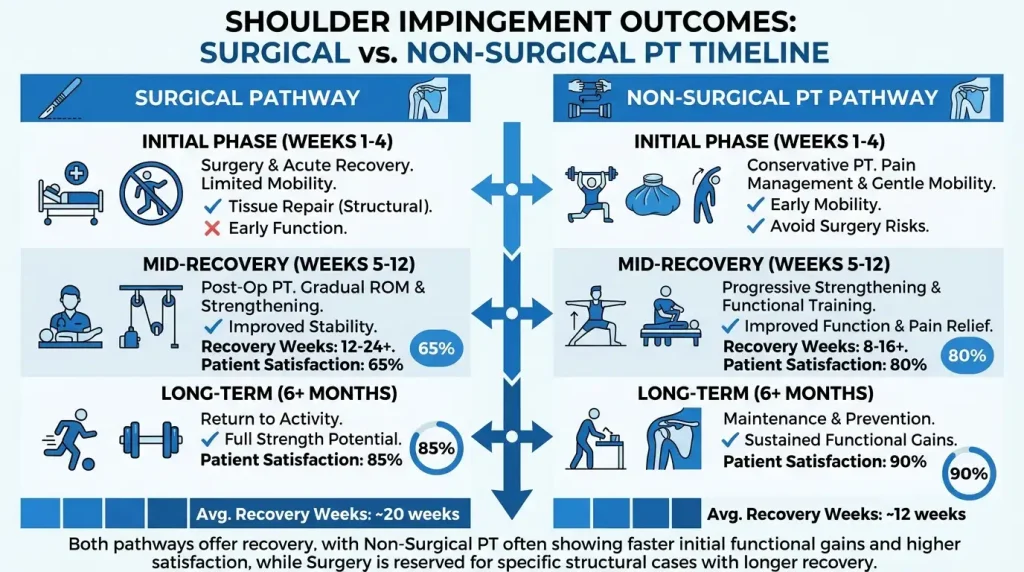
For someone working through this on their own between sessions, the minimum effective dose is roughly 15 minutes daily. Five minutes of isometrics and gentle mobility work, ten minutes of the strengthening exercises I mentioned. Doing it every day rather than every other day accelerates tendon adaptation. Progression is usually adding about one pound per week to the resistance work if the pain stays below a 3 out of 10 during and after the session. That's the threshold most patients can handle without setting themselves back. Return to overhead activities, sports, or heavy labor typically takes eight to twelve weeks of consistent work. Some people get there faster, some slower, and the timeline depends heavily on the original tissue damage level and how well they adhere to the progression. The ones who try to rush it almost always regret it. Patience here isn't optional - it's the entire intervention.