How Shoulder Replacement Protocol Physical Therapy Actually Works
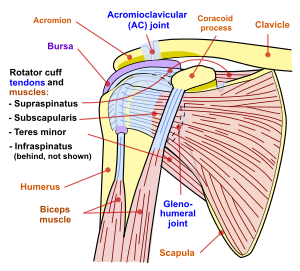
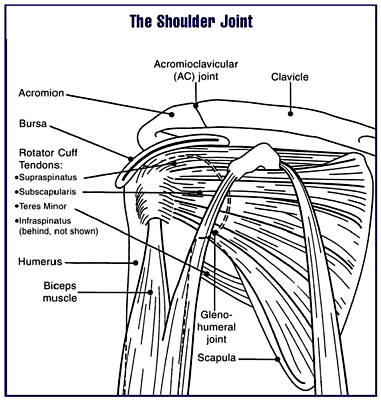
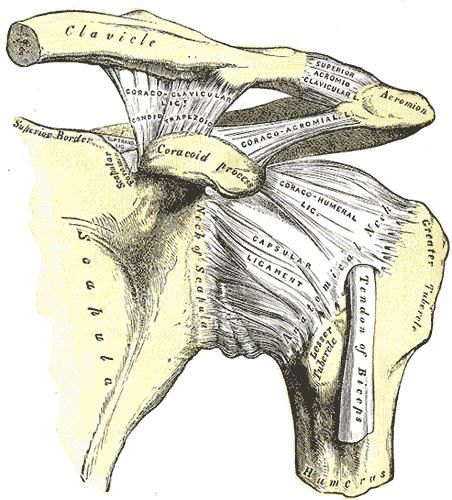
Most people think PT after shoulder replacement is just stretching and exercises. It's more structured than that. The protocol breaks into three phases with clear milestones, and skipping or rushing any of them is the fastest way to end up with a frozen shoulder or a prosthetic that doesn't track right. The first phase runs roughly weeks zero through six. Your surgeon will give you a sling to wear, and you'll be told not to actively lift the arm. What you're supposed to do instead is passive range of motion. A physical therapist or your own good arm moves the surgical shoulder through its motions. Flexion, abduction, external rotation—all passive. The goal here is preventing adhesions without stressing the healing capsule and the tendon repairs if you had a rotator cuff procedure attached to the replacement. I ran into a patient a while back whose surgeon did a reverse shoulder replacement combined with a subscapularis repair. The standard protocol says protect the subscap for six weeks. But this guy was genuinely struggling with edema and early stiffness because he'd been too aggressive with pendulum exercises on his own. He'd turned a week-two situation into a week-four problem. The workaround was straightforward: we dropped the pendulums entirely, switched to table slides with the arm supported, and used gentle manual posterior capsule mobilizations instead. By week six his range was where it should have been at week four. He just needed less movement, not more.
Phase two is roughly weeks six through twelve. This is where active motion starts. The sling comes off during the day, usually. You begin active-assisted then fully active range of motion. Strengthening is light at first—theraband work, light weights, scapular control exercises. The counter-intuitive part most people miss is that external rotation is often the last thing to come back, and it's also the most critical for functional use. Patients will push hard on flexion and abduction because those feel more natural, then neglect external rotation until it's a real problem. You want to treat ER with the same seriousness from day one of phase two. Phase three goes from about three months onward. This is strengthening and return to activity. Heavy resistance comes in gradually. The timeline depends on whether you had an anatomic or reverse replacement, your age, bone quality, and whether the cuff was intact or deficient. Most people are doing full activity by four to six months. Some take longer. It's not a hard deadline, and pushing through pain at this stage is how you irritate the insertion sites or strain the deltoid on a reverse replacement. One practical detail that isn't in the brochures: scapular dyskinesis is a common problem after shoulder replacement, especially with reverse designs. The deltoid gets lengthened and the scapula doesn't sit right. If you're doing PT and your shoulder still feels unstable or weak at eight weeks, check the scapula before you add more resistance. A couple of prone Y raises and serratus punches can make more difference than another set of bicep curls.
Another thing nobody warns you about is sleep disruption. The first six weeks of poor sleep are normal. Not because of pain alone, but because the shoulder is awkwardly positioned and any roll onto it wakes you up. It affects recovery more than people realize. Cortisol stays elevated, tissue repair slows down. I had a patient who kept dismissing the sleep issue until I pointed out her progress had plateaued at week three. Once we adjusted her sleeping position with a wedge pillow and a pillow hugged to the chest to keep the arm supported, her range improvements picked back up the following week. Small change, noticeable difference. There are downsides to following the protocol too rigidly though. Some surgeons insist on six full weeks of sling immobilization regardless of the patient's progress. For a low-demand older patient with good bone and an intact cuff, that might be reasonable. For someone younger and more active, six weeks of complete immobilization can lead to significant stiffness that takes extra months to resolve. In those cases, early controlled motion under guidance can be safer than the alternative of dealing with a frozen joint later. Talk to your therapist and surgeon about your specific situation instead of assuming the protocol is one-size-fits-all. The biggest mistake I see patients make is stopping PT once they feel better. Feeling better and being ready for normal activity are two different things. The soft tissues around a shoulder replacement need months of progressive loading to adapt. If you stop at twelve weeks and go back to manual labor or overhead sports without the strength to support the joint, you're asking the prosthesis to handle forces it wasn't designed for in that position. Keep going until your therapist clears you, not until you feel fine.
Get the Full Details