Reading Shoulder Radiographs Without Losing Your Mind
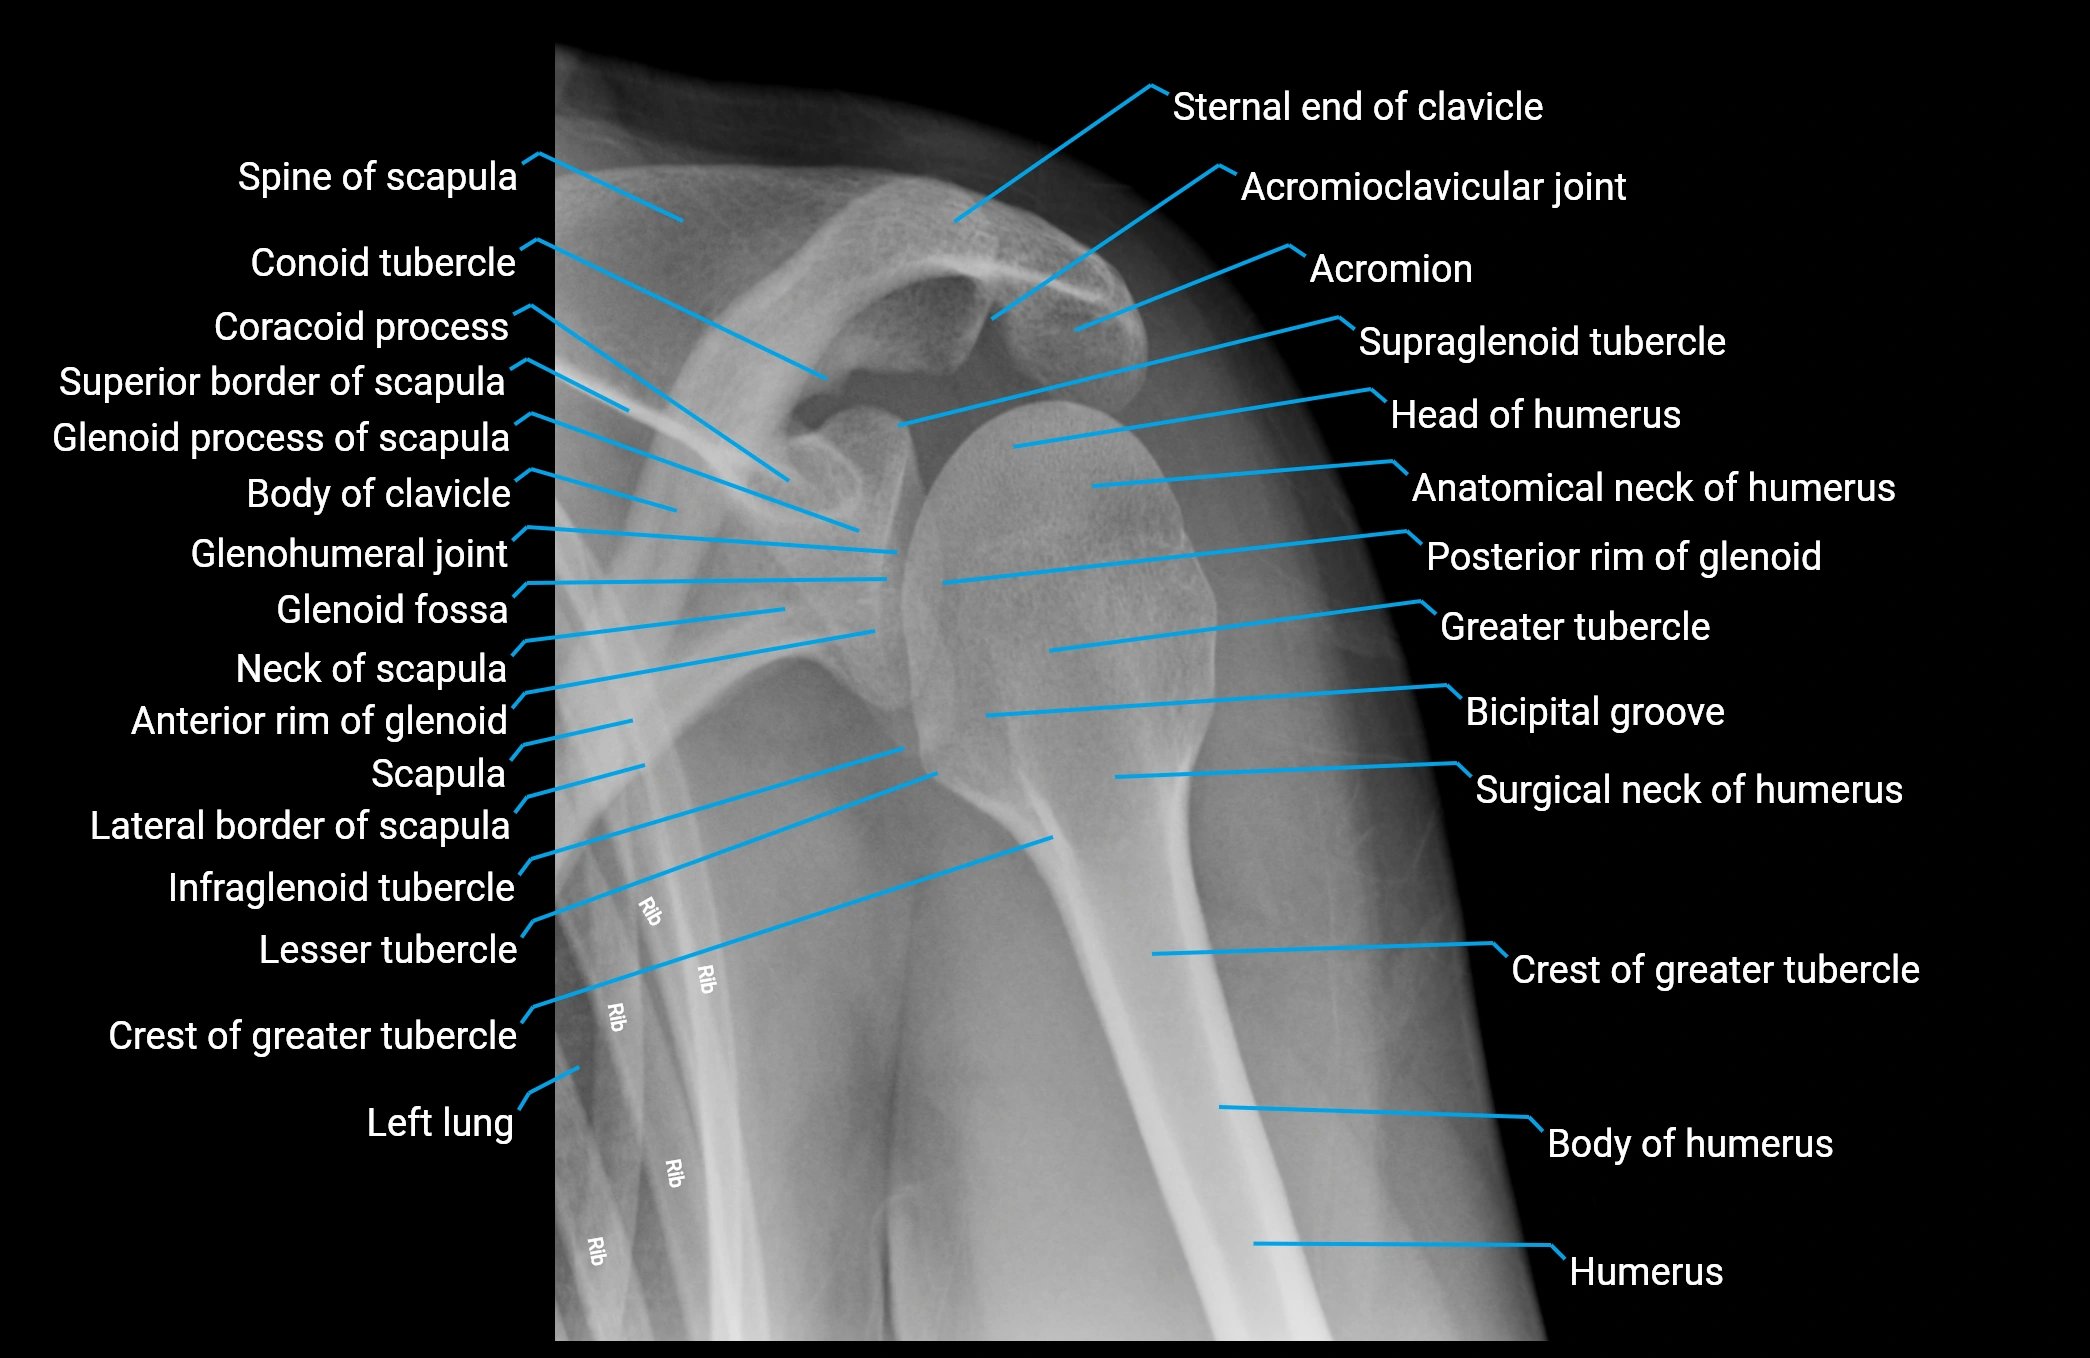
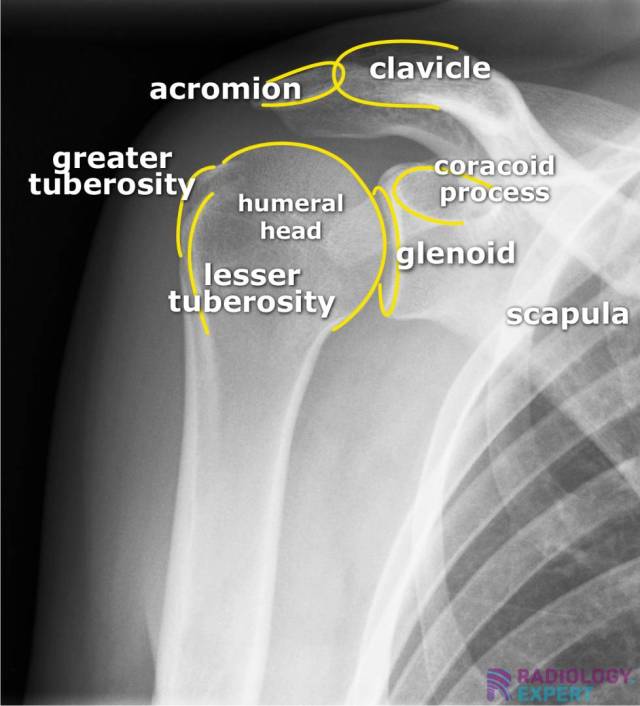
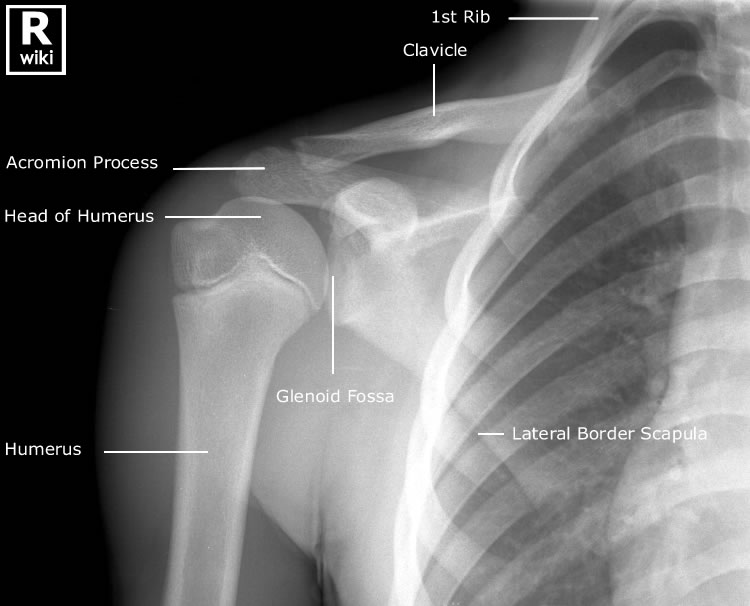
Most people learning radiographic anatomy start by memorizing labels. That approach falls apart the moment you see a real film with pathology present. What actually works is understanding relationships between structures and knowing where things hide from view. I spent years watching junior staff miss fractures because they were looking for textbook anatomy on films that never look like textbooks.Let us talk about the standard shoulder series first. You will get three views: true AP, scapular Y, and axillary lateral. That is the baseline. Anything less and you are flying blind. The AP shows the glenohumeral joint space, the humeral head contour, and the acromioclavicular joint. The scapular Y reveals anterior or posterior dislocations that the AP can easily miss. The axillary view maps the relationship between the humeral head and glenoid most clearly. I have seen too many posterior dislocations slip through because someone only ordered an AP and called it sufficient. On the AP view, focus on the articular surface of the humeral head. It should be smooth and oval. Any flattening, step-off, or irregularity suggests something happened there. Look at the greater and lesser tuberosities as landmarks for rotator cuff insertions. The supraspinatus attaches to the superior facet of the greater tuberosity. The subscapularis sits on the lesser tuberosity. Fractures here are easy to miss if you do not know exactly where to look. A minimally displaced greater tuberosity fracture can look almost normal on a single AP projection. The glenoid rim is where the real trouble lives. Anterior-inferior labral fractures, the so-called bony Bankart lesions, show up as a chunk of bone missing from the glenoid face. On a good AP, you should see a complete curved rim. If that curve breaks, something tore off. I had a case once where a young athlete had recurrent anterior instability but every radiograph looked normal. The CT arthrogram three weeks later showed a 4-millimeter bony defect thatplain films had completely obscured. Do not trust a single negative X-ray to rule out glenoid pathology.
The acromion deserves attention too. Type II and Type III acromions have a hooked shape that narrows the subacromial space. This is not just an anatomical fact, it correlates strongly with rotator cuff disease. Measure the acromiohumeral interval on the AP view. Normal is between 7 and 14 millimeters. Below 7 millimeters suggests significant rotator cuff tears allowing the humeral head to migrate upward. I once read a film where the interval was approximately 3 millimeters. The patient had been treated conservatively for months with no improvement. The MRI confirmed a massive supraspinatus tear. That measurement on a plain X-ray would have saved them eight months of ineffective treatment. The coracoid process is another structure beginners consistently confuse. It overlaps the humeral head on the AP view and can look like a fracture line if you do not know its normal position. The coracoclavicular ligaments attach just medial to the coracoid base. Distal clavicle fractures near the acromioclavicular joint require careful comparison with the opposite side. I routinely order a Clagett view, which is just the AP rotated 30 to 40 degrees caudally, to better separate the coracoid from the humeral head. This simple positioning tweak resolves about half the confusion I see in busy departments. Scapular Y positioning requires the patient to be upright or semi-erect with the arm at their side. The beam enters anteriorly and exits posteriorly. The scapular body forms the vertical limb, the acromion the upper arm, and the coracoid the lower arm of the Y. The humeral head should sit centered within this Y. If it sits anterior to the Y body, you have an anterior dislocation. If it sits posterior, the humeral head may be sitting behind the glenoid. Posterior dislocations are notoriously difficult to detect. About 90 percent of them are missed on initial presentation according to the literature, and a significant portion of those misses happen because the axillary view was not obtained or was technically inadequate.
One thing I want to emphasize that nobody teaches properly: the oblique angles matter more than you think. The internal rotation view, where the patient rotates the arm so the lesser tuberosity faces anteriorly, shows the greater tuberosity in profile. This is critical for detecting greater tuberosity fractures that are not displaced but angulated. External rotation, with the arm out to the side and the hand supinated, opens up the greater tuberosity and the humeral head contour. Both views are part of a complete shoulder series and neither should be skipped unless the patient cannot tolerate the positioning. And even then, you should document why you did not get them. Let me address the limitation of plain radiography directly. X-rays are two-dimensional projections of three-dimensional structures. Overlap is unavoidable. The humeral head partially covers the glenoid. The coracoid overlaps the proximal humerus. The acromion superimposes over the joint space. This is why a normal X-ray does not equal a normal shoulder. Cartilage is invisible. Labral tears are invisible. Early osteonecrosis may not show for weeks. Muscle atrophy is only detectable when it is advanced. If clinical suspicion remains high after a negative X-ray, moving to ultrasound or MRI is not optional, it is standard of care. A specific edge case I encountered involved a 62-year-old woman with persistent lateral shoulder pain. Her X-rays were read as normal three separate times. The humeral head looked fine. The joint space was preserved. The acromion was type I. Everything appeared unremarkable. I repeated the imaging with a modified Y-view at a slightly different angle and caught a subtle 2-millimeter impaction fracture in the lateral aspect of the greater tuberosity that was only visible when the projection shifted enough to unmask it. The initial readings were not negligent, the anatomy was just hiding. This happens more often than anyone admits, especially in osteoporotic bone where fracture lines are faint and comminution is subtle.
Get the Full Details
When evaluating the proximal humerus for fractures, use the Neer classification system. It divides the humerus into four segments: the humeral head, the greater tuberosity, the lesser tuberosity, and the surgical neck. Two or more segments displaced more than 1 centimeter or angulated more than 45 degrees classifies it as a four-part fracture. This classification drives treatment decisions and has prognostic value. A displaced four-part fracture in an elderly patient carries a significant risk of avascular necrosis because the blood supply to the humeral head gets disrupted. The arc of Songcharoen on the AP view, which traces the inner margin of the greater tuberosity to the humeral head, should remain continuous. A break in that line indicates a fracture regardless of displacement. The distal clavicle deserves its own section because pathology there mimics so much else. The CC ligaments insert 1 centimeter medial to the articular surface of the acromion. fractures or separations lateral to this point are commonly missed because they do not involve the ligamentous anchors. Rockwood type I and II AC joint injuries look nearly identical on X-ray. Both may show minimal widening. Clinical examination, specifically the cross-body adduction test and palpation of the AC joint, differentiates them. Imaging alone cannot do that job. If you need a downloadable reference for quick review, most radiology departments have institutional cheat sheets available on their intranets. Radiopaedia.org also maintains free, well-illustrated articles on shoulder radiographic anatomy that are updated regularly. University hospital radiology departments often publish patient-facing educational materials that are accurate and detailed enough for clinical use. Avoid relying on commercial anatomy apps that were last updated five or more years ago, because imaging protocols and classification systems evolve.
The bottom line is practical. Learn the normal variants first so you stop second-guessing yourself on things that are simply asymmetric. Then learn the pathology patterns. Most shoulder fractures follow predictable mechanisms. Anterior dislocations account for 95 percent of all shoulder dislocations. Posterior dislocations are associated with seizures and electrocution. Inferior dislocations, also called luxatio erecta, are rare but dramatic and obvious on the X-ray. Understanding mechanism helps you know which view to prioritize and what to look for specifically. Order the right series. Read the films systematically. Acknowledge what X-rays cannot show. That is the entire workflow.