Working With Iron Inclusions on Peripheral Smears
I spent three years doing peripheral blood smear reads before I stopped second-guessing myself on iron-containing granules. The problem isn't that the concepts are hard. It's that every textbook writes them slightly differently, and the naming convention shifts depending on which staining method you're using that morning. Here's the straight version of Siderotic Granules Vs Pappenheimer, the way we actually deal with it in the lab.
Siderotic Granules Vs Pappenheimer: What They Actually Are
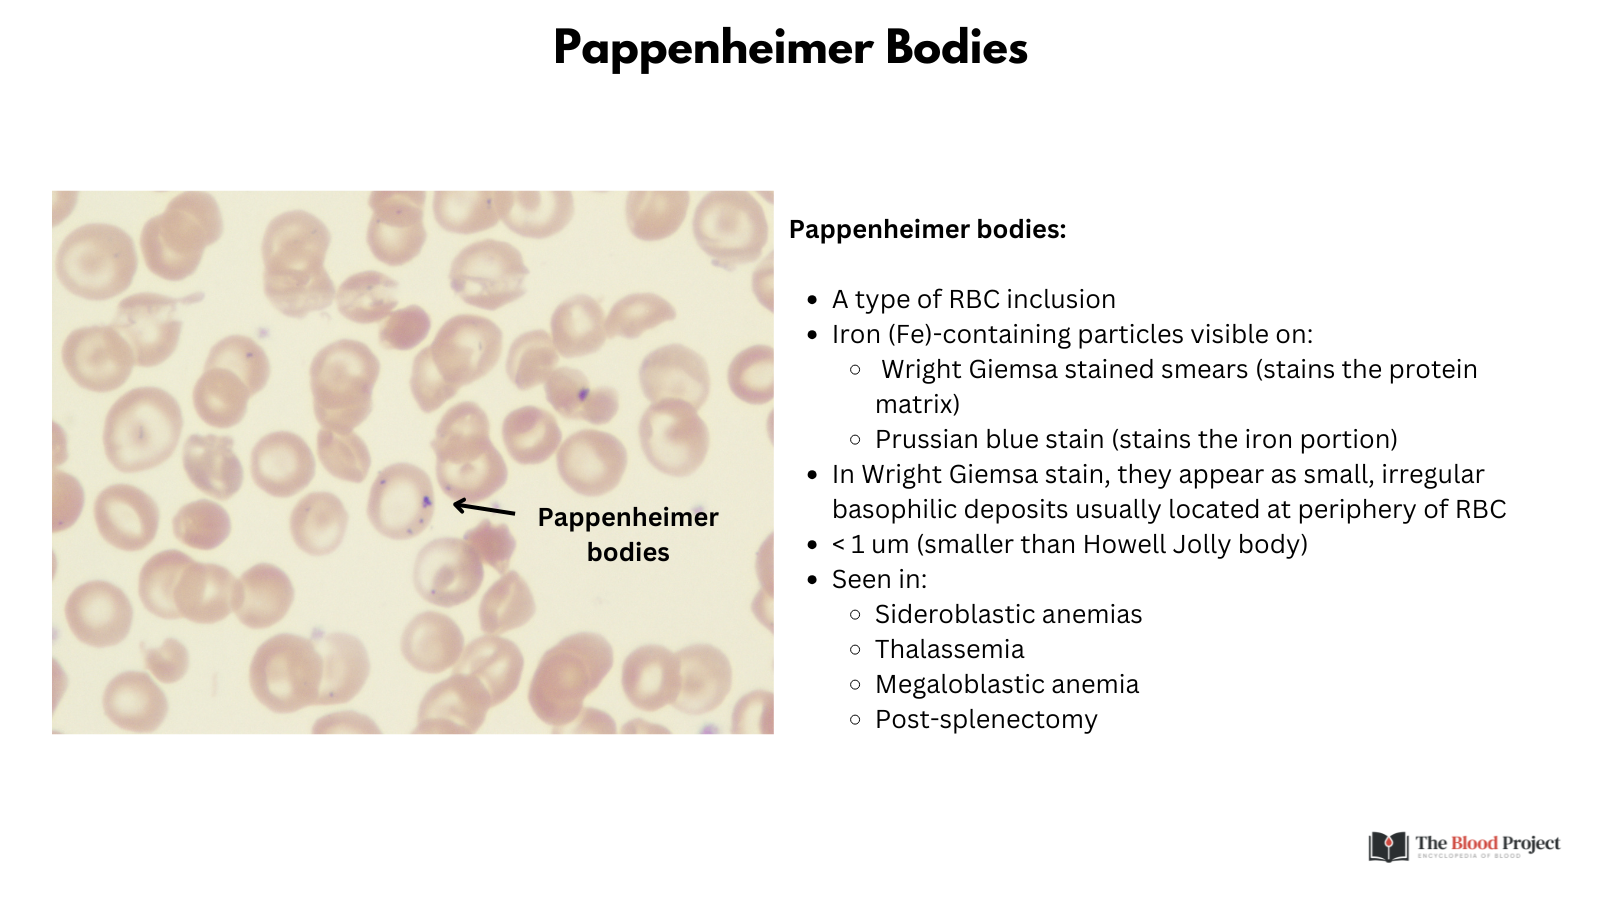
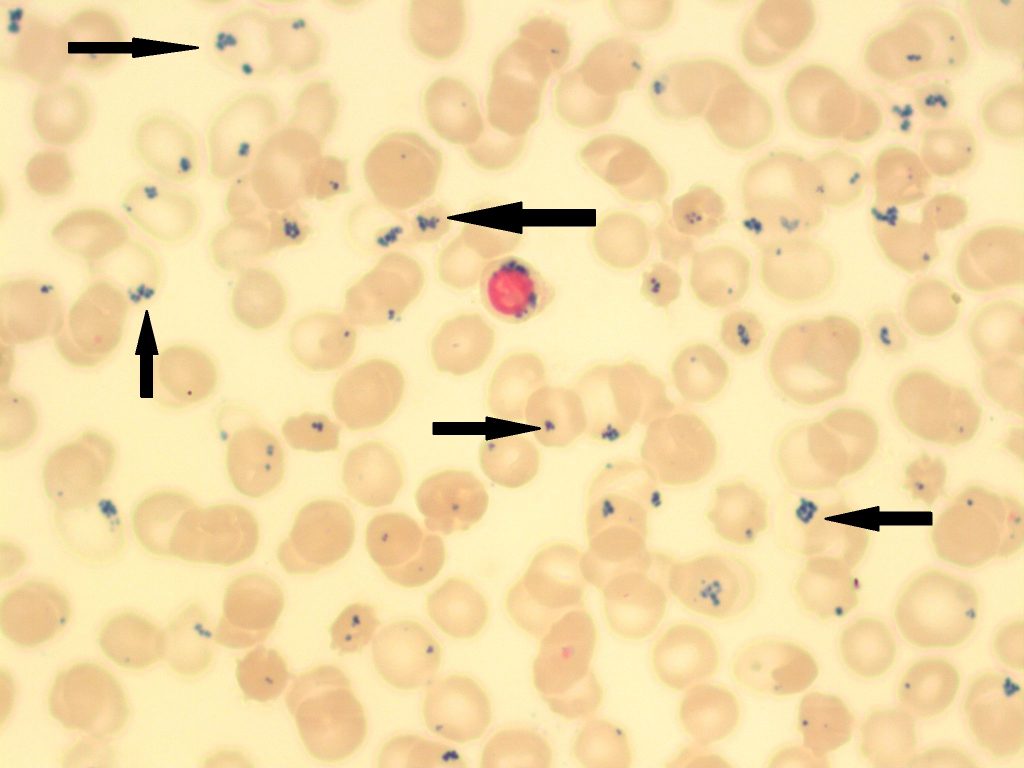
Pappenheimer bodies and siderotic granules are the same morphological structure. Both are small, basophilic, iron-containing granules within red blood cells. The term Pappenheimer body typically appears in standard Wright-Giemsa stains and refers to the visual appearance on a routine smear. The term siderotic granule is what you call them when you've confirmed the iron content with a Prussian blue (perls') stain. That distinction matters because reporting "Pappenheimer bodies" without confirming iron can be misleading. You might see basophilic stippling, which looks similar but is entirely different pathophysiologically. Basophilic stippling is aggregated ribosomes, not iron. The difference is critical for patient management.
How We Identify Them in Practice
The workflow I use starts with the routine smear. You're looking for 1 to 10 small, dark blue to purple granules clustered near the periphery of the red cell or scattered throughout the cytoplasm. They're usually 1 to 3 micrometers in diameter. Unlike Howell-Jolly bodies, which are larger, round, and dense with a sharp edge, Pappenheimer bodies are finer and more irregular. Once you think you've found them, you run the iron stain. A fresh smear gets fixed, flooded with equal parts potassium ferrocyanide and hydrochloric acid, left for ten minutes, counterstained with neutral red, and mounted. Blue-black granules confirm the presence of iron. If they don't stain blue with Prussian blue, they're not siderotic. Period. I learned this the hard way. About two years into my work, I called Pappenheimer bodies on a smear from a patient with thalassemia intermedia. The morphology looked right. The iron stain came back negative. It turned out those granules were calcium deposits from an old transfusion reaction, not iron at all. Mislabeling that could have sent the heme pathology team down a completely wrong diagnostic path. After that, I never report Pappenheimer without iron stain confirmation unless the clinical context makes it overwhelmingly likely, like in a known sideroblastic anemia case with classic ringed sideroblasts in the marrow.
Get the Full Details
Where They Show Up Clinically
Pappenheimer bodies and siderotic granules appear most often in conditions where iron metabolism is disrupted. Sideroblastic anemias are the classic association, whether congenital or acquired. Alcohol toxicity, lead poisoning, and copper deficiency can produce them too. You'll also see them after splenectomy since the spleen is the organ that normally filters these out from circulating RBCs. Asplenic patients frequently have elevated counts of Pappenheimer bodies, and that finding alone shouldn't trigger a workup for something worse. Here's something most beginners miss: the presence of Pappenheimer bodies doesn't automatically mean ringed sideroblasts are in the bone marrow. A peripheral blood finding of Pappenheimer bodies reflects iron overload in individual red cells, while ringed sideroblasts indicate a specific pattern of iron accumulation around the nucleus in erythroid precursors. They can coexist, but they're not the same process, and one can exist without the other.
Common Pitfalls
The biggest issue is overcalling basophilic stippling as Pappenheimer bodies. The stippling pattern is more diffuse and finer, distributed throughout the entire cytoplasm rather than appearing as discrete clumps. Lead poisoning produces prominent basophilic stippling, and mistaking it for Pappenheimer bodies will send the wrong signal about iron status. Another problem is counting errors. Pappenheimer bodies are easy to miss at high power if you're scanning too quickly, but they're also easy to overcall when you're tired and your eyes start pattern-matching. I've seen residents count five or six per cell when there were actually two, and they reported a significant finding that wasn't there. Stain quality is another factor. Overstained smears create artifact that looks remarkably like Pappenheimer bodies. If your Wright-Giemsa is past its shelf life or the pH drifted, everything looks darker and grainier than it should.
Reporting
When you report this on a smear, the format I use is straightforward: note the presence, estimate the number per 100 RBCs, describe the staining characteristics, and mention whether Prussian blue was performed and the result. Don't just write "Pappenheimer bodies present" and stop. That's not actionable. Include the iron stain result and the clinical correlation if you have it. The pathologist reading your work needs to know whether you've actually confirmed iron or just made an educated guess based on appearance. The iron granules themselves don't require any special handling beyond standard smear protocols. There's no reagent to order separately, no software to install, no subscription service to set up. It's a stain, a microscope, and the discipline to confirm before you commit to a diagnosis.