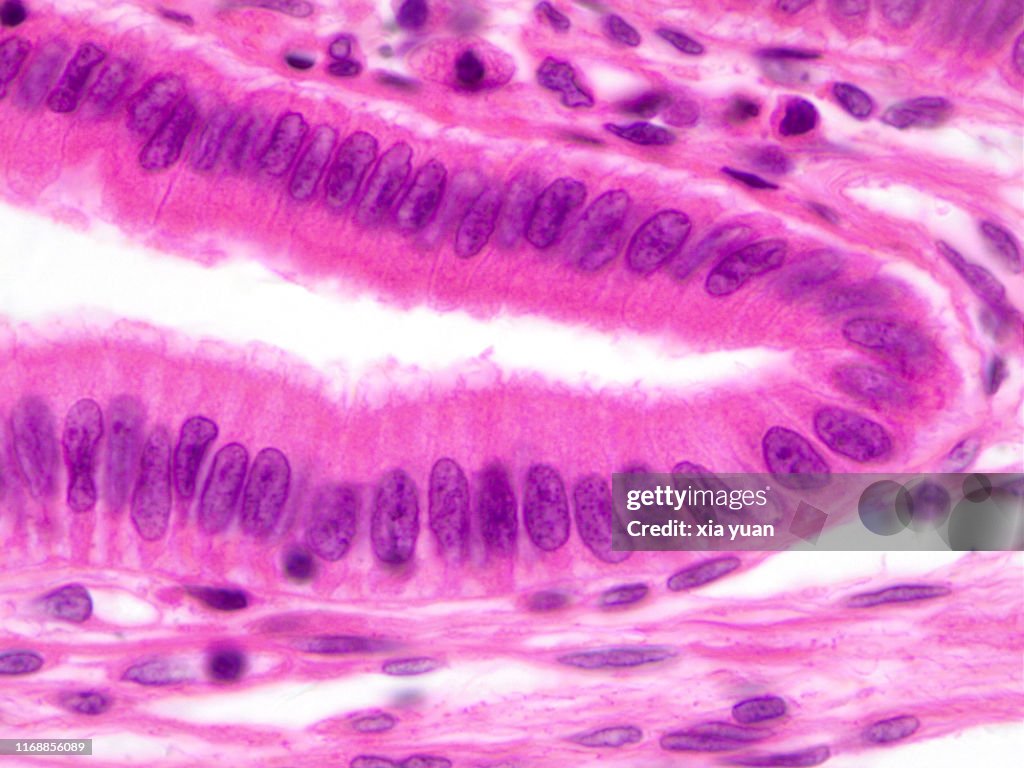
What Simple Columnar Epithelial Tissue Actually Is
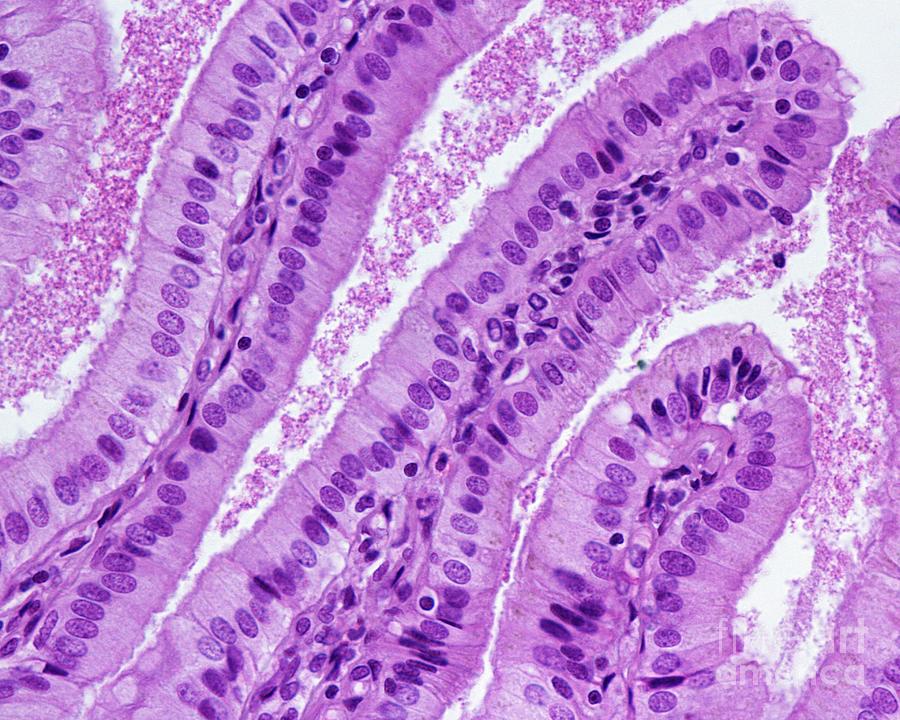
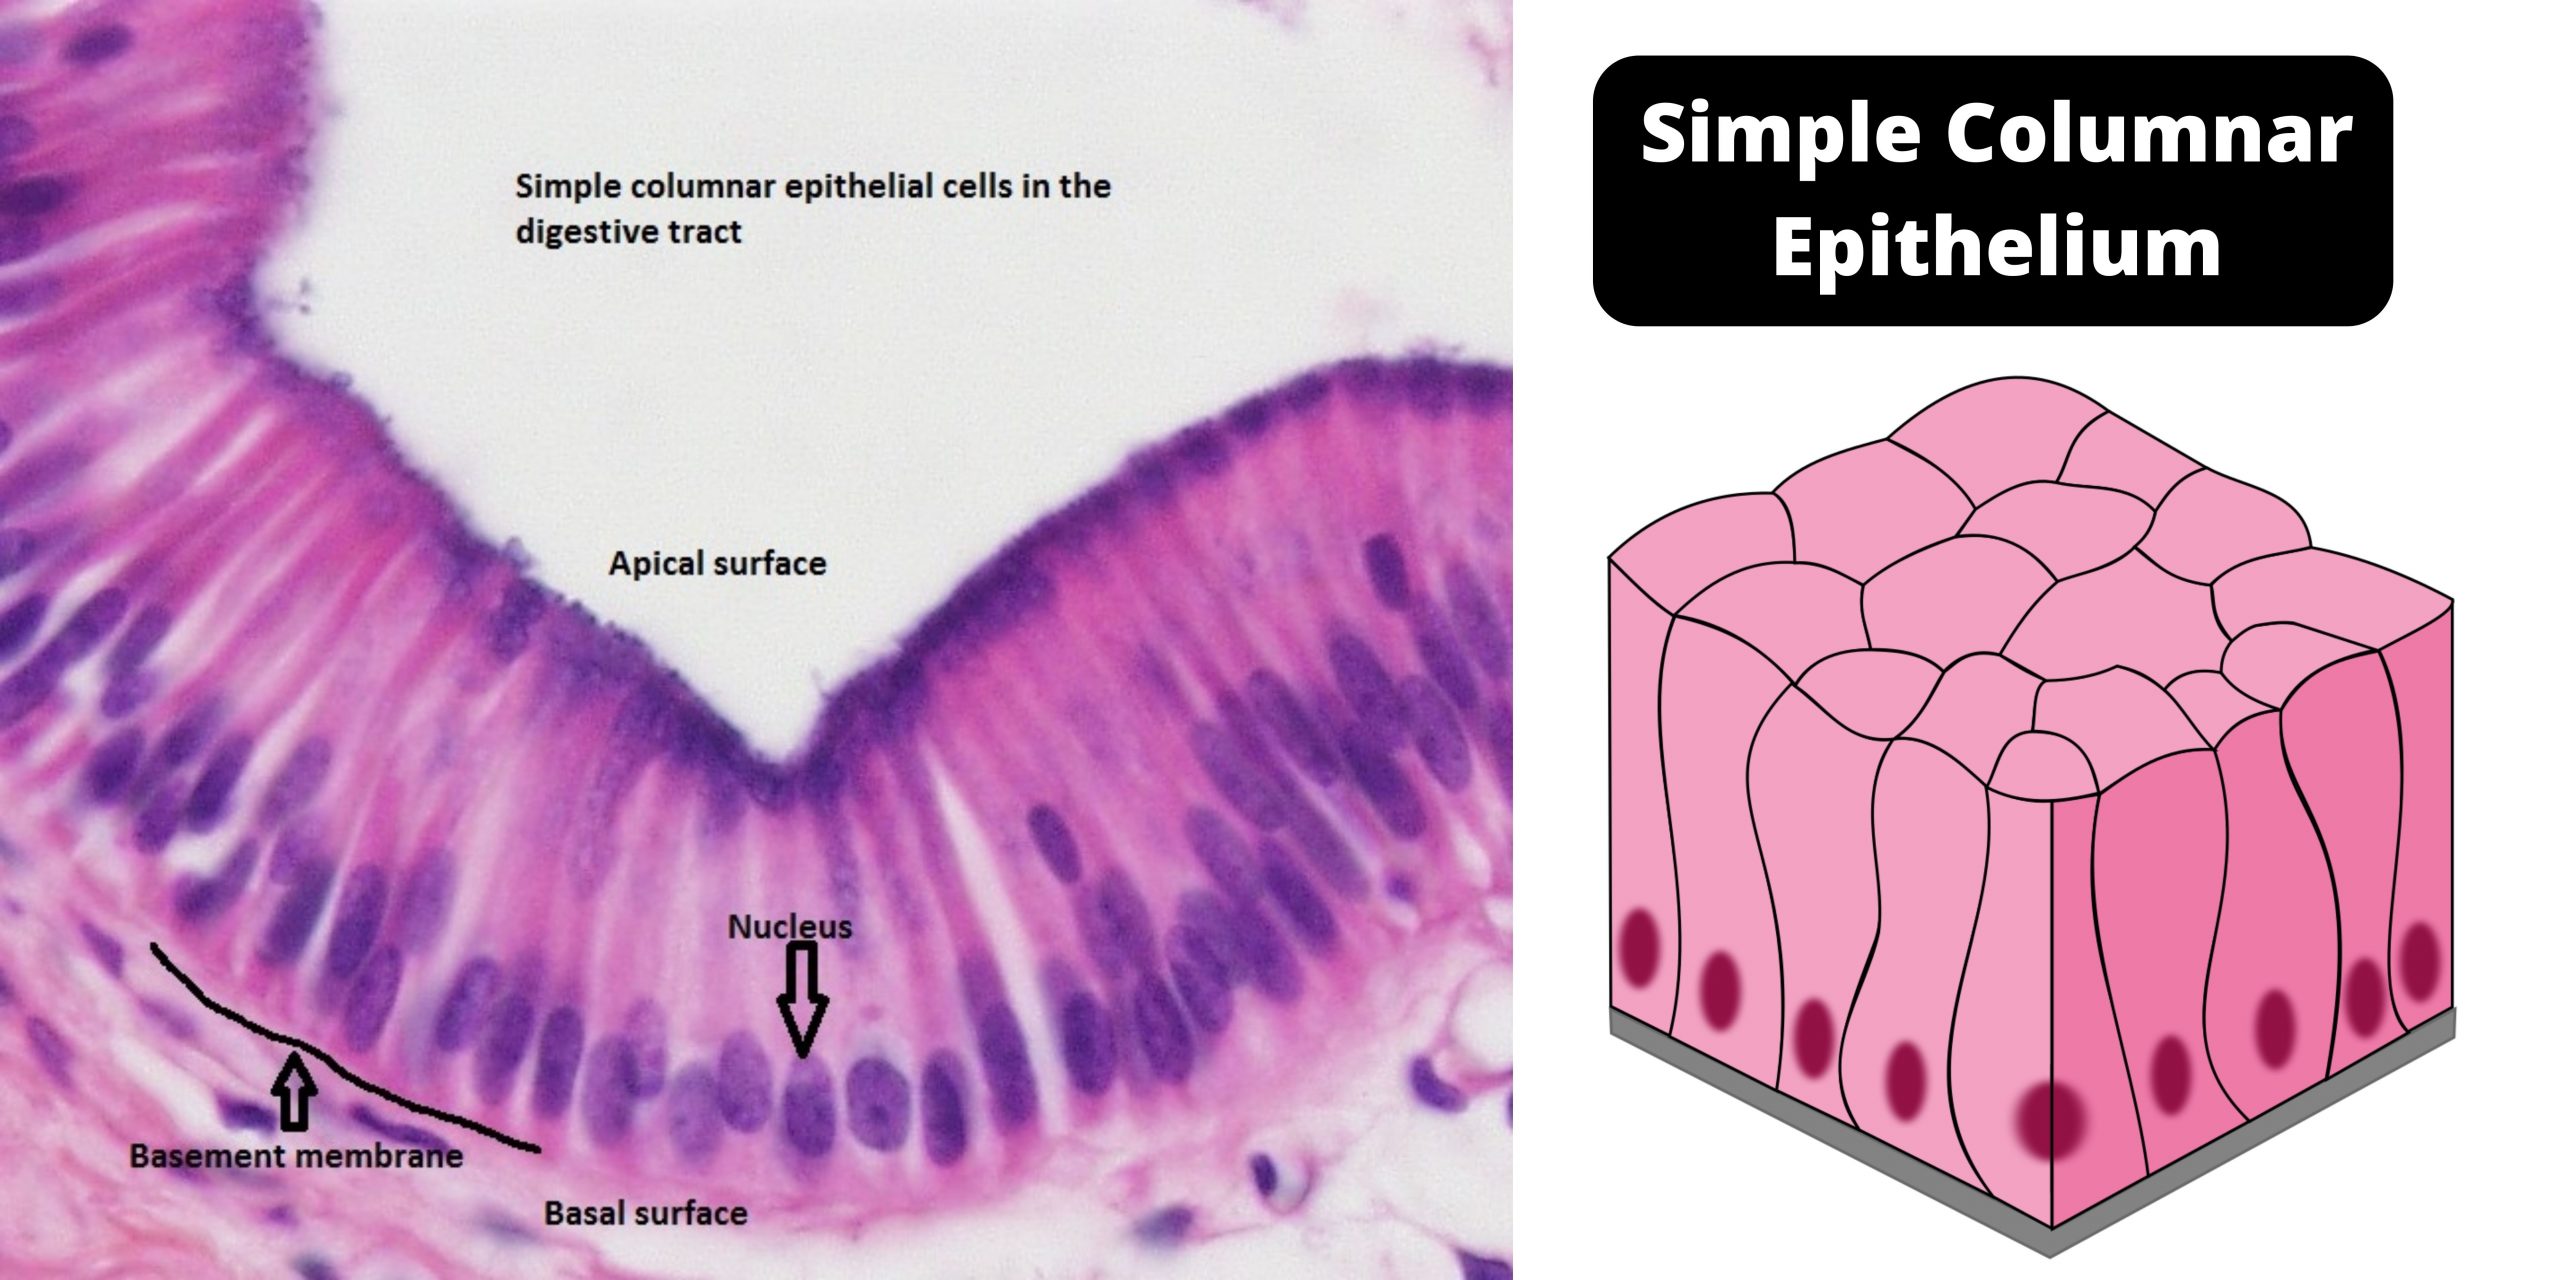
It is a single layer of tall, rectangular cells sitting on a basement membrane. The nuclei are oval and lined up near the base of the cells, which gives it that orderly look under the microscope. You will find this tissue lining the stomach, small intestine, gallbladder, and parts of the uterus and fallopian tubes. It does two things really well: absorption and secretion. The brush border you see in the small intestine, made of microvilli, is what pushes its absorptive capacity way above what a squamous or cuboidal layer could manage. Don't confuse those microvilli with cilia. Microvilli are tiny finger-like projections for absorption. Cilia are longer, whiplash-like structures that move mucus and particles along. They look similar at low magnification but do completely different things. When you are actually looking at a slide, the first thing that tells you what you are dealing with is the nucleus placement. If the nuclei form a neat row near the base and the apical surface is relatively free of organelles, you are probably looking at columnar epithelium. The cell height is greater than the width, which separates it clearly from cuboidal tissue. One thing people mess up constantly: they mistake pseudostratified columnar epithelium for simple columnar because both have tall cells. The difference is that pseudostratified epithelium has nuclei at multiple levels, making it look layered even though every cell touches the basement membrane. Simple columnar has all nuclei at roughly the same level. Start at 4x to get your bearings and find the epithelial layer. Switch to 10x and then 40x to see cellular detail. The trick is to focus through the section slowly. At 40x, you should see individual cell boundaries if the staining is decent. With H&E staining, the cytoplasm will be pink and the nuclei purple. In the intestine, look for goblet cells scattered between the columnar cells. Those are the clear, mucin-filled cups that stain poorly with H&E. If you see a dense brush border on the apical side, you are likely looking at intestinal epithelium. If the surface is relatively smooth with occasional goblet cells, it could be from the stomach or gallbladder.
The basement membrane is another landmark. It should appear as a thin pink line beneath the epithelial layer. If you cannot see it, your section might be too thick or the stain needs adjustment. Sections cut at 5 to 7 micrometers work best for most epithelial tissue. Thicker sections blur the cell boundaries and make identification harder. I once spent twenty minutes trying to figure out whether a section was simple columnar or stratified cuboidal before realizing my microtome was set to 12 micrometers instead of 5. The cells looked squashed and distorted at that thickness, making the nuclei appear at different levels. Fixing the blade angle and restarting with thinner cuts resolved it immediately.
Common Pitfalls When Studying This Tissue
One major issue is autolysis. The stomach and intestinal lining breaks down fast after death because those organs are packed with digestive enzymes. If the tissue is not fixed quickly, the epithelial cells can slough off or distort, making it nearly impossible to identify the layer properly. Formalin fixation within 30 minutes of collection is ideal. Beyond that, fixation artifacts like shrinkage orcrosslinking can make the cells look smaller or the nuclei more condensed than they actually are. Another problem is the distinction between simple columnar and transitional epithelium in certain regions. The ureter and bladder have transitional epithelium that can appear columnar when distended. If you are looking at a section without knowing the organ source, you might misclassify it. Always cross-reference with adjacent tissue layers. Simple columnar epithelium sits on connective tissue with blood vessels. If the underlying tissue looks like smooth muscle or cartilage, you may be looking at a different type of epithelium entirely.
Get the Full Details
Functional Details Most People Miss
The absorptive function of simple columnar epithelium in the small intestine is not just about surface area. The microvilli contain actin filaments that are anchored to the terminal web, a network of proteins just below the apical membrane. This structural support is what keeps the microvilli upright. When actin polymerization is disrupted, the microvilli collapse and absorption drops significantly. This is relevant in conditions like microvillus inclusion disease, a rare genetic disorder where the brush border is malformed. Secretion is equally important. The goblet cells interspersed in the epithelium produce mucin, which hydrates to form mucus. This mucus layer protects the epithelium from mechanical damage and digestive enzymes. In the stomach, the columnar epithelial cells secrete bicarbonate and mucus to protect the lining from hydrochloric acid. Without this protective mechanism, the stomach would digest itself. The balance between acid secretion by parietal cells and mucus-bicarbonate secretion by the surface epithelial cells is what keeps the gastric lining intact.
Pathology to Watch For
Chronic irritation or inflammation can cause metaplasia, where simple columnar epithelium changes into a different type. Barrett's esophagus is the classic example. The normal stratified squamous epithelium of the esophagus is replaced by simple columnar epithelium with goblet cells due to chronic acid reflux. This change is the body's attempt to protect the tissue, but it also increases the risk of adenocarcinoma. Recognizing this change on biopsy is critical and requires understanding the normal histology first. In the intestine, chronic inflammation from conditions like Crohn's disease can damage the epithelial layer, leading to ulceration and loss of the brush border. Under the microscope, you would see shortened or absent microvilli, infiltrating immune cells in the lamina propria, and architectural distortion of the crypts. These changes are subtle at first and become more pronounced over time. Early recognition matters because the epithelial barrier is what prevents bacterial translocation from the gut lumen into the bloodstream.
Practical Tips for Lab Work
If you are working with real tissue samples, staining quality matters more than anything else. Over-stained sections make it hard to distinguish cell boundaries. Under-stained sections make nuclei blend into the cytoplasm. A good rule of thumb is that nuclei should be a deep purple but still show internal structure, and the cytoplasm should be a lighter pink. If both are too dark, your hematoxylin or eosin stain is too concentrated or the differentiation step was skipped. Mounting media choice also affects long-term slide preservation. Synthetic resin-based mounting media like Permount or DPX preserve stains for years. Aqueous mounting media are faster to use but cause stains to fade within months. If you are building a slide library for reference, spend the extra time with resin mounting. The difference becomes obvious after a year or two when the aqueous-mounted slides look washed out and the resin-mounted ones still look fresh. One thing I learned the hard way: label your slides immediately. Not with a pencil on the frosted end, but with an acid-resistant marker directly on the slide. Pencil marks smear during staining procedures and become illegible. I lost an entire batch of intestinal sections because the labels rubbed off during the xylene clearing step. All I had was a stack of unlabeled slides and no record of which organ each came from. That cost me about three days of re-cutting and re-staining.
When Simple Columnar Epithelium Changes
Dysplasia is another concern, particularly in the cervix and gastrointestinal tract. Simple columnar epithelium in the endocervix is a common site for dysplastic changes driven by HPV infection. The normal orderly arrangement of nuclei gets disrupted, with nuclei becoming enlarged, hyperchromatic, and irregularly spaced. Recognizing early dysplasia requires familiarity with the normal architecture. If you have never seen a clean, well-organized simple columnar layer, you will not notice when it starts to look disordered. The repair process after epithelial injury also involves simple columnar cells. In the stomach, for example, surface epithelial cells migrate to cover small erosions within hours. Full restoration of the mucosal barrier takes a few days. This regenerative capacity is one reason the gastric lining can withstand constant exposure to harsh acid. The stem cells in the gastric pits divide rapidly to replace damaged cells. When this regeneration fails, you get chronic ulcers instead of healed tissue.
Summary of Key Features
Simple columnar epithelium is defined by a single layer of tall cells with basal nuclei. It functions primarily in absorption and secretion. The presence of microvilli or cilia on the apical surface modifies its specific role. Goblet cells are often interspersed within the layer. It lines the digestive tract from the stomach to the upper anus, the gallbladder, and the female reproductive tract. Misidentification usually comes from confusing it with pseudostratified or stratified epithelium, or from poor section quality. Understanding the underlying connective tissue and adjacent structures helps confirm your identification.