Understanding Simple Cuboidal Epithelium Labeling in Histology
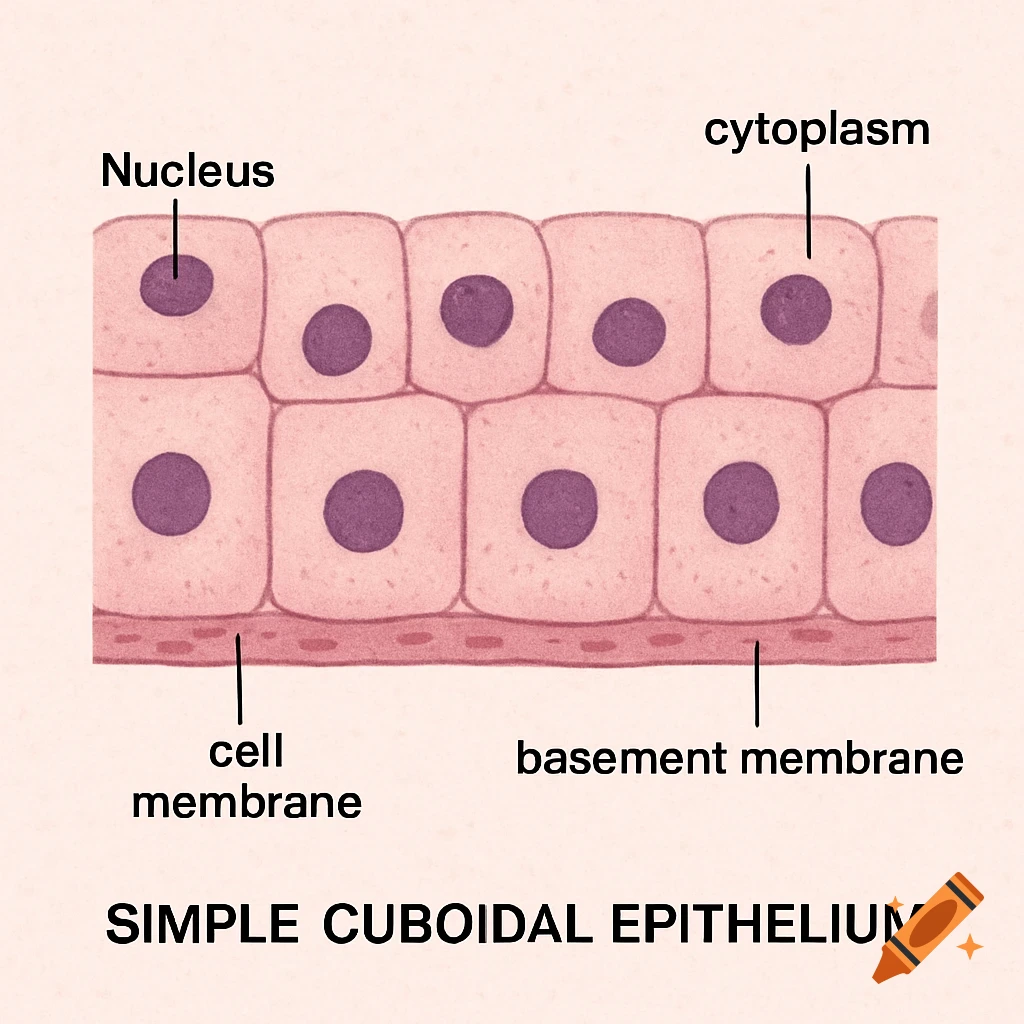
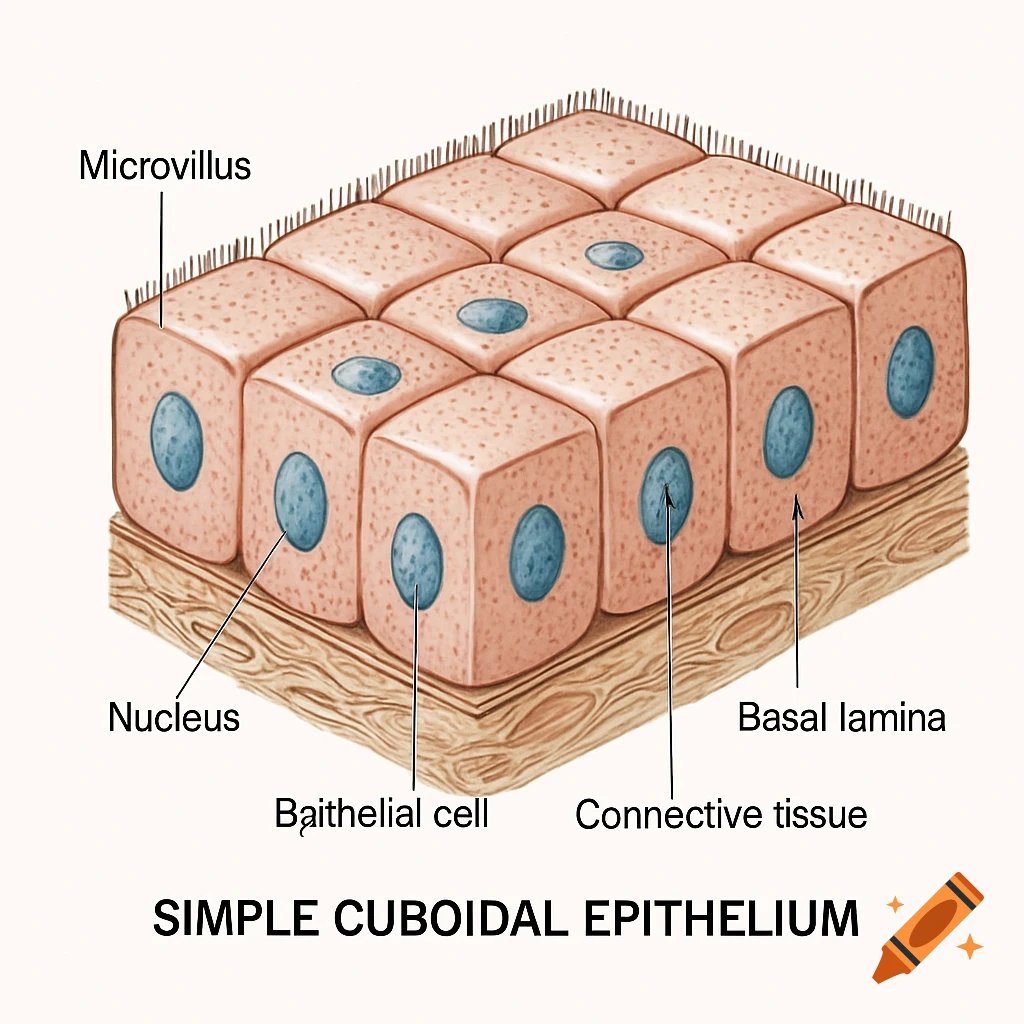
When you're looking at a tissue section and you need to identify simple cuboidal epithelium, the first thing most people reach for is a standard H&E stain. It works fine for basic morphology. But when you actually need to confirm cell type, track protein expression, or distinguish cuboidal from adjacent squamous or columnar cells, you start labeling. I've spent years working with kidney tubules, thyroid follicles, and pancreatic ducts, and labeling simple cuboidal epithelium is where things get interesting. Simple cuboidal epithelium consists of a single layer of cube-shaped cells. The nucleus is typically round and centrally located. When we say "labeled," we're talking about applying immunohistochemical or immunofluorescent markers to highlight specific proteins within those cells. Common targets include cytokeratins (CK7, CK20), E-cadherin, ZO-1 for tight junctions, and various hormone receptors depending on the tissue origin. The labeling pattern tells you more than just "this is cuboidal." It shows you polarity, junctional integrity, and functional state. A properly labeled section should show membrane staining in a continuous band around each cell, with perhaps some cytoplasmic signal depending on your antigen.
Practical Labeling Protocol
Here's how I approach it in my lab. Fixation matters enormously. Formalin fixation for 24 hours is standard, but over-fixation can mask epitopes, especially for membrane proteins. I learned this the hard way with a thyroid project where my TTF-1 staining was inconsistent until I realized the blocks had been sitting in formalin for three weeks. antigen retrieval using citrate buffer at pH 6.0 for 15 minutes in a pressure cooker made the difference. For primary antibodies, I usually start with a dilution range. CK7 at 1:100 to 1:400, ZO-1 at 1:200. Overnight incubation at 4°C gives cleaner results than room temperature protocols. The secondary antibody needs to match your host species and is typically diluted 1:500. DAB chromogen development takes 3 to 8 minutes depending on target abundance. You watch under the microscope and develop just until the positive control shows clear staining, then stop. I ran into a specific problem with renal proximal tubules a while back. The brush border was labeled beautifully, but the lateral membranes were weak. Turns out the fixation was slightly acidic due to old formalin, which altered the charge on membrane proteins. Switching to freshly prepared neutral buffered formalin and adding a 0.1% Triton X-100 permeabilization step for 10 minutes after antigen retrieval fixed it. Lateral membrane staining became crisp and continuous.
Interpreting the Labeling Pattern
Proper labeling of simple cuboidal epithelium should show uniform circumferential membrane staining. If you see patchy or discontinuous labeling, check for several issues. Tissue thickness matters. Sections that are too thick (greater than 5 microns) cause out-of-focus signal and make junctional staining look irregular. Section adhesion is another factor. Poorly adhered sections can distort cell morphology during processing, making cubes look squashed or stretched. Background staining is the other common problem. High background usually means insufficient blocking. I use 5% normal serum from the same species as the secondary antibody for 30 minutes before applying the primary. This cuts non-specific binding significantly. If you're doing multiplex labeling with multiple fluorophores, spectral overlap becomes your enemy. Use single-stain controls for each channel to set your compensation correctly.
Get the Full Details

Common Pitfalls and How to Avoid Them
One thing beginners miss is that not all cuboidal cells label the same way. In the kidney, proximal tubules express CK7 strongly, but distal tubules are CK7 negative and instead show calbindin labeling. If you're using CK7 as a pan-cuboidal marker, you'll miss the distal portion. Similarly, thyroid follicular cells label with thyroglobulin and TTF-1, but parafollicular C cells are positive for calcitonin and negative for thyroglobulin. The morphology looks identical under H&E, so labeling is essential for distinction. Another pitfall is over-labeling. Strong signal isn't always better. When the staining is too intense, you lose the ability to compare expression levels between cells. Nuclear counterstaining with hematoxylin should be light enough that you can still see cytoplasmic and membrane patterns clearly. If the blue is too dark, you're obscuring your data. I also found that fixation time affects membrane labeling differently than cytoplasmic labeling. Membrane proteins like E-cadherin and ZO-1 are more sensitive to over-fixation. If your membrane signal is weak but cytoplasmic signal is strong, try shorter fixation times or milder antigen retrieval conditions. For cytoplasmic targets, longer fixation is usually fine.
Quality Control Steps
Every labeling run should include a positive control tissue you know expresses your target. Kidney is useful for general epithelial markers. Thyroid works for thyroid-specific antigens. The negative control should be a tissue that lacks the target or omission of the primary antibody. If your negative control shows signal, you have a blocking or secondary antibody issue. If your positive control is weak, check fixation, antigen retrieval, and antibody freshness. Image acquisition matters too. For DAB staining, brightfield microscopy at 40x or 60x objective gives good detail. For fluorescence, use a camera with low noise and acquire images with consistent exposure settings. Auto-exposure can vary between fields and make comparison unreliable. I lock my exposure parameters and use the same settings for all sections in a given experiment.
When Labeling Doesn't Work
Sometimes you'll encounter tissue where simple cuboidal epithelium simply won't label with available antibodies. This happens with decalcified bone sections, heavily cross-linked samples, or antigens that are internally sequestered. In those cases, you might try alternative fixation like methanol or acetone for frozen sections, or switch to a different epitope target on the same protein. Some antibodies are clone-specific and recognize only certain conformations of the protein. For challenging samples, I sometimes combine labeling with in situ hybridization to detect mRNA expression when protein detection fails. This gives you spatial information even if the protein is degraded or below detection limits. It's an extra step, but it can rescue otherwise lost data. The bottom line is that labeling simple cuboidal epithelium requires attention to fixation, antibody selection, and interpretation. There's no single perfect protocol. You need to optimize for your specific tissue and target. My experience across dozens of projects shows that small changes in retrieval conditions and blocking can make the difference between ambiguous staining and clear, publishable results.