What You Actually Need to Know About Simple Cuboidal Epithelium Location
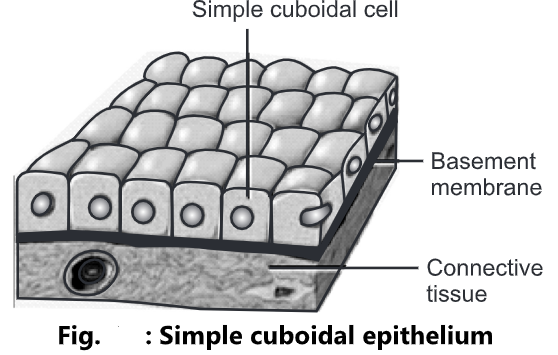
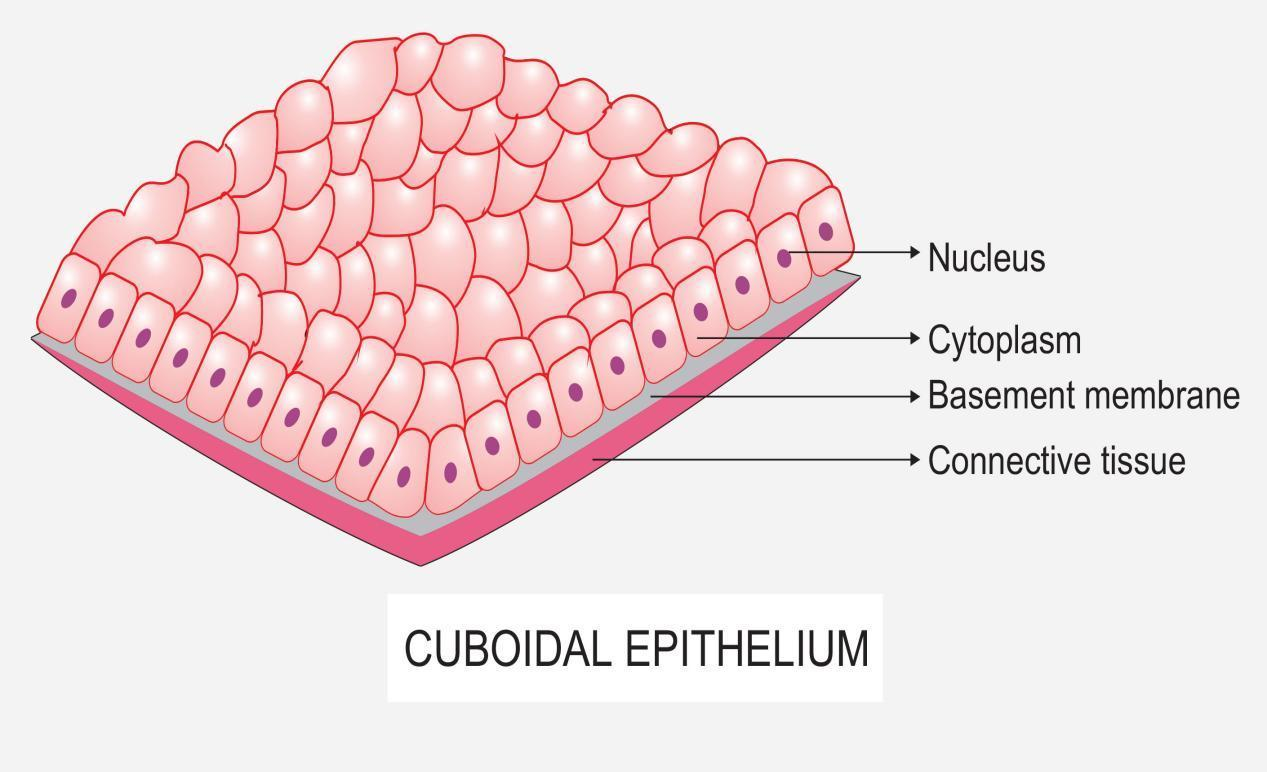
I spend most of my time looking at tissue sections under a microscope, and honestly, the topic of simple cuboidal epithelium comes up constantly in both teaching labs and real diagnostic work. People tend to memorize the standard list of locations and then move on, but the actual application is messier than that. Let me walk through what matters. Simple cuboidal epithelium consists of a single layer of cube-shaped cells, where the nucleus is round and centrally located. The cells are roughly as tall as they are wide. Under low magnification on a routine H&E stain, they show up as neat little tiles. At higher power you can see the apical surface sometimes has microvilli, though not as prominently as the simple columnar type in the gut. The classic locations taught in every textbook are the renal tubules of the kidney, the ducts of small glands, the surface of the ovary, and the thyroid follicles. That list is accurate but incomplete in practice. You will also encounter this tissue type lining the proximal and distal convoluted tubules, the collecting ducts in some regions, the efferent ductules of the epididymis, and the bruchia of the eye. The key is recognizing the morphology rather than just reciting locations, because pathology changes how these tissues look and where they appear in a section.
I remember running into a tricky case a few years back where a biopsy from a patient with chronic lithium use showed extensive cuboidal metaplasia in the distal nephron. The tubules looked almost identical to the proximal ones at low power, and the pathologist on call initially called it artifact. The workaround was straightforward once I suggested checking for the characteristic granular eosinophilic cytoplasm and comparing it side by side with a known normal kidney section from the same batch. Lithium causes exactly this kind of change, and if you are not expecting it, you can miss it. The cells become more cuboidal than their normal columnar state, and the nuclei pull toward the base. It is easy to confuse with early tubular injury if you do not have a reference point.
How to Actually Identify It in a Specimen
Start with the staining. Hematoxylin and eosin is the standard, but the quality of your stain matters more than most people admit. Over-stained sections make the cytoplasm look too pink and the borders disappear. Under-stained sections make the nuclei hard to distinguish. A well-stained slide should show clear cell boundaries with a distinct pink cytoplasm and a purple round nucleus sitting right in the middle. If the cells look flattened, you are probably looking at simple squamous epithelium, not cuboidal. If they look taller than wide with basal nuclei, that is simple columnar. One thing beginners consistently get wrong is the relationship between cell shape and function. Cuboidal epithelium is not just a structural placeholder. In the kidney tubules, these cells are actively reabsorbing and secreting ions and water. In the thyroid, they produce and store thyroglobulin within the follicular lumen. The morphology matches the function because the cells need enough cytoplasmic volume to house the organelles required for transport and synthesis. Flat squamous cells would not have that capacity. Another counter-intuitive point is that simple cuboidal epithelium can transform. It does not always stay cuboidal. Chronic irritation or hormonal changes can push these cells toward a columnar or even squamous appearance. This is called metaplasia, and it happens in real tissue. If you are grading a pathology slide and the cells look slightly elongated, do not automatically call it simple columnar. Check the surrounding tissue context. A transition zone is often the answer.
Get the Full Details

Common Pitfalls and Where This Approach Breaks Down
The main limitation with identifying simple cuboidal epithelium location in practice is that artifact and sectioning plane can completely change the appearance. If a tubule is cut obliquely instead of cross-section, the cells will look elongated and you might misidentify the tissue type. This happens all the time in biopsy sections. I usually deal with it by scanning multiple fields and finding a clean cross-section before making a call. It adds maybe five minutes to the reading, but it prevents misdiagnosis. Another issue is that not all cuboidal-appearing cells are epithelium. In some glandular tissues, the myoepithelial cells can look remarkably similar at low magnification. They sit between the epithelial layer and the basement membrane and are contractile in function. The distinction matters because myoepithelial cells are marked by smooth muscle actin and p63 in immunohistochemistry, while true epithelial cells express cytokeratins like CK7 and CK8/18. If you are working in a diagnostic setting, running a quick IHC panel resolves the ambiguity in about twenty minutes. There is also the problem of partial or fragmented sections. In fine needle aspiration biopsies or small core samples, you might only get a fragment of the epithelial lining. Without the full architectural context, identifying the tissue type becomes guesswork. In those cases, relying on cytological features alone is risky. Correlation with imaging and clinical history is essential, and sometimes the best you can say is "consistent with simple cuboidal epithelium but insufficient to rule out other possibilities." That is an honest answer, and it is better than being confidently wrong.
Practical Tips That Actually Help
When you are learning to recognize this tissue, start with kidney cortex sections. They are the cleanest examples you will find. The proximal convoluted tubules have a brush border that makes them stand out, and the distal convoluted tubules lack that border, giving you two clear variants of cuboidal epithelium side by side. Once you can tell the difference between those two, the rest of the body's cuboidal locations become much easier to identify. For the thyroid, the follicles are lined by a single layer of cuboidal cells surrounding a pink colloid center. The height of the cells can vary depending on the functional state of the gland. In a hyperactive thyroid, the cells may become more columnar. In an inactive or atrophic state, they can appear flattened. So the same tissue can look different depending on the physiological context. Keep that in mind when you are evaluating slides from different patients. If you are doing this work in a lab setting, keep a reference atlas open while you scan. Having images of known normal tissue makes it significantly faster to spot abnormalities. I usually keep a digital atlas on a second monitor, and it cuts my identification time roughly in half compared to relying on memory alone. The improvement is real and measurable if you track it over a few weeks of regular practice.
Resources and Where to Find Better Reference Material
The internet has plenty of free histology resources, but the quality varies widely. University histology labs often post high-resolution image sets with labels, and those are usually more reliable than random educational websites. Some good options include the University of Michigan Histology Guide, the NIH's Histology Tutorial, and the University of Oklahoma's interactive histology atlas. These resources show real microscope images rather than illustrations, which is important because illustrations can oversimplify the variability you will see in actual tissue. I also recommend practicing with virtual microscopy platforms if your institution has access. Being able to zoom in and out on real slide scans helps you develop the pattern recognition that comes with experience. It is not a replacement for looking at actual glass slides, but it is closer than any textbook diagram. The best results come from combining both approaches over several months of consistent study. One thing I would caution against is relying too heavily on automated image analysis software for identification. These tools can be helpful for counting cells or measuring nuclear size, but they often misclassify cuboidal epithelium as columnar or squamous depending on the training data they were built on. I have seen this happen repeatedly, and the errors are subtle enough that a quick sanity check by a trained eye catches them before they cause problems. Use the software as a supplement, not a substitute.

Bottom Line on What Matters
Simple cuboidal epithelium is one of the most common tissue types you will encounter, and its location in the body follows predictable patterns, but those patterns are not fixed. The tissue adapts, transforms, and sometimes looks deceptively different depending on the angle of the section or the functional state of the organ. The most reliable approach is to combine morphological recognition with contextual awareness and, when in doubt, confirm with additional stains or reference material. That is how you avoid the common mistakes and build actual competence rather than just passing a quiz.