Understanding Simple Squamous Epithelial Tissue Location
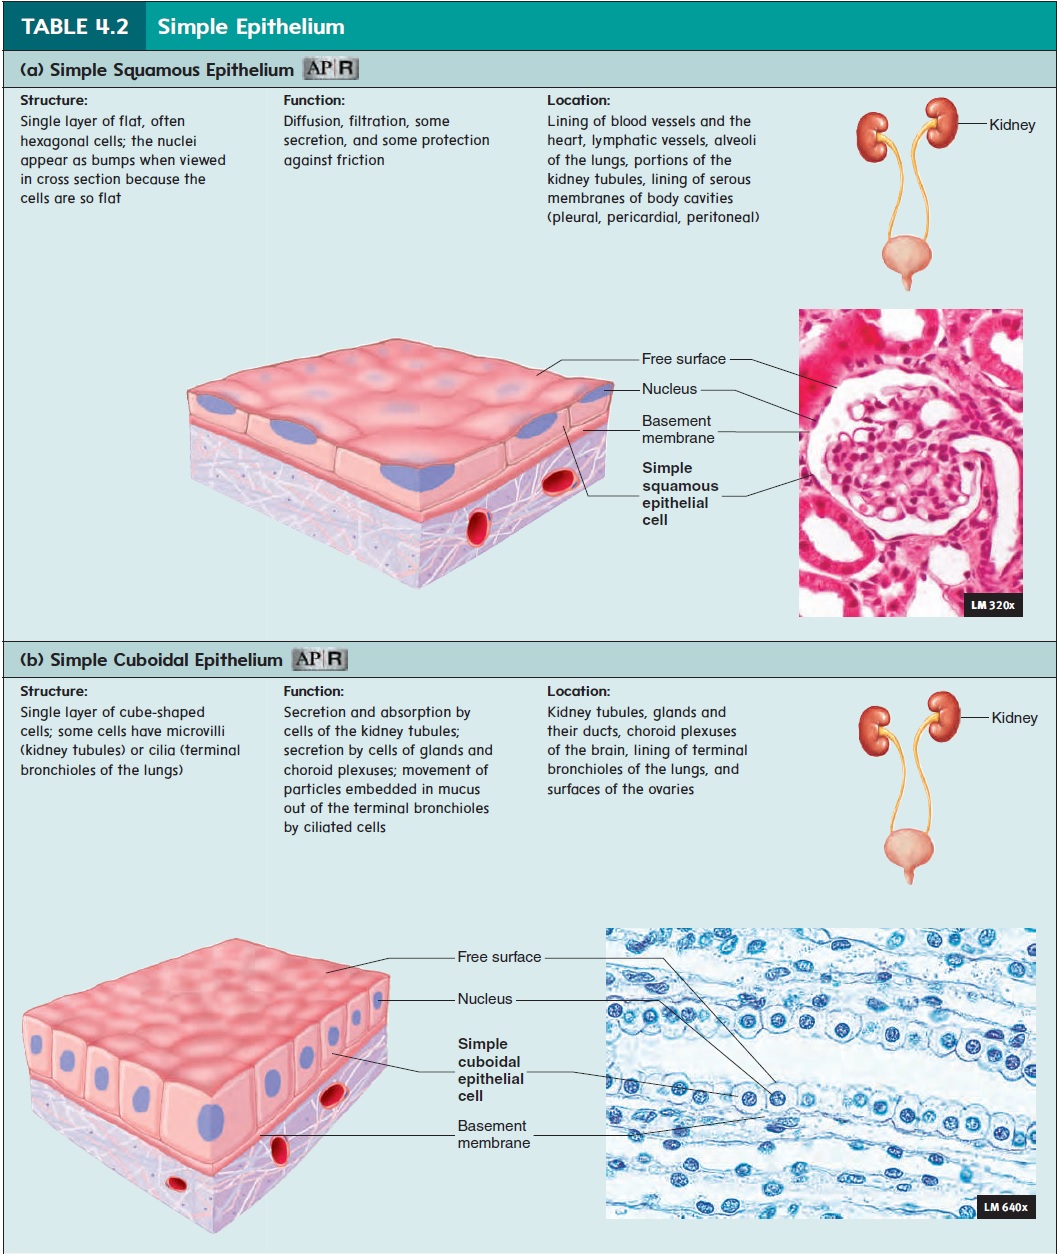
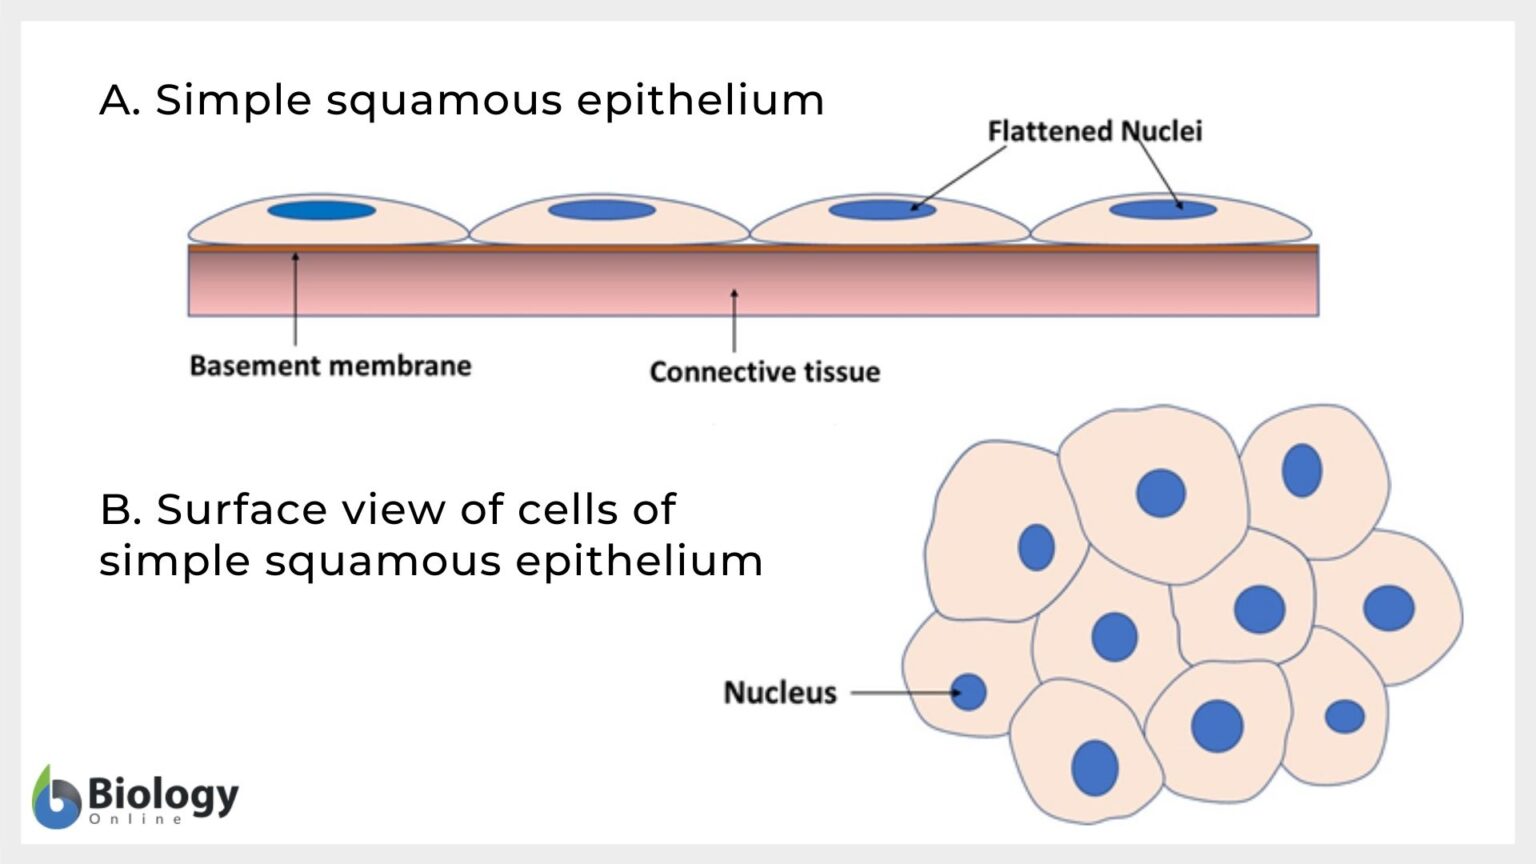
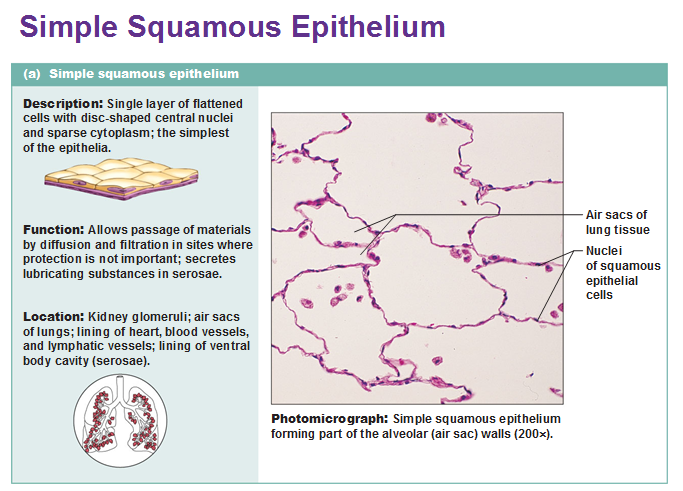
Simple squamous epithelium consists of a single layer of flattened cells. You will find it where rapid diffusion or filtration is required. The thin cytoplasm minimizes the distance molecules must travel. The alveoli in your lungs are lined with simple squamous epithelium. This is type I pneumocyte territory. Oxygen crosses from the air space into capillary blood here. Carbon dioxide moves in the opposite direction. The entire respiratory membrane is roughly 0.5 micrometers thick at these sites. Blood vessel linings use the same tissue. Endothelium is technically simple squamous epithelium. It lines every artery, vein, and capillary in your body. When you see cross-sections of vessels under a microscope, that thin inner layer is endothelium. The cells are so flat you can barely distinguish their borders.
The kidneys contain simple squamous epithelium in Bowman's capsule. The parietal layer forms this capsule. It surrounds the glomerular capillaries. Filtrate passes from blood into the Bowman's space here. The slit pores between podocyte foot processes are the actual filtration barrier, not the epithelial cells themselves. This distinction matters for understanding kidney physiology. Body cavities use a variant called mesothelium. The pleura lining the lungs, the pericardium around the heart, and the peritoneum in the abdomen all have simple squamous epithelium. These membranes secrete serous fluid. The fluid reduces friction between moving organs. Your lungs slide against the chest wall without sticking. I spent hours trying to identify alveolar epithelium in a histology practical once. The tissue looked like scattered chicken wire under low magnification. At higher power, the nuclei bulged into the lumen. I initially misidentified the endothelial cells in capillaries as alveolar cells. The trick is remembering that alveoli are air spaces while capillaries contain blood. One tissue serves gas exchange. The other serves nutrient transport. Both use simple squamous epithelium.
Why This Tissue Matters
Simple squamous epithelium exists where speed matters. Diffusion rate depends inversely on membrane thickness. A single flat cell provides minimal barrier. Large surface area combined with thinness enables rapid exchange. Capillaries demonstrate this principle. The entire wall may be one cell thick. Red blood cells squeeze through single file. Plasma components pass freely through the endothelium. Small molecules like glucose and oxygen diffuse rapidly. Large proteins generally stay in the blood. The fenestrations in kidney capillaries allow more passage. Filtration pressure drives movement across this epithelium. Blood pressure pushes fluid out of glomerular capillaries. Oncotic pressure pulls fluid back. The balance determines net filtration rate. Alterations in this equilibrium cause edema or dehydration. Understanding the tissue helps explain these clinical conditions.
Get the Full Details
Identifying Simple Squamous Epithelium Under Microscope
Look for nuclei that bulge into the lumen. The cytoplasm appears as thin rims around these nuclei. Cell borders are often invisible. Staining matters. Hematoxylin and eosin show pink cytoplasm with purple nuclei. Silver stains outline the basement membrane better. Capillary endothelium can be confused with other tissues. The cells are flat but may appear cuboidal in cross-section. Oblique cuts through vessels create artifacts. Always examine multiple sections. The nucleus position helps identify orientation. Flat nuclei parallel to the surface indicate squamous cells. Alveolar epithelium presents different challenges. Type II pneumocytes are cuboidal. They produce surfactant. Only type I cells are truly squamous. Yet type II cells cover more surface area despite their shape. The ratio is roughly 96 percent type I to 4 percent type II by surface coverage. This seems counter-intuitive until you consider cell geometry.
Peritoneal mesothelium often looks like scattered tiles. The cells are polygonal in surface view. Under section, they appear as thin lines. The basement membrane is prominent. Fibroblasts in the underlying connective tissue may confuse beginners. Real epithelium sits on a distinct membrane. Mesothelium is a specialized epithelium. It shares features with both epithelial and connective tissue.
Pathological Changes
Squamous metaplasia occurs when simple squamous epithelium transforms. Chronic irritation causes this change. The respiratory tract in smokers demonstrates this. Pseudostratified ciliated columnar epithelium becomes stratified squamous. The change protects against damage. It also reduces gas exchange capacity. Atherosclerosis affects endothelial function. Plaque builds up in arterial walls. The simple squamous lining becomes disrupted. Permeability increases. Lipids infiltrate the vessel wall. White blood cells migrate through the damaged endothelium. The tissue response creates fibrous caps over lipid cores. These caps can rupture, causing thrombosis. Kidney diseases often involve the glomerular basement membrane. Diabetic nephropathy thickens this membrane. Filtration becomes impaired. Protein leaks into urine. The simple squamous epithelium itself may appear normal initially. The pathology lies in the basement membrane and podocyte foot processes. Understanding tissue is crucial for diagnosis.
Limitations and Considerations
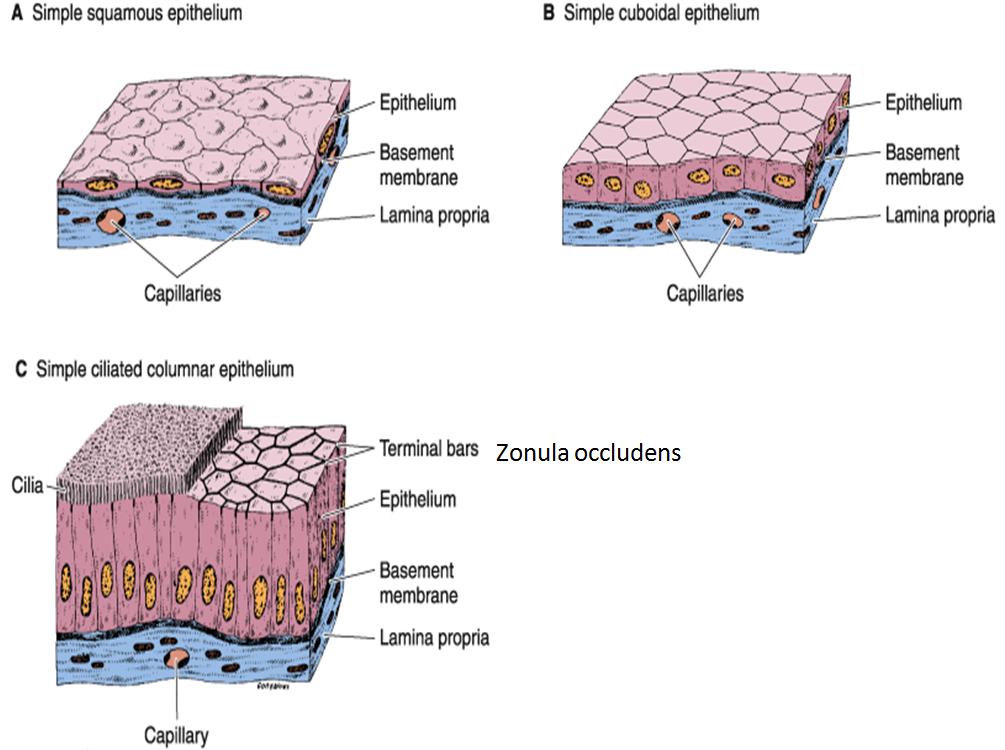
Simple squamous epithelium provides strength only through its basement membrane. The cells themselves offer minimal structural support. Damage to underlying connective tissue compromises the epithelium. Wound healing involves proliferation of adjacent cells. Migration covers defects within hours. Regeneration restores the barrier function. This tissue cannot withstand mechanical stress. Stratified epithelia protect skin and esophagus. Simple squamous appears only where protection is unnecessary. The alveoli experience minimal friction. Blood flow provides gentle movement. Body cavity linings slide against each other with lubrication. Identification requires good microscopy technique. Artifacts from sectioning can mimic pathological changes. Overstretching tissue creates gaps. Underfixation causes nuclear swelling. Always compare with known normal sections. The learning curve spans weeks of practice. Mistakes are common until pattern recognition develops.
When simple squamous epithelium fails, organ function declines. Pulmonary edema fills alveoli with fluid. Gas exchange becomes impossible. Patients require mechanical ventilation. Renal filtration drops in kidney disease. Dialysis replaces glomerular function. Understanding normal tissue helps recognize pathology. The location determines function. Function explains vulnerability.