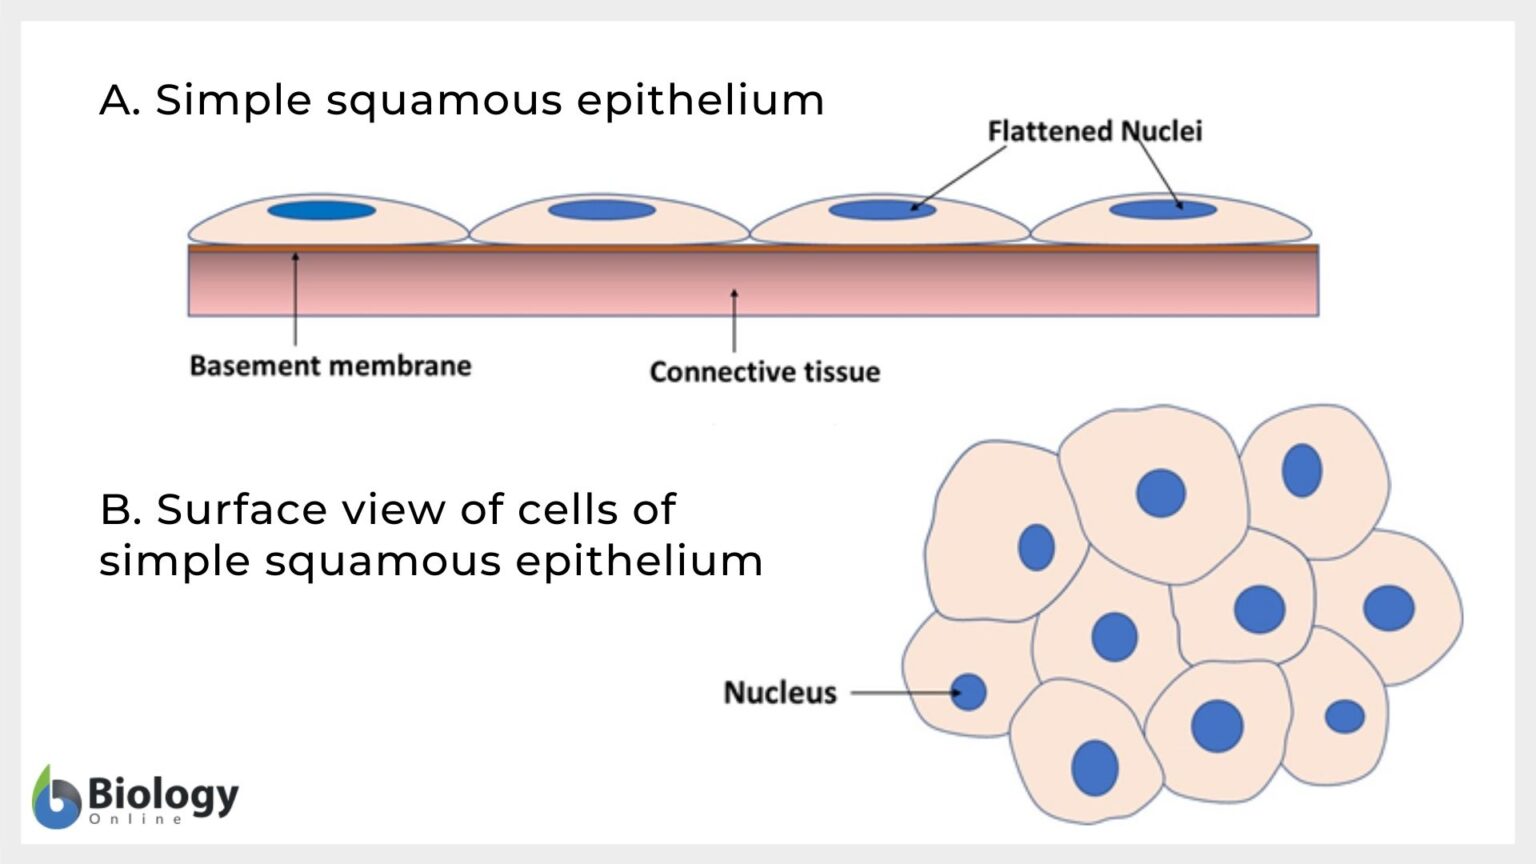
Identifying Simple Squamous Epithelium Under the Microscope
The key to finding simple squamous epithelium location isn't memorizing lists—it's knowing what to look for when you're staring at a slide at 40x or 100x objective. I spent weeks troubleshooting why my lung sections kept looking like nonsense until I figured out the tissue preparation sequence matters more than the stain itself. Simple squamous epithelium consists of a single layer of flat, scale-like cells. The nuclei appear as flattened ovals or disks, and the cytoplasm is thin enough that you can often see through the cell to structures underneath. This is exactly why it's found where rapid diffusion or filtration needs to happen.
Common Simple Squamous Epithelium Location Sites
The most clinically relevant sites are the alveoli in lung tissue, the endothelial lining of blood vessels throughout the body, the mesothelium lining body cavities (peritoneum, pleura, pericardium), Bowman's capsule in the renal corpuscle, and the thin limbs of Henle's loop. Each of these has slightly different functional requirements that affect how the tissue appears under standard H&E staining. In practice, when I'm working with lung sections, the alveolar walls can be so thin that they're nearly impossible to distinguish from individual alveolar type I pneumocytes without proper fixation. Over-fixation with formalin makes the tissue brittle and causes artificial tearing during microtomy. I learned this the hard way when I wasted three blocks on a section that looked like Swiss cheese. The workaround is to fix in 10% neutral buffered formalin for exactly 24 hours at room temperature, then rinse in running water for 1 hour before processing. This preserves the delicate alveolar architecture without causing shrinkage artifacts. Blood vessel endothelium presents a different challenge. In capillaries, the endothelial cells are so thin that they're essentially invisible as distinct structures—they blend into the basement membrane. You identify them by the nucleus bulging into the lumen rather than by the cytoplasm. In larger vessels like arteries and veins, you'll see multiple layers of smooth muscle cells beyond the endothelium, which can confuse beginners into thinking they're looking at stratified epithelium. The trick is to follow the endothelial lining around the entire circumference; it should be continuous and a single cell thick.
Kidney tissue requires careful attention to the distinction between Bowman's capsule parietal layer (simple squamous) and the visceral layer (podocytes, which are modified epithelial cells with foot processes). The parietal layer lines the capsular space and appears as a simple squamous epithelium location with flattened nuclei. The visceral layer wraps around the glomerular capillaries and looks completely different under light microscopy—you need electron microscopy to see the foot processes clearly.
Get the Full Details

Practical Tips for Histological Identification
When staining, hematoxylin and eosin remains the gold standard, but the staining time affects visibility. Over-staining with hematoxylin makes the thin nuclei appear excessively dark and can obscure the cytoplasmic borders. I typically use 3-5 minutes for hematoxylin and 30-60 seconds for eosin in routine work. One counter-intuitive point: simple squamous epithelium can be difficult to identify in routine H&E sections because the cells are so thin that their cytoplasm barely stains. The nuclei stand out, but the cell boundaries may not be visible. This doesn't mean the tissue is poorly prepared—it's a limitation of light microscopy. Electron microscopy reveals the tight junctions and basement membrane details, but for routine histology, you identify simple squamous epithelium by the presence of a single layer of flattened nuclei with minimal visible cytoplasm. Another common pitfall is confusing simple squamous epithelium with the endothelium of sinusoids or the mesothelium of body cavities. These are technically different tissues—endothelium lines blood vessels and lymphatics, while mesothelium lines body cavities—but both are simple squamous in appearance. The distinction matters functionally but not morphologically under light microscopy.
For lung tissue specifically, I recommend using a scanning electron microscope when available. The alveolar surface area is enormous—approximately 70 square meters in an adult human—and the type I pneumocytes cover about 95% of this surface despite being extremely thin. Under scanning EM, you can see the endothelial cells of capillaries bulging into the alveolar spaces, creating the characteristic "cups" that the alveolar walls fit around. This intimate relationship between the epithelium and endothelium is what enables efficient gas exchange. When preparing sections, cut at 4-6 micrometers for lung and kidney tissue. Thinner sections make the alveolar walls nearly invisible, while thicker sections can cause overlapping structures that mimic stratified epithelium. I've found that 5 micrometers is the sweet spot for routine diagnostic work. There's a specific problem I encountered with renal biopsies where the Bowman's capsule parietal layer appeared to be stratified squamous epithelium due to tangential cutting. The section was taken at an angle that made the simple squamous layer appear as multiple layers of nuclei. The solution was to examine multiple serial sections and look for areas where the capsule was cut perpendicularly, revealing the true single-layer architecture.
Functional Correlations
The thinness of simple squamous epithelium directly correlates with its function. In the alveoli, the barrier between air and blood is approximately 0.5 micrometers thick, allowing rapid diffusion of oxygen and carbon dioxide. In the glomerular capillaries, the same thinness permits filtration of plasma while retaining blood cells and large proteins. One limitation to be aware of: simple squamous epithelium provides minimal protection against mechanical stress or abrasion. This is why it's only found in protected environments—inside the body, lined by other tissues or supported by underlying structures. If you see simple squamous epithelium in a location exposed to friction or trauma, suspect metaplasia or a pathological condition rather than normal anatomy. The turnover rate is another practical consideration. Endothelial cells in blood vessels have a half-life of several months to years in adults, meaning they're relatively stable. Alveolar type I pneumocytes, however, are terminally differentiated and rely on type II pneumocytes for repair. This has implications for recovery from lung injury—the epithelium regenerates slowly and incompletely compared to other tissues.

For identification purposes, remember that simple squamous epithelium appears different depending on the plane of section. In cross-section through a vessel, you see the endothelial nuclei as round or oval structures. In longitudinal section, they appear as elongated, flattened shapes. This variation can be confusing if you're not expecting it, so examine multiple planes before making a definitive identification. Finally, a note on staining artifacts: autolysis of simple squamous epithelium occurs rapidly after death or during prolonged ischemia. The nuclei may appear pyknotic or karyorrhectic, and the cell borders become indistinct. If you're examining post-mortem or biopsy tissue, check for preservation quality before committing to a diagnosis. Proper fixation within 30 minutes of collection makes a dramatic difference in diagnostic accuracy.


