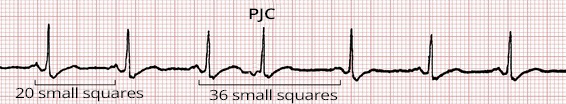
Understanding Sinus Rhythm With Premature Junctional Contractions on ECG
When you're reading 12-lead ECGs and see a rhythm strip that isn't perfectly regular, your first instinct should be to slow down and look at the P waves more carefully. Sinus rhythm with premature junctional contractions (PJCs) is one of those things that looks simple on paper but can trip up anyone who's not paying attention to the right details. The good news is that once you know what to look for, it's actually straightforward. The bad news is that missing the subtle clues can lead to calling something sinus arrhythmia when it's not, or worse, missing an underlying conduction problem. A normal sinus rhythm has a P wave before every QRS complex, the rate sits between 60 and 100 beats per minute, and the rhythm is regular. When you add premature junctional contractions into the mix, you're essentially dealing with two competing pacemaker sites: the SA node doing its normal job and the AV junction firing early on its own. The junctional focus is faster than it should be relative to whatever the SA node is doing at that moment, so it beats ahead of schedule and produces a QRS complex that arrives prematurely. The PJC itself typically produces a narrow QRS because the impulse travels down the normal His-Purkinje system rather than taking an abnormal ventricular pathway. That's the key difference from a premature ventricular contraction, which always has a wide, bizarre-looking QRS. The trickier part is what happens to the P wave. A junctional ectopic beat can fire before the SA node, during the SA node's normal firing, or after it. When the PJC fires early enough, the P wave often ends up buried inside or right after the QRS complex, making it invisible on the surface ECG. This is why you'll sometimes see what looks like a premature beat with no preceding P wave at all.
If the junctional impulse happens to travel retrogradely to the atria before it goes down to the ventricles, you'll see an inverted P wave before the QRS. In leads II, III, and aVF those inverted P waves point downward, which is the opposite of what you see in normal sinus rhythm. The PR interval when that retrograde P wave is visible is usually less than 120 milliseconds because the impulse has a much shorter distance to cover from the junction down to the ventricles than it does from the SA node through the AV node in a normal beat.
How to Identify PJCs Step by Step
Start by establishing whether the underlying rhythm is actually sinus. Look for upright P waves in leads I and aVF with a consistent PR interval. Once you've confirmed that baseline, scan for beats that arrive early. A premature beat on a sinus background should make you ask whether it has a P wave before it and whether that P wave looks like a normal sinus P wave or something different. Measure the pause that follows the premature beat. Complete compensatory pauses are classic for PVCs, meaning the rhythm returns to exactly where it would have been if the premature beat never occurred. Junctional premature beats usually produce an incomplete compensatory pause because the ectopic impulse often retrogradely depolarizes the SA node and resets its timing. This is one of the most reliable differentiators and it's something I've found myself going back to repeatedly over the years. Look at the QRS morphology. Narrow QRS with a premature timing points toward a supraventricular origin, which narrows it down to either a PAC or a PJC. From there, check for the P wave. If there's a visible P wave before the QRS and it's inverted in the inferior leads with a short PR interval, you're looking at a junctional premature beat. If the P wave is buried or absent, that's also consistent with a PJC. If the P wave looks normal and upright but the beat is still premature, it's probably a PAC instead.
Get the Full Details

The timing matters too. A sinus rate of 75 gives you a R-R interval of about 800 milliseconds. A PJC that arrives at 500 milliseconds after the previous QRS is premature by 300 milliseconds. That kind of numeric framing helps keep your assessments grounded rather than relying on a vague sense that something feels off rhythm.
Common Pitfalls When Reading Sinus Rhythm With PJC
One thing that catches people off guard is how easily a PJC can be mistaken for a PAC, especially when the premature beat has a visible P wave. The distinction really comes down to P wave morphology and the PR interval. Junctional P waves are inverted in the inferior leads because the atria are being activated from the bottom up rather than from the top down. PACs produce P waves that look similar to the underlying sinus P waves, just slightly different because they're coming from an ectopic atrial focus rather than the SA node. Most readers miss this distinction in the moment because they're focused on whether a P wave exists at all rather than what that P wave actually looks like. Another pitfall is confusing a blocked PAC with a PJC. Sometimes a premature atrial impulse arrives so early that it hits the AV node during its refractory period and fails to conduct to the ventricles. You see a premature P wave followed by a pause, but no QRS. This can look very similar to a non-conducted junctional beat, and the two require different clinical thinking. The blocked PAC scenario means you have an atrial ectopic focus firing aggressively, while a non-conducted junctional beat means the junctional focus is dominant. The distinction matters for management decisions. I ran into a particularly stubborn case a few years back where a patient had what appeared to be frequent premature beats with no visible P waves and narrow QRS complexes. My initial read was multifocal premature junctional contractions, but the beats were coming in such rapid succession that I couldn't clearly identify the underlying sinus P waves at all. What I eventually realized was that the patient had sinus rhythm with Wenckebach-type second-degree AV block, and what I was calling PJCs were actually dropped QRS complexes from the AV node. The workaround was to switch to a longer rhythm strip, slow the paper speed down to 25 mm per second to stretch things out visually, and then methodically mark every visible P wave regardless of whether a QRS followed it. That took about five extra minutes but completely changed my interpretation and the subsequent management plan.
Clinical Significance and When It Matters
Isolated PJCs in an otherwise healthy heart are generally benign. They don't carry the same prognostic weight as PVCs in patients with structural heart disease. The presence of PJCs alone rarely changes management. What matters more is the context: how frequent they are, whether they're occurring in runs, and what the underlying cardiac status is. Junctional tachycardias are a different story entirely. Sustained junctional tachycardia at rates above 100 can compromise cardiac output because you lose the atrial kick from proper SA node activation and atrial contraction. The junctional focus isn't coordinating with the atria the way normal sinus rhythm does, so ventricular filling suffers. This is something you'd see in post-cardiac surgery patients, in digoxin toxicity, or in certain inflammatory conditions affecting the AV node. Medications and electrolyte disturbances are common culprits when PJCs appear in a previously normal heart. Digoxin is the classic one because it increases automaticity of junctional tissue while simultaneously slowing AV nodal conduction. Hyperthyroidism can also accelerate junctional automaticity. Electrolyte abnormalities like hypokalemia and hypomagnesemia lower the threshold for ectopic beats from any origin, junctional included. When you're seeing new onset PJCs in a hospitalized patient, checking a basic metabolic panel and reviewing the medication list should be immediate steps rather than something you circle back to later.

The limitation I need to be blunt about is that surface ECG interpretation of PJCs has real constraints. You cannot determine the exact anatomical origin of a junctional ectopic focus from a standard 12-lead ECG. You also can't reliably distinguish between enhanced automaticity and reentrant mechanisms causing premature junctional beats without invasive electrophysiology studies. This means your clinical management is often based on pattern recognition rather than definitive mechanistic diagnosis, and that's fine for most situations but it's something to keep in mind when the case doesn't fit neatly into a textbook pattern.
Practical Approach to Documentation
When you're writing up an ECG interpretation that includes sinus rhythm with premature junctional contractions, be specific. Note the underlying sinus rate, the number of premature junctional beats per minute or per hour if you have a monitoring strip, the morphology of any visible retrograde P waves, and the compensatory pause characteristics. Mention whether the premature beats are unifocal or multifocal. If you're unable to confirm the junctional origin due to buried P waves and lack of distinguishing features, state that explicitly rather than defaulting to a blanket supraventricular premature beat classification. For monitoring scenarios, tracking the burden of PJCs over a 24-hour period using telemetry or Holter analysis gives you data that a single 10-second ECG strip simply cannot provide. A patient with two PJCs in a 10-second strip is a very different clinical picture from someone with 200 junctional ectopic beats per hour. The threshold for ordering additional workup or adjusting medications shifts substantially based on that quantitative information. Ultimately, reading sinus rhythm with premature junctional contractions is about pattern recognition refined by methodical verification. The beats look a certain way, the pause characteristics tell you where they're coming from, and the clinical context tells you whether you need to do anything about it or just document and move on. The mistakes happen when you skip the verification steps because the pattern looks familiar enough. It's always familiar enough until it isn't.