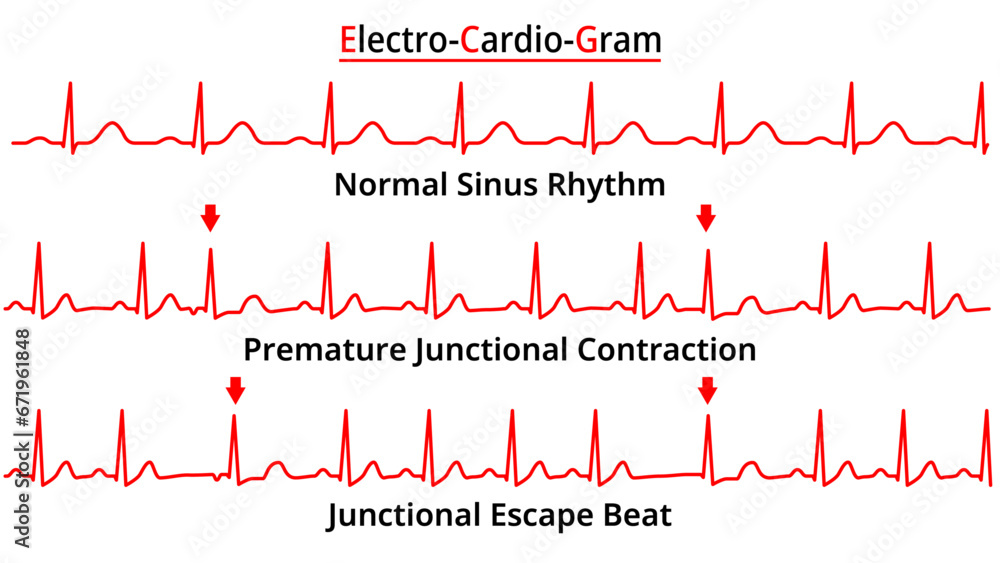
Reading Sinus Rhythm With Premature Junctional Contraction on a 12-Lead ECG
Most residential and small clinic ECG machines will label this automatically as "junctional ectopy" or just "PVC rule out," which is about as helpful as a screen door on a submarine. The machine doesn't know what it's looking at. You do. Or you don't. Let's talk about how to actually identify and interpret this rhythm when it shows up on your monitor or paper strip.Step-by-Step: Identifying Sinus Rhythm With Premature Junctional Contraction
Here is the practical workflow I use when I see an early beat on a strip and need to figure out whether it is junctional or ventricular. This is not textbook order. It is the order that saves time when you are looking at a busy monitor in real time. Step one: Count the rate and check regularity. Sinus rhythm with premature junctional contractions (PJC) usually presents with a baseline rate between 60 and 100 beats per minute, though the underlying sinus rate can be anything. The key is that the rhythm is mostly regular until the early beat interrupts it. Measure the R-R intervals before and after the premature complex. If the pause after the PJC is non-compensatory — meaning the interval from the beat before the PJC to the beat after it is less than two full sinus cycles — that is your first signal this is supraventricular in origin. Step two: Find the P wave. This is where most people mess up. In a premature junctional contraction, the P wave may be hidden inside the QRS, appear immediately before it, or appear immediately after it. If the P wave is buried, flip through leads II, III, and aVF. Sometimes you can see a negative deflection right before the QRS that the machine filtered out. If the P wave comes after the QRS, look for it in the ST segment or early T wave. A retrograde P wave in lead II will be inverted. That is the signature move of a junctional focus firing backward instead of forward.
Step three: Check the PR interval. If a P wave precedes the QRS, the PR interval will be short — typically less than 120 milliseconds. Junctional tissue conducts to the ventricles faster than the AV node does because it bypasses the normal conduction delay. A narrow QRS with a short PR confirms the impulse originated near the AV junction and traveled down the normal His-Purkinje system. If there is no visible P wave and the QRS is narrow, it is still junctional. The impulse just fired at the same time as the retrograde atrial depolarization. Step four: Rule out the mimics. An atrial premature beat can look identical to a PJC. The difference is the P wave morphology. Atrial premature P waves are upright in lead II when they come from the high right atrium. Junctional P waves are inverted in the inferior leads. Also watch for aberrant conduction — if the QRS is wide but the P wave is clearly retrograde, you are dealing with a PJC with functional bundle branch block, not a PVC. I have seen juniors call this a PVC three times in one shift before I got them to look at the P wave again. I ran into a specific case last year where a patient on a telemetry floor had frequent early beats that the monitor was calling PVCs. The QRS was narrow, the rate was 78, and the early beats were happening every fourth beat. I pulled the paper strip, measured the post-extrasystolic pause, and it was clearly non-compensatory. There was a retrograde P wave buried in the T wave of the preceding sinus beat — you could only see it if you laid a caliper on the paper and matched the T wave peak to the next QRS. Those were junctional bigeminy, not ventricular. The attending had already ordered a lidocaine drip. We stopped that and switched to observation. The PJCs resolved within 48 hours once we corrected the patient's borderline hypomagnesemia. If those had been treated as PVCs, the lidocaine would have been unnecessary and potentially harmful.
What Makes PJCs Clinically Relevant
A single or occasional PJC is almost never a problem. They show up in perfectly healthy people, especially during sleep or vagal predominance. The junctional focus is irritable and fires early. That is all. But when PJCs become frequent, they signal something about the autonomic tone or the electrical substrate of the heart. Common triggers include increased vagal tone, digoxin toxicity, inferior wall ischemia, and post-cardiac surgery inflammation around the AV node. I have also seen them cluster in patients with acute pulmonary embolism, where right heart strain changes the conduction dynamics. The context matters more than the beat itself. When PJCs are frequent — say, more than six per minute or running in runs — they can degrade cardiac output. The early beat fills the ventricle before the atria have contributed their full preload. The ventricle is less compliant at that point. You lose the atrial kick on every premature contraction. In a healthy heart this is negligible. In a heart with diastolic dysfunction or significant mitral stenosis, it can drop blood pressure measurably. I had a patient with hypertrophic cardiomyopathy who became symptomatic — lightheaded, borderline hypotensive — specifically because the PJCs were stealing atrial contribution on a near-regular basis. Treating the underlying trigger fixed it. Antiarrhythmics were not needed.
Get the Full Details

Common Pitfalls When Interpreting Sinus Rhythm With Premature Junctional Contraction
The biggest mistake is calling every early narrow beat a PJC without checking the pause pattern. Atrial premature beats also have non-compensatory pauses. The differentiator is the P wave axis, not the timing. If you skip the P wave analysis, you will misclassify half the beats you see. Another trap is assuming a junctional rhythm means AV node disease. It does not. Junctional escape rhythms and accelerated junctional rhythms indicate that the SA node is failing or blocked, yes. But premature junctional contractions in an otherwise normal sinus rhythm usually mean the junctional tissue is just irritated. It is a sign of excitability, not structural disease. Telling a patient their heart has a "secondary pacemaker problem" when they actually have stress-induced junctional irritability is unnecessary alarm and not accurate. The third pitfall is overtreating. I cannot stress this enough. There is no guideline recommendation for antiarrhythmic therapy for asymptomatic PJCs. Beta blockers or calcium channel blockers are sometimes prescribed off-label if the patient is very symptomatic, but the evidence is thin. The rhythm usually resolves on its own once the underlying cause is addressed. I once spent twenty minutes explaining to a worried resident that doing nothing was the correct intervention for a telemetry patient with isolated PJCs and a structurally normal heart. He kept asking if we should start amiodarone. We did not. The PJCs stopped on day three without any medication.
When to Escalate and When to Walk Away
If you are seeing frequent PJCs on a monitor, check the patient, not the strip. Are they hypotensive? Symptomatic? Ischemic? If the answer is no to all three, document it and move on. Repeat the ECG in a few hours if the burden is high. Check electrolytes — potassium and magnesium are the usual suspects. Review medications. Digoxin, sympathomimetics, and anticholinergics can all precipitate junctional ectopy. If the PJCs are running into non-sustained junctional tachycardia — that is, a run of three or more consecutive junctional beats at a rate above 100 — that warrants a deeper workup. Echocardiogram, ischemic evaluation, and medication review become necessary. Sustained junctional tachycardia is rare in adults and usually points to digoxin toxicity or post-surgical inflammation. There is no downloadable reference chart that replaces this process. The ECG is the tool. Your eyes and your measurement habits are the instrument. Practice calipering strips until you can measure PR intervals and pause relationships without thinking about it. It takes about two weeks of deliberate practice to get fast at it. After that, you will spot these by pattern recognition alone.


