Getting Your Occlusion Journal Actually Useful Instead Of Being Another Paperweight
Most dentists I see never use their occlusion journals properly. They either skip them entirely or fill them out like they are doing a compliance audit for someone who will never read it. The Six Keys To Occlusion Journal method exists because the standard approach generates garbage data that nobody acts on. I have spent years watching people mess this up in my clinic and in courses I run. Here is what actually works.Six Keys To Occlusion Journal
What The Six Keys Actually Are
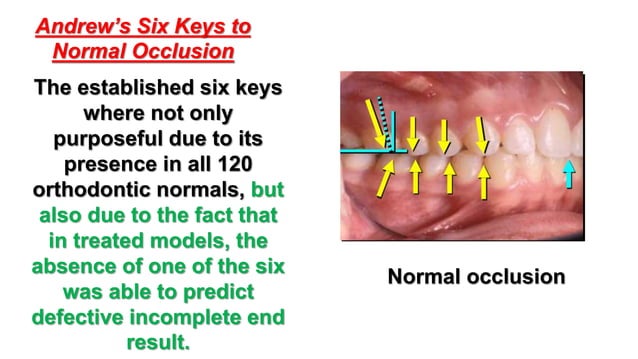
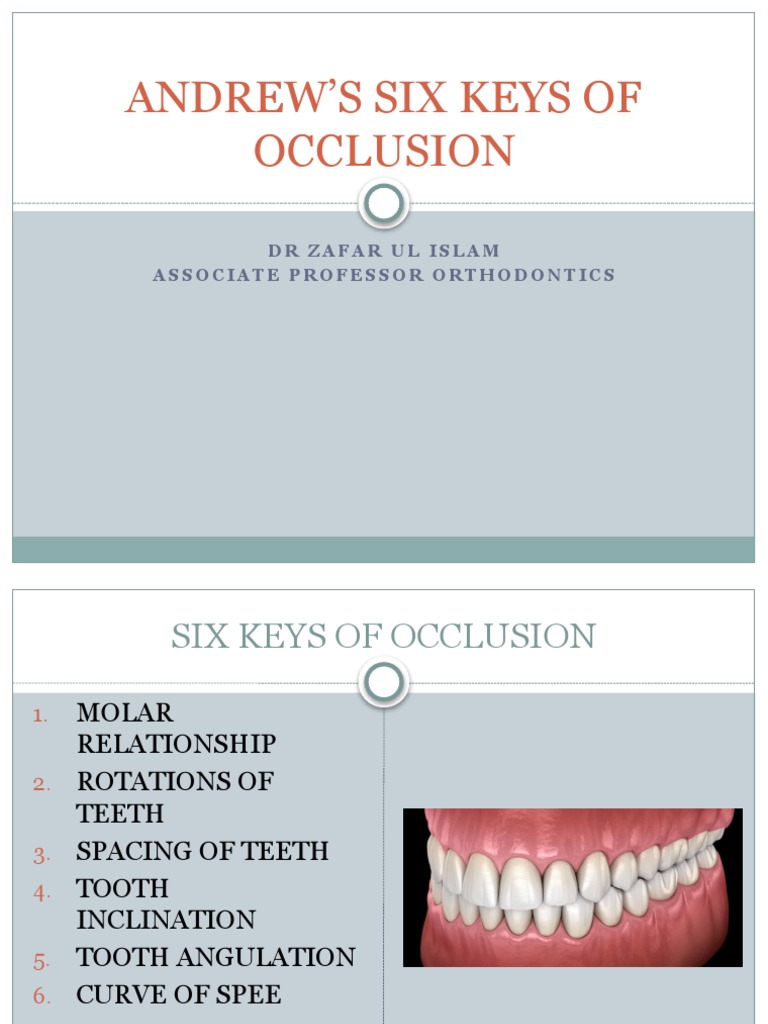
The six keys are not a rigid checklist you tick off in order. They are overlapping categories that map the entire occlusal relationship during function. If you only look at static centric relation, you are missing half the picture. The keys break down into: centric relation registration accuracy, anterior guidance pattern, canine guidance integrity, posterior disclusion during excursions, freeway space consistency, and neuromuscular stability over time. I used to think key three was the most important. That changed after I had a patient come back three months post equilibration with the exact same TMD symptoms she had before. We had nailed canine guidance perfectly. We had missed that her freeway space had decreased by four millimeters between visits. Her condyles had shifted because of muscle splinting that never got addressed. Fixing just the guidance without locking in stable vertical dimension was like putting a new tire on a car with bad suspension.
How I Actually Use This In The Chair
Here is the workflow I go through now. It takes about twelve minutes per patient once you stop second guessing yourself. First I record the centric relation bite using a product that actually holds. Calibré wax works but tears if the patient talks during it. I switched to a dual-viscosity silicone material and that solved the registration accuracy problem for most cases. The trick is getting the patient to close slowly without guidance from you. If you guide them, you are not recording CR, you are recording whatever muscular habit they already have. Second I check anterior guidance. I need to see clear contact on the anteriors during protrusive movement with no posterior interference. I use 80 micron articulating paper. Not the thick blue stuff. The thin red or green paper that actually shows micro contacts. If I see posterior marks during protrusion, I document where and whether they are heavy or light. Heavy is a problem. Light might be acceptable depending on the case.
Third is canine guidance. During lateral excursion I need to see disclusion of all posterior teeth on the working side. If I get any posterior contact marks, those are interferences. I mark them with a small dot and note the tooth number. This part of the journal entry is where most people get lazy. Write down the exact tooth number. Not "premolar area." I mean number 27 or 14. Something specific. Fourth is posterior disclusion. This ties directly into the canine guidance check. I also want to verify that there is no group function happening unless that is the intentional design for that patient. Group function is not inherently bad but it needs to be documented because it changes the load distribution. Fifth is freeway space. I measure this before treatment and after any occlusal adjustment. The norm is roughly two to four millimeters. If it drops below two, something is wrong. Could be muscle spasm. Could be that the patient is clenching through the bite registration. Could be a failing restoration pushing the bite open unevenly.
Get the Full Details

Sixth is neuromuscular stability. This is the one nobody checks consistently. I have patients return at three month intervals after any occlusal work and I re document everything. The goal is to see if the patterns hold. If canine guidance was perfect day one but degraded by month three, something is moving that we missed initially.
A Specific Problem I Ran Into And How I Fixed It
Two years ago I had a case where the occlusion journal entries looked perfect every single visit. All six keys checked out. Static and dynamic everything was clean. The patient still complained of jaw fatigue by afternoon. We were going in circles for six months until I started paying attention to a detail that the journal format almost encouraged me to gloss over. The patient had a deep bite with minimal over open. Her freeway space measurements were technically within the two to four millimeter range but they varied by almost two millimeters between visits. That variation should have been a red flag. The journal template I was using had a single line for freeway space. I was writing one number and calling it done. I changed my approach. I started taking three freeway space measurements per visit at different points along the arch. The inconsistency was right there. Her right posterior freeway space was consistently one millimeter less than the left. She had a subclinical asymmetrical habit pattern that was never showing up in the standard journal entry. I adjusted the splint therapy to account for the asymmetry and the symptoms resolved within eight weeks.
The lesson was that the Six Keys To Occlusion Journal framework is only as good as the granularity of the data you put into it. A template that asks for a single value where variability matters is a trap.

Counter Intuitive Things Beginners Miss
One thing that always surprises people is that perfect anterior guidance does not guarantee posterior protection. You can have beautiful canine disclusion and still have posterior crashes during fast movements. Speed matters. Most articulators and even visual checks are done slowly. Patients do not chew slowly. I sometimes use a quick snap test with thin shim stock between posterior teeth during rapid mandibular movement to catch fast interferences that slow examination misses. Another one is that high frequency of journal updates does not equal better outcomes. I see a lot of clinicians making daily occlusal notes after every adjustment. That is usually noise. Three month check-ins with full six key documentation gives you trend data. Daily notes give you anxiety and a ten page journal that means nothing.
When This Method Falls Apart
The Six Keys To Occlusion Journal approach assumes you have a cooperative patient. It assumes they can close into CR without sliding into MIP. It assumes they will follow through with return visits. Full mouth reconstruction cases with significant neuromuscular instability often break the model. In those situations the journal becomes a stream of conflicting data because the system is too chaotic to stabilize. For bruxers with severe muscle hypertrophy, the journal entries during active bruxism phases are essentially useless for treatment planning. I switch to a simplified logging system for those patients. Just track symptoms and freeway space. The detailed six key assessment waits until the bruxism activity calms down, usually after a hard stabilization splint trial for at least eight weeks. If you are working with patients who have TMJ internal derangement with disc displacement without reduction, the six keys framework needs modification. Closed lock patients cannot always achieve the range of motion needed for proper excursive checks. Forcing the movement creates more problems than it solves. I document what I can and note the limitation clearly in the journal so the next clinician knows why certain keys were incomplete.
Getting The Journal System
There is no single official Six Keys To Occlusion Journal form that everyone uses. Different programs adapt it differently. I have seen versions from ACE Academy materials, different prosthodontic societies, and standalone clinical tools sold through dental supply channels. When I look for a download, I check the Academy of Comprehensive Care archives and the American College of Prosthodontists member resources. Those tend to have the most clinically tested templates. If you are building your own, the format I use has six main sections matching the keys above plus a running log area at the bottom for tracking changes across visits. One page per patient per visit keeps it manageable. Two pages gets unwieldy and nobody finishes it. The whole point of the Six Keys To Occlusion Journal is not paperwork. It is creating a record that actually predicts what will happen when you adjust, restore, or equilibrate. Most of us were never taught to look at occlusion as a dynamic system. This framework forces you to. That is why it matters and why so many people still ignore it.