Understanding Muscle Tissue Types in the Human Body
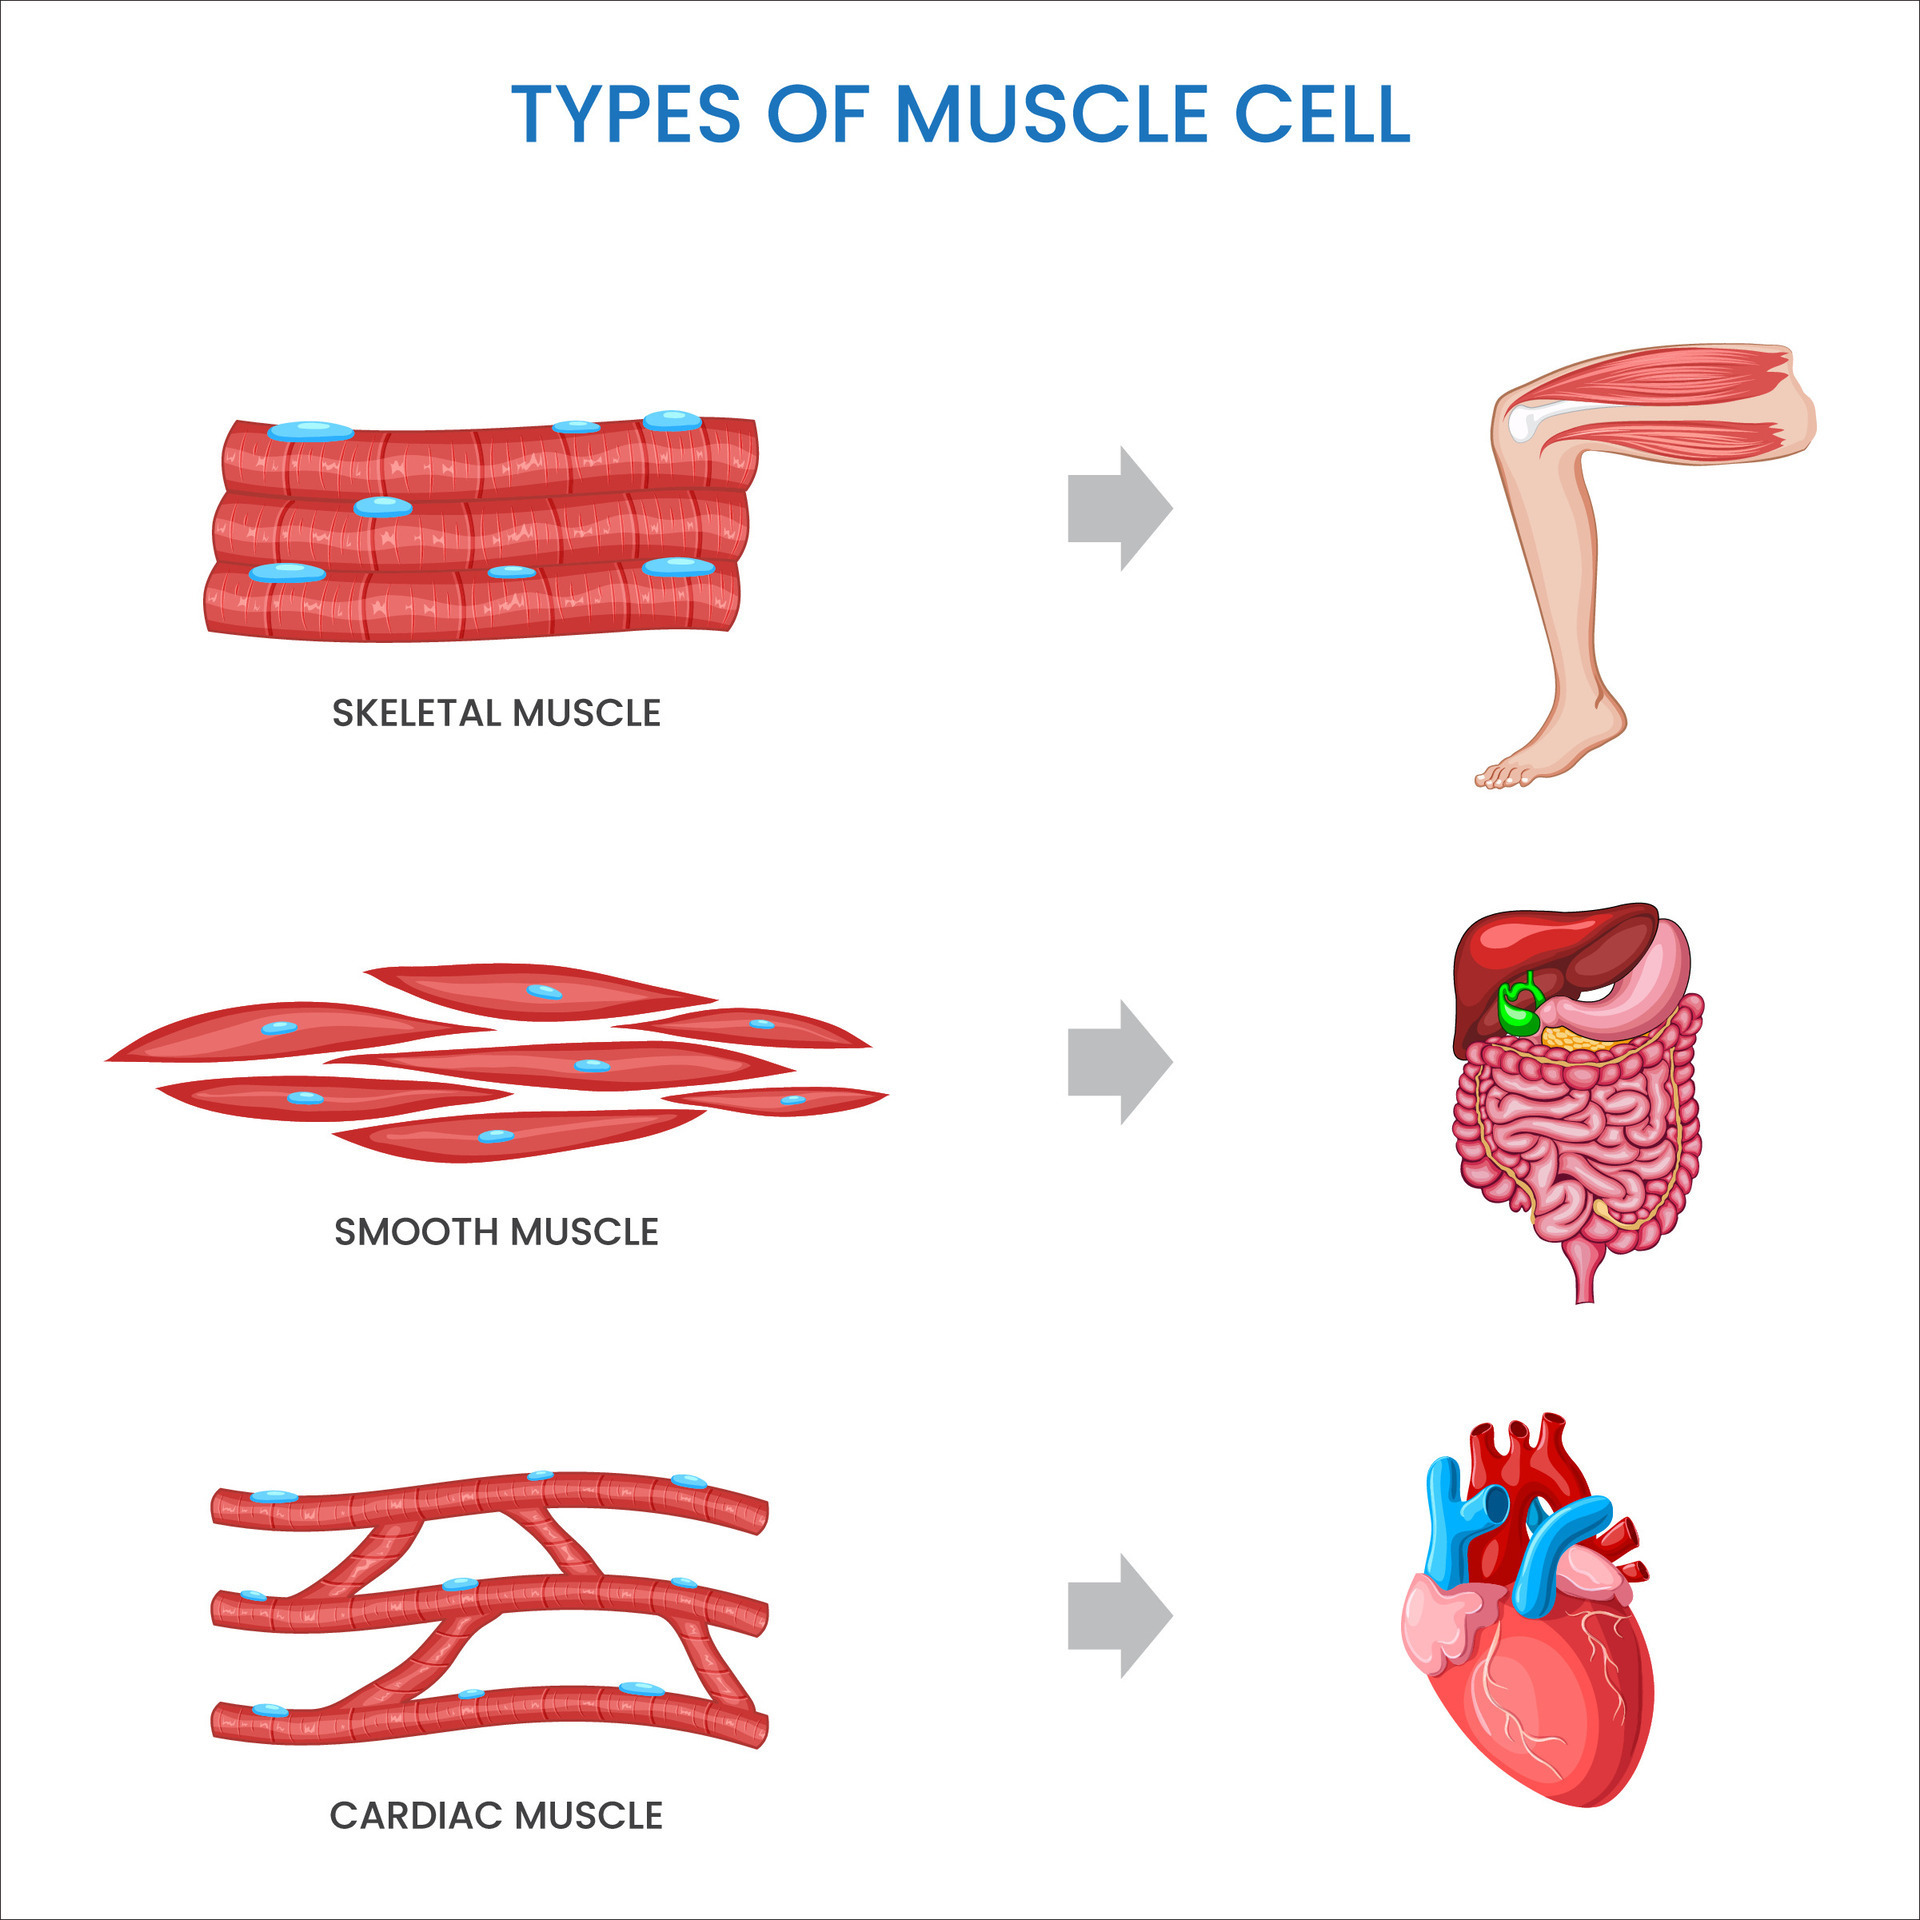
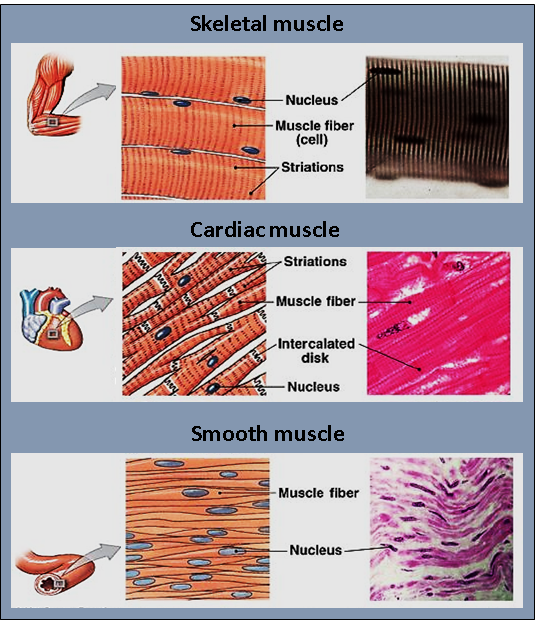
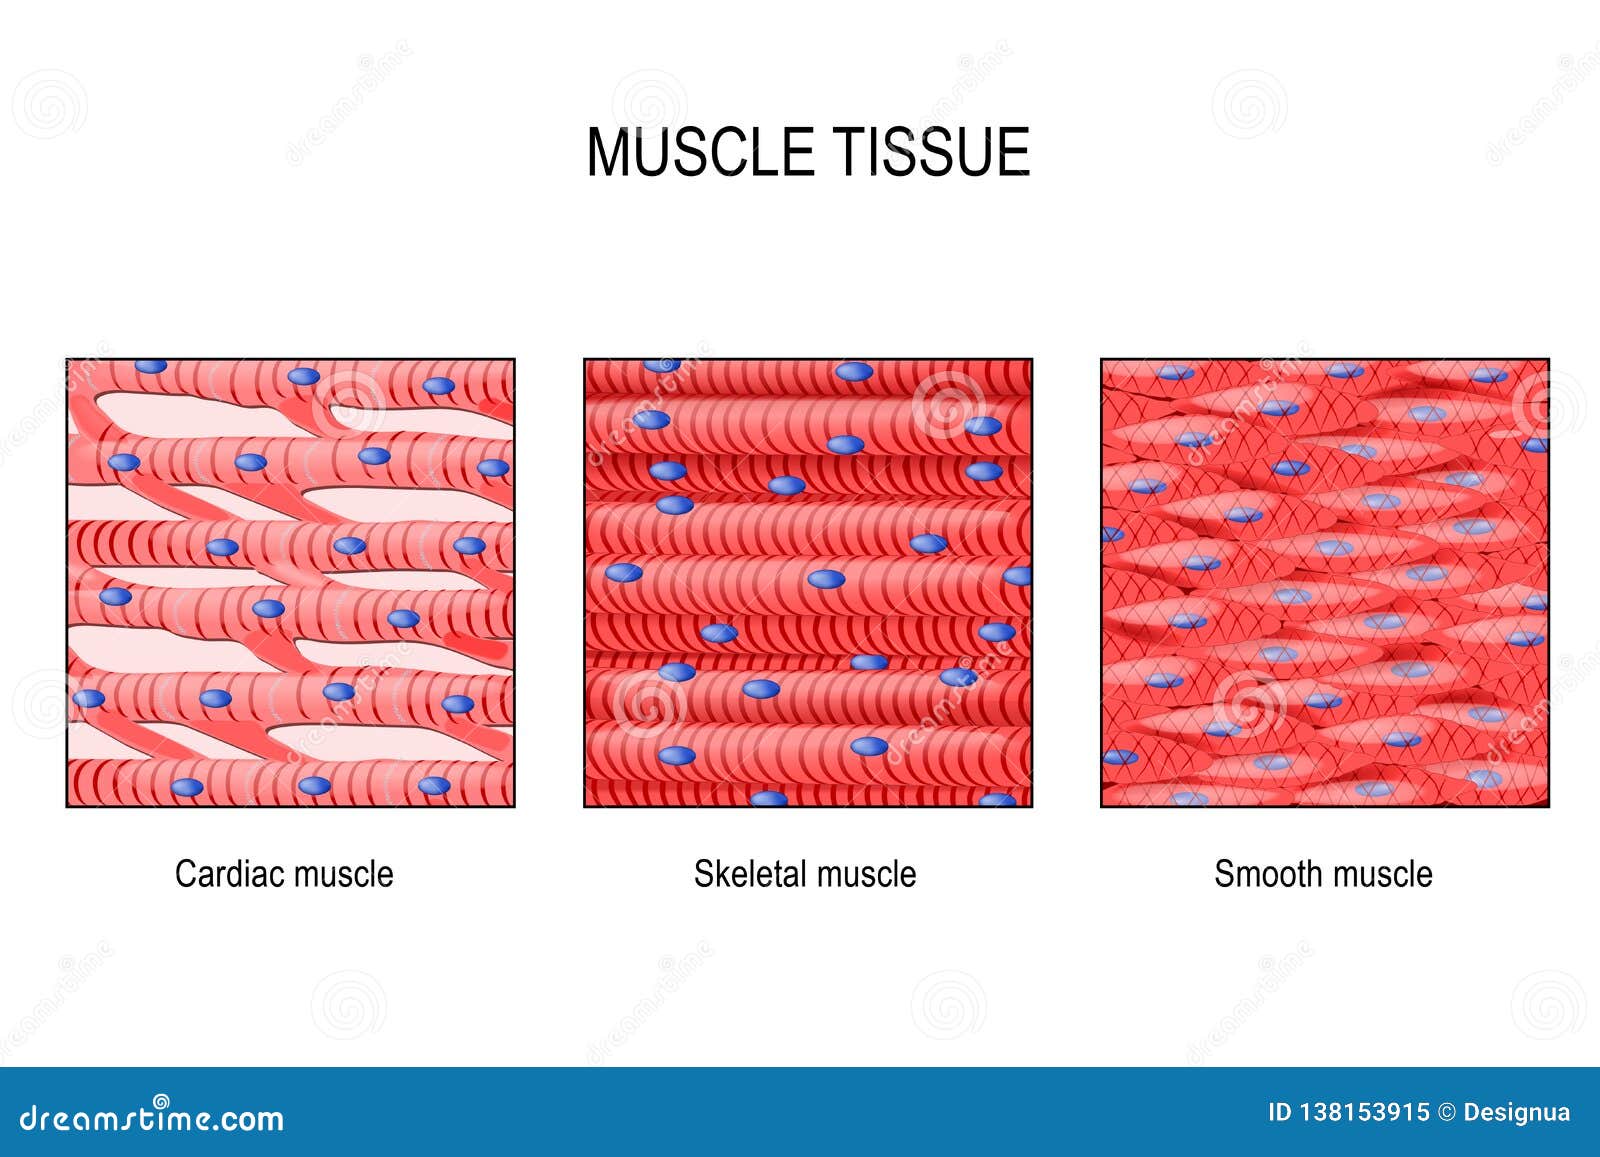
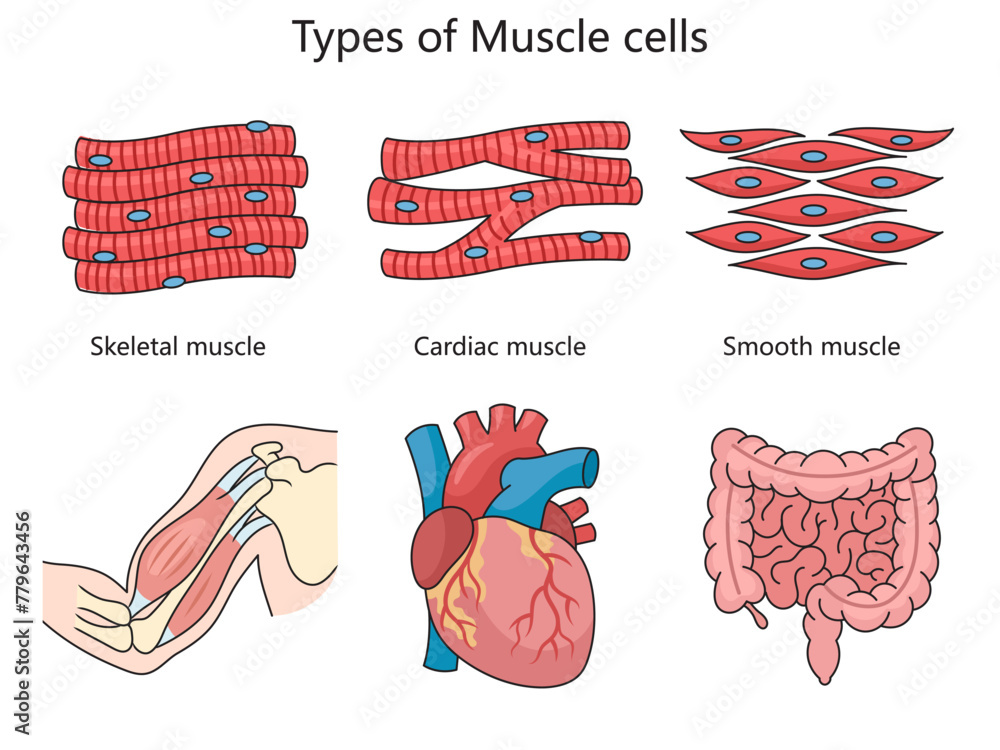
When I first started studying anatomy in med school, I used to mix up the different muscle types all the time. There are three main kinds of muscle tissue, and each has its own structure, function, and control mechanism. The key is knowing when something is voluntary versus involuntary, and how the cellular machinery actually works under a microscope. Skeletal muscle is what most people think of when they hear "muscle." It's attached to your bones, and you control it consciously. When you decide to lift your arm or kick a ball, skeletal muscle fibers contract. These fibers are long, cylindrical, and multinucleated, with obvious striations visible under magnification. The striations come from the organized arrangement of actin and myosin filaments in repeating units called sarcomeres. Each skeletal muscle fiber is a single cell with multiple nuclei positioned at the periphery. They require calcium from the sarcoplasmic reticulum to trigger contraction, and acetylcholine at the neuromuscular junction to initiate the signal. I spent hours practicing identifying skeletal muscle in histology slides during my first year. The trick is recognizing the peripheral nuclei and the clear banding pattern. One thing that always confused me was distinguishing between longitudinal and cross-sections. In cross-section, you see individual polygonal fibers with nuclei pushed to the edges. In longitudinal section, the striations run perpendicular to the fiber axis. If you're looking at a slide and can't tell which is which, rotate the sample mentally or check the nucleus position again.
Cardiac muscle is found only in the heart wall. It shares some features with skeletal muscle but has critical differences. Cardiac muscle cells are shorter, branched, and typically have one or two central nuclei. The striations are present but less regular than skeletal muscle. The key identifier is the intercalated disc, a specialized junction between cells that allows rapid electrical coupling. These discs contain gap junctions for ion flow and desmosomes for structural integrity. Cardiac muscle is involuntary, controlled by the autonomic nervous system and intrinsic pacemaker cells. The calcium handling in cardiac muscle is different from skeletal. Cardiac myocytes rely on calcium influx from the extracellular space through L-type calcium channels, which then triggers release of more calcium from the sarcoplasmic reticulum. This is called calcium-induced calcium release. It means certain medications like beta-blockers affect cardiac contractility by blocking these channels. I once saw a patient on verapamil, a calcium channel blocker, who developed significant hypotension because the drug reduced cardiac output more than intended. The workaround was adjusting the dosage and monitoring blood pressure closely every few hours. Smooth muscle is found in the walls of hollow organs, blood vessels, and the iris of the eye. These cells are spindle-shaped with a single central nucleus and no striations. They lack the organized sarcomere structure entirely. Smooth muscle contraction is slower and more sustained than skeletal or cardiac. The regulation involves calmodulin and myosin light chain kinase rather than troponin. Calcium binds to calmodulin, activating the kinase, which phosphorylates myosin to enable cross-bridge cycling.
I encountered a tricky case with gastrointestinal smooth muscle during my rotation. A patient had abnormal motility after surgery, and we couldn't determine if it was ileus or partial obstruction. The workaround was using contrast imaging followed by checking for bowel sounds and abdominal distension every four hours. If the patient couldn't pass gas within 48 hours, we considered surgical intervention. This usually takes about 24 to 72 hours to resolve, depending on the cause. One counter-intuitive point about smooth muscle is that it can maintain contraction with very little energy expenditure. This is called the latch state, where cross-bridges cycle slowly while maintaining tension. It's why vascular smooth muscle can constrict blood vessels without tiring. Skeletal muscle cannot do this; it requires constant ATP turnover to maintain contraction and fatigues quickly. This difference explains why smooth muscle is suited for sustained tone in blood vessel walls and why skeletal muscle is designed for rapid, forceful movements. Another nuance beginners miss is that all three muscle types can be affected by the same diseases but present differently. For example, muscular dystrophies primarily target skeletal muscle, causing weakness and atrophy. Cardiomyopathies affect cardiac muscle, leading to heart failure. Vascular smooth muscle can undergo hypertrophy in response to chronic hypertension, narrowing the vessel lumen. Recognizing these patterns helps in differential diagnosis and treatment planning.
Get the Full Details
There are limitations to this framework. Some tissues contain mixed muscle types, like the iris, which has both smooth and skeletal muscle components. The outer layer of the esophagus contains skeletal muscle, while the inner layer is smooth. This transition zone can be confusing when studying histology slides. Additionally, some smooth muscles, like those in the uterus, can exhibit spontaneous contractions similar to cardiac muscle. Understanding these exceptions prevents oversimplification. If you're studying for exams, focus on the control mechanisms. Skeletal muscle is somatic, cardiac is intrinsic with autonomic modulation, and smooth is autonomic with local factors. Know the calcium sources, the regulatory proteins, and the structural features. Practice identifying them in slides, and don't rely solely on textbook descriptions. Real histology samples can be messy, and you need to recognize the key features quickly under time pressure.