Understanding What Actually Happens When You Tear a Muscle
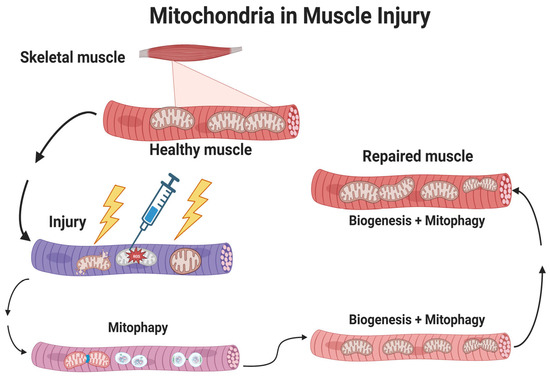
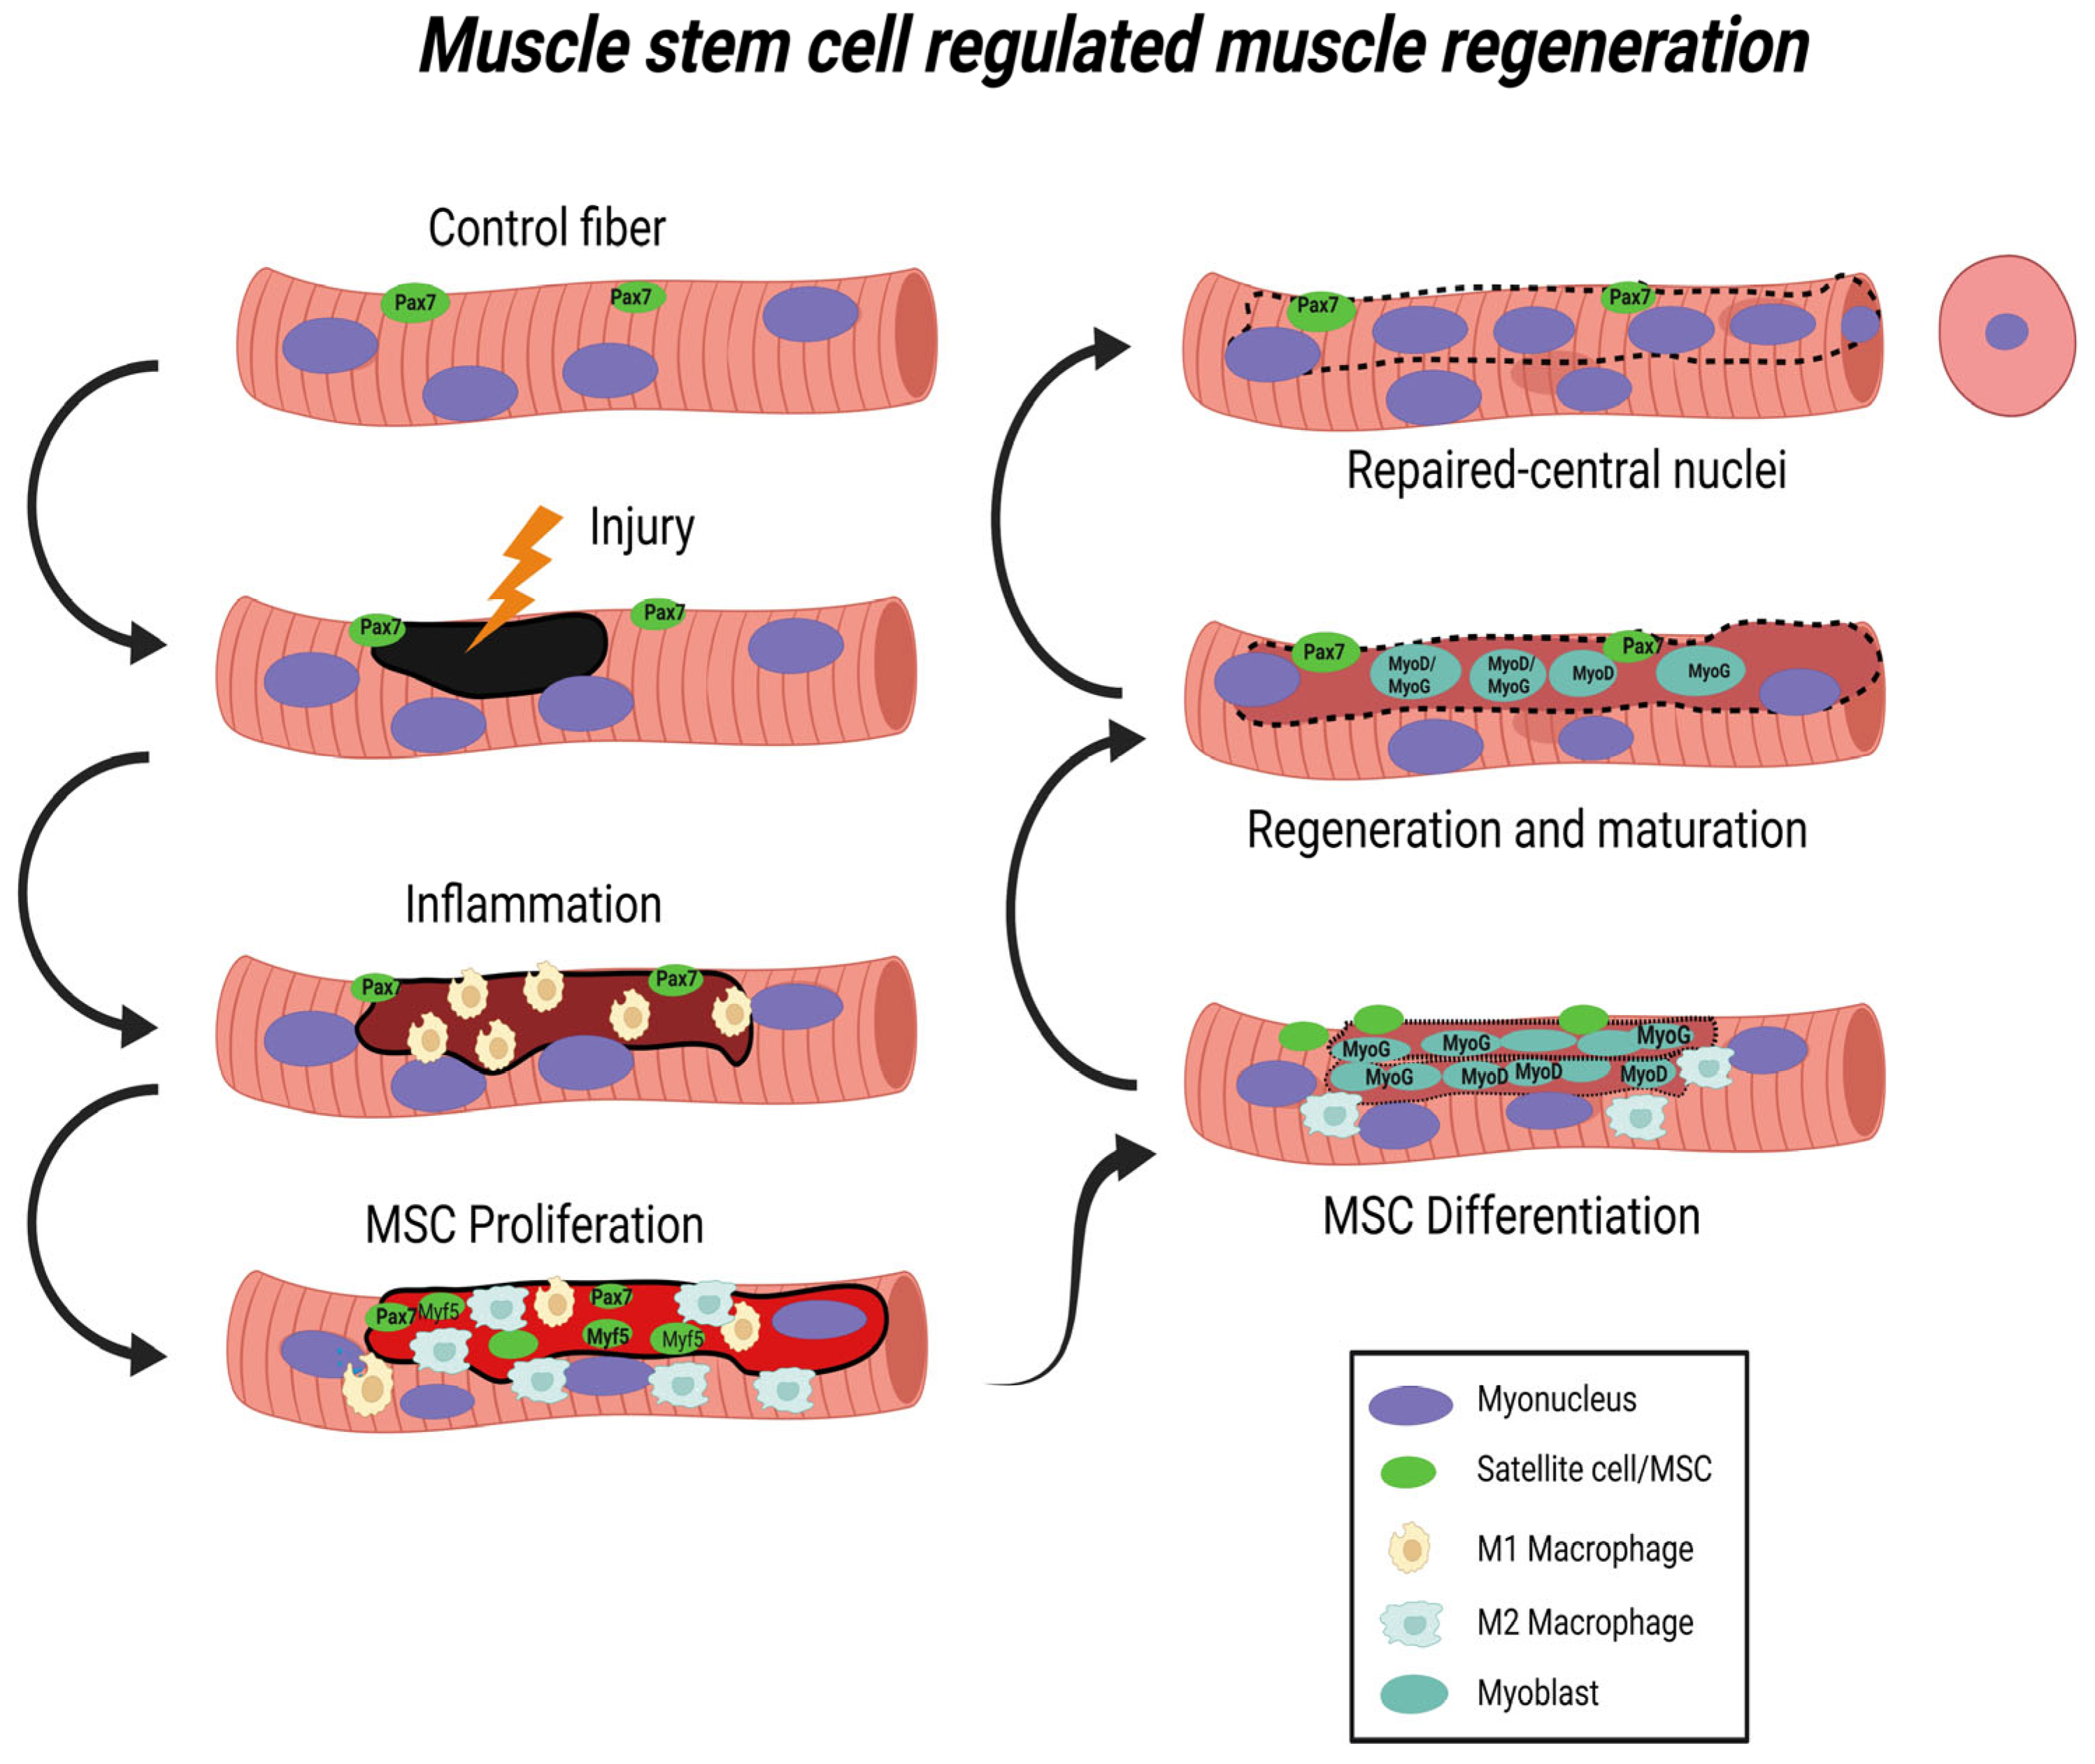
Skeletal muscle damage and repair is one of those topics where everything you think you know from a fitness blog is probably wrong or at least misleading. I have spent years watching people try to speed this process up with supplements, ice, compression, and every other protocol you can find on the internet. Most of it is noise. A small amount is actually useful. The rest is just expensive reassurance. Here is the basic mechanism without the fluff. When you damage skeletal muscle — whether from eccentric loading, trauma, or sustained isometric tension — the muscle fibers themselves tear. This triggers an inflammatory cascade. Neutrophils arrive first, clearing debris. Then macrophages take over. M1 macrophages are pro-inflammatory and destructive. M2 macrophages are anti-inflammatory and regenerative. The switch from M1 to M2 is where everything depends. If that transition drags on, you get fibrosis. Scar tissue replaces functional muscle. That is the worst outcome, and it is far more common than people realize.
The Skeletal Muscle Damage And Repair Process in Practice
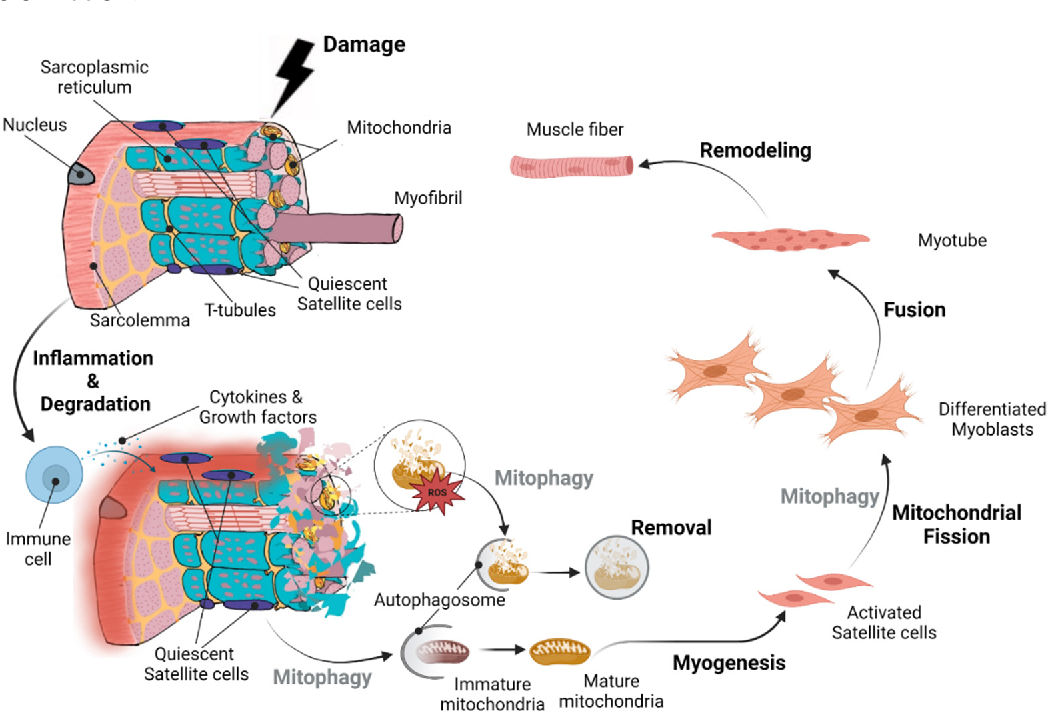
Satellite cells are the real players here. They sit between the sarcolemma and the basal lamina in a quiescent state. Once damage signals arrive — primarily through mechanical stress and inflammatory cytokines like IL-6 and TNF-alpha — they activate, proliferate, and differentiate into myoblasts. These fuse to the damaged fiber or to each other to form new myofibers. This whole process takes roughly 3 to 14 days depending on severity. A mild strain might resolve in under a week. A grade 2 tear can take 4 to 6 weeks, and even then the strength return is rarely linear. I remember a specific case a few years back where a client came in with what looked like a routine hamstring strain. Standard protocol would have been rest, ice, gentle stretching, and gradual loading. But something about the presentation was off. The injury was on the proximal hamstring near the ischial tuberosity, which is already a low-blood-flow zone. I pushed for an MRI and it confirmed a partial avulsion with some retraction. This is not a tear that heals well with conservative management alone. Blood flow to that region is inherently poor, satellite cell recruitment is limited, and the mechanical tension across the repair site during normal walking is significant. We modified the protocol. Instead of the standard RICE approach, we started with relative rest for five days — not complete immobilization, because that causes atrophy and adhesions — then moved into controlled eccentric loading at 30 percent of maximum voluntary contraction. The key was keeping the hip in flexion during early rehab to reduce tension on the proximal attachment. Once the hamstring was in a shortened position, the repair site was protected. We progressed slowly over eight weeks. He returned to sport at week ten with full function. Without that MRI, he would have been told to ice it and come back in two weeks. That would have been a mistake.
The counter-intuitive part that most people miss is that complete rest during the early phases is actually detrimental. Immobilization for more than a few days after injury reduces satellite cell proliferation and increases collagen deposition in the wrong orientation. Light mechanical loading within the first 48 to 72 hours, if done carefully, actually accelerates repair by stimulating satellite cell activity and aligning new fibers along the line of stress. This is not about pushing through pain. It is about applying sub-threshold mechanical stimuli that signal the tissue to rebuild properly. Another thing people get wrong is the timing of anti-inflammatory use. NSAIDs are commonly recommended immediately after muscle injury. But inflammation is not the enemy here. The inflammatory phase is necessary for clearing damaged tissue and signaling satellite cell recruitment. Blocking it with ibuprofen or similar drugs in the first 48 hours has been shown in multiple studies to delay regeneration and reduce final muscle strength. That does not mean you should never use them. If pain is preventing basic movement and sleep, a short course is reasonable. But using them prophylactically to eliminate all inflammation is counterproductive. Nutrition matters more than most protocols acknowledge. Protein intake during the repair phase should be at least 1.6 grams per kilogram of body weight per day, distributed across four to five meals. Leucine is the critical amino acid trigger for mTOR activation, which drives protein synthesis in the damaged tissue. A dose of 2 to 3 grams of leucine per meal is approximately what you get from 25 to 30 grams of whey protein or 100 grams of chicken breast. Without adequate leucine signaling, satellite cell differentiation slows significantly regardless of total protein intake.
Get the Full Details

Omega-3 fatty acids have a nuanced role. They do not simply reduce inflammation in a blanket way. Instead, they modulate the inflammatory response, helping the M1-to-M2 macrophage switch happen faster and more cleanly. This reduces the window during which fibrosis can develop. A dose of 2 to 3 grams of combined EPA and DHA daily during the repair phase is supported by the literature. That is a pharmaceutical-grade dose, not what you get from eating fish once a week. Vitamin D status is another overlooked factor. A large portion of the population, especially those who train indoors, are suboptimal in vitamin D. Receptors for vitamin D are present on satellite cells, and insufficiency has been linked to delayed muscle regeneration and reduced force production during recovery. Getting levels checked and supplementing to reach a serum 25(OH)D concentration above 30 ng/mL is a low-cost intervention with measurable impact on repair speed. Sleep is non-negotiable. Growth hormone pulses during deep sleep directly support tissue repair. One study showed that restricting sleep to four hours per night for five consecutive nights reduced myogenic progenitor cell function by roughly 60 percent. That is not a small number. Poor sleep does not just make you feel tired. It directly impairs the cellular machinery responsible for rebuilding muscle. Seven to nine hours per night during an active repair phase is the minimum, not a recommendation.
What Most Protocols Get Wrong
The most common mistake I see is rushing back into loading too aggressively. The misconception is that if it does not hurt, it is healed. It is not. Pain does not equal structural integrity restored. Histological studies show that even after pain subsides and range of motion is normal, the repaired tissue is biomechanically weaker for several more weeks. The collagen network is still disorganized. The cross-sectional area of new myofibers is smaller. Returning to high-load activities at this stage significantly increases re-injury risk, and re-injuries heal worse than the original damage. Another widespread error is over-reliance on modalities like ultrasound, laser therapy, and electrical stimulation. The evidence for these is mixed at best. Low-level laser therapy has some support for reducing pain and inflammation, but the effect sizes are small and the optimal parameters are not well standardized. Therapeutic ultrasound shows inconsistent results across studies. Electrical stimulation can help maintain muscle activation during early rehab when voluntary contraction is limited, but it does not accelerate the repair process itself. None of these replace proper loading, nutrition, and time. Myofascial release and aggressive stretching in the acute phase can actually worsen the injury. Stretching a healing muscle fiber before the sarcolemma has rebuilt its integrity creates micro-tears in the repair site. This is why passive stretching is typically contraindicated for the first week or two after a moderate strain. Gentle active range of motion within a pain-free range is preferable. Let the tissue heal under minimal tension before introducing stretch loads.
The concept of treating through pain is probably the most damaging advice in the repair process. There is a difference between discomfort from stiffness and sharp pain from tissue strain. The first is manageable. The second means you are re-damaging the repair site. I have seen athletes push through sharp pain during rehab and end up with chronic tendinopathy or recurrent strains because the initial damage was never allowed to consolidate properly. Pain is a signal, not a challenge to overcome.

Realistic Timelines and Expectations
Grade 1 strains — microscopic fiber disruption with minimal strength loss — typically resolve in 1 to 3 weeks with appropriate management. Grade 2 strains — partial tears with noticeable strength and function deficits — require 3 to 6 weeks. Grade 3 strains — complete tears — may require surgical intervention and 4 to 6 months of rehabilitation. These are general estimates. Individual variation is significant based on age, training history, nutrition, sleep quality, and the specific muscle involved. Proximal hamstring and adductor injuries tend to have longer and more complicated courses than distal injuries. This is partly due to blood supply and partly due to the higher mechanical loads these regions endure during daily activities. A distal biceps strain might be manageable in three weeks. A proximal hamstring avulsion of similar size could take three months to return to sport safely. Location matters more than grade in some cases. Older adults repair muscle more slowly due to reduced satellite cell function and hormonal changes. The repair mechanisms are not broken, they are just less efficient. This is not a reason to avoid loading during rehab. It is a reason to be more patient and to prioritize protein intake and resistance training over passive modalities. The principles remain the same. The timeline just stretches.
When to Seek Professional Evaluation
If you experience a pop or snap at the time of injury, significant bruising within the first 24 hours, visible deformity, inability to bear weight or use the limb, or pain that does not improve after three to five days of conservative care, get imaging. These are signs of a more serious injury that may not respond to standard management. A Grade 2 or 3 tear that is mismanaged early on can result in permanent strength deficits and a higher likelihood of re-injury. Early accurate diagnosis saves time in the long run, even if it feels like an unnecessary expense in the moment. MRI is the gold standard for assessing the extent of muscle damage. It shows the location, size, and severity of the tear, as well as any hematoma or fluid collection. Ultrasound is a reasonable alternative for dynamic assessment and follow-up, though it is operator-dependent. X-rays rule out bone involvement but do not show soft tissue damage. Don't let anyone tell you that an X-ray was sufficient to clear a suspected muscle tear. It was not. The bottom line is that skeletal muscle damage and repair follows predictable biological timelines. There is no shortcut that bypasses inflammation, satellite cell activation, and organized collagen deposition. The interventions that actually move the needle are controlled loading, adequate protein and leucine, omega-3s, vitamin D optimization, and sleep. Everything else is supportive at best. Understand the process, respect the timeline, and you will recover faster and stronger than someone who tries to force it.