
Getting Started With Posterior Skeleton Anatomy
Most students and technicians approaching the skeletal system posterior view answer key are doing it for cadaver lab prep, radiology certification, or gross anatomy coursework. The material itself is straightforward, but the way the answer key is typically structured creates a lot of unnecessary friction. I need to explain how to actually use it rather than just describing what it is, because reading through a key linearly from top to bottom wastes about forty percent of study time if you aren't paying attention to how the labels are organized. The posterior view is deceptively simple compared to the anterior. You see the spine running straight down the middle, the scapulae on both sides, the pelvic bones, and the long bones of the upper and lower limbs. What people don't expect is how many overlapping structures there are. The trapezius attachment sites, the nuchal line variants, the sacral cornua, and especially the relationship between the iliac crest and the posterior superior iliac spines — these are the landmarks that show up on every practical exam and trip everyone up at the same time.
How to Use a Skeletal System Posterior View Answer Key Without Wasting Time
Start by identifying the major bone groups before you look at any labels. The axial skeleton comes first — skull, vertebral column, ribs, sternum — then the appendicular skeleton, girdles and limbs. If you go label by label without this framework, you will misidentify structures constantly because your brain won't have a reference map. This cuts my review sessions from roughly an hour down to about twenty minutes per topic block. Here is the practical approach. Print or open the key side by side with an unlabeled posterior diagram. Cover the labels with a blank sheet. Work through each bone systematically. Say the name out loud. Then verify against the key. If you get one wrong, do not move on. You need to look at that structure again until you can point to it without hesitation, because in a timed practical you won't have the luxury of working through options. Several answer keys organize labels numerically or alphabetically rather than anatomically. This is a poorly designed layout that creates extra cognitive load. If yours is organized this way, ignore the numbering and map the labels to anatomical regions yourself. Draw quick connecting lines on your printed sheet from the label number to the structure it identifies. This takes three minutes and dramatically improves retention.
Common Pitfalls and What They Actually Look Like
One issue that comes up constantly involves the spinous processes. Keys will label C7 as the vertebra prominens, which is correct for the average case, but C7 spinous processes vary significantly between individuals. Some are markedly longer, some are bifid, and some sit nearly level with T1. If a specimen or image shows an ambiguous cervical-thoracic transition, relying solely on spinous process length as your identifier is unreliable. The safer approach is to count down from C2 or up from T1 using the rib articulations as confirmation points. I spent two full lab sessions stuck on a dissection where the student team kept mislabeling T1 as C7 because the spinous process was unusually prominent. We ended up verifying with the first rib attachment and the transverse foramen absence, which resolved the confusion immediately. Another frequent error involves the scapula. The inferior angle, the medial border, the lateral border, the spine of the scapula, and the acromion process all appear in posterior view and are routinely confused on exams. The key differentiator is orientation. The spine of the scapula runs laterally from the medial border toward the acromion. Anything labeled "superior angle" that appears lower on the diagram than the spine level is misidentified. This happens more often than you would think in student lab settings. The sacrum and coccyx presentation also causes problems. In many posterior views, the sacral vertebrae fusion lines are not clearly visible, making it hard to distinguish individual sacral segments from the coccyx. The median sacral crest marks the fused spinous processes, the intermediate sacral crest marks fused articular processes, and the lateral sacral crest marks fused transverse processes. Keys sometimes skip these distinctions entirely and just label "sacrum" as one unit, which is fine for introductory courses but insufficient for any anatomy program requiring structural detail.
Get the Full Details
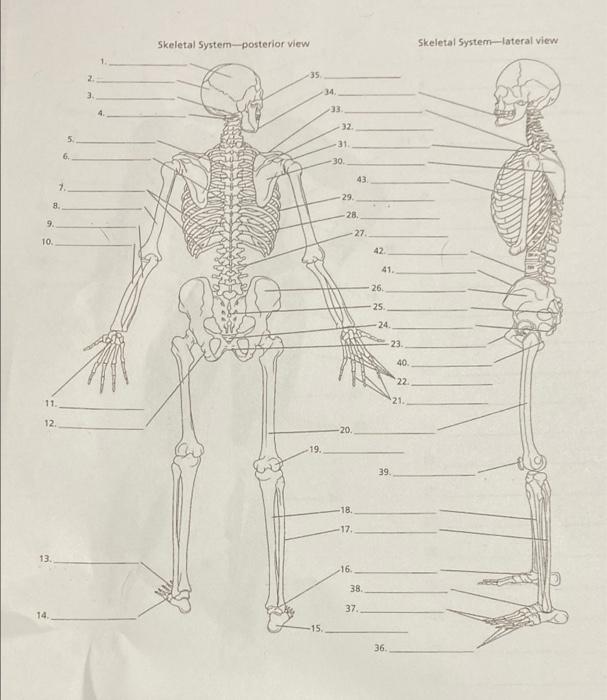
Pelvic landmarks on the posterior view are another area where answer keys tend to be inconsistent. The posterior superior iliac spine, the posterior inferior iliac spine, the iliac tuberosity, and the sacroiliac joint surface all occupy a crowded region. Keys that group them vaguely as "posterior iliac features" without specifying which is which are not adequate for lab practicals. You need to be able to locate the PSIS specifically because it corresponds to the S2 dermatome level clinically and is a standard landmark for regional anesthesia and spinal procedures.
Limitations of Typical Posterior View Answer Keys
Answer keys for this material are not uniformly reliable. Some sources contain labeling errors, particularly older PDFs and freely distributed study guides that were never peer-reviewed or corrected. I have seen keys that labeled the greater sciatic notch as the lesser sciatic notch and vice versa, which would cost you marks on any practical exam. Always cross-reference with an atlas when something looks off. Gray's Anatomy, Netter's, or the Visible Human Project are good verification points. Another limitation is that most keys present idealized diagrams rather than real skeletal specimens. Real bones have wear patterns, variation in process size, degenerative changes, and individual anatomical differences that textbook diagrams smooth over. If your course uses actual cadaveric or dry bone specimens, a diagram-based answer key will not fully prepare you for what you are looking at. The labels will match, but the morphology may not. Some keys also omit the occipital bone structures entirely or label them incorrectly. The external occipital protuberance, the superior nuchal line, and the inferior nuchal line are sometimes missing from posterior skull diagrams, or the protuberance is placed too low on the lambdoid suture. This matters because the protuberance is a key palpable landmark and a frequent exam question.
If you are working with a key that has these issues, the workaround is straightforward. Use it as a starting framework, not a final authority. Pull up a second source, compare the labels, and note where they diverge. The discrepancies themselves become valuable study material because they reveal exactly where your understanding might have gaps.
What to Focus On for Maximum Retention
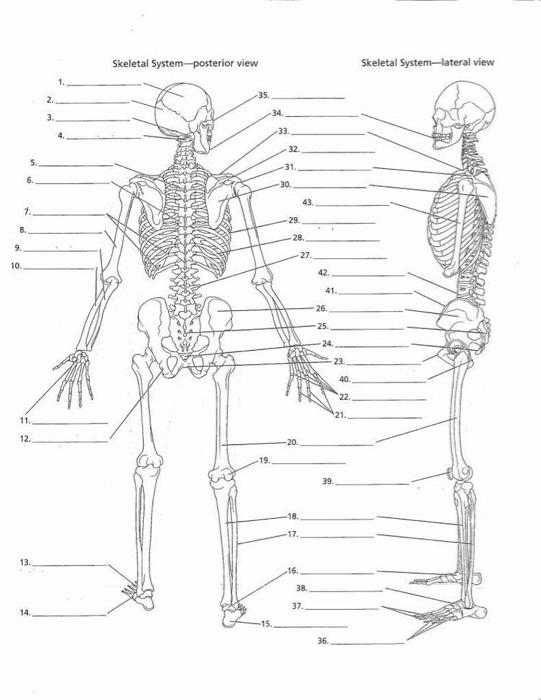
Not every label in a posterior view answer key carries equal weight. The high-yield structures are the ones you will encounter repeatedly across courses and clinical contexts. The nuchal lines and external occipital protuberance for skull identification. The vertebral landmarks — spinous processes, transverse processes, laminae, pedicles — because spinal anatomy underpins neurology and orthopedics. The scapular borders and processes for shoulder girdle work. The posterior pelvic landmarks for clinical procedure orientation. The fibular head and tibial condyles for lower limb studies. Lower priority labels tend to be minor tubercles, subtle crest segments, and variant articulation surfaces that rarely appear on standard practical exams unless you are in an advanced osteology course. If you are studying for a general anatomy exam, spending extra time memorizing the posterior auricular mastoid notch or the precise curvature of the posterior pubic ramus is inefficient use of study time. The most effective method combines the answer key with active recall. Do not just read the labels. Close the key and reconstruct the diagram from memory. Then open it and check. Repeat until you can draw the posterior skeleton and label every structure correctly without reference material. This usually takes three to four study sessions of about twenty minutes each for a complete posterior view, and the retention lasts significantly longer than passive reading does.
If you need the answer key document itself, search for your specific course or textbook edition since the labeling varies between publishers. Moore's Clinically Oriented Anatomy, Marieb, and Sinnatamby's Last's Anatomy each produce their own versions with different emphases. Make sure your key matches the source material your instructors are using, because mismatches between key and lecture content are a common source of unnecessary stress.


