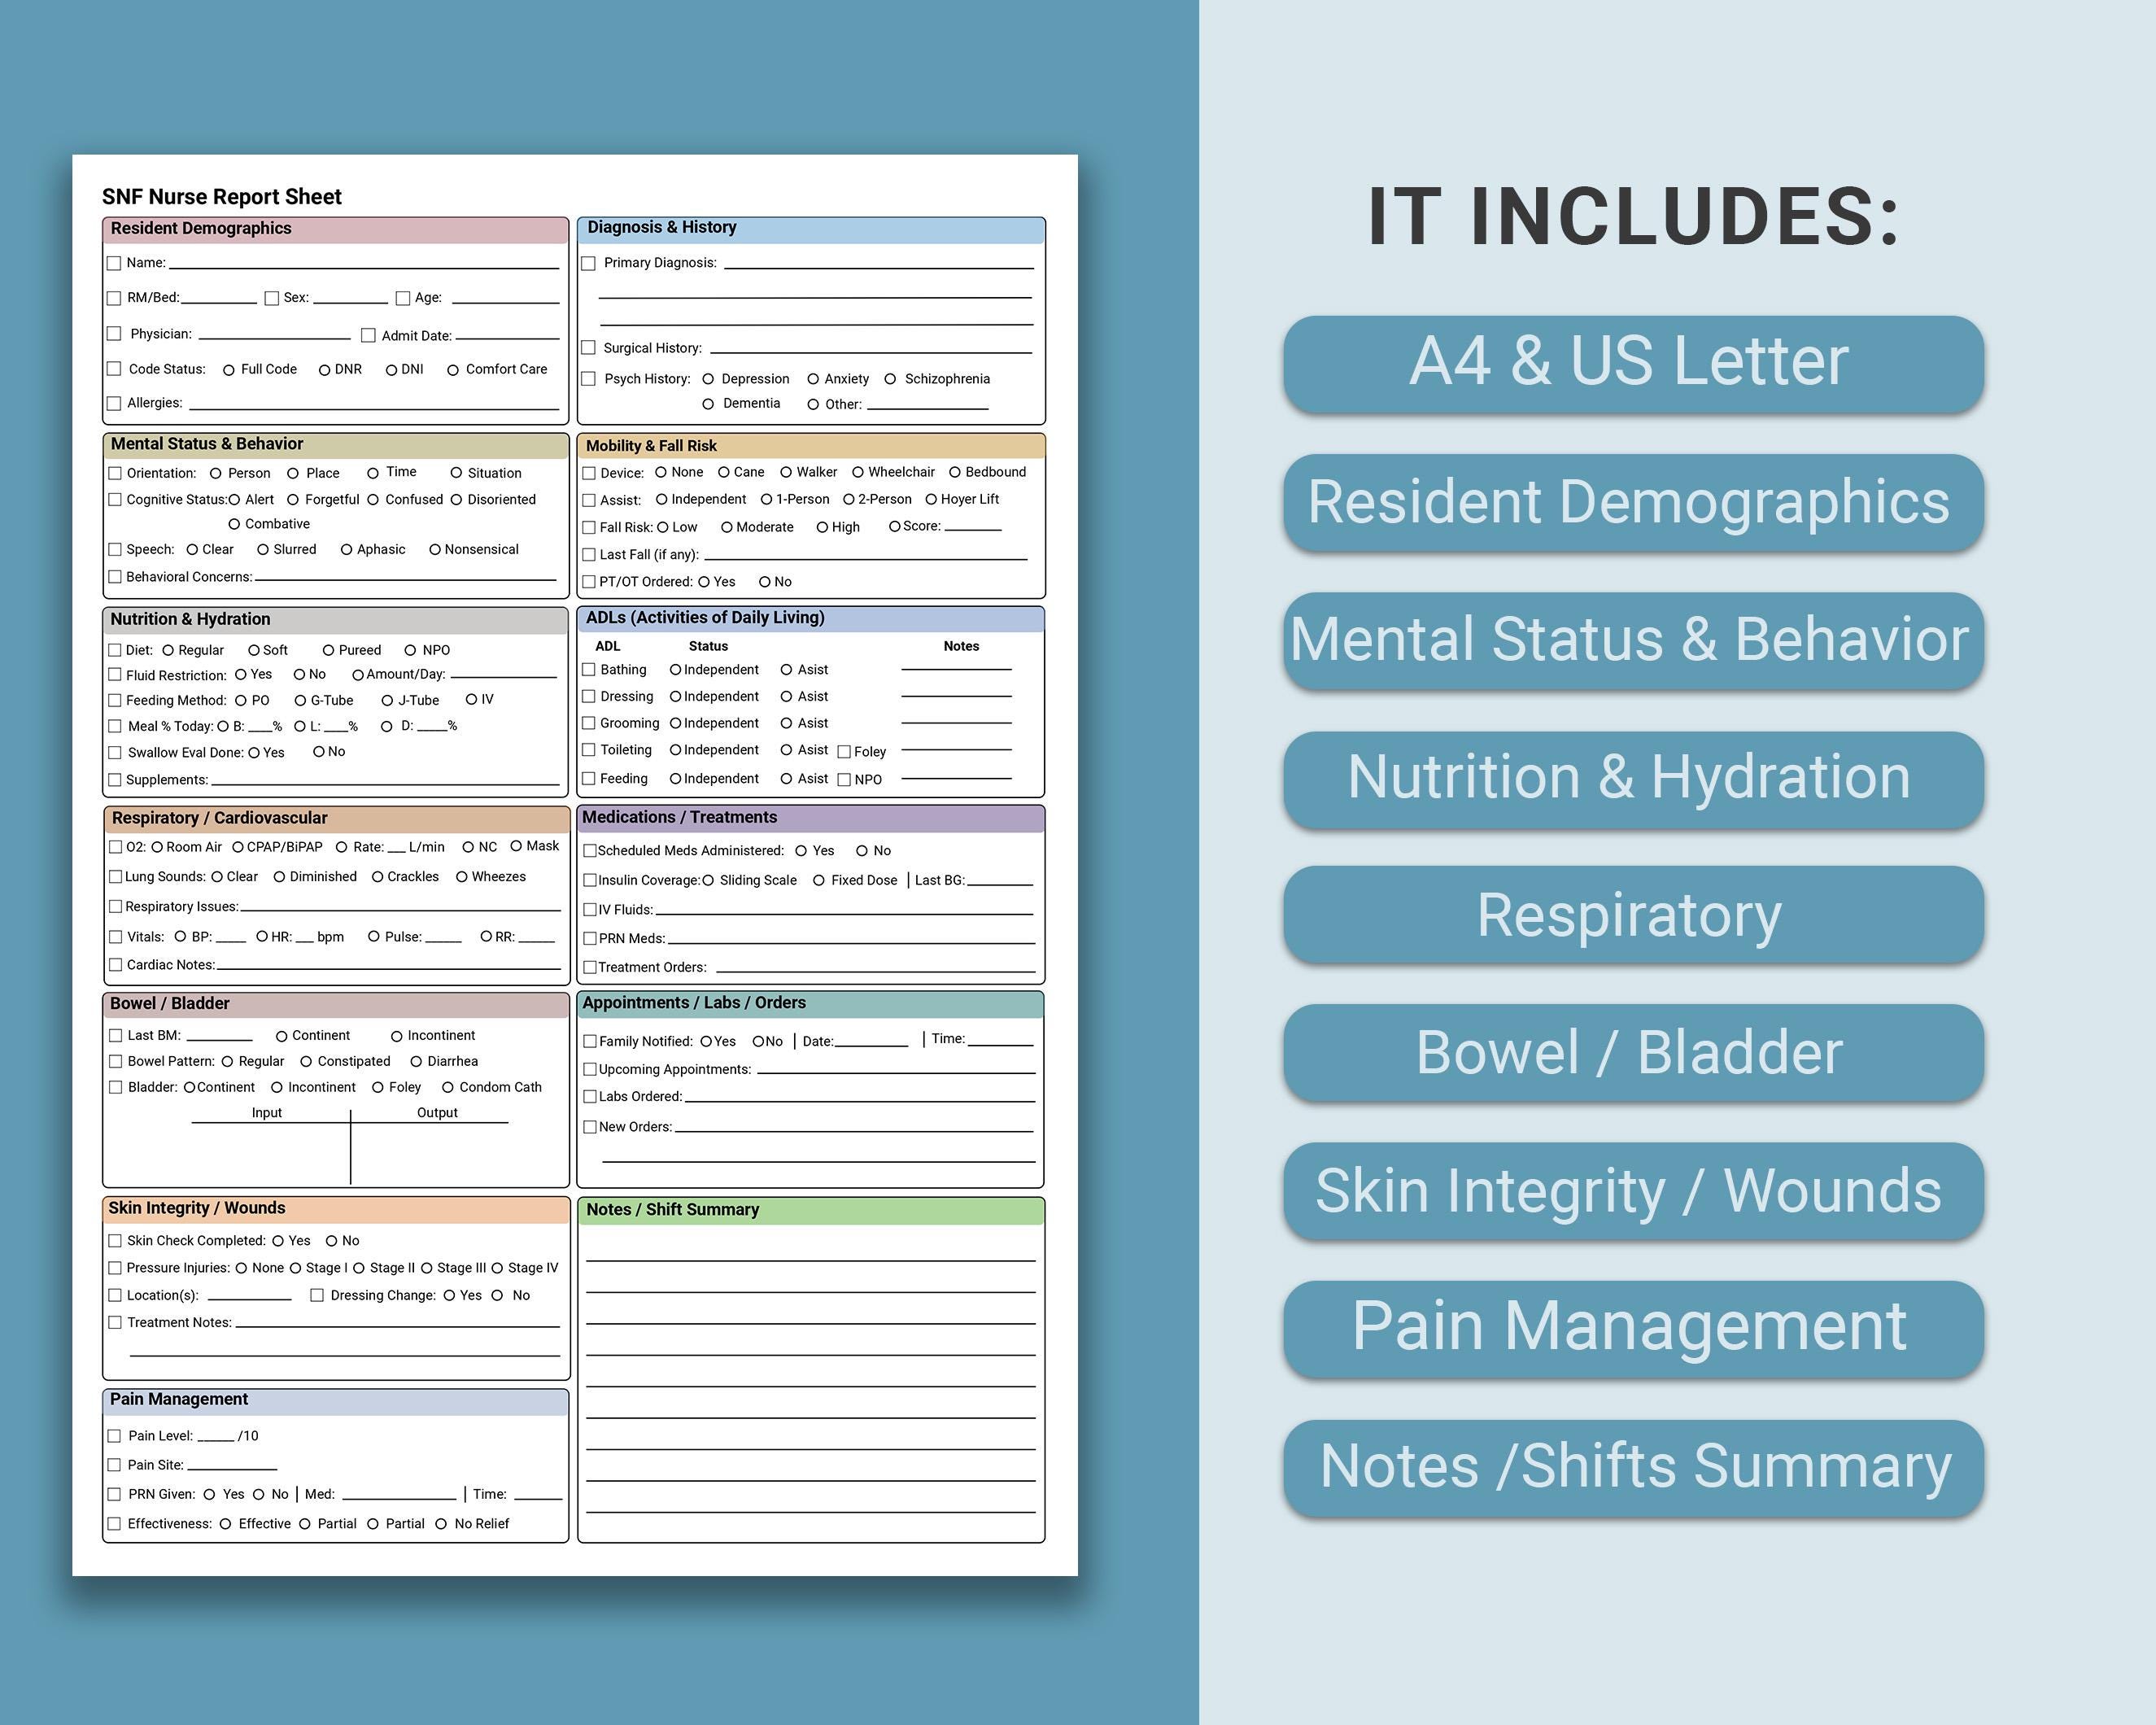
Why You Need Something Quick at the End of a 12-Hour Shift
I spent six years working the evening and night shifts in a 120-bed skilled nursing facility before moving into quality assurance. The documentation requirements alone could fill a textbook. What actually helps your team is a single reference document that cuts through the noise. This is what I mean by a Skilled Nursing Documentation Cheat Sheet. A cheat sheet is a condensed reference that covers the documentation elements most likely to get flagged during a survey or audit. It lists the required fields, the timing expectations, and the common pitfalls. It is not a replacement for full policy. It is the thing you pin to the nurses' station board or keep on a lanyard card. The core components that need to be there are the OBRA basics, the MDS timing windows, and the documentation rules for each department. You cover the care plan requirements, the physician order signature dates, the MAR compliance checks, the incident reports, and the discharge summaries. Everything else is detail work. But the detail work is what gets you denied payment.
What Actually Gets Flagged on Survey
Surveyors do not read every page. They sample. They look for consistency between the physician orders, the care plan, the medication administration records, and the progress notes. When those four documents disagree, that is an immediate deficiency. I have seen facilities lose significant revenue because a wound care order was updated but the care plan was not revised within the required timeframe. The specific problem I ran into most often involved the interdisciplinary team meeting minutes. The regulation says you must hold IDT meetings at admission, at least every 30 days, upon significant change in condition, and at discharge. The minutes need to show participation from nursing, physician, therapy, social work, and dietetics when applicable. I watched a facility get cited because their IDT notes were copy-pasted templates with zero individualized content. The workaround was simple. I made the nursing supervisor initial each section after the meeting, confirming that the discussion reflected the actual resident status rather than a generic template.
The Parts That Matter Most
Here is what your cheat sheet needs to prioritize. The MDS assessment sections are the biggest revenue driver and the biggest audit target. The RAI Manual version matters. Make sure your staff knows which version the facility is using. The OASIS data set applies to home health, not SNF, so do not mix those up. That mistake costs money. Physician orders require a signature within 48 hours of initiation or renewal for most orders. Stat orders require immediate signature. Verbal orders need to be cosigned within 24 hours per federal requirements. Your cheat sheet should make these timeframes impossible to miss. Progress notes need the SOAPIE or DAR format depending on your EHR setup. Subjective, objective, assessment, intervention, evaluation. The assessment portion is where most notes fail. Writers often describe what they did without stating what the clinical reasoning was. A note that says "applied dressing to wound" without documenting the wound size, appearance, and healing status is insufficient. I used to tell my team to ask themselves whether a different nurse reading the note could reconstruct the clinical picture without asking follow-up questions.
Get the Full Details

Counter-Intuitive Things Beginners Miss
Most people think more documentation is better. It is not. Over-documentation creates contradictions. If a nurse documents a fall risk in the shift notes but the care plan still shows the resident as independent with ambulation three days later, the surveyor sees the inconsistency and questions everything. Less documentation that is accurate beats thorough documentation that is contradictory. The second thing people miss is the flow sheet trap. Flow sheets look harmless. They track vitals, intake and output, bowel movements, and glucose levels. But flow sheet data must match the progress notes and the care plan. I have seen a resident's I&O totals on the flow sheet contradict the physician's daily weight trend in the progress note by nearly two liters. That triggered a full audit of fluid management documentation across the entire unit. Another nuance is the timing of notifications. When a resident's condition changes, the physician must be notified promptly. The cheat sheet should list exactly what constitutes a reportable change for your facility. Blood pressure drop of 30 mmHg systolic. Oxygen saturation below 88 percent. New onset confusion. These thresholds need to be explicit. Generic language like "significant change" will not hold up under scrutiny.
Building the Actual Document
Start with a single page if possible. Two pages maximum. Group the content by documentation type rather than by department. Care Plan section, Physician Orders section, MAR Section, Progress Notes Section, Incident Reporting Section. Each section gets a checklist of required elements and the timeframe for completion. Include the specific code references. OBRA '87, 42 CFR 483.21, the state-specific regulations that apply to your facility. Surveyors love to see that your staff knows the regulatory basis, not just the procedural steps. For the MDS section, include the assessment trigger table. Admission, 30-day, 60-day, significant change, discharge. List what changes trigger a significant change RAI. Weight loss of five percent in 30 days. New pressure ulcer. Hospitalization requiring IV antibiotics. These specifics turn a vague policy into an actionable tool.
Where This Approach Falls Apart
A cheat sheet does not work if your EHR has poor configuration. If the system allows charting closures without supervision or forces template-heavy notes that encourage copy-paste, no reference document will fix that culture problem. I worked at a facility that had the best cheat sheets and the worst documentation compliance because the EHR automatically populated every field from admission data with zero requirement for ongoing updates. The cheat sheet was useless against a system designed to make sloppy charting easy. The other limitation is staff turnover. A cheat sheet assumes your team will read it and use it. New hires often skip straight to the EHR templates without consulting the reference. You need to build the cheat sheet into the onboarding checklist and require new staff to pass a quick documentation quiz before working independently. Without that enforcement step, the document sits there. If your facility is small with fewer than 60 beds, you might not need a separate cheat sheet at all. The regulatory requirements are the same, but the documentation volume is lower and experienced staff tend to know the requirements by osmosis. In that case, a laminated reference card for the charge nurse is more practical than a full cheat sheet distributed to every employee.

What to Include When You Print It
Your final document should have the facility name and the effective date at the top. Documentation requirements change. The cheat sheet from two years ago may reference a RAI Manual version that is no longer current. Every printout needs a revision date and the name of the person who approved it. Include a contact column. Who to call when a physician order is unclear. Who approves exceptions to the documentation policy. Who handles the MDS submission questions. Time spent searching for the right person during a shift is time taken away from actual resident care. The download link for a usable template would typically be found through your state's nursing home association or your long-term care consultant's resource library. The Medicare Learning Network also publishes free MDS reference materials that can be adapted into a facility-specific format. I used the CMS RAI Manual companion documents as the backbone of my own cheat sheet and filled in the facility-specific details on top.
The Bottom Line Without a Conclusion
A Skilled Nursing Documentation Cheat Sheet is worth the one afternoon it takes to build correctly. It reduces survey citations, cuts down on documentation-related pay denials, and gives new nurses a clear standard to follow. It is not a magic solution for systemic documentation failures. But it removes the excuse of not knowing what is required. In my experience, most deficiencies come from ambiguity, not from unwillingness to comply. Clear requirements posted where staff can actually see them solve that problem faster than any training program.