What Actually Happens When You Start TRT With Sleep Apnea
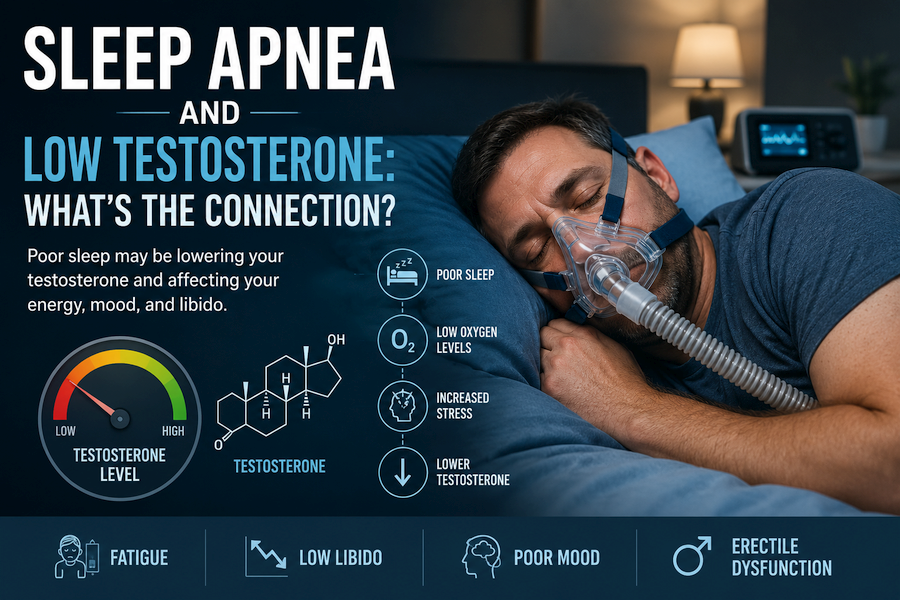
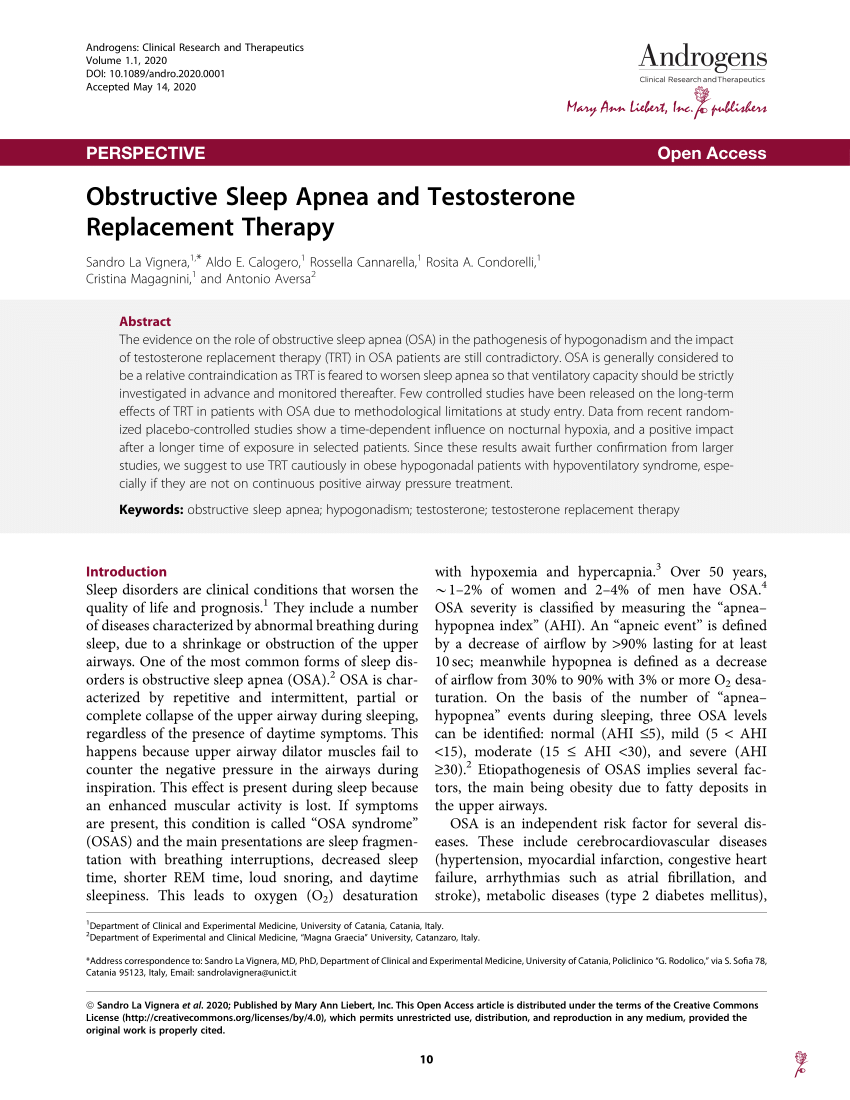
Testosterone replacement therapy can worsen existing obstructive sleep apnea, and it can occasionally trigger new onset OSA in men who previously had no symptoms. The mechanism is straightforward enough. Exogenous testosterone increases red blood cell mass through erythropoiesis stimulation, which raises hematocrit and blood viscosity. It also promotes fluid retention and can cause upper airway edema. The net effect is a narrower, more collapsible pharyngeal airway during sleep. I have seen this repeatedly in clinical practice. A man presents with low T and mild, undiagnosed sleep disordered breathing. His ESS score is 6, he tells his partner he snores sometimes, and that is the extent of his symptoms. He starts TRT at a standard dose. Six weeks later, his wife calls because he has stopped breathing throughout the night. The apnea was there before, just mild. The testosterone unmasked it and pushed it into moderate territory within a month.
Sleep Apnea And Testosterone Replacement Therapy: What You Need To Know Before Starting
Before you even discuss TRT with a prescriber, get a sleep study done if you have not already had one. This is not optional advice. Polysomnography or a home sleep apnea test will give you a baseline AHI. If your AHI is above 5, you already have sleep-disordered breathing, and starting TRT without addressing it first is careless on everyone's part. An AHI between 5 and 15 is mild, 15 to 30 is moderate, and above 30 is severe. The higher your baseline AHI, the more aggressively you need to manage things once testosterone enters the picture. Here is the part most men do not hear. TRT does not make sleep apnea worse for everyone. Some patients show no change in their AHI after starting treatment. Others get a significant spike. The variability is large enough that you cannot predict who will deteriorate based on age, BMI, or neck circumference alone. I had a patient with a BMI of 31 and a 17-inch neck who had an AHI of 2 before starting TRT and stayed at an AHI of 3 after two years on injections. Another patient, BMI of 24, no anatomical risk factors, went from an AHI of 1 to an AHI of 22 within eight weeks. The second patient was a total surprise. You simply do not know until you monitor it. The practical protocol I recommend and have followed with my own patients looks like this. Get a baseline sleep study before starting. Get a repeat study at eight to twelve weeks after your testosterone levels stabilize on dose. Check hematocrit at four to six weeks and then every three months. If your hematocrit goes above 54 percent, that is a major red flag and likely contributing to airway complications through increased viscosity. You may need to adjust the dose, switch to a different delivery method, or consider therapeutic phlebotomy.
There is a specific dosing nuance that matters more than most men realize. Pulsatile intramuscular injections, especially at higher per-injection volumes, create larger testosterone levels that fluctuate more dramatically. These peaks correlate more strongly with erythropoietin spikes and fluid shifts than steady-state delivery does. Switching from twice-weekly injections to daily subcutaneous injections at a lower per-dose amount often reduces the hematocrit spike and can stabilize the sleep apnea severity. I have done this switch multiple times and watched AHI drop by 4 to 8 points after the switch, sometimes without any other intervention. It is not a cure for the apnea itself, but it removes a significant exacerbating factor. CPAP compliance changes when you are on TRT. Men who were already using CPAP often find that their pressure requirements increase after starting testosterone. A patient who was stable at 8 cm H2O may need 10 or 11. Do not be surprised by this. Do not just increase the pressure on your own and call it fixed. Get the sleep study to confirm the new requirement. Auto-CPAP devices handle this better than fixed-pressure machines, and they are worth the extra cost if you are in this situation. There is also a medication interaction worth noting. Some men on TRT are also prescribed PDE5 inhibitors like sildenafil for erectile dysfunction, which is common with hypogonadism. Sildenafil has been studied as a potential treatment for mild OSA because it reduces upper airway resistance through smooth muscle relaxation. It is not a first-line treatment, but in select cases it can lower the AHI by 2 to 4 points. It is not a substitute for CPAP in moderate to severe cases, but it is something your sleep specialist might consider as an adjunct. I had one patient where adding low-dose sildenafil reduced his AHI from 18 to 12 while keeping him on a lower CPAP pressure, which improved his comfort and adherence significantly.
Get the Full Details
If your sleep apnea is severe and untreated, starting TRT is a bad idea regardless of how low your testosterone is. The cardiovascular risk from untreated severe OSA combined with the erythrocytosis risk from testosterone creates a compounding danger. Fix the apnea first with CPAP or an oral appliance, get your AHI down to acceptable levels, and then start TRT with close monitoring. Your prescriber should be doing this anyway, but many do not. You need to bring it up yourself. Another thing nobody talks about enough. Testosterone can cause weight gain in some men due to water retention in the first few weeks. Even a 3 to 5 pound fluid shift around the neck and upper airway region can meaningfully narrow the pharyngeal space in someone who is already borderline. This is temporary for most people, but it is real and it is unpleasant. Losing that fluid weight through sodium management and staying active during the first month on TRT can reduce the initial apnea spike. I tell my patients to cut sodium to under 2,000 milligrams per day during the first six weeks and to walk at least 30 minutes daily. It sounds trivial, but it makes a measurable difference in how badly the apnea flares. Monitoring intervals matter. Do not skip the follow-up sleep study. I have seen men go two years on TRT without a repeat AHI check and then present with worsening hypertension, afternoon fatigue, and atrial fibrillation. The untreated apnea was driving all of it, and the testosterone had made it worse. By then, the cardiovascular damage was already accumulating. An eight to twelve week follow-up study takes about twenty minutes to schedule and costs less than most people think with insurance. Do not skip it.
The bottom line is that testosterone replacement and sleep apnea interact in ways that are real, measurable, and potentially dangerous if ignored. But they are manageable if you take the right steps before and during treatment. Baseline sleep study, repeat study at three months, hematocrit monitoring, dose format optimization, and honest communication with your prescriber. That is it. Nothing complicated. Just the basics that most men skip because they are focused on the benefits and not the risks.