The Uncomfortable Truth About Sliding Scale Insulin
I spent about three years working on a diabetes education unit before I accepted that the sliding scale was simultaneously the most necessary and most flawed dosing tool we had. It's still the default protocol in hospital settings, outpatient clinics, and a lot of home care plans. The reason isn't because it's elegant. It's because it's predictable, and predictability wins in clinical environments where turnover is high and decisions need to be made fast. A Sliding Scale Insulin Dosage Chart maps a blood glucose reading to a specific insulin dose. That's the entire mechanism. Most charts you'll encounter are built around rapid-acting analogs like lispro or aspart, though some older versions reference regular insulin with longer onset windows. The chart itself is just a table: range A gets dose X, range B gets dose Y, and so on.
Sliding Scale Insulin Dosage Chart How It Actually Works
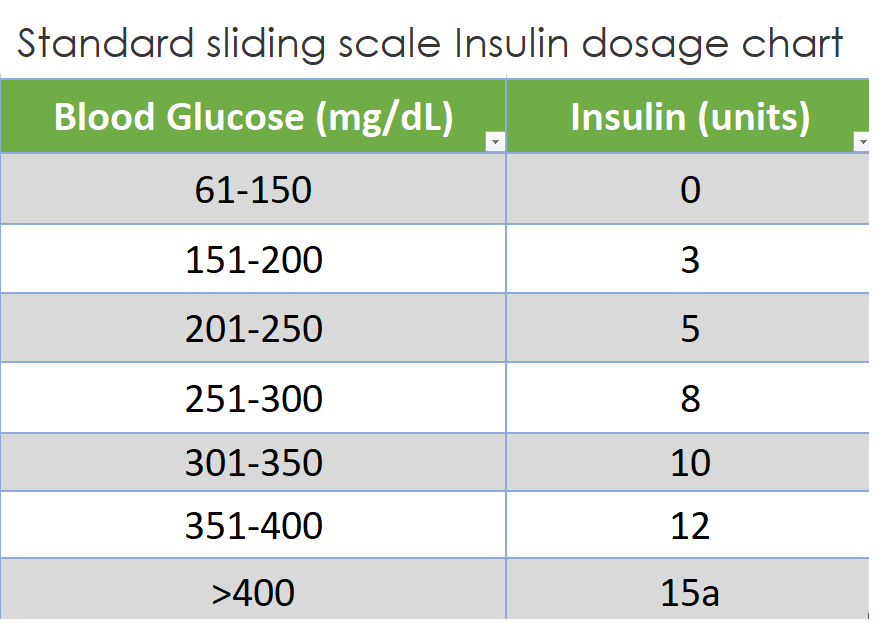
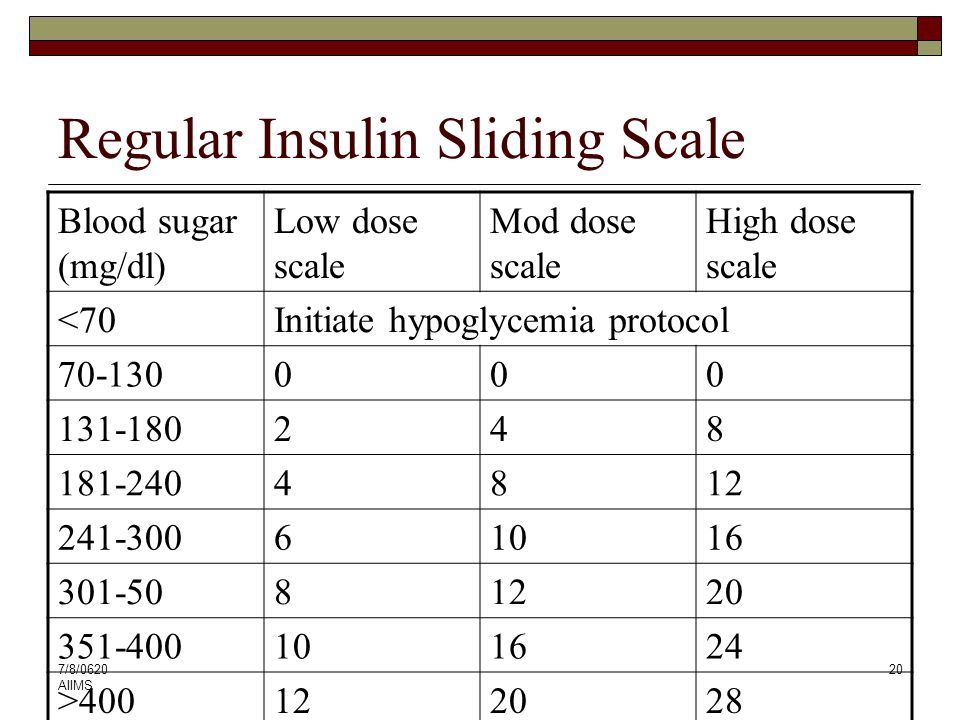
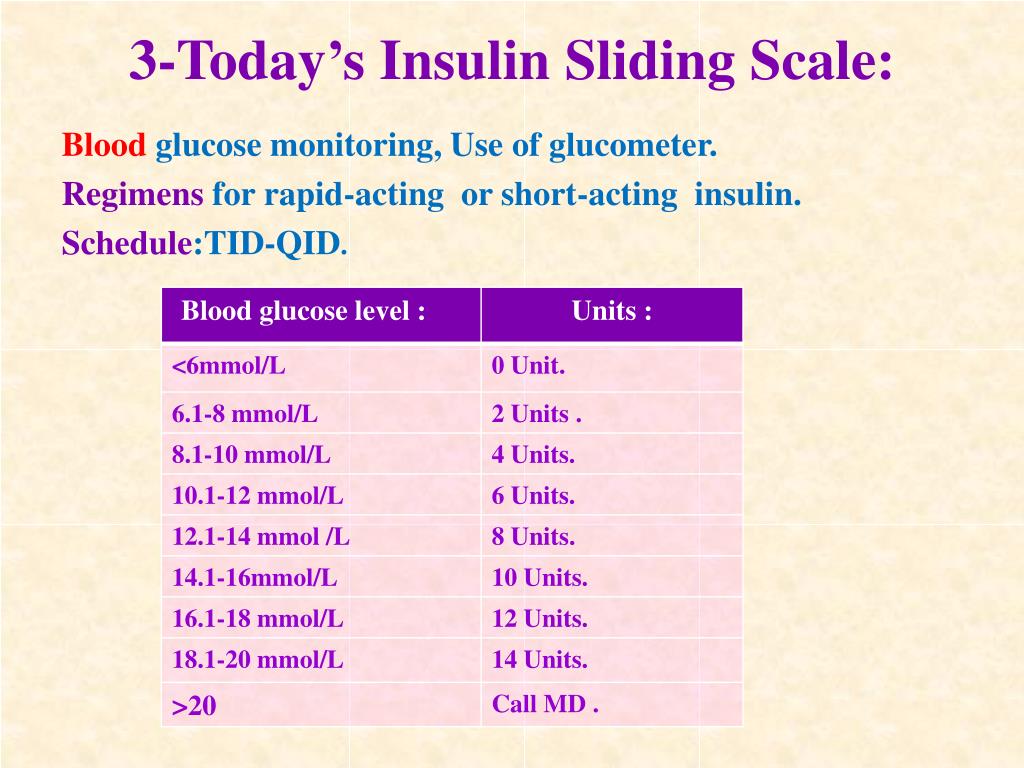
Here is the standard structure you'll find in virtually every chart: BG 150-200 mg/dL: 2 units rapid-acting
BG 201-250 mg/dL: 4 units rapid-acting
BG 251-300 mg/dL: 6 units rapid-acting
BG 301-350 mg/dL: 8 units rapid-acting
BG above 350 mg/dL: 10 units plus provider notification Those numbers are illustrative, not universal. The actual values differ by patient weight, insulin sensitivity, renal function, and whether the person is on a basal background. A chart designed for a 50 kg post-op patient will look completely different from one written for a 100 kg type 2 diabetic on metformin and a long-acting basal.
The mechanism assumes a linear correction factor, which is almost never true biologically. Insulin sensitivity changes throughout the day. Morning dawn phenomenon can push readings higher independent of actual carbohydrate load. Infection, steroids, and stress dramatically shift the correction landscape without any change to the chart itself.
Get the Full Details
The Edge Case I Still Think About
About four years ago, I worked with a patient on a standard sliding scale who presented with a BG of 280 mg/dL at 2 PM. The chart called for 6 units of lispro. I administered it. By 4 PM, her glucose had dropped to 72 mg/dL and she was symptomatic. The chart had no adjustment for her recent lunchtime activity, which included a 45-minute walk, or for the fact that she had skipped her morning basal dose due to a miscommunication during shift change. The sliding scale corrected the number on the page but not the physiology in front of me. My workaround was straightforward but not reflected in any training manual: I started cross-referencing the sliding scale chart against the patient's total daily insulin dose and their known sensitivity factor rather than treating the chart as an autonomous protocol. When the chart and the clinical picture diverged, the clinical picture won. That decision required calling the prescriber, which bought time and got a revised correction factor added to the order set. The patient stabilized over the next two days without further hypos.
Why the Chart Fails More Often Than People Admit
The sliding scale operates on a single data point. One fingerstick determines the entire dose. That is its fundamental structural weakness. Blood glucose is a lagging indicator. A reading of 220 mg/dL tells you what happened over the past two to three hours, not what will happen over the next four. Insulin peaks around one to two hours after injection and wears off in about three to five hours for rapid-acting analogs. The timing mismatch between when the measurement reflects reality and when the insulin actually does its work is where most dosing errors originate. Another issue is that sliding scale charts are usually static. They do not auto-adjust for cumulative insulin on board. If a patient received a correction dose two hours ago and their glucose is still elevated, a second correction on the same chart can stack with residual insulin and drive them into hypoglycemia. This is called IOB stacking and it accounts for a significant portion of mild-to-moderate hypo events in settings where sliding scale is the primary correction method. Renal impairment is another variable most charts ignore entirely. Patients with reduced GFR clear insulin more slowly. A standard chart dose that is appropriate for someone with normal renal function can produce prolonged and unpredictable glucose lowering in someone with stage 3 or 4 chronic kidney disease. I have seen cases where the dose needed reduction by half or more simply because the clearance pathway was compromised. The chart did not account for this because it never would.
Building a Usable Chart from Scratch
If you need to construct or evaluate a Sliding Scale Insulin Dosage Chart, start with the patient's total daily dose, not with a template. Take their TDI, divide it by weight in kilograms, and compare that to standard sensitivity ranges. A common starting correction factor is 1800 divided by TDI for rapid-acting insulin, giving you the approximate drop in mg/dL per unit. This is the 1800 rule, widely used but imperfect. For example, if a patient's TDI is 40 units, 1800 divided by 40 equals 45. Each unit of rapid-acting insulin should theoretically lower glucose by approximately 45 mg/dL. If their current reading is 310 mg/dL and the target is 120 mg/dL, the correction needed is 190 mg/dL. Dividing 190 by 45 gives roughly 4 units. Round appropriately based on the pen or syringe available. That is a single-point calculation, not a sliding scale, but it is often more accurate than a fixed table. When you do use a table format, include a column for the action to take when readings exceed the highest bracket. Most charts stop at 350 or 400 mg/dL and leave the clinician to guess whether to call the provider, give a larger dose, or check for ketones. Building that decision branch directly into the chart reduces ambiguity at the point of care. I recommend adding a note about ketone testing for any reading above 300 mg/dL in type 1 diabetes or in type 2 patients with suspected insulin deficiency. That single addition prevented at least two cases of delayed DKA recognition in my experience.

What to Look for in a Downloadable Chart
Most downloadable Sliding Scale Insulin Dosage Chart resources you find online are either too generic to be clinically useful or they are outdated sheets based on regular insulin dosing rather than analog protocols. The ones worth using share a few characteristics. They specify the insulin type and formulation. They include renal and hepatic adjustment notes. They define the correction factor calculation alongside the table rather than replacing it. They have a clear escalation path for hyperglycemic crisis thresholds. You can typically find printable versions through hospital intranets, diabetes association websites, or clinical decision support platforms. I prefer charts that are structured as Excel or PDF files with separate tabs for different patient populations rather than single static images. The ability to adjust the dosage brackets for weight bands makes the chart usable across a broader range of cases instead of requiring you to discard it after the first mismatch. One practical tip: if the chart you are using does not include a column for timing or interval between doses, add one. Most rapid-acting protocols require at least a four-hour window between correction doses unless the prescriber has specified otherwise. Without that interval marker, nurses and patients tend to re-dose based on the current reading alone, which accelerates IOB stacking. I started adding a simple time stamp column to every printed chart and the recurrence of repeat-corrective dosing dropped noticeably in my patient group.
When the Chart Should Not Be Used at All
Sliding scale alone is inadequate for initiating insulin therapy in most type 2 diabetes cases. Current guidelines favor basal insulin started at a fixed dose with or without adjunct oral agents, reserving sliding scale corrections for inpatient settings or acute hyperglycemic management. Using a sliding scale chart as the sole insulin strategy in an outpatient setting leaves the underlying fasting hyperglycemia untreated while only addressing post-meal spikes reactively. That approach delays meaningful A1C improvement and increases variability. It is also insufficient for pregnant patients with gestational diabetes or pre-existing diabetes. The insulin requirements in pregnancy change week to week, often doubling or tripling by the third trimester. A static chart cannot track that trajectory. These patients require frequent reassessment and dose adjustment schedules that a sliding scale document cannot support on its own. Pediatric dosing follows a different sensitivity profile entirely. Children are more prone to hypoglycemia from correction doses because of lower glycogen stores and higher metabolic variability. The 1800 rule tends to overestimate sensitivity in younger patients. I have seen charts that produced safe results in adults cause problematic lows in adolescents using the same formula. Age-specific charts or weight-based dosing with pediatric Endocrine Society references are the safer alternative.
A More Useful Alternative Framework
Correlation-based dosing, sometimes called the correction factor method, produces more consistent results than a fixed sliding scale table. The principle is simple: calculate an individualized sensitivity factor, then apply it to the difference between current glucose and target glucose. This requires knowing the patient's TDI and their insulin regimen, which is usually already documented in the chart or medication list. The math is slightly more involved at first but becomes routine within a few cases. Once you have the sensitivity factor, you can build a dynamic table that auto-updates if you enter it into a spreadsheet. A cell reference formula means the entire chart adjusts when the TDI changes, which happens frequently in inpatient settings where stress dosing, steroid tapers, or nutritional changes alter requirements day to day. A static paper chart does not adjust. It stays wrong until someone manually rewrites it. I switched my practice pattern to this approach about three years ago and have not gone back. The time investment to set up the spreadsheet initially is perhaps twenty minutes per new patient. After that, each subsequent dose calculation takes about thirty seconds. The reduction in corrective events and readjustment visits has been significant enough that I now use this as the default framework and reserve the traditional sliding scale chart only for situations where the patient's insulin history is incomplete and a correction factor cannot be calculated yet.

The Sliding Scale Insulin Dosage Chart remains a functional tool when used with awareness of its constraints. It works best as a bridge until a more individualized regimen is established, not as a permanent solution. Understanding its mechanics, recognizing when it conflicts with the clinical picture, and knowing the replacement methods when the chart falls short is what separates competent use from mechanical reliance.