What the Procedure Actually Involves
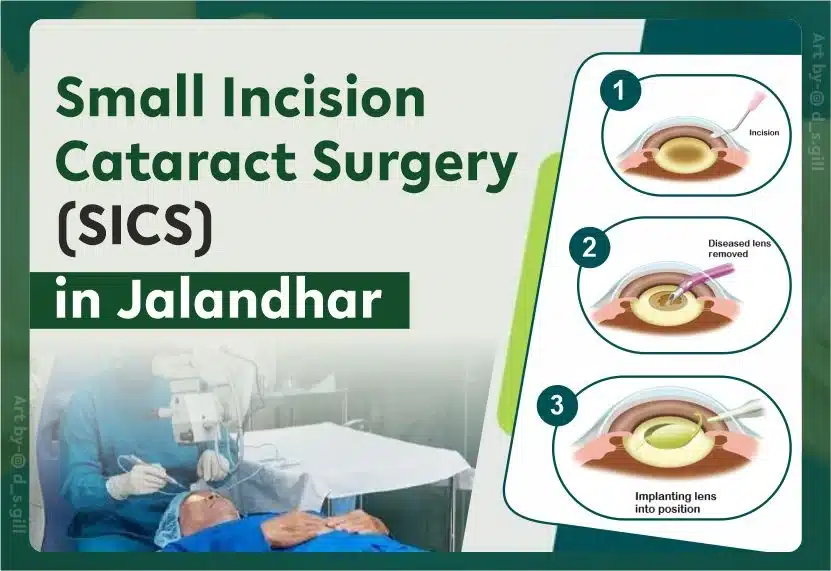
Small Incision Cataract Surgery is the modern standard for removing cataracts, and it differs from older techniques mainly in the size of the corneal incision and the amount of suturing required. The typical incision measures between 2.0 and 3.0 millimeters, which is substantially smaller than the 10 to 12 millimeter wounds used in extracapsular cataract extraction decades ago. This reduction in wound size means the eye can seal itself without stitches in most cases, cutting down postoperative discomfort and speeding visual recovery. The surgery involves making a self-sealing tunnel incision in the cornea, injecting viscoelastic material to maintain anterior chamber depth, performing phacoemulsification to break up the cloudy lens using ultrasonic energy, and then folding and inserting a posterior chamber intraocular lens through the same small opening. Here is how the procedure unfolds in the operating room, from setup to closure, in the sequence I have seen it done thousands of times across different patient populations. The patient arrives prepped with topical anesthetic drops, usually a combination of proparacaine and sometimes a little lidocaine for patients who are anxious or have sensitive corneas. A eyelid speculum gets placed to keep the eye open, and a sterilizing solution like povidone-iodine is applied to the conjunctiva and skin around the eye. The surgeon marks the cornea with a surgical marker to indicate the intended incision site and axis, typically at the 12 o'clock position or slightly temporal depending on the surgeon's handedness and the patient's anatomy.
The actual incision begins with a clear corneal tunnel. This is where technique matters more than anything else. The needle or blade enters the cornea about 1.5 to 2 millimeters posterior to the limbus at a slight upward angle, then advances parallel to the iris plane for roughly 1.5 to 2 millimeters before curving forward to create a ramp that exits at the corneal surface. The geometry of this tunnel determines whether the incision self-seals. If the entry angle is too steep, the incision gapes under pressure. If the intrastromal portion is too shallow, aqueous humor leaks around the phaco probe during surgery, which causes chamber collapse and can lead to complications. I once had a patient whose corneal curvature was unusually flat with a keratometry reading of 38 diopters, and my standard tunnel technique kept leaking. What I ended up doing was extending the intrastromal portion by about half a millimeter and making the exit wound slightly more posterior than usual, which created enough resistance to seal the incision adequately. It is a detail that does not show up in any textbook but becomes important when you are operating on eyes that do not conform to average anatomy. Once the incision is formed, the anterior chamber is entered with a viscoelastic device. Ocucoat or DisCoViscon are common choices, and the viscoelastic serves two purposes: it maintains the depth of the anterior chamber and it protects the corneal endothelium from thermal and mechanical damage during the phaco step. Without adequate viscoelastic, the phacoemulsification probe can damage the endothelial cells on contact, leading to corneal edema that may take weeks to resolve or in severe cases result in permanent vision loss from bullous keratopathy. The phacoemulsification step is where the cataract is removed. Modern machines use either the divide-and-conquer technique or the chop technique, sometimes called the modify-and-chop depending on the surgeon's preference. The divide-and-conquer approach involves creating a central furrow in the lens nucleus, then removing the peripheral portions in quadrants. The chop technique involves splitting the nucleus laterally with a second instrument before emulsifying the fragments. Both are effective, but the chop technique generally uses less ultrasonic energy, which translates to less endothelial cell loss and a safer outcome for patients with compromised endothelial counts. I prefer chop for hard cataracts, grade 3 and above on the LOCS classification, because it requires less phaco time and less aspiration flow.
After the lens material is removed, the cortex is cleaned using irrigation and aspiration. This is called cortical cleanup or CLO, and it is important to get as much residual cortex as possible because leaving cortical material behind can cause inflammation and make the IOL optic cloudy over time. A thick-viscosity viscoelastic like heparin-coated dispersible viscoelastic is often used at this stage to protect the endothelium while you work. The intraocular lens is folded and inserted through the same 2.0 to 3.0 millimeter incision. Most modern IOLs are foldable made from acrylic or silicone material, and they come preloaded in cartridge systems that attach directly to the injector. The key here is to ensure the haptics are fully deployed in the sulcus or in the bag depending on the IOL design. I have seen cases where the surgeon rushed this step and one haptic remained tucked behind the iris, which required a second incision to reposition. It is a frustrating complication but entirely preventable if you take the time to confirm haptic position under the operating microscope before finishing. The incision is then hydrated and tested for watertight seal. You inject balanced salt solution into the incision bed and watch for leakage. If there is a leak, you hydrate the incision more aggressively or place a single 10-0 nylon suture. Most incisions seal without sutures these days, which is one of the main advantages of small incision technique. The surgery typically takes 10 to 20 minutes for an uncomplicated case, and the patient is usually able to leave the surgery center within an hour after recovery.
Get the Full Details

Why the Incision Size Matters Clinically
The move to small incisions was not just about cosmetics or faster recovery, though those are real benefits. The primary clinical advantage is the reduction in surgically induced astigmatism. A large incision cuts through a significant portion of the corneal meridians, disrupting the corneal curvature and causing postoperative refractive error that can require glasses or even secondary procedures to correct. A 2.0 millimeter incision induces approximately 0.5 to 1.0 diopter of astigmatism at most, and often less if the tunnel is properly constructed. This is why intraocular lens power calculation formulas work better with small incision surgery, and why patients have more predictable refractive outcomes. Another advantage is the reduced risk of endophthalmitis. There is a theoretical concern that smaller incisions might allow more bacterial ingress, but the self-sealing nature of well-constructed corneal tunnels actually provides a barrier against infection. The wound architecture creates a flap-valve mechanism where increasing intraocular pressure pushes the flap tighter against the incision walls. This is the same principle behind the Seidel test and why you always check for aqueous flutter after surgery. When the chamber is pressurized, a properly sealed incision does not leak. The main limitation of small incision cataract surgery is that it requires more surgical skill and experience than older techniques. A large incision is more forgiving of technical errors. You can remove the lens nucleus through a big wound even if your incision geometry is suboptimal. With a small incision, every step demands precision, and mistakes in tunnel creation, phaco energy management, or IOL insertion can lead to complications that are harder to manage. Corneal edema, suprachoroidal hemorrhage, posterior capsule rupture, and vitreous loss are all risks that increase when the surgeon is still learning the technique. I would not attempt small incision phaco on a cataract that is hypermature or very hard without significant experience, because the ultrasound energy required increases the risk of endothelial damage and postoperative inflammation.
For patients with very dense cataracts, brunescent nuclei, or conditions like pseudoexfoliation syndrome where the zonules are weak, some surgeons still opt for a larger incision or a femtosecond laser-assisted approach to reduce phaco time and improve safety. Small incision does not mean small complications. It means small incision, but the surgical decision-making is actually more complex because you are working in a tighter space with less margin for error.
What to Expect After the Procedure
Recovery from small incision cataract surgery is generally quick. Most patients notice improved vision within 24 to 48 hours, though the eye may be slightly red and gritty for a few days. Topical antibiotics and anti-inflammatory drops are prescribed for about two to four weeks, and patients are told to avoid rubbing the eye, swimming, and heavy lifting for a couple of weeks. Follow-up visits are typically scheduled at one day, one week, and one month after surgery to monitor intraocular pressure, corneal healing, and visual acuity. Complications are rare but can include posterior capsule opacification, which affects a significant number of patients within one to three years after surgery and is easily treated with a YAG laser capsulotomy. This is not a failure of the surgery but a natural healing response where residual lens epithelial cells migrate and proliferate on the posterior capsule, causing vision to become cloudy again. The YAG procedure takes about five minutes and restores vision in the vast majority of cases. Another issue some patients experience is dry eye symptoms, especially in the first few weeks after surgery. The corneal incision disrupts some of the corneal nerves that contribute to tear production and blink reflex, and this can cause temporary dryness. Artificial tears and punctal plugs in persistent cases help manage this. For most patients, sensation and tear film stability return to normal within three to six months.

The overall success rate for small incision cataract surgery is very high, with excellent visual outcomes reported in over 95 percent of uncomplicated cases. It remains the most commonly performed surgical procedure worldwide, and for good reason. It is safe, effective, and when performed by an experienced surgeon, it delivers reliable results with minimal downtime.