What actually happens when you try to manage SIBO with food
I spent about three years working with gastroenterology patients on SIBO protocols, and the diet piece is the part that gets oversold and misunderstood the most. People expect eating differently to fix the bacterial overgrowth itself. It doesn't. The diet manages symptoms while other treatments address the root cause. That distinction matters because confusing the two leads to months of unnecessary restriction and then frustration when symptoms return the moment you relax the rules. At its core, a SIBO diet works by reducing the available fermentable substrate in the small intestine. Bacteria feed on carbohydrates, particularly certain types that are poorly absorbed or rapidly fermented. Less substrate means less gas production, less distension, and fewer symptoms. The two most established approaches are the Low FODMAP diet and the Specific Carbohydrate Diet, with the Low F FODMAP having the strongest clinical evidence behind it. Low FODMAP means reducing fermentable oligosaccharides, disaccharides, monosaccharides, and polyols. These are short-chain carbohydrates found in wheat, onions, garlic, legumes, certain fruits, and some dairy products. The diet has three phases: restriction, reintroduction, and personalization. Most people spend two to six weeks in the restriction phase. That timeframe is important because going longer without medical supervision tends to create unnecessary gut microbiome diversity loss without additional symptom benefit.
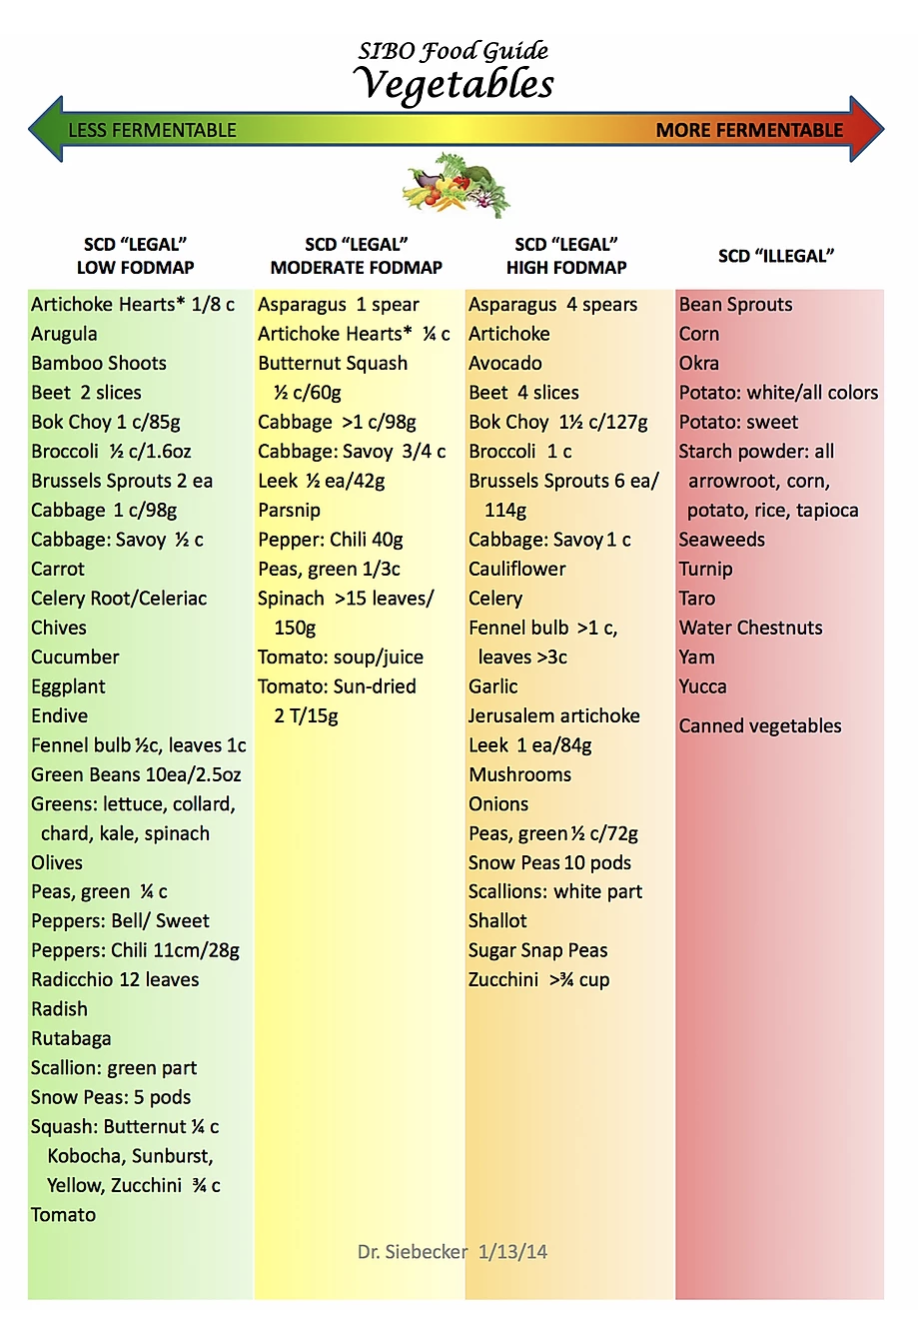
SCD removes most complex carbohydrates, grain sugars, and processed foods. It's more restrictive than Low FODMAP and has less robust evidence for SIBO specifically, though it originated for inflammatory bowel disease. Some practitioners prefer it because the rules are simpler to explain and follow long-term, even if the evidence base is thinner. Here is a practical problem I ran into repeatedly. Patients would do the restriction phase perfectly and feel great. Then they'd stay restricted for four or five months because they were afraid to reintroduce foods. Their symptom scores were zero, but their quality of life was also zero. They couldn't eat at a restaurant, couldn't share a meal with family, and were developing orthorexic patterns around food. The workaround was straightforward but requires discipline from both the patient and the clinician. I set a hard deadline for starting reintroduction at six weeks, regardless of symptom status. The reintroduction phase isn't optional. It's how you figure out which FODMAP groups actually trigger you. Staying restricted indefinitely solves nothing and creates new problems. Another thing people get wrong is assuming the diet is static. It isn't. A typical reintroduction protocol starts with one FODMAP group at a time, testing a small amount on an empty stomach in the morning so you can observe reactions without the noise of a full meal. You wait 24 to 48 hours before moving to the next group. Most patients end up tolerating some forms of lactose, maybe half a cup of strawberries, perhaps a small serving of honey. The idea isn't to end up eating nothing. The idea is to identify your personal threshold and rebuild a varied diet around it.
There are counter-intuitive aspects to this that aren't obvious. One is that a strict Low FODMAP diet can worsen SIBO over time by reducing prebiotic fiber diversity, which some of the beneficial bacteria in the colon actually need. Another is that some patients with hydrogen-dominant SIBO feel worse on Low FODMAP not because the diet is wrong, but because they have concurrent fructose malabsorption that predates the SIBO. In those cases, the bacterial overgrowth is a secondary problem, and treating only the SIBO leaves the primary malabsorption untouched. The breath test result matters more than patients realize. Hydrogen-dominant SIBO responds differently to dietary intervention than methane-dominant or hydrogen sulfide–dominant overgrowth. Methane is associated with slow transit and constipation, which changes the therapeutic approach entirely. If you're constipated and doing Low FODMAP, you're often compounding the problem because many Low FODMAP foods are also low in fiber. I've seen patients spiral into severe constipation while following the diet rigidly, thinking they were doing everything right. Practical food substitutions that actually work: swap onions and garlic for garlic-infused oil, since the flavor compounds are fat-soluble and the FODMAPs are water-soluble. Use herbs and spices freely. Replace wheat pasta with rice or corn pasta during the restriction phase. Choose lactose-free dairy or hard aged cheeses, which are naturally low in lactose. Stock up on safe proteins and vegetables like eggs, chicken, fish, zucchini, spinach, carrots, and blueberries. The restriction phase isn't as restrictive as people fear once you stop looking at the exclusion list and start looking at what you can actually eat.
Get the Full Details

The honest limitations: this diet does not eradicate SIBO. It manages symptoms. If you have anatomical issues like adhesions from prior surgery, a motility disorder, or a blind loop syndrome, diet alone will not resolve the overgrowth. In those cases, you need the underlying structural or motility problem addressed first, or the diet becomes a temporary bandage at best. Some patients see significant improvement with antibiotics like rifaximin alongside dietary changes, and that combination is where the evidence is strongest. But even then, relapse rates are high, which is why the dietary work during and after treatment matters. If your primary symptom is bloating and gas without significant diarrhea or constipation, Low FODMAP is the better starting point. If you have significant IBS-like symptoms with alternating bowel habits and you've already tried Low FODMAP without relief, SCD might be worth discussing with your gastroenterologist. If you have known scleroderma, diabetes-related gastroparesis, or post-surgical anatomy, diet is adjunctive at best and you should prioritize motility evaluation and likely prokinetic therapy alongside whatever dietary approach you choose. The biggest practical tip nobody emphasizes enough: keep a symptom and food journal during the restriction phase, but don't obsess over it. Write down what you ate, the portion size, and any symptoms on a simple scale from one to ten. Review it weekly, not daily. Daily tracking creates anxiety that interferes with adherence and makes it harder to follow the diet consistently. Weekly review gives you enough signal to notice patterns without feeding health anxiety.
And one more thing that surprised me repeatedly. Patients often think they need to avoid all fiber during a SIBO flare. That's not correct. Soluble fiber from sources like peeled oats or well-cooked carrots is generally well-tolerated and supports colonic health without feeding small intestinal bacteria in the same way insoluble fiber might. The problem isn't fiber itself, it's the specific fermentable types. Knowing that difference prevents patients from going too low-fiber and creating a secondary dysbiosis in the colon.