Why Your SOAP Notes Look Different Than Everyone Else's
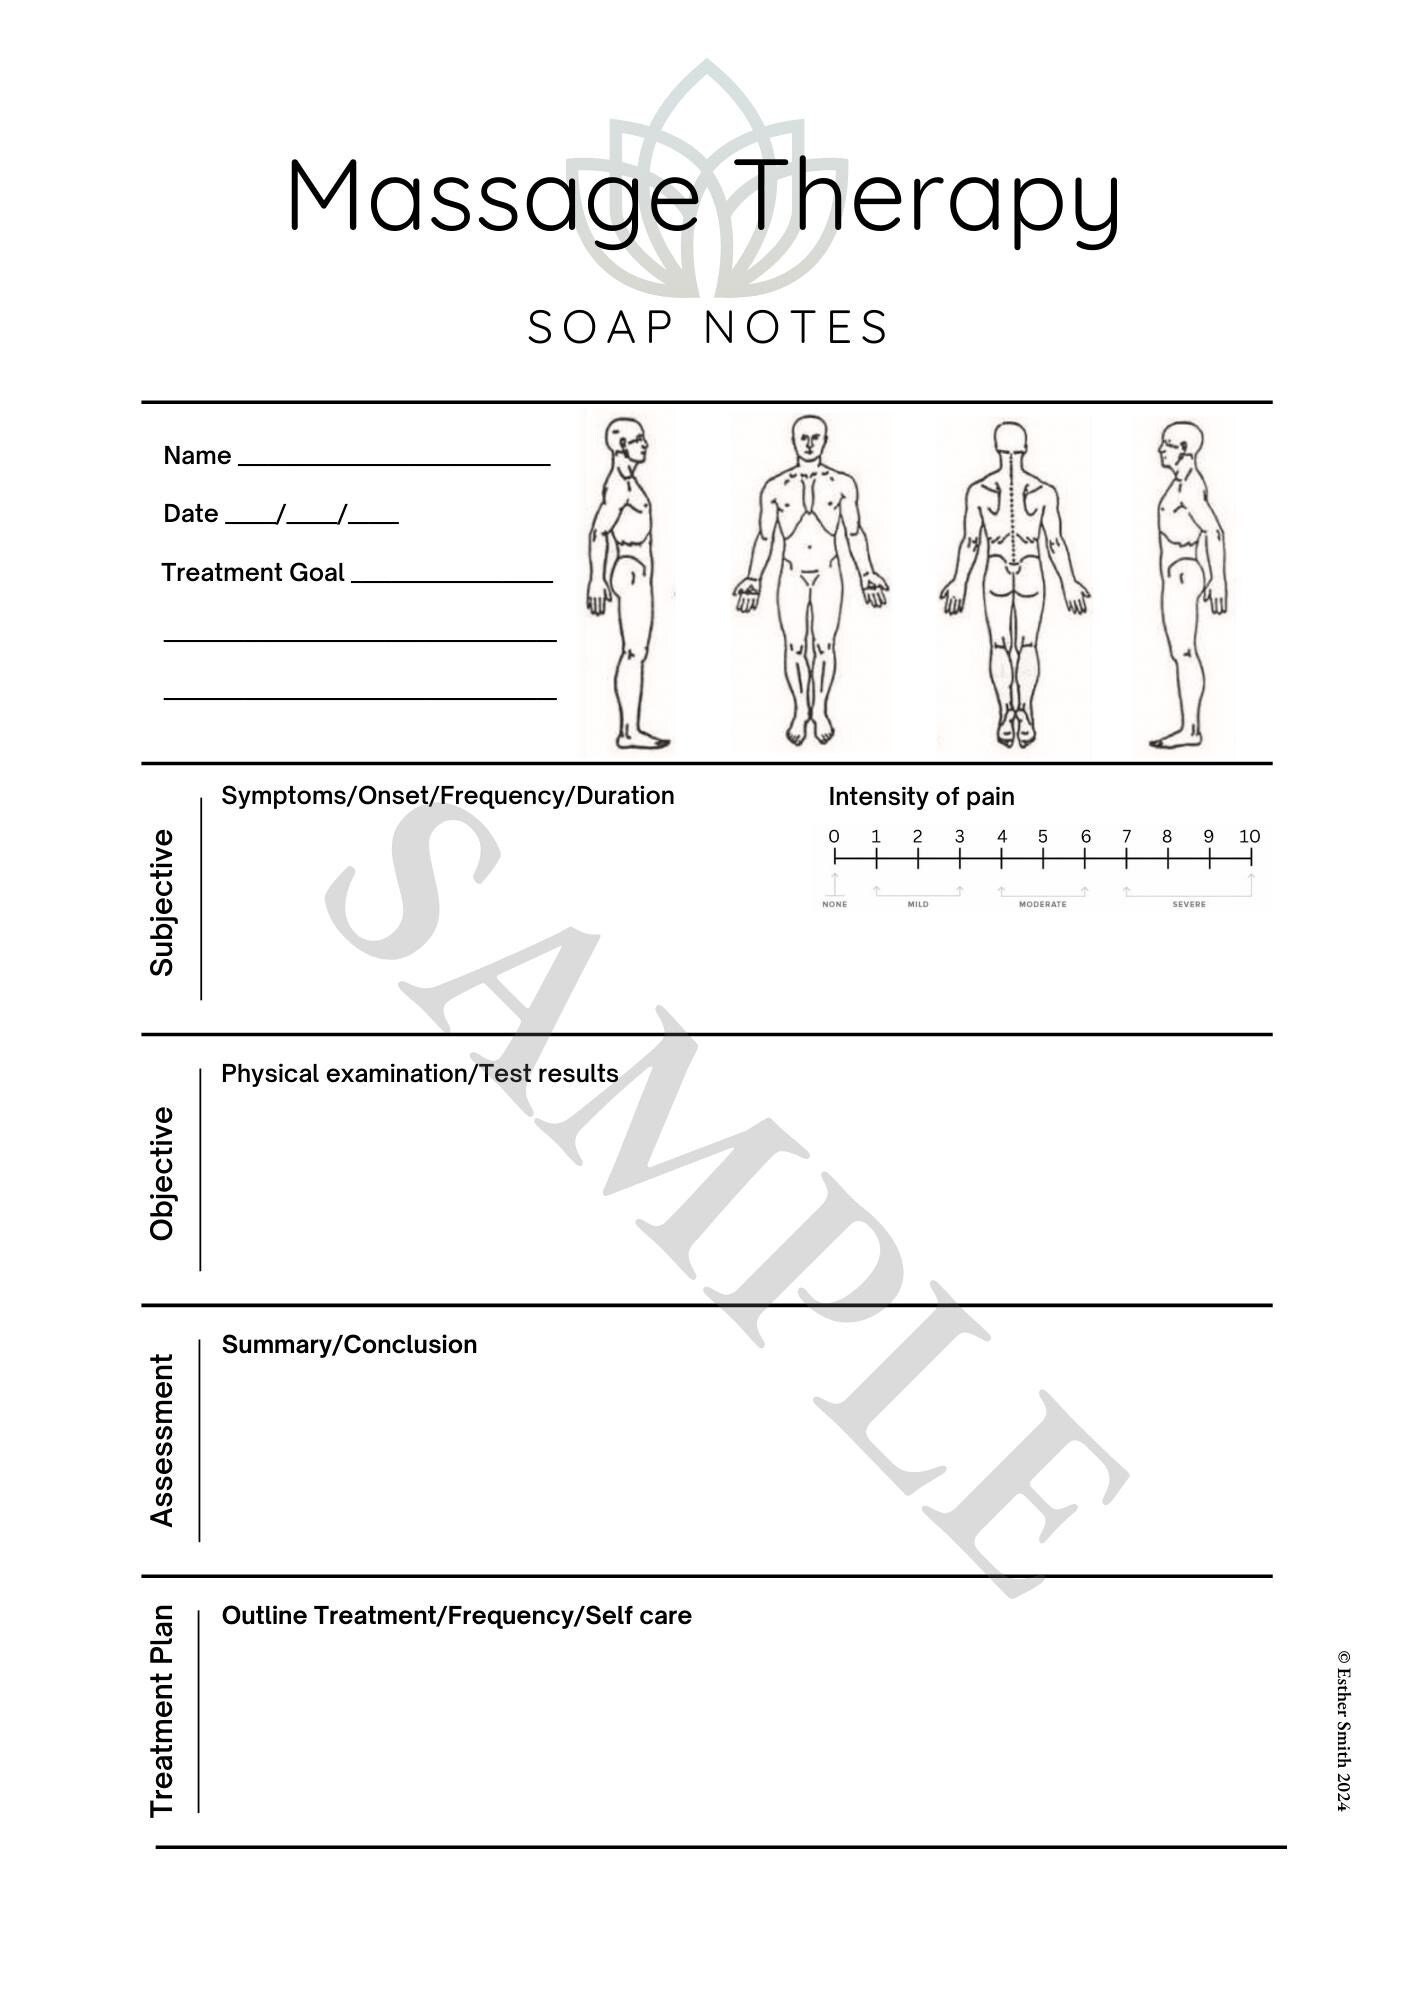
SOAP notes in massage therapy are not some sacred clinical document prescribed by some national board. They are a structuring device. A way to make sure that when you or another provider reads the chart six months later, you actually know what happened. The acronym stands for Subjective, Objective, Assessment, Plan. That is it. It does not guarantee better outcomes. It guarantees you have something to point at. I used to write these for a private practice, then for a physical therapy clinic that insisted on them even though we were doing soft tissue work, not surgery. The biggest problem I ran into was not the format. It was time. A full SOAP note, done properly, takes about eight to twelve minutes per session. Most therapists rush through it in two or three minutes and write garbage that is useless on re-read. I learned to accept that I would never get it perfect, so I built a system instead.
Soap Notes Massage Therapy: What It Actually Looks Like On Paper
Subjective is what the client says. Objective is what you measure or observe. Assessment is your clinical judgment. Plan is what you are going to do next time. Here is a practical version of how that looks in a real massage context: Subjective: Client reports mid-back tightness after desk work. Pain 4 out of 10. Says it gets worse around 3pm. No history of injury to that area. Objective: Visible forward shoulder posture. Trapezius and rhomboids tender to palpation. Range of motion: shoulder abduction to 140 degrees bilaterally, slight guarding on the right.
Assessment: Myofascial restriction in upper trapezius and levator scapulae. Contributing postural pattern likely sustained from workstation setup. Plan: Continue soft tissue work focusing on thoracic extensors. Recommend ergonomic evaluation. Return in two weeks. That took me about five minutes to write once you get comfortable with it. It also tells a second therapist everything they need to know. The version that takes thirty seconds and says "feel good, worked on back" tells them nothing.
Get the Full Details
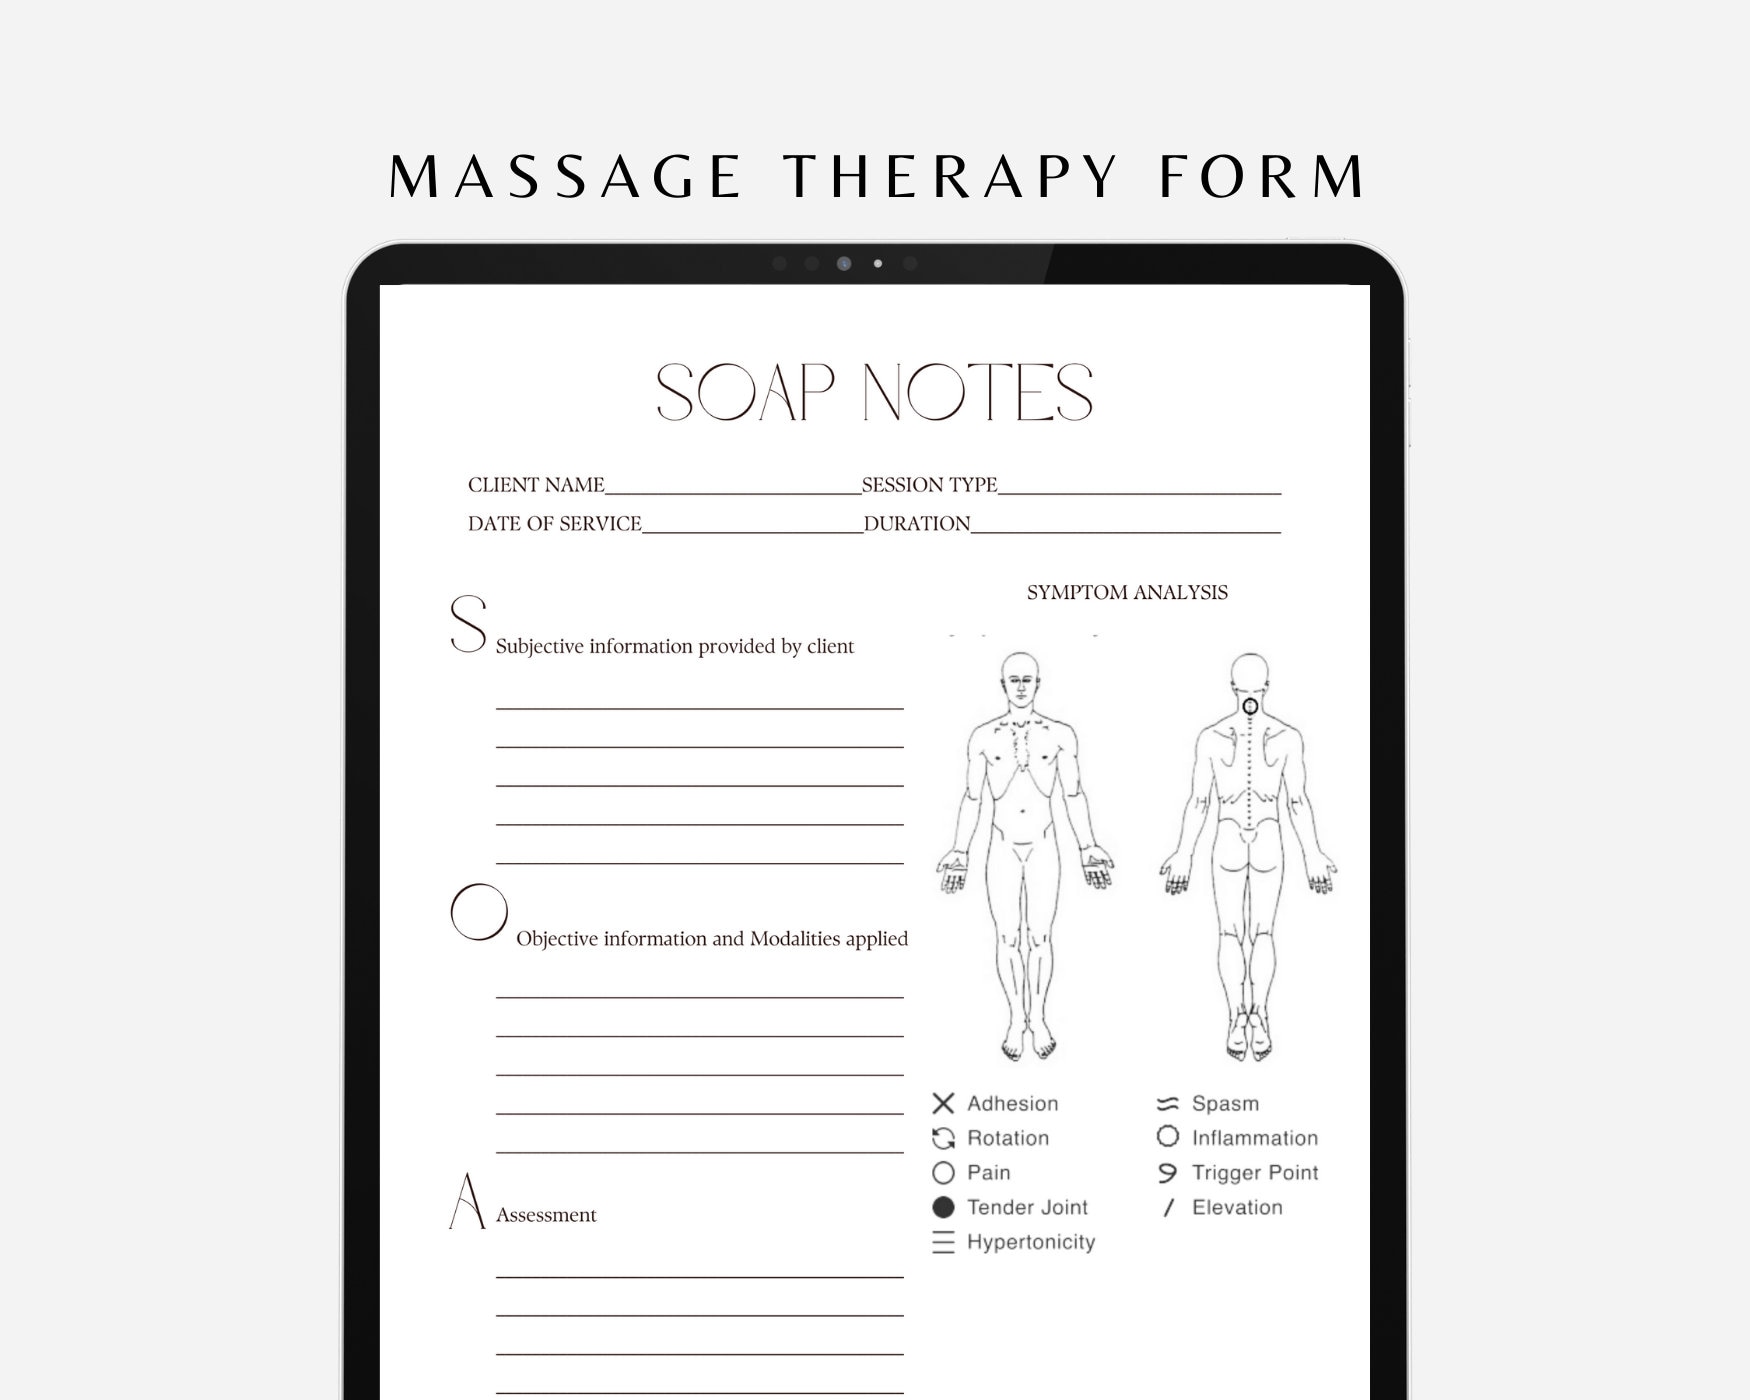
The format can shift depending on your setting. Some clinics require you to include vitals, hydration notes, and skin assessment in the Objective section. Others just want the relevant findings. Know what your board or your employer expects before you start filling out pages of fluff. I spent four months writing full narratives because my first clinic thought that was the standard. Then a new manager came in and demanded I cut everything down to bullet points. I had to rewrite half my charting habits overnight. It was annoying. It also made me better at it.
The Parts People Get Wrong
Subjective and Objective get swapped all the time. That is the most common mistake I see. Subjective is the client's report. Objective is your independent finding. If the client says their neck hurts, that is subjective. If you press the sternocleidomastoid and find trigger points, that is objective. Mixing them up makes the note unreliable for anyone reading it later. Another mistake is making the Assessment section just a restatement of the Objective section. Your assessment should connect the dots. It should say why what you found matters. "Tight upper trapezius" is objective. "Upper trapezius tightness correlating with reported mid-day pain spike and forward head posture" is an assessment. One is data. The other is interpretation. You need both, and you need to know which is which. I also cannot stress enough how important it is to document what you did not do. If a client mentions lower back pain but you only worked the upper body, write that down. Not because you are trying to cover your back, but because the next therapist needs to know you checked and decided against it. One of my clients had recurring lumbar pain that kept showing up in subjective. I documented each time I assessed it as non-contributory to the current presenting issue. When they finally saw a different provider who recommended imaging, that chart history was the only thing that showed I had been paying attention all along.
A Real Workaround I Had to Build
Here is a specific problem I ran into that you will probably encounter too. Insurance reviewers sometimes reject massage therapy notes if they contain subjective language that sounds like diagnosis. Words like "adhesive capsulitis" or "cervical radiculopathy" can trigger a denial if you are not a licensed medical provider in your jurisdiction. I had a whole block of clients whose notes got flagged because I used clinical terms that sounded like I was diagnosing instead of documenting findings. My workaround was simple and it cut my documentation time from about ten minutes per note down to roughly four. I stopped using diagnostic language entirely. Instead of writing "possible rotator cuff tendinopathy," I wrote "pain with resisted shoulder abduction, positive Hawkins-Kennedy presentation." Instead of "lumbar strain," I wrote "paraspinal tenderness at L4-L5 bilaterally, pain with flexion." The meaning is the same. The risk is almost none. Insurance reviewers can read descriptive language all day. They flag terms that sound like a diagnosis from someone who might not be qualified to make one. This also happened to work better for my own clarity. When you describe what you actually feel and measure instead of reaching for a label, you tend to be more precise. I started catching things I had been glossing over. A client who always had asymmetrical scapular motion. Another whose shoulder pain was clearly related to thoracic spine restriction rather than the shoulder itself. Better notes led to better treatment decisions. That was the actual benefit I did not expect.

How Long This Actually Takes And How to Speed It Up
A thorough SOAP note for a standard sixty-minute session runs about eight to twelve minutes if you are typing it fresh. If you use templates, it drops to four to six. If you use voice dictation or a structured app, it can go under three. I recommend building your own template with checkboxes for common body regions and common findings. You should still write the assessment and plan by hand or with custom text each time. That is where the clinical value lives. The rest can be standardized. One thing that helps: stop trying to make every note read like a story. Clinical notes are reference documents, not narratives. Bullet points are fine. Fragments are fine. "Tender to palpation, bilateral trapezius" is a complete thought. You do not need to write "The client reported that the bilateral trapezius muscles were tender to palpation." Nobody reads it like that. Nobody needs it like that.
When SOAP Notes Fall Short
They are not a substitute for actual clinical reasoning. A beautifully formatted SOAP note cannot compensate for a session where you did not listen to the client or did not perform a proper assessment. I have seen therapists with immaculate charts who clearly had no idea what they were doing. The note was perfect. The treatment was not. They also do not capture everything that matters in a session. The therapeutic relationship, the client's response to touch, the nonverbal cues, the things that made you change your approach mid-session. None of that goes in a SOAP note unless you force it in, and forcing it in tends to make the note unreadable. Some therapists keep a separate brief narrative section for that. I did, and it helped more than I expected when reviewing my own cases later. If you are working in a setting that requires billing or insurance submission, you may find that SOAP notes alone are not enough. Many payers require additional documentation: treatment times by body region, CPT code justification, progress notes over multiple sessions. Check what your specific context demands before you assume the standard SOAP format covers everything.
The core skill is not writing the note. It is noticing enough during the session that you have something worth writing down. Everything else is just formatting.



