What You Actually Need to Know About Softwave Therapy Side Effects
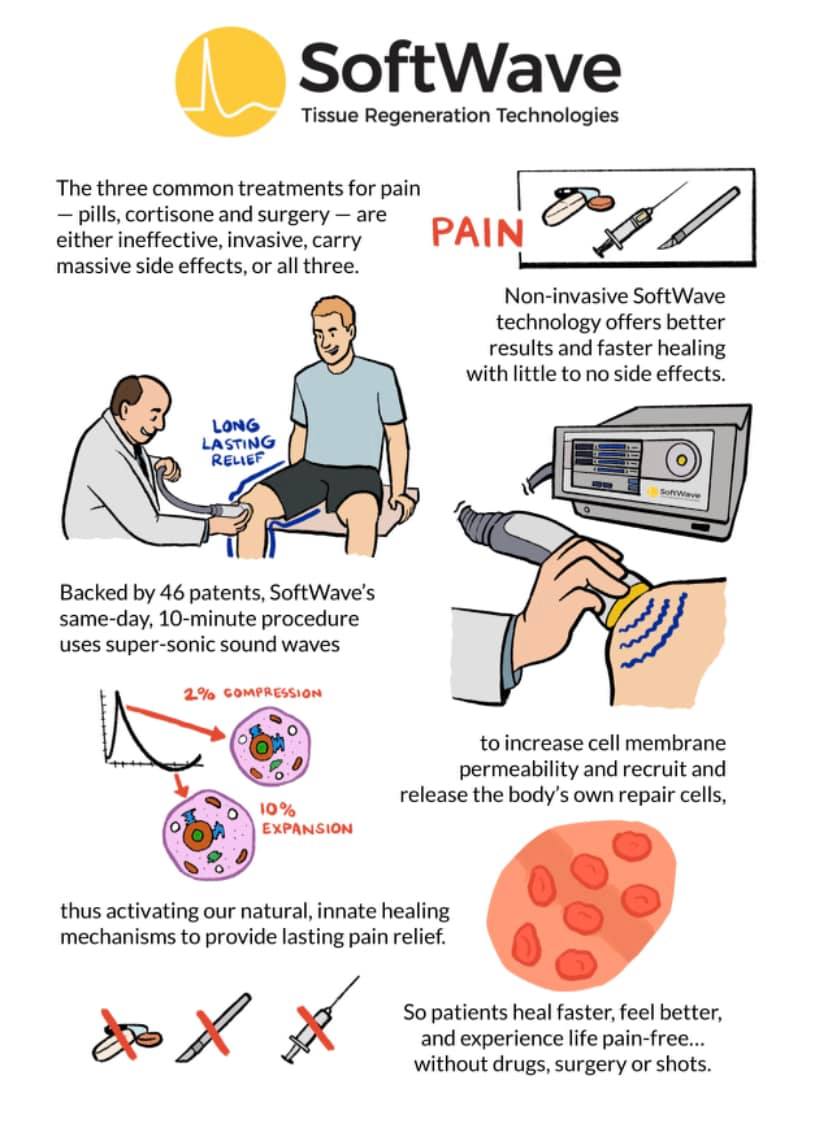
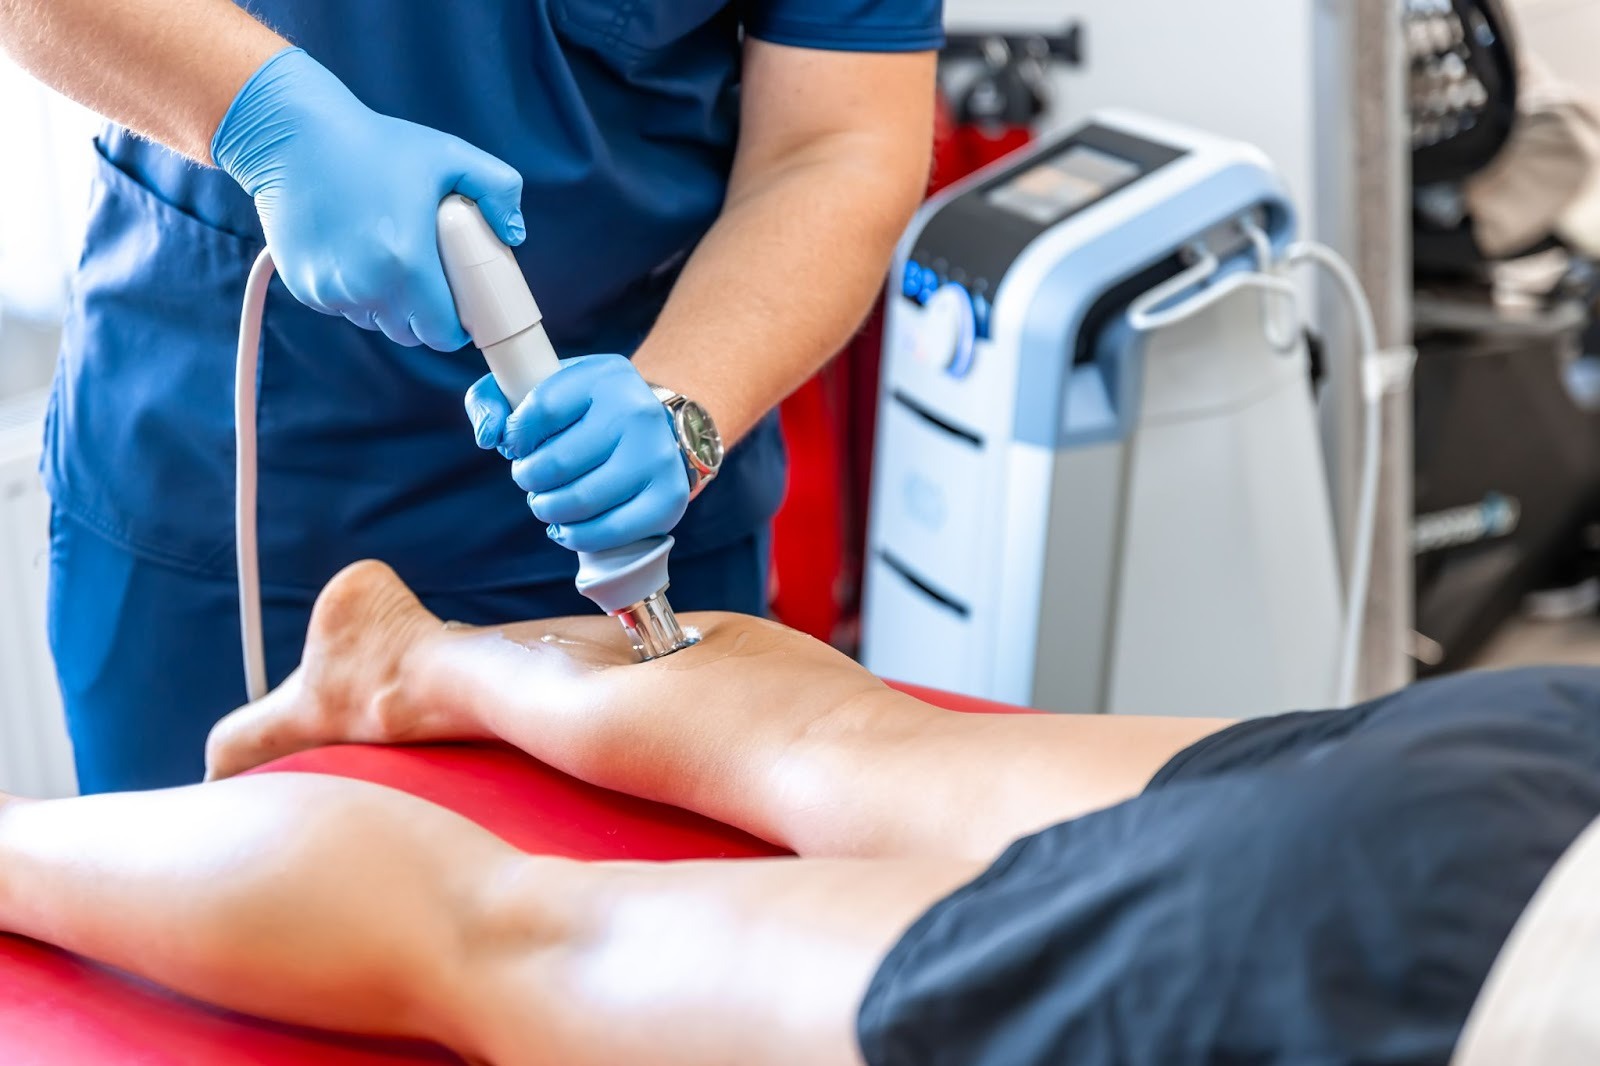
Softwave therapy is a form of low-intensity extracorporeal shockwave therapy (Li-ESWT). It uses focused acoustic waves to stimulate tissue repair, primarily in orthopedic and urological applications. The side effects are generally mild compared to higher-intensity shockwave protocols, but they are not zero. Here is what actually happens in practice when patients go through a treatment course, along with the complications I have seen repeat across different clinics.
Common Softwave Therapy Side Effects
The most frequent side effect is localized tenderness at the application site. This peaks within the first 24 hours and usually resolves on its own within three to five days. Patients describe it as a deep bruise-like ache. It is not dangerous, but it can be uncomfortable enough that people want to stop treatment early. I have seen this multiple times. The workaround is simple: advise the patient to avoid NSAIDs for 48 hours after treatment, because those compounds blunt the inflammatory cascade that the therapy is trying to trigger. Paracetamol works fine if something is needed.
Other side effects include minor swelling, redness, and occasionally small pinpoint bruises from capillary rupture under the skin. These are cosmetic and fade within a week. Numbness or tingling around the treatment area is less common but happens, especially when the probe is positioned near superficial nerve branches. In most cases it resolves within days, but I have encountered one case where paresthesia lasted about three weeks before fully subsiding. That patient had been treated for plantar fasciitis and the applicator head had been pressed too close to the medial plantar nerve. Adjustment of the angle and reducing contact pressure fixed it going forward.
Why the Protocol Matters More Than Most Clinics Admit
Most side effect discussions focus on the device itself, but in reality the operator settings and anatomy knowledge drive the risk profile far more than the machine. Shockwave therapy delivers energy in joules per square millimeter (J/mm²). Low-intensity protocols typically operate between 0.08 and 0.25 J/mm². Pushing toward the upper end of that range increases both efficacy and adverse effects in a nearly linear fashion. The mistake I see repeatedly is clinics cranking the intensity to chase faster results without accounting for tissue tolerance. A patient with thin subcutaneous fat over the treatment zone — say, a lean athlete getting treatment for a shoulder impingement — will experience significantly more bruising and soreness than someone with more padding in the same anatomical region, even at identical settings.
Another thing that catches people off guard is the delayed onset of pain. The initial treatment often feels fine or even pleasant due to the neuromodulatory effect on nociceptors. Then 12 to 24 hours later the tissue reaction kicks in and the patient calls the clinic saying something is wrong. This is a normal physiological response, not a complication. But because the timing is delayed, patients and some clinicians misattribute it to an error. Documenting baseline pain levels before each session and tracking post-treatment soreness on a simple scale helps separate normal recovery from actual adverse events.
Less Common but Worth Knowing About
Headaches can occur after cervical or upper thoracic treatments due to referred tension from the fascial layers. It is uncommon but well-documented. Fatigue is another one I see more often than expected. The body is mounting a localized healing response, which draws metabolic resources. Some patients report feeling unusually tired for one to two days after a full treatment session, particularly if multiple areas were addressed in one visit.
There is also the issue of flare-ups of the underlying condition. A patient coming in for lateral epicondylitis might find their elbow pain intensifies during the first two to three sessions before it starts improving. This is the so-called irritation phase and it is a recognized part of the mechanism. I once had a patient who stopped treatment at session two because she thought the therapy was making things worse. She called me three weeks later saying she wished she had pushed through because by session four the trend had clearly shifted. Now I make sure to warn every patient about this possibility upfront.
When Softwave Therapy Is Not the Right Call
I need to be straight about the limitations. This therapy does not work for everything and it can make certain conditions worse. Coagulopathy or use of blood thinners is an absolute contraindication — the bruising and bleeding risk becomes unmanageable. Treatment over malignant tissue is another hard stop. Pregnancy rules out treatment over the abdominal or lumbar region. Open growth plates in pediatric patients should not be targeted. Infections at the treatment site are a clear no.
The therapy also has a steep drop-off in effectiveness for certain pathologies. Acute tendon ruptures will not benefit and delaying surgical consultation in favor of shockwave sessions wastes valuable time. Calcific tendinitis responds variably — some cases resolve completely, others barely budge. I would rather see a patient with calcific shoulder tendinitis get a ultrasound-guided barbotage first and consider shockwave only as an adjunct if the calcium burden is still significant afterward. That sequence tends to produce better outcomes than shockwave alone.
For chronic pelvic pain or erectile dysfunction indications, the evidence base is thinner and the side effect profile shifts slightly. Perineal and pelvic floor applications carry a risk of transient genital numbness and urinary urgency. These are rare but they matter to patients who are already dealing with sensitive quality-of-life issues. I always disclose those possibilities clearly before consent.
Practical Takeaways
If you are considering softwave therapy, the key is finding a practitioner who understands dosing, anatomy, and patient selection — not just someone with access to the equipment. Ask about their typical energy flux density settings, how they adjust for individual tissue characteristics, and what their protocol is for managing the post-treatment flare-up window. Track your own symptoms daily for the first week after each session. If side effects persist beyond two weeks, escalate rather than pushing through. Most Softwave Therapy Side Effects resolve within the first few days, but persistent symptoms warrant reassessment of the treatment plan.
Gallery Softwave Therapy Side Effects
Is SoftWave Therapy Safe? Side Effects, Risks, and Recovery ...
SoftWave Therapy | Active Life Project, Collingswood, New Jersey
Understanding the Risks: Unveiling the Side Effects of Corticosteroid ...
What is SoftWave Therapy? SoftWave Therapy vs Shockwave Therapy ...
The Science of Softwave Therapy: How It Works and Why It's Effective ...